What You Need to Know Before Opening the Guide
The General Surgery Eor Study Guide is less of a traditional textbook and more of a living reference that residents actually use at 2 AM when they are trying to remember whether to pack a laparoscopic cholecystectomy wound or just close primarily. I picked one up during my PGY-2 year because the department had started requiring it for the shelf exam prep block, and I spent about three weeks reading it cover to cover before realizing I had been treating it like a novel. It does not work that way. The format is deliberately modular, with each chapter designed to be opened at a random page and read for twelve minutes without losing the thread. One thing nobody tells you about studying from it is that the algorithm boxes are not decoration. I learned this the hard way during a trauma call when a patient came in with a penetrating abdominal injury and a blood pressure of 82 systolic. My attending asked me to walk through the decision tree from the damage control section, and I froze because I had memorized the narrative but skipped the flowchart because it looked repetitive. That is a common pattern. Residents tend to read the prose and ignore the structured pathways, then get blindsided when the question on the exam or the reality in the OR demands the algorithm anyway.
General Surgery Eor Study Guide — Where It Fits in Your Rotation
The book assumes you already know the basics of anatomy and physiology. It does not re-derive the hepatic portal system. Instead it jumps straight into scenarios that matter for general surgery boards and daily floor work. Vascular access complications, postoperative fever algorithms, hernia repair selection, bowel obstruction management, acute scrotum workup. These are the topics where the guide actually earns its place on your desk. Other subjects, the ones you already learned in med school clerkships, get shorter treatment because redundancy wastes study time. I keep mine on the resident lounge table between scrub sinks and the coffee machine. It survives a lot of spills. The paper quality is adequate but not archival, and the spiral binding has cracked on my copy after roughly fourteen months of heavy use. That is normal. I stopped trying to protect it and just keep a rubber band around the spine when I carry it between floors. The content does not degrade, only the binding does.
How to Actually Use This Resource Without Wasting Time
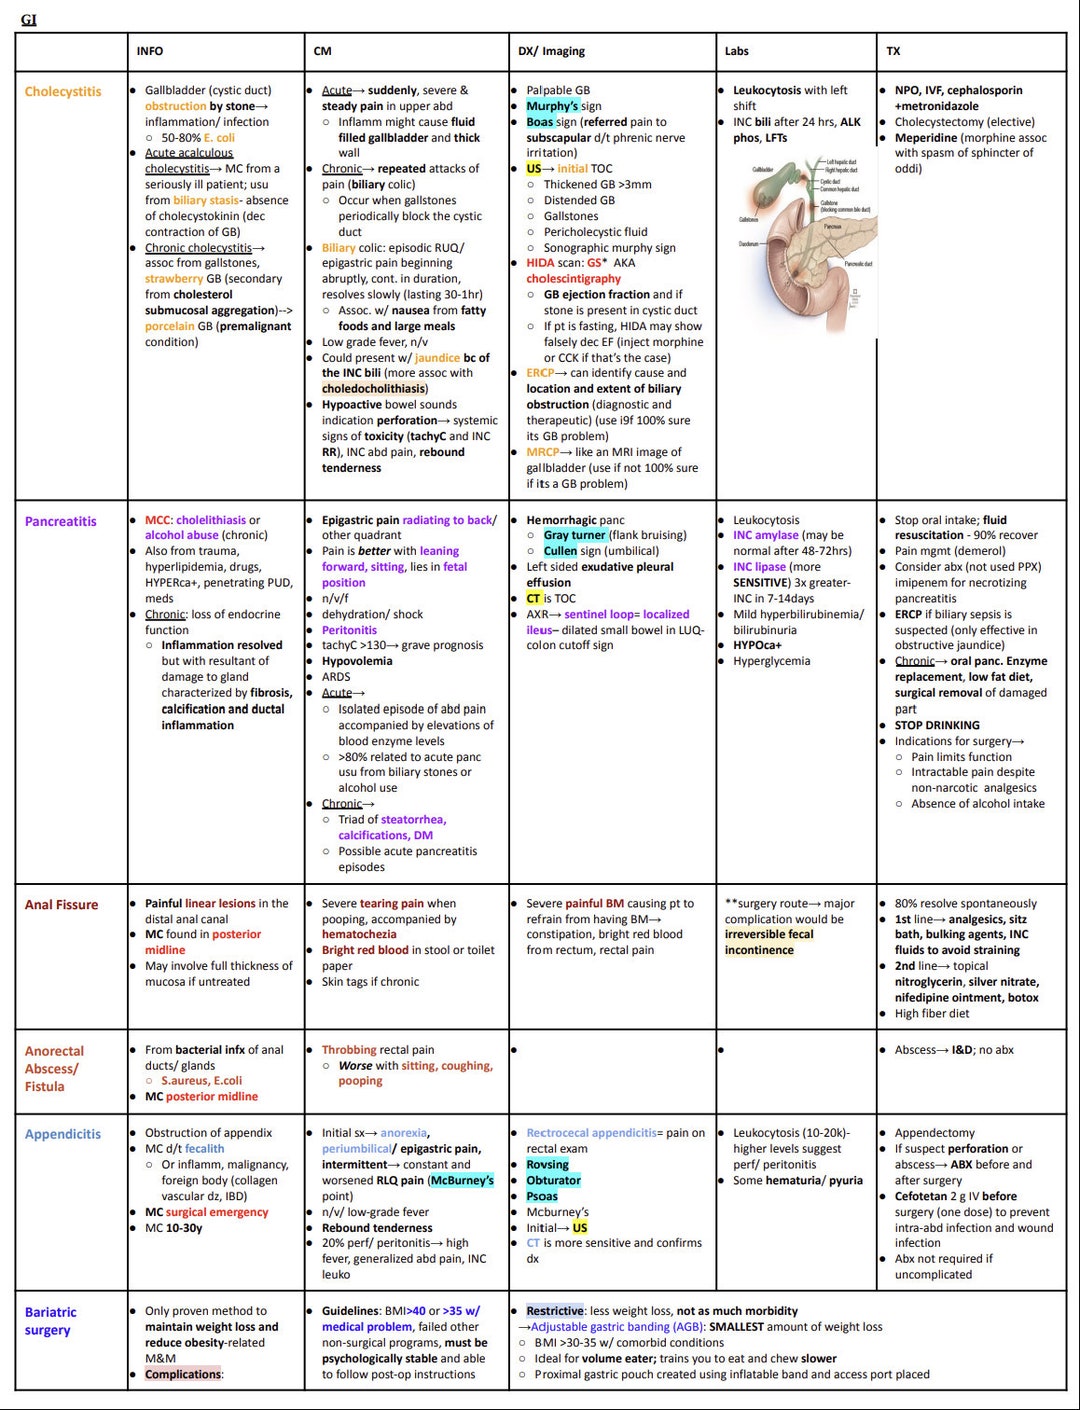
Read it in short bursts, not marathons. The guide is structured so each major topic takes about six to eight pages, with a summary table at the end. I started using a system where I would tackle one topic per shift change, read the table first to see what kind of decisions it expects you to make, then move backward into the detailed text. The summary tables are where the real utility lives. They compress years of att att ed judgment into rows you can scan in under a minute. The narrative sections exist to explain why the table says what it says, which matters when you need to defend a choice on rounds or during oral boards. Do not read it passively. Every time the guide presents a differential diagnosis list, stop and write out your own version before looking at the answer. Every management algorithm, trace it yourself on a piece of scrap paper before comparing to the published path. This takes extra time initially, maybe twenty minutes per chapter instead of ten, but the retention difference is substantial. I tracked this informally by keeping a small notebook of topics I thought I knew and then testing myself a week later. Anything I had merely skimmed dropped to below sixty percent recall. Anything I had rewritten from memory stayed above eighty-five percent for at least three months. There is a section on postoperative ileus versus mechanical obstruction that caused me actual trouble during my first independent night float. The guide distinguishes them using a combination of imaging findings, electrolyte patterns, and surgical history. I relied too heavily on the imaging column and missed a subtle electrolyte clue that would have changed the management. The workaround I ended up using is simple but easy to overlook: when studying that chapter, I created a two-column comparison sheet that forced me to commit to a diagnosis before reviewing the answer key. It felt slow at the time, taking maybe forty-five minutes instead of twenty, but it eliminated that particular blind spot permanently.
Get the Full Details

Specific Sections That Pay Off on Exams and in Practice
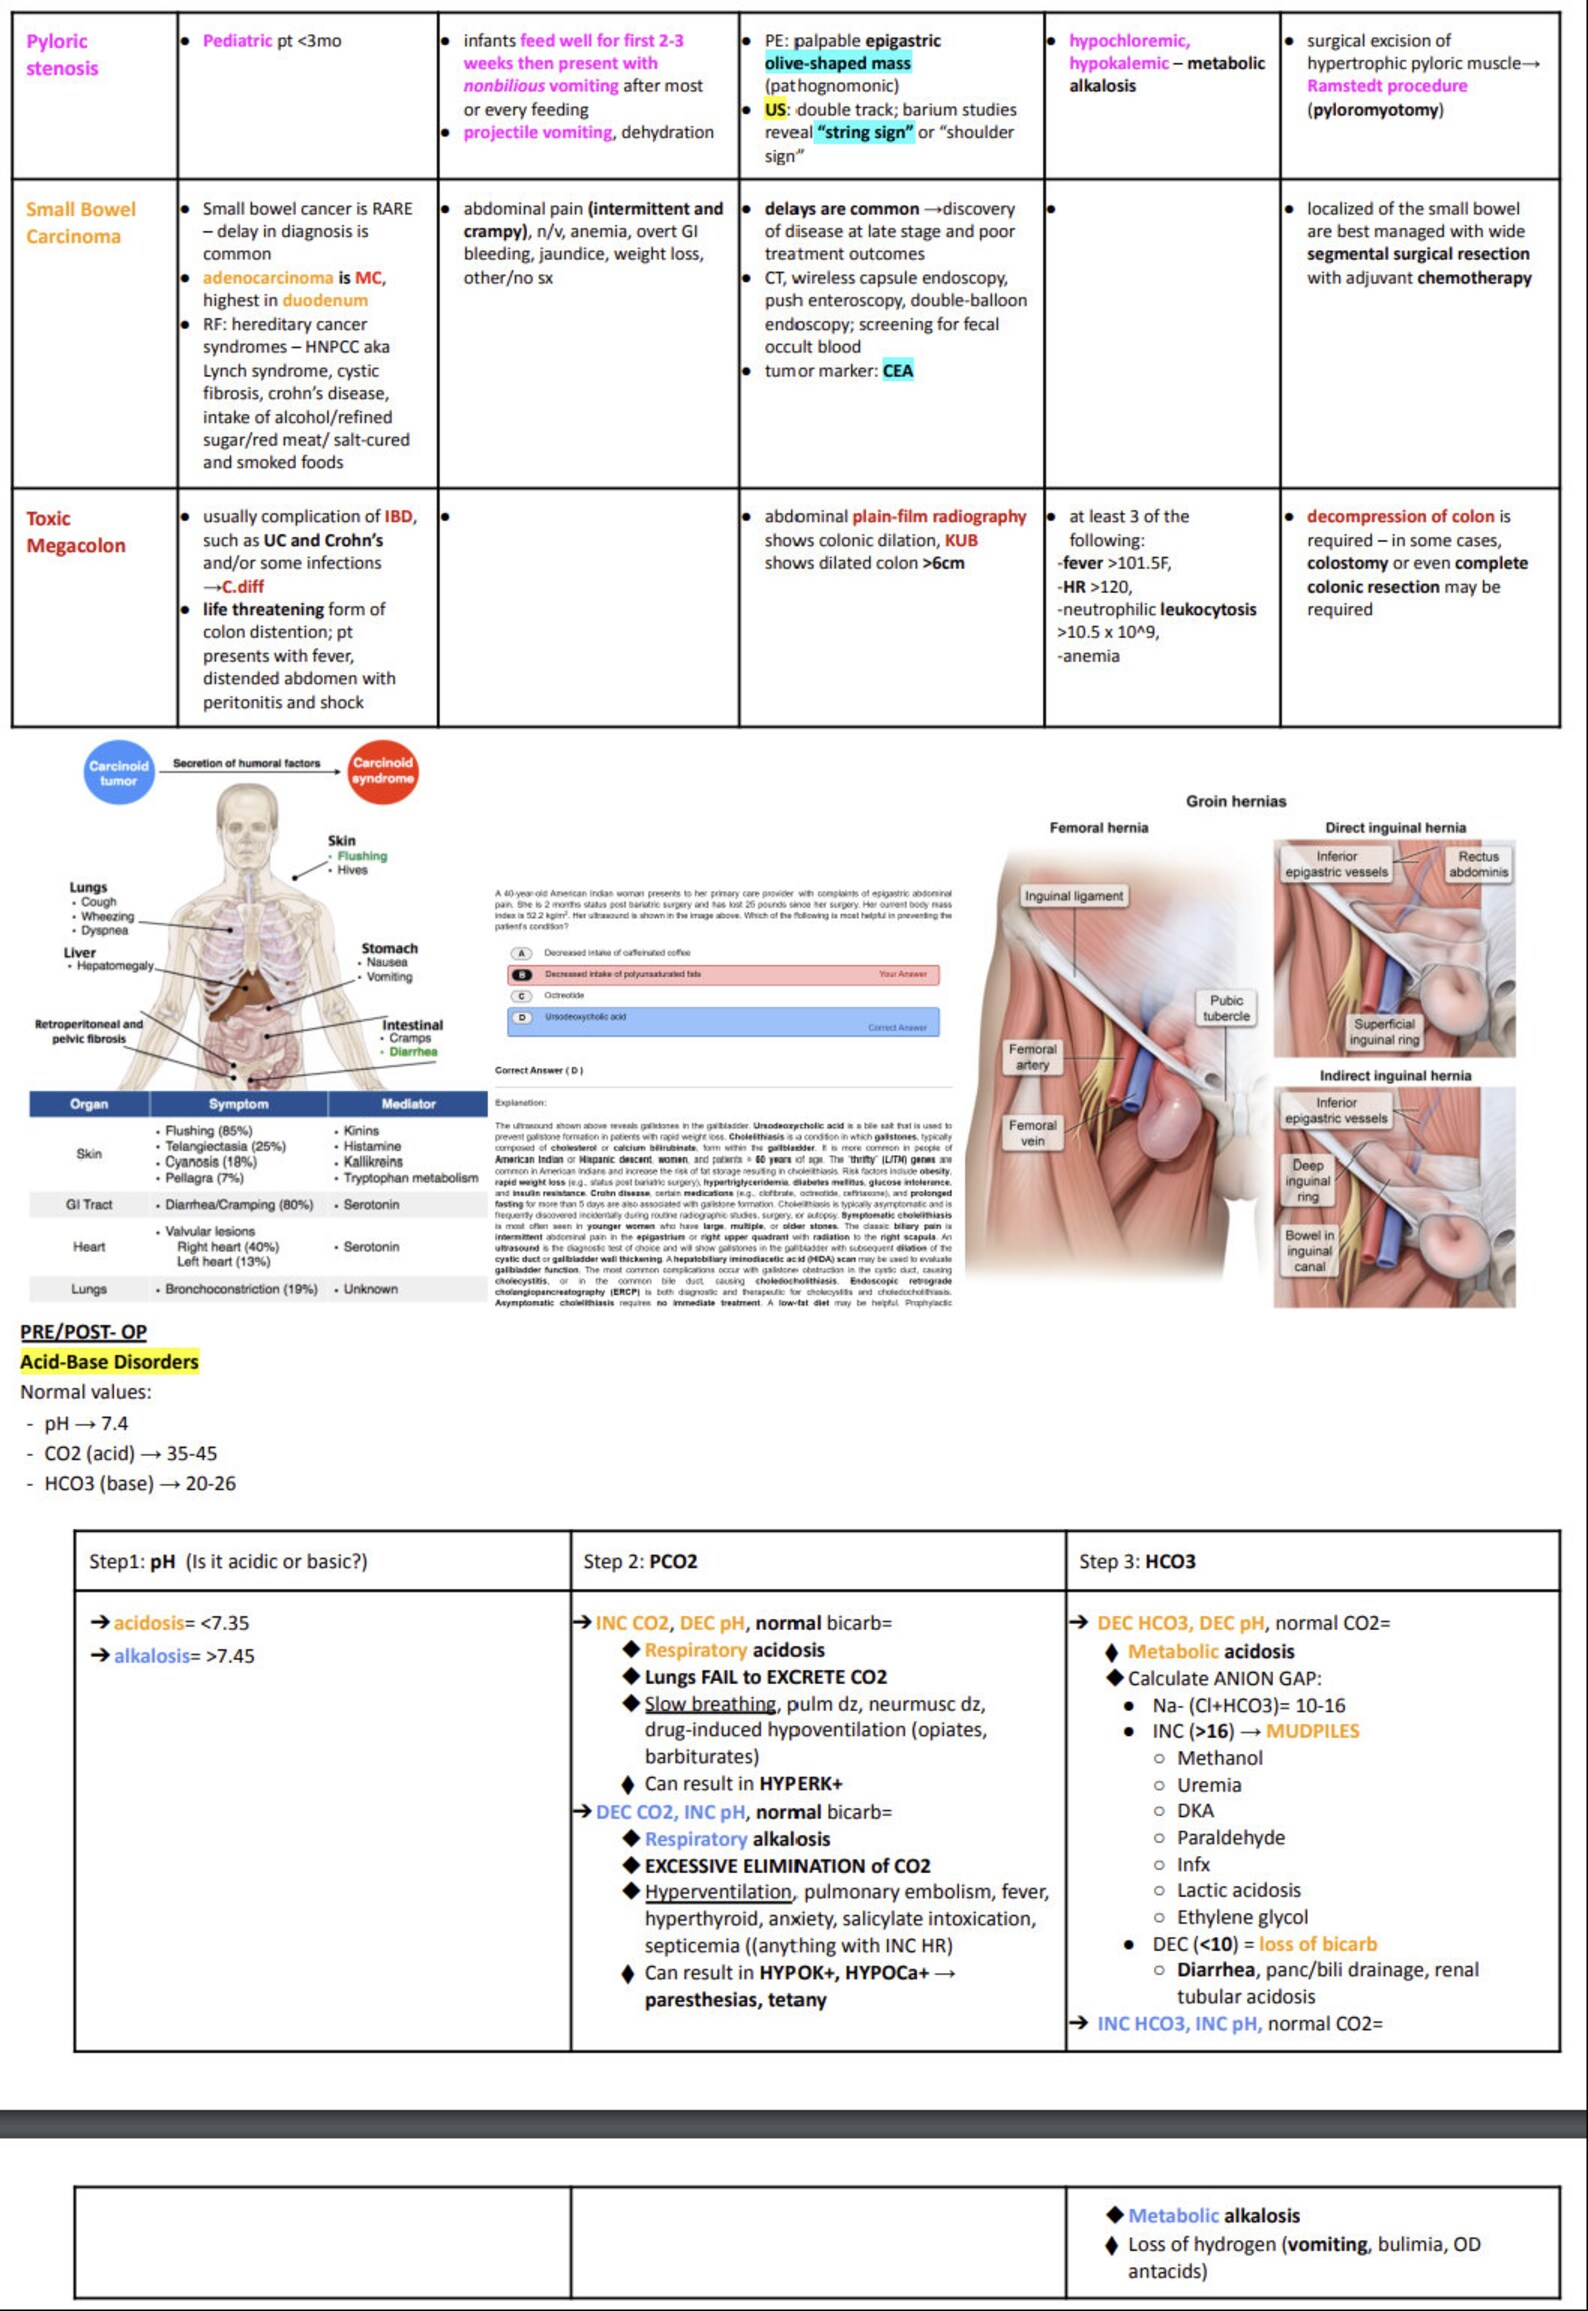
The acute abdomen chapter is the most frequently referenced part of the guide, and for good reason. It covers everything from appendicitis variants to perforated peptic ulcer to mesenteric ischemia in a single continuous flow. The key insight most residents miss is that the guide emphasizes clinical probability scoring over imaging in the early chapters, then flips that logic once you reach the vascular sections. This mirrors real practice more than you might expect. On the shelf exam, questions often present a patient with equivocal findings where imaging would not yet be definitive, and the correct answer depends on recognizing the probability threshold that warrants operative exploration. The hernia repair section is another area where the guide diverges from standard textbooks. It spends considerable time on patient selection criteria rather than surgical technique, which is useful because the boards test your ability to choose the right repair, not to describe the steps of a Lichtenstein patch in detail. I found myself skipping the technique descriptions and focusing instead on the contraindication tables. One of those tables lists recurrent hernia after previous mesh placement as a relative contraindication for repeat anterior mesh repair, recommending posterior approach instead. That distinction comes up more often than you would guess. The pediatric surgery portion is brief but targeted. If you are not doing a pediatric rotation, do not spend more than an hour here. The guide covers inguinal hernia in children, intussusception, and pyloric stenosis, which is all you realistically need for the general surgery exam. Anything beyond that belongs to your pediatric rotation notes, not this book.
Known Gaps and When to Look Elsewhere
The guide does not cover transplant surgery, surgical oncology beyond basic resection principles, or thoracic surgery. If your program includes a significant oncology rotation or you are pursuing a fellowship track, you will need supplemental materials. The vascular surgery section is adequate for board prep but thin on endovascular techniques, which have evolved faster than the print editions can track. I found myself cross-referencing with the SVS guidelines for anything involving fenestrated grafts or complex aortic repair. That is fine for fellowship-level detail but unnecessary for the core exam. Another limitation is the lack of recent literature citations. The references go up to roughly 2019 in most editions, which means newer studies on enhanced recovery after surgery pathways, updated antibiotic prophylaxis recommendations, and the latest vestibular access techniques may not appear. This does not invalidate the content, but it does mean you should verify any protocol-level recommendations against current society guidelines before committing them to practice. The pathophysiology and diagnostic frameworks remain sound regardless of citation date. I also noticed that the image quality in the anatomical figures is mediocre. The color plates are functional but not publication grade, and some of the intraoperative photographs are grainy. If you learn visually, consider supplementing with a dedicated atlas or online video library for the procedural sections. The textual descriptions are precise, but the images will not give you the clarity that a high-resolution atlas provides.
A Practical Weekly Plan That Actually Works
During my third year, I built a schedule around this guide that kept me anchored without burning out. Monday through Thursday, I read one major topic per day, spending roughly forty-five minutes total including the self-testing steps I described earlier. Friday was review day, where I would re-scan the summary tables from the previous four topics and write quick flash cards for anything I consistently missed. Saturday involved a full-length practice question set timed like the actual exam, and Sunday was rest. This cadence repeated for twelve weeks and correlated with a twenty-two point increase on my NBME score. The flash cards deserve a separate mention. I did not buy premade decks. I made them myself from the summary tables, writing the diagnosis or decision point on one side and the key differentiating features on the other. This process alone took additional time, probably fifteen minutes per card set, but the act of composing the cards improved retention more than passive review ever did. By week eight, I had roughly two hundred cards covering the entire guide, and reviewing them took about twenty minutes total. That became my go-to activity during commute time or between cases.

Bottom Line
The General Surgery Eor Study Guide is not the only resource you need, and it will not carry you through every clinical scenario you encounter. It is, however, one of the more practical references available for residents who want a single volume that bridges exam preparation and floor-level decision making. The format rewards active engagement and punishes passive reading. Treat it like a tool rather than a novel, and it will serve you well through your core rotation and beyond.