Building a Generic Physical Exam Form That Actually Works
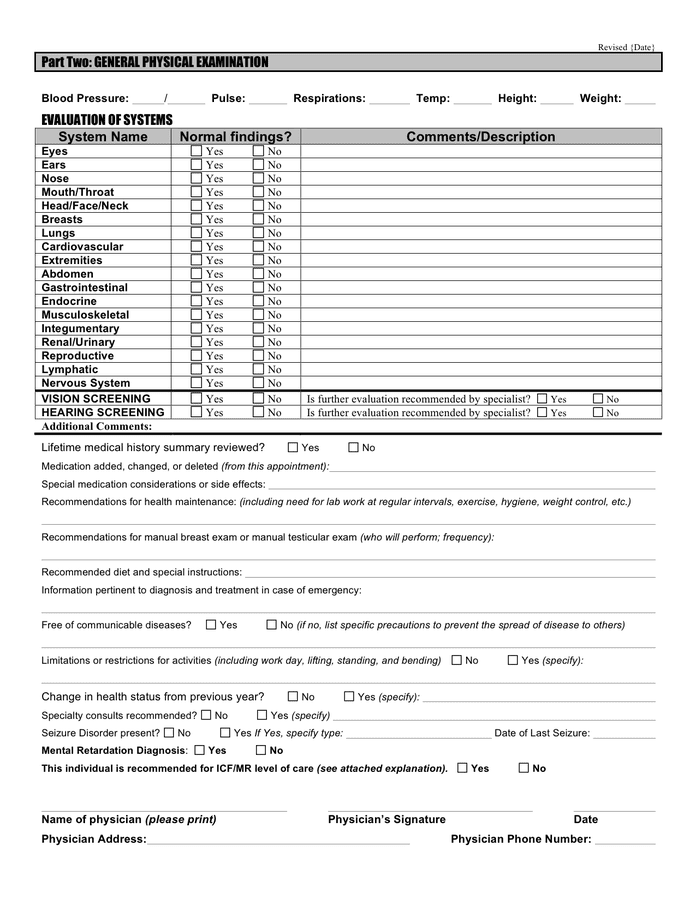
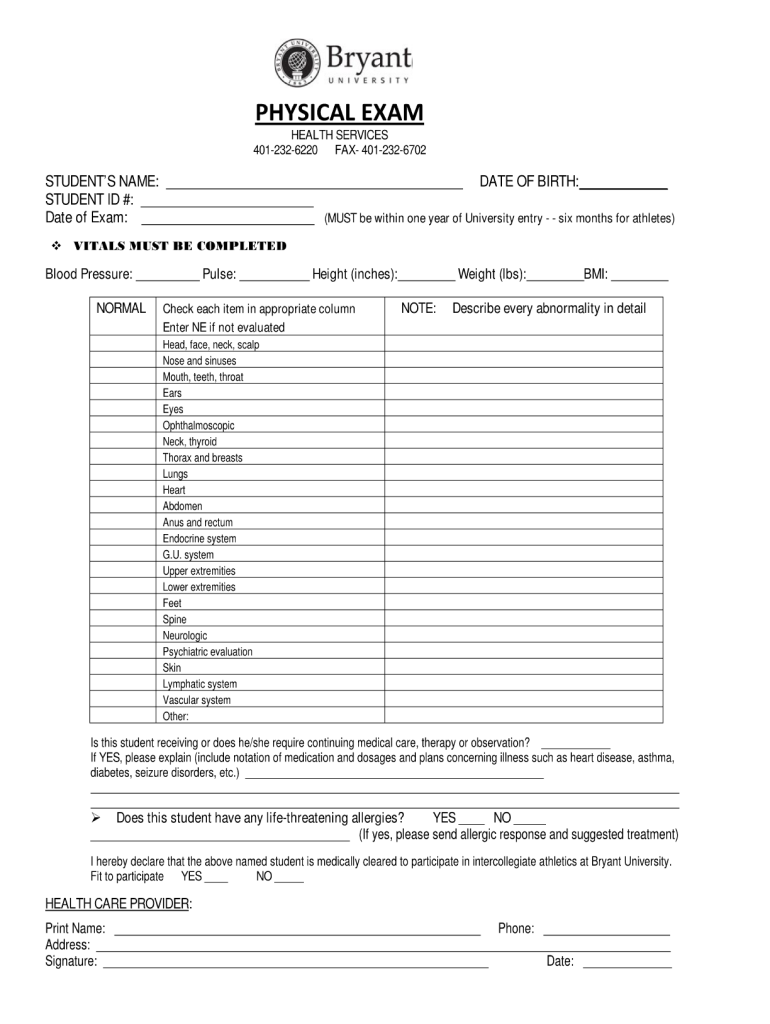
I spent years trying to make physical exam forms that doctors would actually fill out. Most of them end up unused because they're either too rigid or too complicated. The trick isn't making it look professional. It's making it impossible to mess up. A Generic Physical Exam Form needs to cover the basics without forcing every clinician to adapt it to their own quirks. You want vitals, general appearance, and system-by-system findings. Nothing fancy. If you've ever watched someone struggle through a form they've never seen before, you know the frustration. They'll skip sections or circle vague answers because the options don't match their actual workflow. The fields I usually include are: patient demographics, date of exam, examiner name, chief complaint, vital signs (blood pressure, heart rate, respiratory rate, temperature, oxygen saturation, pain score), general appearance observation, and each body system broken into head, eyes, ears, nose, throat, cardiovascular, respiratory, gastrointestinal, musculoskeletal, neurologic, skin, and lymphatic. Each section gets a normal/abnormal toggle plus a free-text note field. That's it. Nothing else matters for the baseline version.
I built one once where the client wanted everything packed into a single page. They thought it was about saving paper. It wasn't. It was about speed. But when you cram an entire exam onto one page, you lose the ability to track findings over time. I learned that the hard way when a follow-up patient came back three months later and the prior exam sheet was just illegible scribbles because the provider had rushed through it. Now I recommend two pages minimum: one for vitals and general, one for the full system review.
Setting Up the Structure
Start with the format you're using. If this is digital, think about how your EHR or survey tool handles conditional logic. If you're building this from scratch in something like Google Forms or a PDF builder, you need branching logic that hides sections based on responses. For example, if the provider selects abnormal under cardiovascular, the form should immediately prompt for specific findings rather than burying that request at the bottom. Don't use checkboxes for everything. Checkboxes create ambiguity. Is a checked box confirming normal? Or is it marking an abnormality? This is a mistake I see constantly in forms that people copy from hospital templates. I switched to radio buttons for normal/abnormal paired with a text field that only appears when abnormal is selected. The workflow becomes straightforward: pick the status, then describe if needed. It takes about three seconds per section instead of four. The date field should auto-populate but allow manual override. I found that providers often schedule exams on one day and perform them on another, so pre-filling the current date caused more errors than it prevented. Let them correct it. It's a one-click fix compared to the rework when the wrong date ends up on a legal document.
Get the Full Details

Common Problems and How to Fix Them
One issue that always comes up is the musculoskeletal section. Every provider has a different approach. Some start with inspection, others with range of motion, and a few document gait separately. If your form forces a linear sequence, it creates friction. The workaround is to label each subsection clearly but avoid numbering them in a way that implies order. Use category headers instead: inspection, palpation, range of motion, strength, gait. Let the provider jump around. They know what they're doing. Another problem is the neurologic exam. It's easy to make it either too detailed or too vague. A form that asks for twelve individual reflex locations usually gets half filled out because most providers screen just the major ones. Conversely, a form that says "neuro grossly intact" with no guidance turns into a liability risk. The solution is listing the standard reflex sites as checkboxes (biceps, triceps, brachioradialis, patellar, Achilles) with a "not tested" option and a notes field for anything beyond the screening. This gives structure without demanding completeness for cases where a full exam isn't indicated. I once worked on a form where the client insisted on including a psychiatric screening section. Half the providers just skipped it or wrote "N/A" because the questions didn't fit their patient population. After six weeks of tracking, we removed the section and replaced it with a simple mental status observation line: alert and oriented, mood and affect appropriate, speech and thought process clear. It covered the same ground in two seconds instead of dragging out a mini-mental exam that nobody had time for. Sometimes less is genuinely better.
Digital vs. Paper Considerations
If you're building this for an electronic system, validation rules matter more than you'd think. Set required fields for vitals. A physical exam without blood pressure or heart rate is incomplete, plain and simple. Don't let providers submit without it. But don't require free-text notes on every single system unless you have a reason to believe they'll actually use them. That habit leads to form abandonment. For paper forms, use a clean sans-serif font at 11 points minimum. Handwritten notes on cramped forms are unreadable and create problems downstream during audits or when another provider tries to follow up. I've seen insurance claims delayed because a provider's cursive on a vitals table was mistaken for a different number. It happens more often than you'd expect. Stick to printed text for the form fields and leave blank space for handwriting only where it's necessary. Field sizing is another detail people overlook. The free-text note areas need to be deep enough for an actual paragraph, not a single line. When you restrict notes to one line, you get fragments. "R-L-L-R" for lung sounds tells someone nothing if they're not already in the room. Two lines minimum for each system note prevents that kind of lazy documentation.
Pitfalls to Avoid
The biggest mistake is trying to make the form perfect before releasing it. A Generic Physical Exam Form doesn't need every possible condition accounted for. It needs to capture the routine exam competently and flag abnormalities clearly. Over-engineering it leads to a document nobody wants to use. Start with the core sections, deploy it, collect feedback after two weeks, and iterate from there. Don't use medical jargon in the labels unless your audience is exclusively physicians. If nurses, PAs, and techs will also be using this, keep the language plain. "Heart sounds" instead of "cardiac auscultation." "Belly" or "abdomen" works, but avoid terms that assume prior training. The form should be usable by anyone who's done a basic physical exam. Another trap is the lack of a summary section. By the time the provider finishes the body systems, they've forgotten the key finding from the beginning. Add a brief assessment and plan box at the bottom. This doesn't need to be elaborate. A few lines for impression and next steps give the form clinical relevance beyond just data collection. It also serves as a natural conclusion point so the provider knows they're done.

Implementation Checklist
Before rolling this out, verify the following: all required fields are clearly marked, the form flows logically from general to specific, abnormal findings are easy to document without extra clicks or pages, the layout prints cleanly on standard letter paper if needed, and there's a spot for the examiner's signature and date. Test it with at least two different providers who have different habits. If one finishes in under five minutes and the other is still struggling after ten, there's a friction point you need to address. The form I ended up using most consistently had exactly forty-eight fields across ten body systems, four vital sign entries, and a summary box. It took most providers about three to five minutes to complete a normal exam. Abnormal findings added maybe ninety seconds. That's the pace you want. Anything slower and people start skipping sections.