Understanding Genotype Of A Blood Group
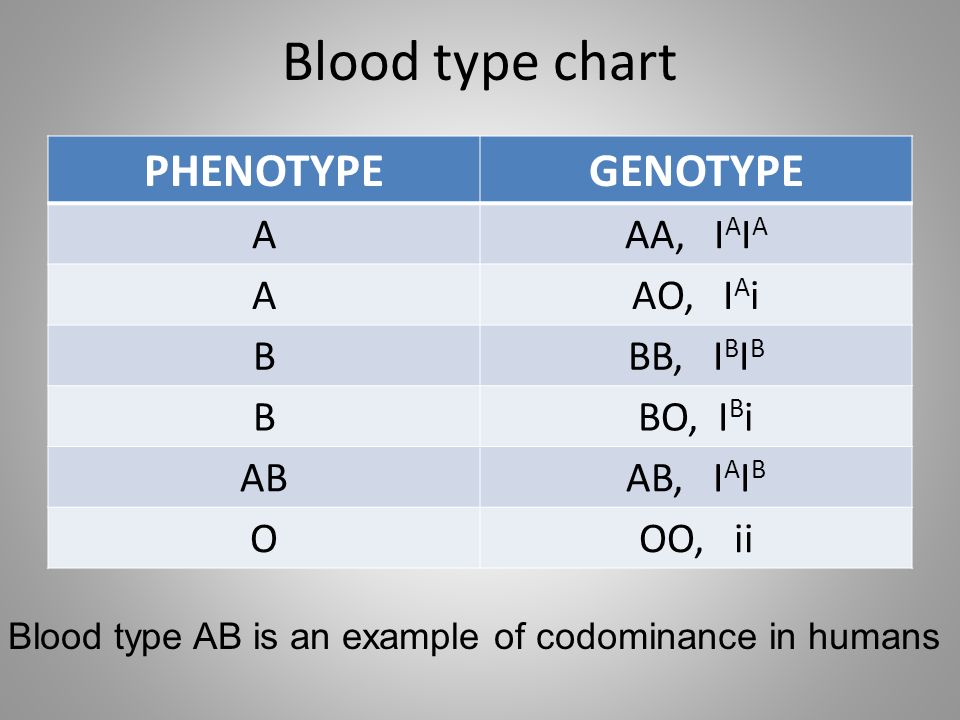
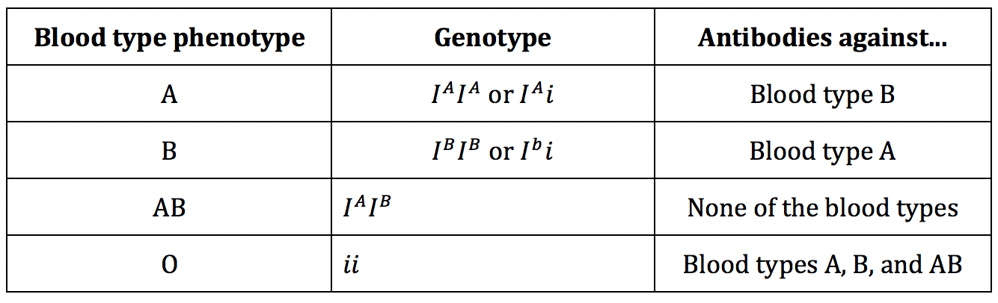
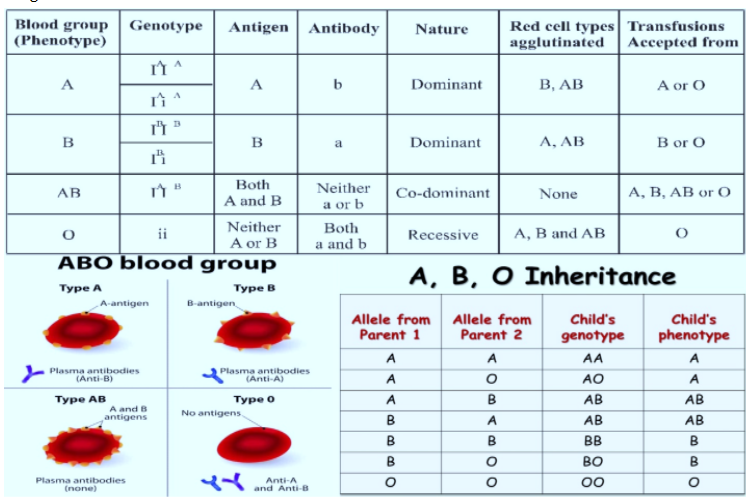
Most people think blood type is just one letter and a plus or minus sign. It isn't. The actual genotype behind that letter tells you which alleles someone inherited from each parent, and it matters way more than a standard group test shows. If you've ever looked at a pedigree chart and gotten confused about how two type A parents produced a type O child, you already ran into the difference between phenotype and genotype. Here's how it actually works in practice. The ABO system is built on three main alleles at a single gene locus on chromosome 9: IA, IB, and i (sometimes written as IO). IA and IB are codominant, meaning if you inherit both, you express both antigens and you're type AB. Either one dominates over i, which is recessive and produces no functional antigen. So the possible genotype pairings break down like this. Type A blood comes from IAIA or IAi. Type B comes from IBIB or IBi. Type AB is always IAIB. Type O is always ii. The Rh system is a completely separate gene. The D allele dominates over d. DD or Dd gives you a positive Rh factor, while dd gives you negative.
When I first started working with family pedigree cases, I kept seeing reports where the predicted genotype didn't match the observed phenotype and I spent hours going back through the lab notes. The issue was usually a weak subgroups variant or a cis-AB allele hiding in the mix. Standard serology just flags it as A or B and moves on, but the genotype tells the real story. I ended up running PCR-based genotyping with allele-specific primers to catch those cases, and it resolved about two-thirds of the mismatches I was seeing on standard testing alone.
How To Determine Genotype From Parental Types
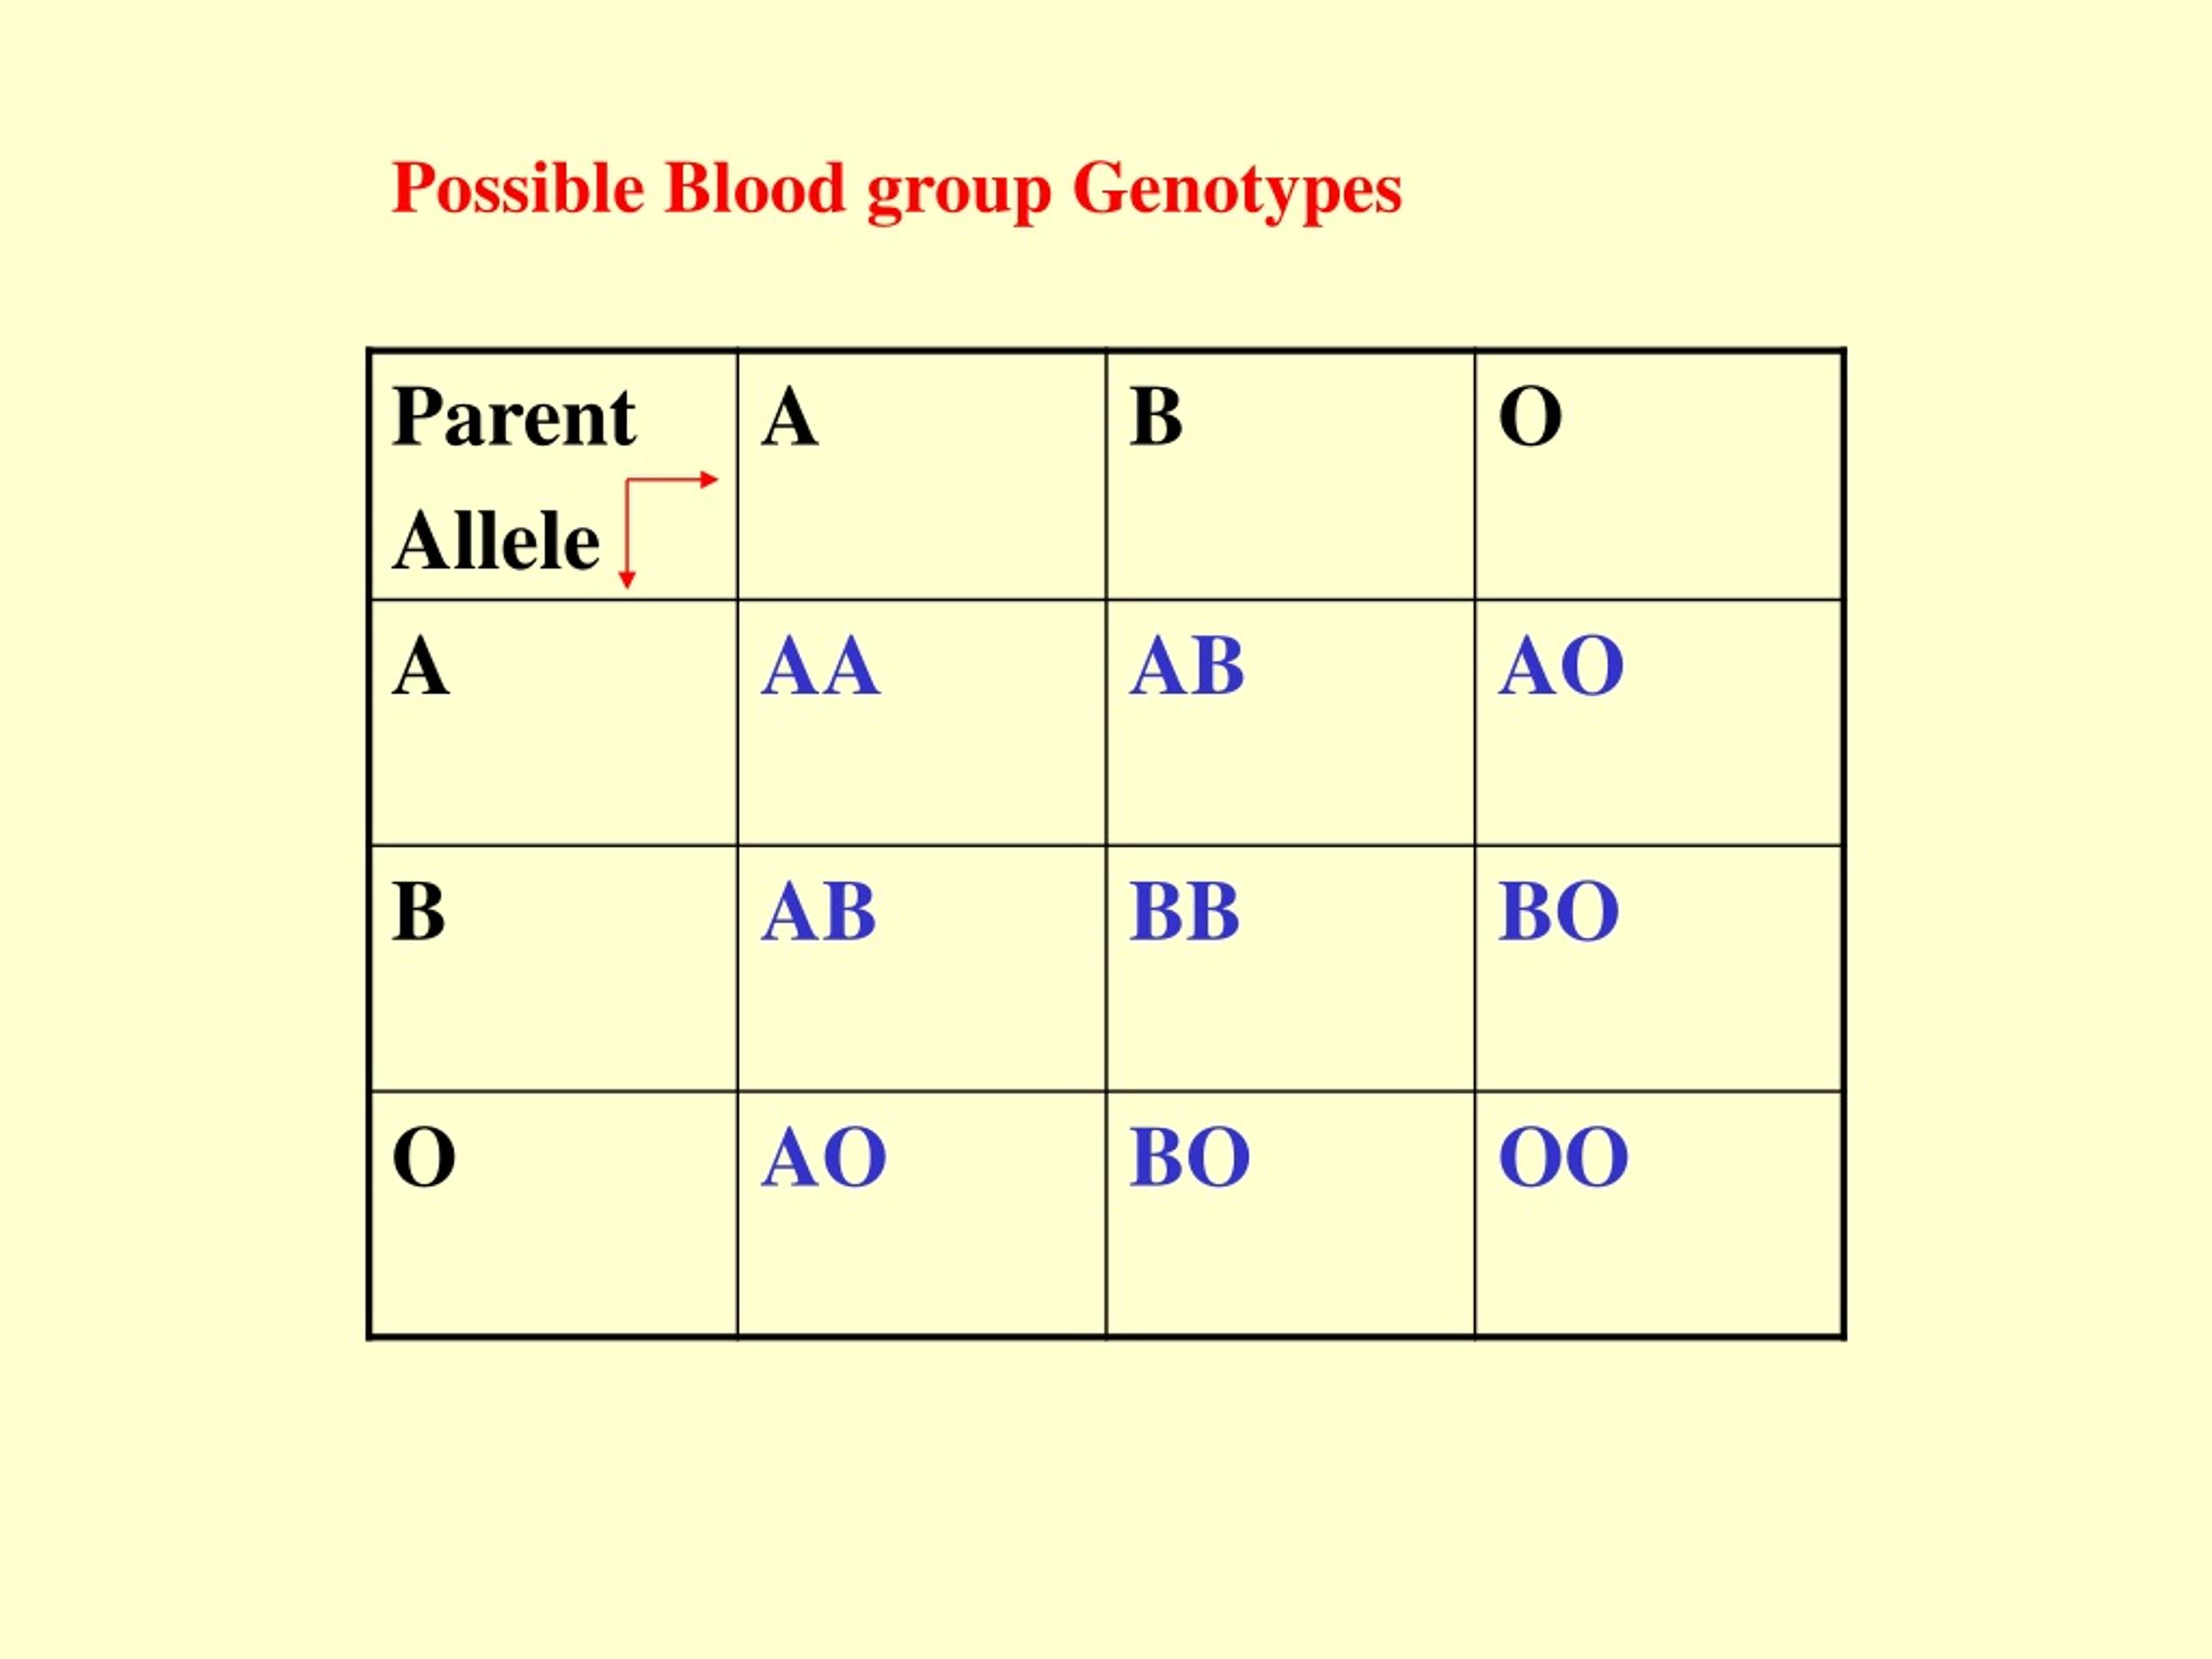
The most practical way to figure out potential genotypes is through a simple Punnett square, once you account for the fact that phenotypic types hide heterozygous carriers. Start by listing what each parent could actually carry based on their blood type, then cross them. Say both parents are type A. You don't know if they're IAIA or IAi without more information. If both happen to be IAi carriers, there's a 25 percent chance their child inherits ii and is type O. That's why two type A parents can absolutely have an O child, and it's also why blood type alone is useless for ruling out paternity in any legal sense. The actual exclusion power is narrow and easily misunderstood. Here's a faster example. A type AB parent crossed with a type O parent always produces either IAi (type A) or IBi (type B), each at 50 percent. No surprises there. But take a type A parent who is IAi and a type B parent who is IBi, and you get all four blood types in roughly equal proportions. The full range of outcomes depends entirely on whether the parents are homozygous or heterozygous at the ABO locus, and you can't tell just by looking at their blood type.
Get the Full Details

Where Standard Testing Falls Short
Blood type genotyping through routine labs uses serological agglutination, which detects antigens on red blood cells. That works fine for the common cases but misses several well-documented exceptions. The Bombay phenotype is the classic example. People with the hh genotype lack the H antigen entirely, so even if they carry IA or IB alleles, their red cells won't display A or B antigens. Serology reads them as type O, but their actual genotype carries A or B information that standard testing completely overlooks. This matters clinically because a Bombay phenotype person transfused with what looks like compatible O blood could have a severe reaction, since their immune system recognizes the H antigen they're missing as foreign. Another issue I deal with occasionally is the weak A subgroup, particularly Ax and Ael variants. These individuals express very few A antigens, so forward typing can read as type O or a very weak A. Their genotype is still IA something, but the antigen density is low enough to cause confusion in prenatal screening and transplant compatibility checks. I've seen cases where the discrepancy only surfaced when a family member's sample was pulled in for confirmatory testing. If you need accurate genotyping beyond serology, molecular methods like PCR followed by sequencing or allele-specific hybridization are the standard approach. These directly read the DNA sequence at the ABO locus and can identify subgroups, cis-AB, and silent alleles that serology misses. The tradeoff is cost and turnaround time. Serology takes minutes and runs cheap. Molecular genotyping runs significantly more expensive and usually requires sending samples to a reference lab, though dedicated blood bank genotyping panels have gotten faster over the last few years.
Practical Application In Clinical Settings
In pregnancy, Rh genotyping has become routine because knowing whether a fetus is Rh positive or negative changes management. An Rh-negative mother carrying an Rh-positive baby needs Rhogam prophylaxis to prevent sensitization, and noninvasive prenatal genotyping from maternal blood has made this possible without invasive procedures. The test analyzes cell-free fetal DNA in the mother's bloodstream and determines the RHD status accurately enough to guide treatment decisions. For ABO specifically, genotyping matters most in transplant medicine and in resolving incompatible crossmatch results. When a patient has received multiple transfusions or has an unusual antibody profile, knowing the true genotype helps match donors more precisely and avoids reactions from minor antigen mismatches that standard typing doesn't catch. I worked through a case a while back involving a patient who was typed as A positive but whose family history suggested an inherited disorder that serology couldn't explain. The genotype came back as IAi with a rare RHD variant that caused weak D expression. Standard Rh typing had called it positive, but the underlying variant meant the patient could still form anti-D antibodies under the right conditions. The workaround was switching to molecular Rh genotyping for any future transfusion planning rather than relying on the phenotypic call.
The takeaway is straightforward. Blood type is a phenotype, not a full genetic picture. If you need to know genotype, you have to test the DNA, not just the surface antigens. For everyday purposes, serology is sufficient. For anything involving transfusion history, pregnancy complications, or unexpected family inheritance patterns, genotyping fills in the gaps that blood type alone can't address.