What Actually Happens When You Set Goals For Depression In Therapy
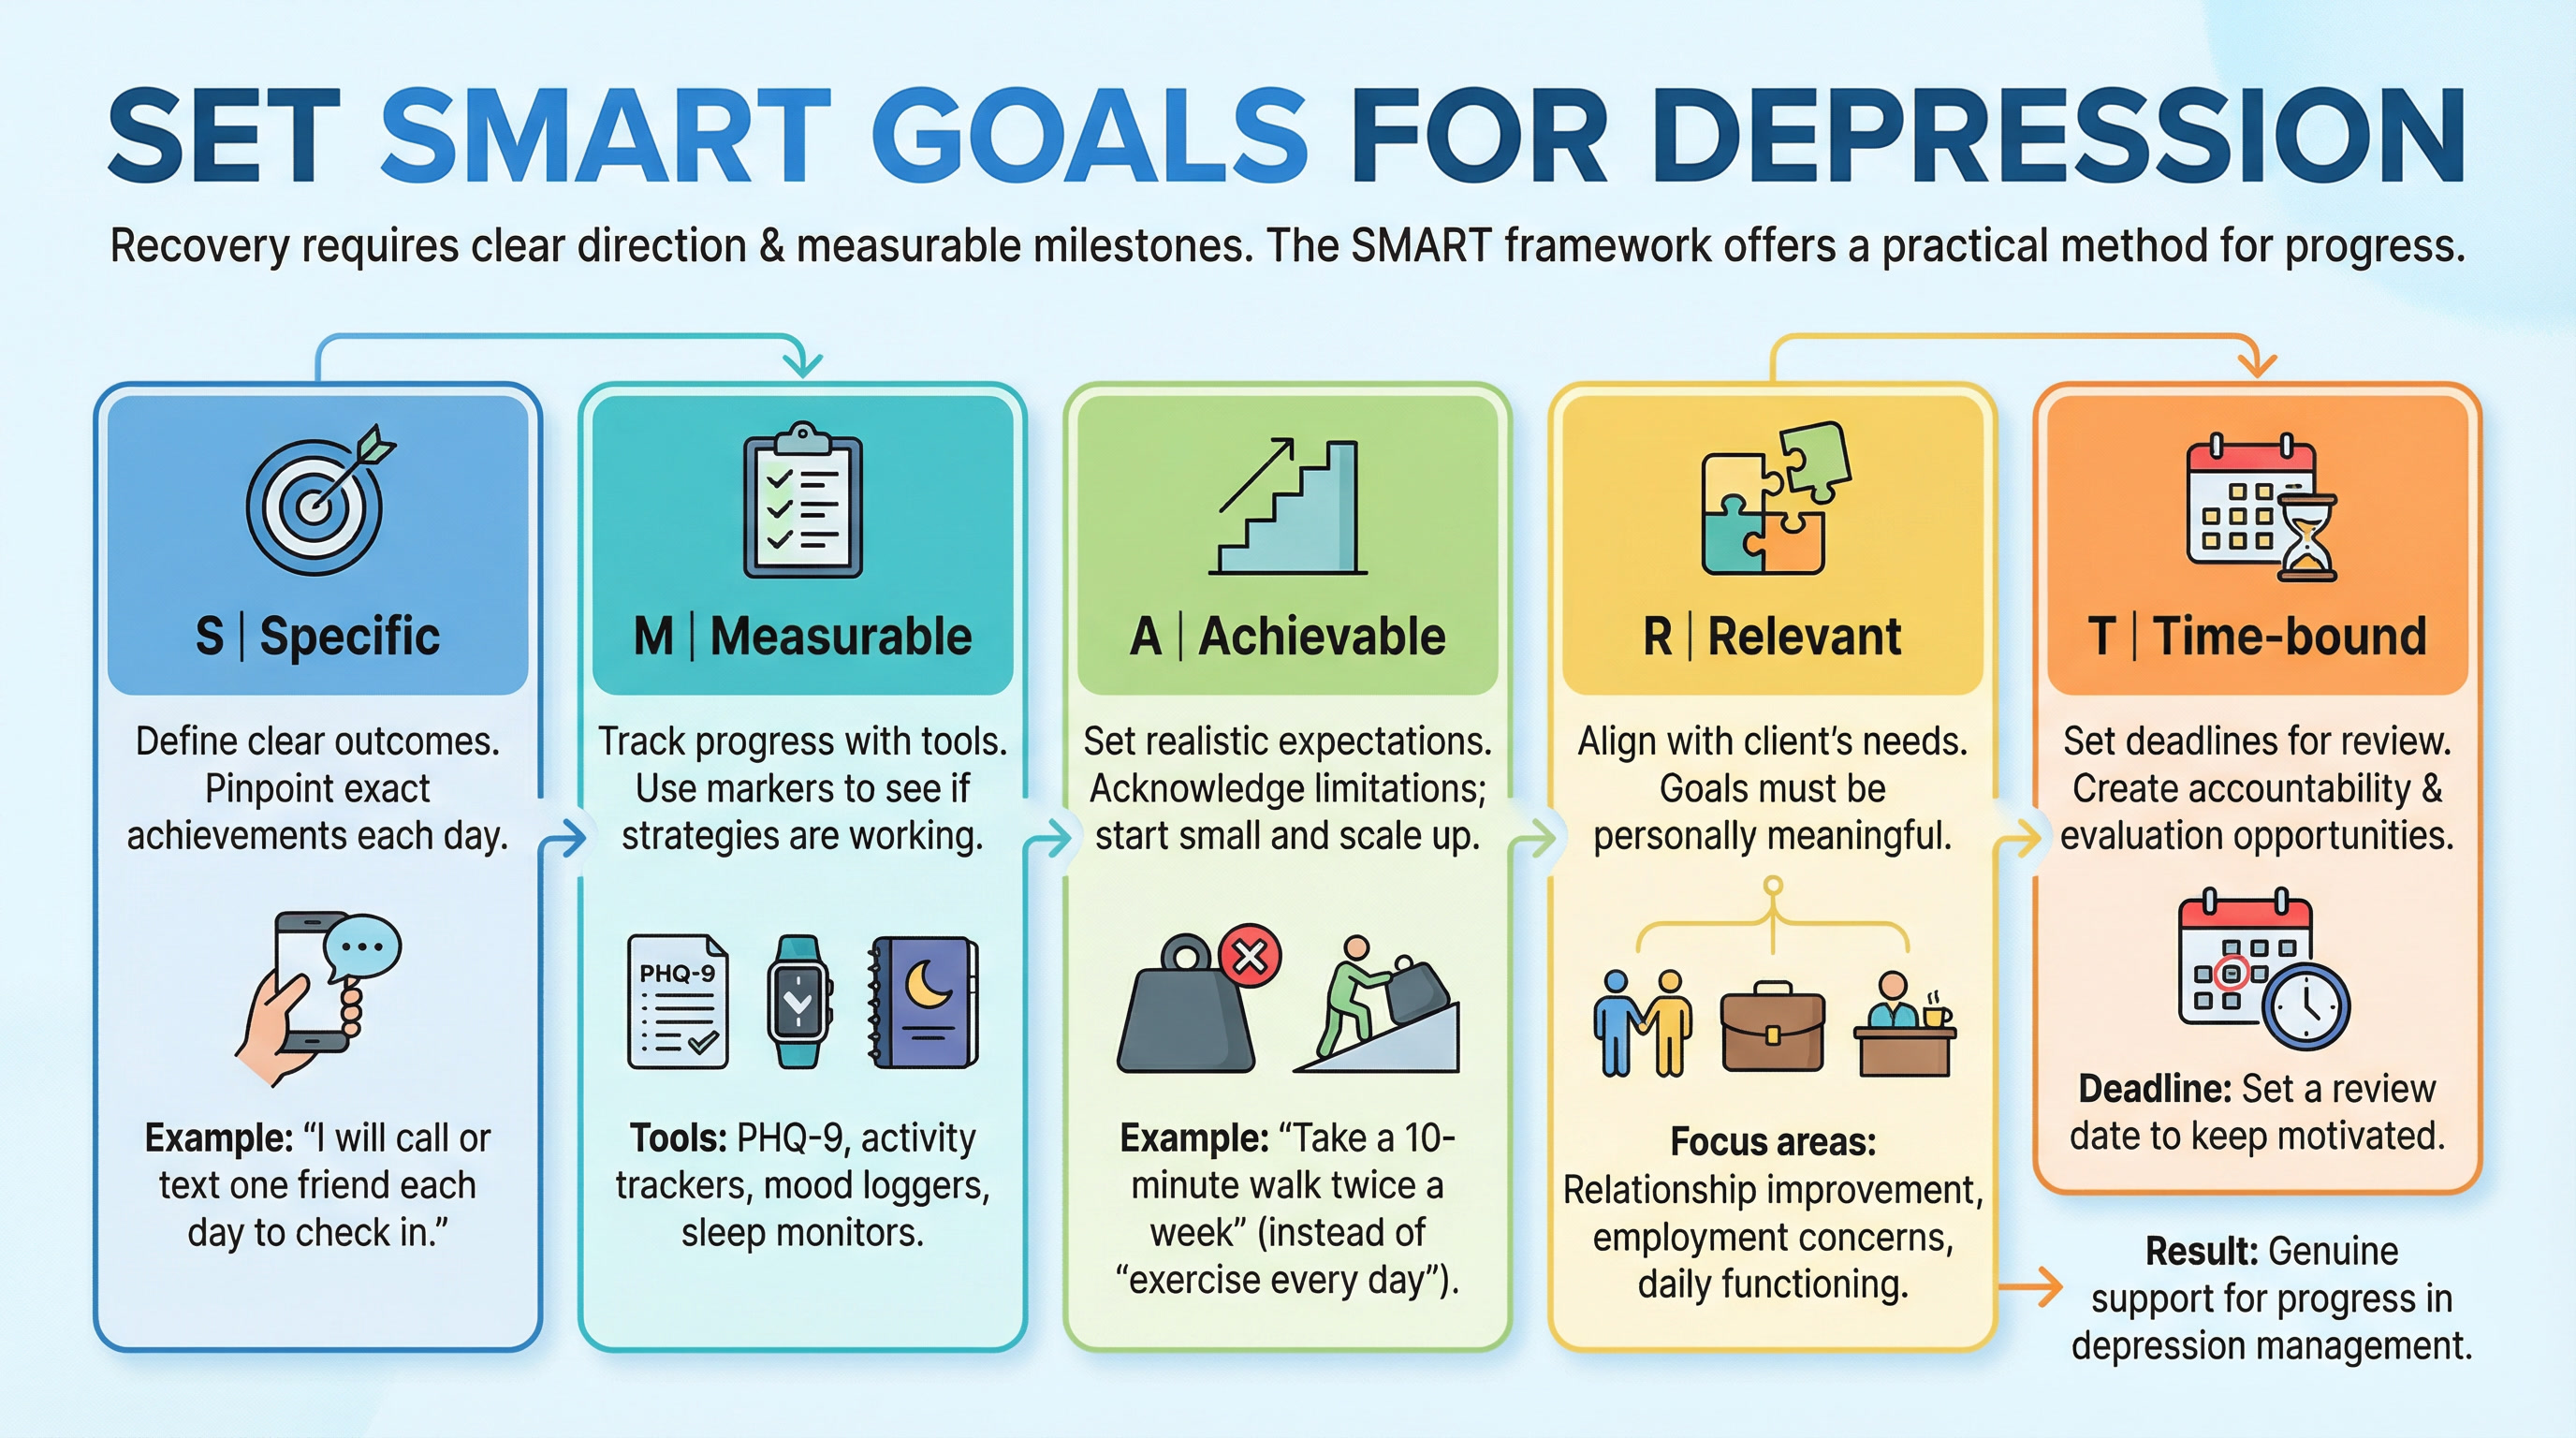
Therapists don't just sit there and nod for fifty minutes. The most effective depression treatment plans start with defining what success looks like, and most people have no idea how to do that. They walk in saying they want to "feel better" or "stop being sad," which isn't a goal. It's a wish. A goal needs a measurable endpoint, a timeframe, and it has to be something that can actually be tracked week to week. I spent years watching clients struggle with this exact problem. The ones who improved fastest were the ones who could articulate concrete targets. The ones who stagnated were usually the ones who couldn't say what differently their life would look like if therapy worked. Here is how you actually build those goals without wasting months on vague aspirations.
How To Structure Goals For Depression In Therapy
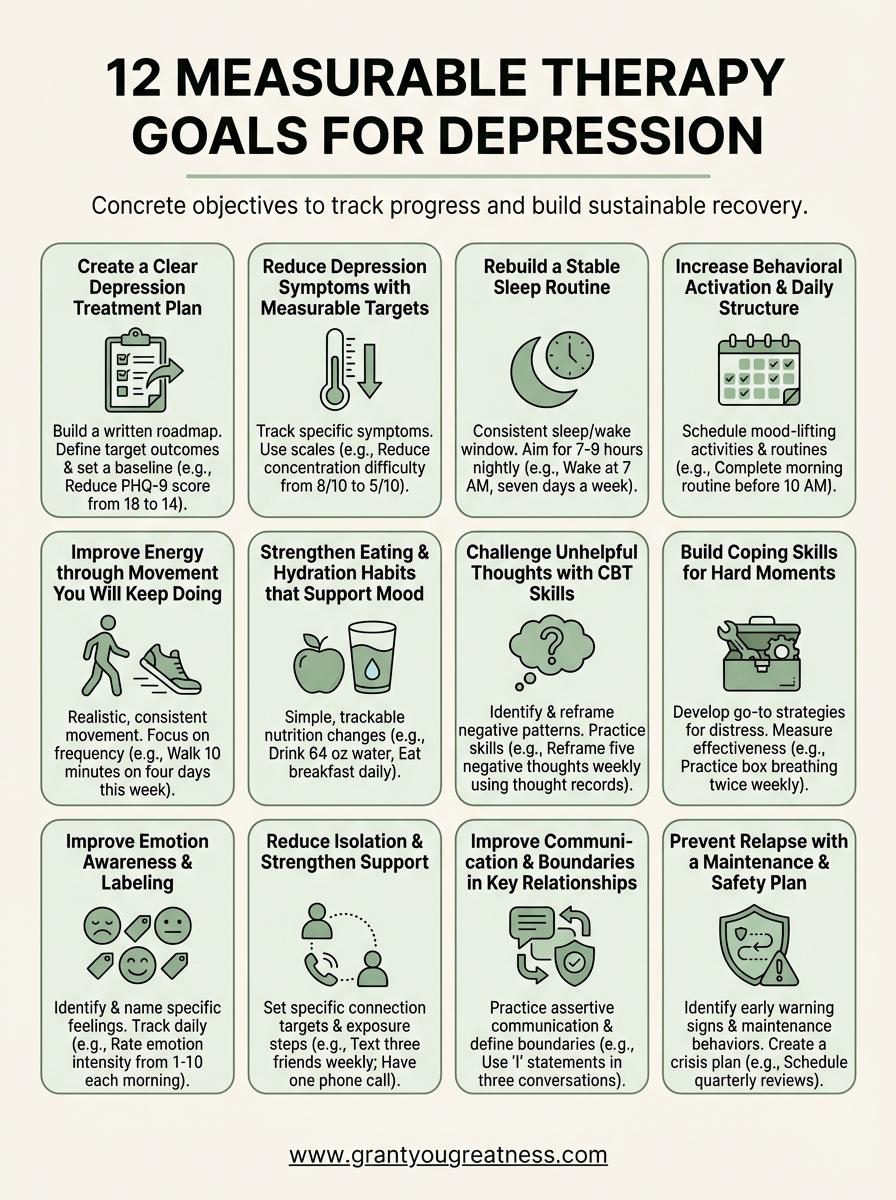
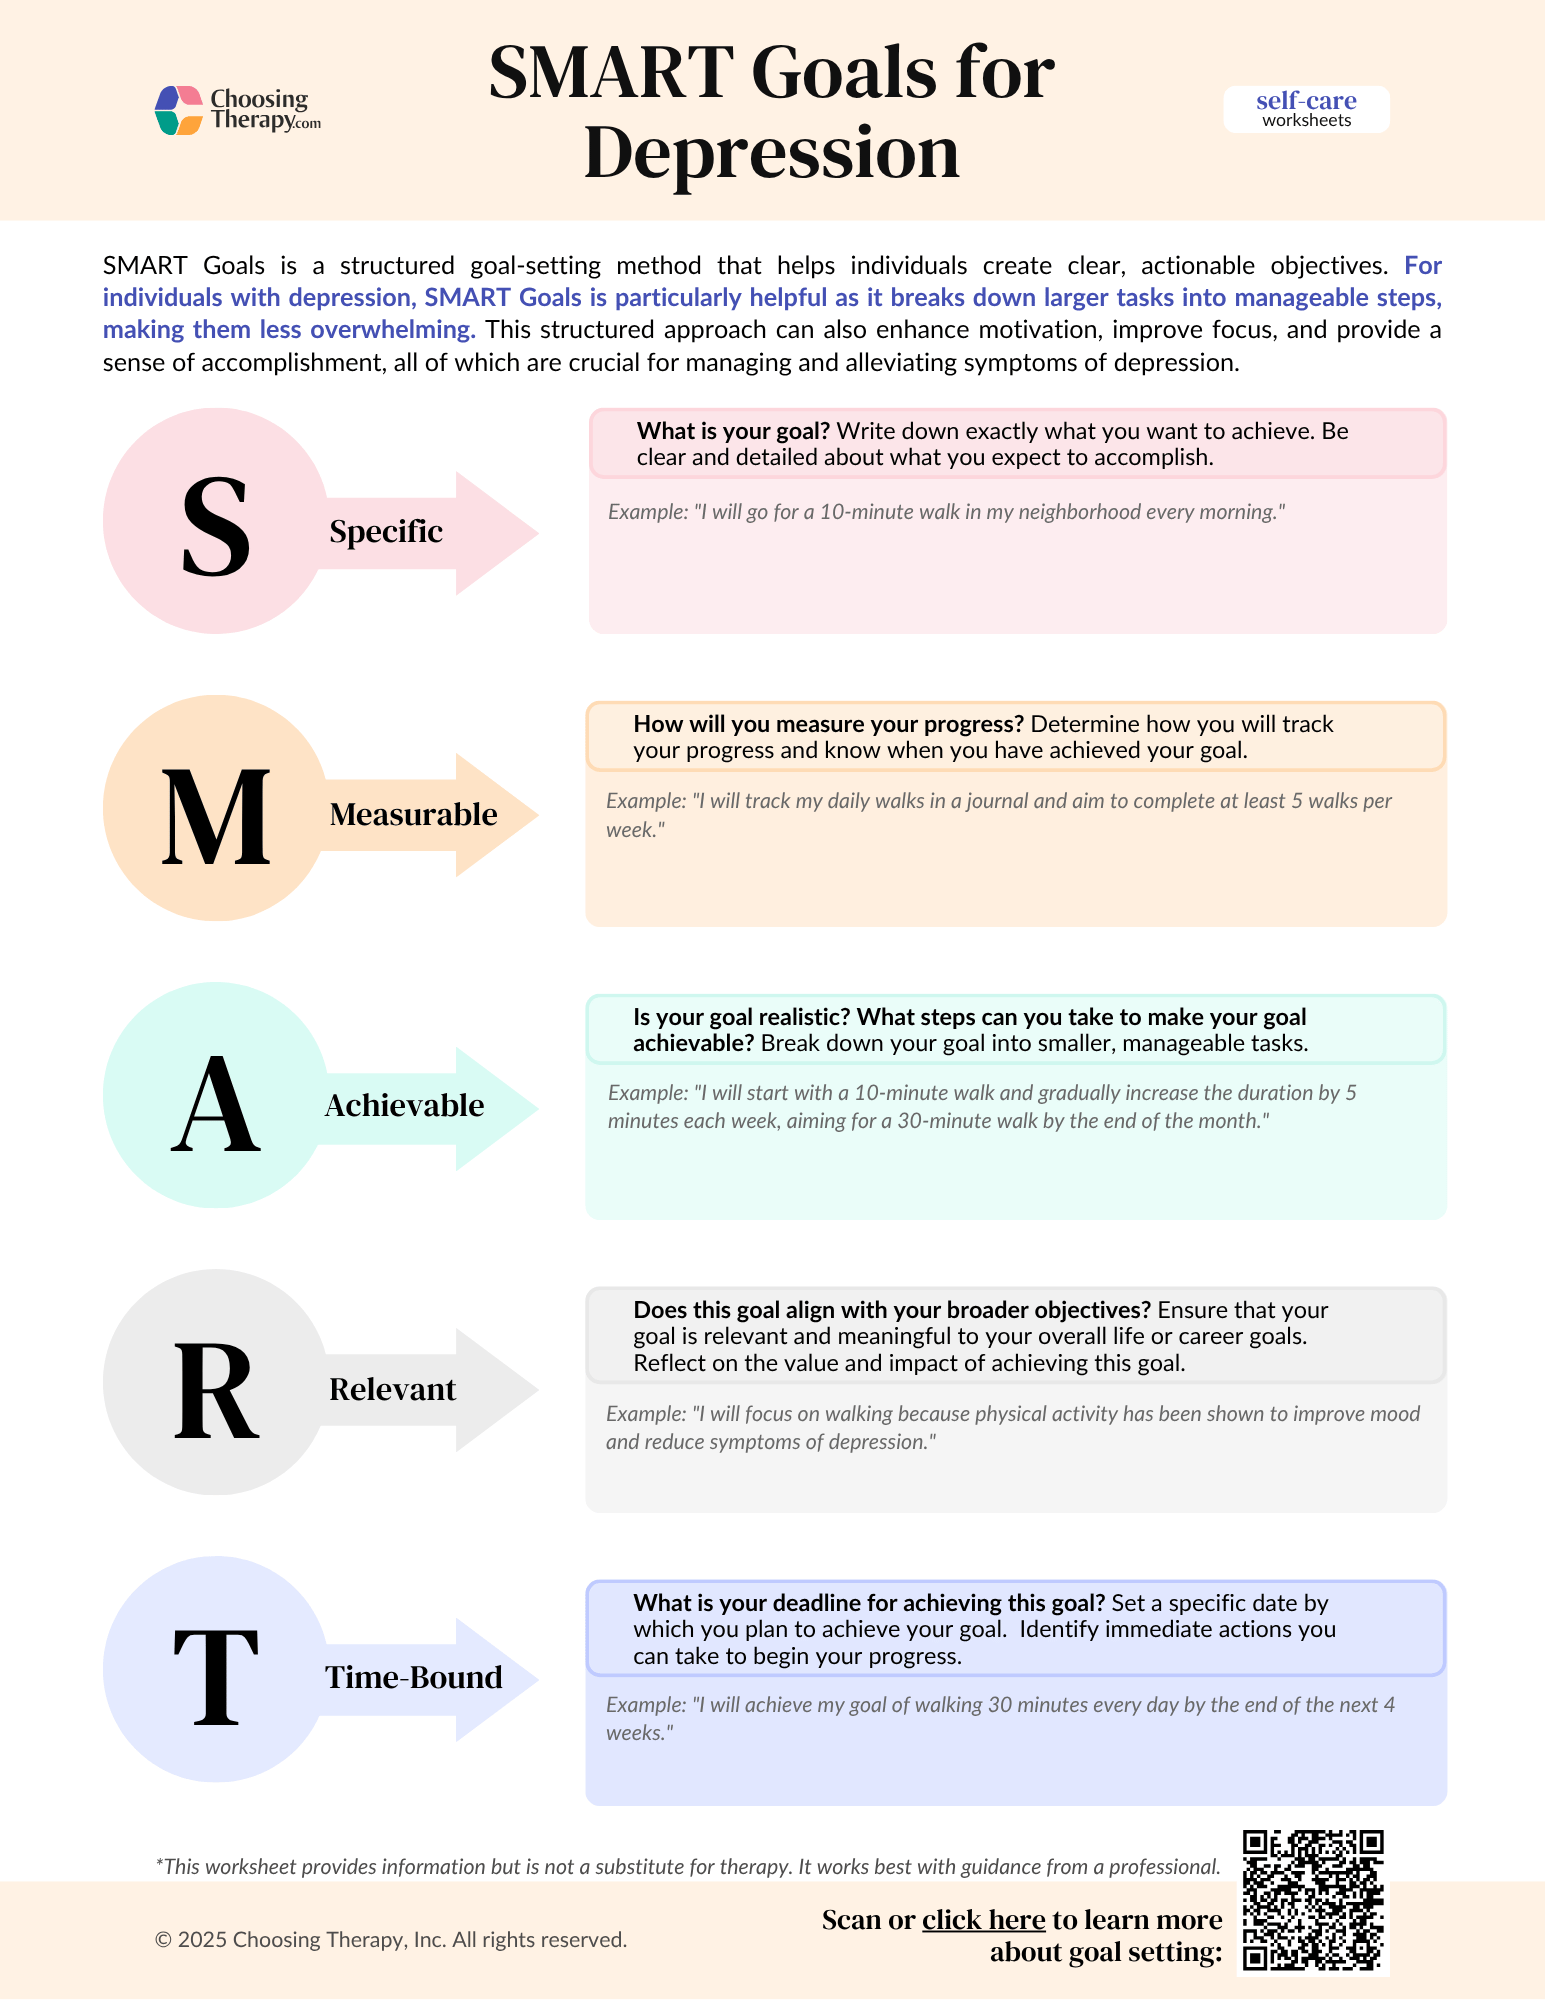
Start by identifying the behavioral markers of your depression first, not the emotional ones. Saying "I want to be less anxious" is useless because anxiety doesn't have a consistent meter. Saying "I want to return to going to the gym three times a week" is trackable. You can measure that. You can count it. You can look back at week four and know exactly whether you made progress. The framework I use is straightforward: Each goal needs a behavior, a frequency, a baseline, and a target. Take sleeping as an example. If your baseline is sleeping five hours a night because rumination keeps you awake, your goal isn't "sleep more." Your goal is "sleep six hours per night, four nights out of seven, over the next eight weeks." That is specific enough that you and your therapist can both look at the data at the end of month two and say yes or no.
Activity scheduling is where most people stall out. Depression shrinks your world until leaving the house feels insurmountable. Breaking that down into a goal means starting absurdly small. I had a client whose depression was so severe that her only achievable goal in week one was making her bed before noon. Not exercise. Not socializing. Making the bed. She tracked it every day. By week three she was able to add "walk to the mailbox and back" as a second goal. By week eight she was walking for twenty minutes. Small increments compound. That is the mechanics of it. Some of the goals you set will be cognitive rather than behavioral. If your depression includes a pattern of catastrophizing every minor setback, a goal might be "write down three alternative explanations for any negative event before concluding it is permanent and personal." That sounds clinical but it is incredibly practical. You are building a skill, not just waiting to feel different. Social re-engagement is another category where vague goals kill progress. "Spend more time with friends" will get you nowhere. "Call one person per week and schedule a thirty-minute coffee or phone chat" is something you can check off. The trick is picking activities that are low friction. High effort social goals when you are deeply depressed just create a checklist of failures.
Get the Full Details

The Reality Of Tracking Progress In Depression Treatment
You need a system to log these goals. Paper journals work but they are unreliable because you are more likely to skip entries when you are at your worst. A simple spreadsheet or a notes app on your phone is better. What matters is consistency, not sophistication. I once worked with a client who used a dedicated habit-tracking app and abandoned it within three weeks because the gamification annoyed her. She switched to a plain Google Sheet with checkboxes and stuck with it for six months. The tool does not matter. The routine does. Here is a practical note about weekly reviews. Most people skip them. They are tedious. But reviewing your tracked goals every Sunday takes about ten minutes and it is where the actual insight happens. You will start to see patterns. Certain days correlate with missed goals. Certain thoughts precede skipped behaviors. This is raw material your therapist can use to adjust the treatment plan. Without it you are just guessing. A counter-intuitive thing about depression goals is that some of them should deliberately include failure. If your goal is to shower every day and you only showered two days that week, punishing yourself for missing the target just reinforces the depressive cycle. The goal is the direction, not a pass-fail test. You adjust the difficulty. You notice what got in the way. You keep moving.
I encountered a specific edge case recently with a client who had a goal to resume reading books as a form of behavioral activation. She tracked it religiously but made zero progress for six weeks. The breakthrough came when we realized she was trying to read full chapters. She wasn't struggling with motivation. She was struggling with cognitive fatigue. She couldn't hold a narrative together in her head anymore. We changed the goal to "read one page per day." She was doing that every day within a week. Then we slowly increased the target. The problem was never the activity. It was the dosage.
Where This Approach Breaks Down
Setting goals for depression in therapy is not a universal solution. It fails in several predictable scenarios. People with severe anhedonia often cannot generate internal motivation to pursue any goal, regardless of how small. For those individuals, external accountability structures like daily check-in calls with a therapist or a support person are necessary before goal-setting becomes viable. The standard CBT goal framework assumes a baseline of executive function that simply does not exist during acute episodes. Cognitive impairment from depression itself is another blind spot. Processing speed slows. Working memory shrinks. Keeping track of daily goals can feel genuinely impossible. In those cases the therapist should reduce the scope drastically and use reminders, alarms, and external prompts rather than relying on the patient's own monitoring ability. There is also a risk of turning therapy into a productivity exercise. When goals become too achievement-oriented, some patients start measuring their worth entirely by whether they checked boxes. That is a trap. Depression recovery is not a sprint. Some weeks you will miss everything and still be making progress. The treatment plan needs to account for that reality from the start.
If goal-setting approaches are not working after four to six weeks, it is worth reassessing whether the underlying treatment modality fits. Medication evaluation, interpersonal therapy, or even a change of therapist may be more appropriate than pushing harder on the same framework. No single method works for everyone, and recognizing that early saves months of frustration.
What To Do Before Your First Session
You do not need to have everything figured out before you start. But writing down a few specific behaviors that depression has taken away from your life will make the first session productive. Think about things you used to do regularly that you stopped. Work. Hobbies. Social contact. Self-care routines. Pick three. Describe them in concrete terms with a realistic frequency. That is your starting point. Everything else gets built from there.