Setting Up a Clinical Database That Won't Collapse Under Its Own Weight
Most people think Good Clinical Data Management Practices is about making sure the spreadsheets look tidy. It's not. It's about building a system where the data can survive the audit three years later when nobody involved in the trial is still on the payroll. I spent six months trying to reconcile query statuses across twelve sites that each used slightly different definitions for what "resolved" meant. Half the queries had been marked resolved by the site, then overridden by the monitor without any flagging. The database didn't know who resolved what and when. I ended up writing a custom reconciliation script that cross-referenced source documents, eCOA timestamps, and monitoring visit notes to find the gaps. Took two weeks to build, saved us from a regulatory observation. The core issue nobody talks about enough is that Good Clinical Data Management Practices exists in a tension between three forces: the sponsor who wants data yesterday, the site who wants to finish data entry before lunch, and the auditor who will tear apart anything that isn't perfectly traceable. Your data management plan has to account for all three. Usually it fails because people design it for the auditor and forget the site.
What Good Clinical Data Management Practices Actually Means in Practice
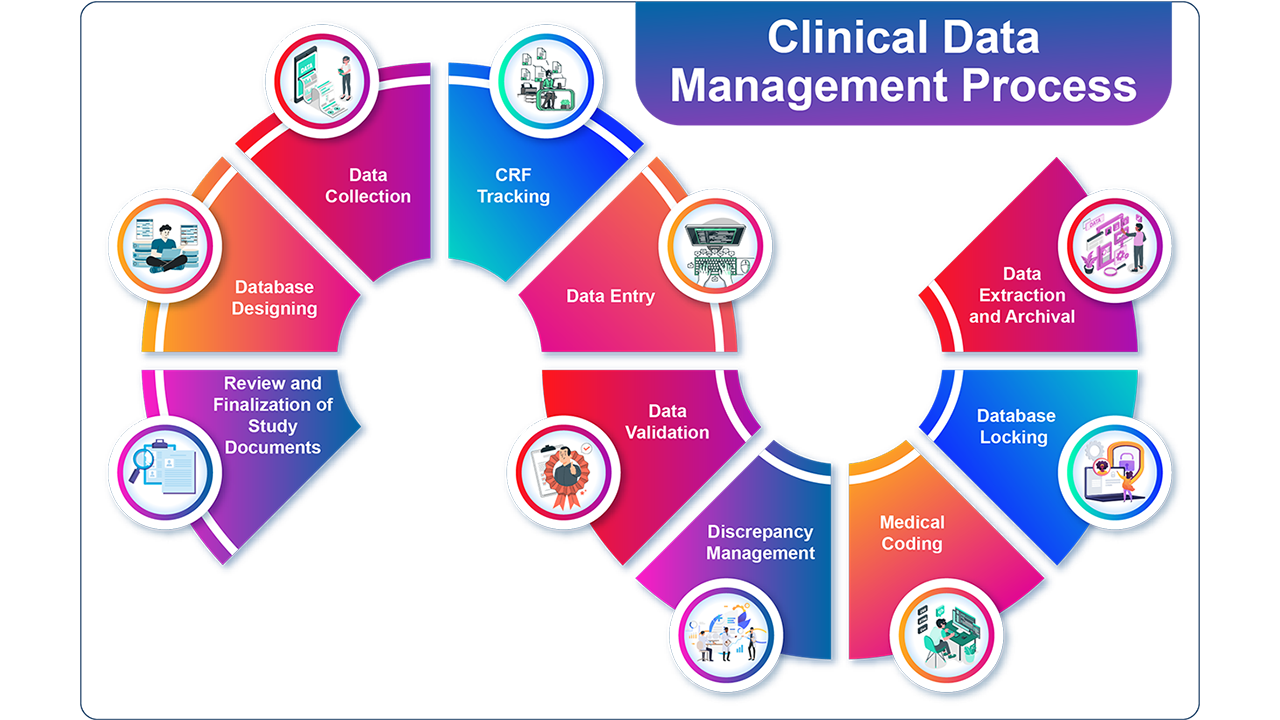
It's a framework covering how clinical trial data is captured, validated, cleaned, and archived from the moment a patient enters a study through to database lock. That includes CRF design, edit checks, query management, data cleaning cycles, audit trails, and security. The CDISC standards (SDTM and ADaM) are the backbone most sponsors follow, but following CDISC doesn't mean you're doing good data management. It means you're following a standard. There's a gap between conformance and quality. CRF design is where most programs go wrong. I've seen electronic case report forms with 400 fields on a single page because the sponsor wanted everything in one screen. Sites hate that. They start using the comment field for actual data entry because they can't find the right dropdown. Then the data is unusable. Put a maximum of eight to twelve fields per logical screen. Group related items together. Make required fields obvious. Sites will work with clear forms. They will rebel against confusing ones.
Building the Validation Layer
Edit checks are the first line of defense, and most people implement them poorly. There are two types you need to understand: hard checks and soft checks. A hard check prevents data submission until the value is valid. A soft check flags a discrepancy but allows the data to go through. The mistake people make is putting hard checks on everything. When a site hits a hard check for a legitimate edge case, they either spend twenty minutes calling the sponsor to ask if they should submit anyway, or they enter fake data to bypass the check. Both options destroy data integrity. My approach is to categorize edit checks by risk. Critical safety data gets hard checks. Everything else gets soft checks with mandatory query resolution before database lock. This cuts down unnecessary queries by about 60 percent and keeps sites moving. The trade-off is that you need a very robust query management process, because soft-check data will sit unresolved longer. But unresolved soft checks are better than sites entering garbage data to work around your hard checks. Audit trails are non-negotiable under 21 CFR Part 11 and the EU GDPR. Every data change must be recorded with a timestamp, the user who made the change, the old value, and the new value. What most sponsors mess up is the audit trail granularity. If your system logs every keystroke, you'll have a billion rows of noise. Log at the field level, not the session level. When a site modifies a lab result from "abnormal" to "normal," you want to see that exact change with the reason. You don't need to see that they opened the form, navigated to the tab, and typed their password.
Get the Full Details

The Query Management Problem
This is the part that breaks programs. Query management is supposed to be a conversation between the data manager and the site. Instead it becomes a bureaucracy. Sites get flooded with queries they don't understand. Data managers send queries that sites can't resolve without contacting five different people. Queries sit open for weeks. Nobody tracks resolution quality. Here's what actually works: limit the number of open queries per site at any given time. I set a cap at twenty-five. When a site hits that number, no new queries are generated until some are resolved. It sounds punitive. It's not. It forces prioritization. The data manager has to decide which queries matter and which can wait. Sites can focus on clearing the backlog instead of drowning in a constant stream of new questions. In my experience this reduced average query resolution time from eleven days to four days. The other thing that matters is query templates. Writing the same query seven hundred times in slightly different ways is useless. Build a library of standardized queries for common issues — missing consent dates, out-of-range lab values, mismatched diagnoses — and reuse them. Custom queries should be reserved for genuinely unusual situations. This also helps during data cleaning reviews because you can spot patterns. If fifty percent of your queries are about the same missing field, the CRF design is the problem, not the sites.
When Things Go Wrong
I worked on a Phase III oncology trial where the central lab and the site lab produced systematically different values for the same biomarker. The central lab reported in SI units, the site lab reported in conventional units, and the CRF only had one field. Nobody caught it during validation because the edit checks were comparing ranges, not units. By the time I noticed the pattern during the first interim analysis, seventeen patients had been dosed with potentially incorrect stratification assignments. We had to pull the data, reformat everything, and resubmit to the biostatistician. Cost us three weeks and a very uncomfortable conversation with the sponsor. The lesson is that cross-domain consistency checking is more important than single-domain validation. You need to compare data points across modules — lab results against dosing records, adverse events against concomitant medications, demographic data against eligibility criteria. Most data management systems are configured to check within a module. Very few catch discrepancies between modules automatically. You either build that into your validation plan or you rely on biostatistics to find it later, which is expensive and delays lock.
Good Clinical Data Management Practices for Small Sponsors
Big pharma has dedicated data management teams and can afford custom EDC configurations. Small sponsors and CROs usually have one person handling data management for five concurrent trials. In that situation, standardization is your only option. Use a template database. Reuse edit check libraries. Don't customize unless you have a documented, approved reason. Every custom edit check is a maintenance burden that will come back to haunt you during a data freeze or a system upgrade. The biggest risk for small sponsors is understaffing the data cleaning phase. It's easy to skip a cleaning cycle because the trial is behind schedule. But skipping cleaning means locked data with unresolved issues, and that becomes a regulatory finding. Plan for at least two full cleaning cycles before you even think about database lock. The first cycle finds the obvious problems. The second cycle finds the problems the first cycle introduced while fixing the first cycle. The data manager who skips the second cycle is the one getting paged at 2 AM before lock.
Archive and Retention
Data retention is another area where people cut corners. The minimum is usually ten years after trial completion, but that's a legal floor, not a best practice. Clinical data gets reanalyzed. Regulatory agencies request raw data years later. Patients sue. You need to be able to produce the exact dataset as it existed at lock, not a cleaned version that's been through multiple transformations. Store the raw data, the cleaned data, the SDTM datasets, the analysis datasets, and the statistical code. Everything. And verify the archive annually. I've seen companies that stored their data on deprecated media formats and couldn't read the files when they needed them three years later. Electronic archives need backup verification. A checksum on day one means nothing if you don't verify it on day three thousand. Run periodic integrity checks. Test restores. Document everything. The auditor won't care about your beautiful data management plan. They'll care about whether you can actually retrieve the data when asked.
Tools and Systems
Commercial EDC systems like Oracle Clinical, Medidata Rave, and Veeva Vault cover most of what you need out of the box. They handle edit checks, audit trails, role-based access, and CDISC export. The problem is that out-of-the-box configurations are generic. They work for standard trials. They don't work well for complex adaptive designs, decentralized trials with patient-reported outcomes feeding directly into the system, or trials using live biometric data from wearables. If your trial is unusual, you'll spend more time configuring the system than managing the data. In those cases, I've had better luck with open-source EDC platforms combined with custom validation scripts, though that shifts the burden to your internal team rather than a vendor. The tool matters less than the process. A well-managed trial on a basic EDC will pass inspection. A poorly managed trial on the most expensive system in the world will fail. Invest in training your data managers and your monitors. Train them on the protocol, not just the software. The person entering data at a site in Romania should understand why the eligibility criteria exist, not just which dropdown to click.
The Things Nobody Wants to Admit
Good data management doesn't prevent all errors. It prevents undetected errors. There will always be data entry mistakes, protocol deviations, and missed queries. The difference between a clean audit and a major finding is whether you can demonstrate that you caught them and addressed them. Your documentation has to tell that story. Every query, every resolution, every data change with its reason — it all needs to be traceable and defensible. Database lock is not a celebration. It's a moment of maximum vulnerability. The pressure to lock increases as the trial drags on. Sponsors want to report results. Regulators want to review. The team is tired. This is exactly when mistakes happen. Someone overrides a query without documentation. Someone approves a data extraction that hasn't been fully cleaned. Someone locks the database and forgets to notify the biostatistician. Establish a formal lock checklist. No exceptions. Three independent sign-offs. One from data management, one from clinical operations, one from biostatistics. If anyone is missing, the database stays locked in place, not in name. The industry keeps moving toward real-world data integration, decentralized trials, and direct-to-patient data capture. These innovations create new data management challenges that current frameworks aren't fully equipped to handle. Patient consent data flowing from mobile apps doesn't map cleanly onto SDTM domains. Wearable device data arrives in streams rather than discrete CRF entries. The principles of Good Clinical Data Management Practices still apply — traceability, validation, quality control — but the execution needs to evolve. The sponsors who figure this out first will have a significant advantage. The ones who treat new data sources like legacy data will accumulate technical debt that slows them down for years.