Why Nurses Actually Use Gordon Functional Health Patterns Instead of Writing Free-Form Notes
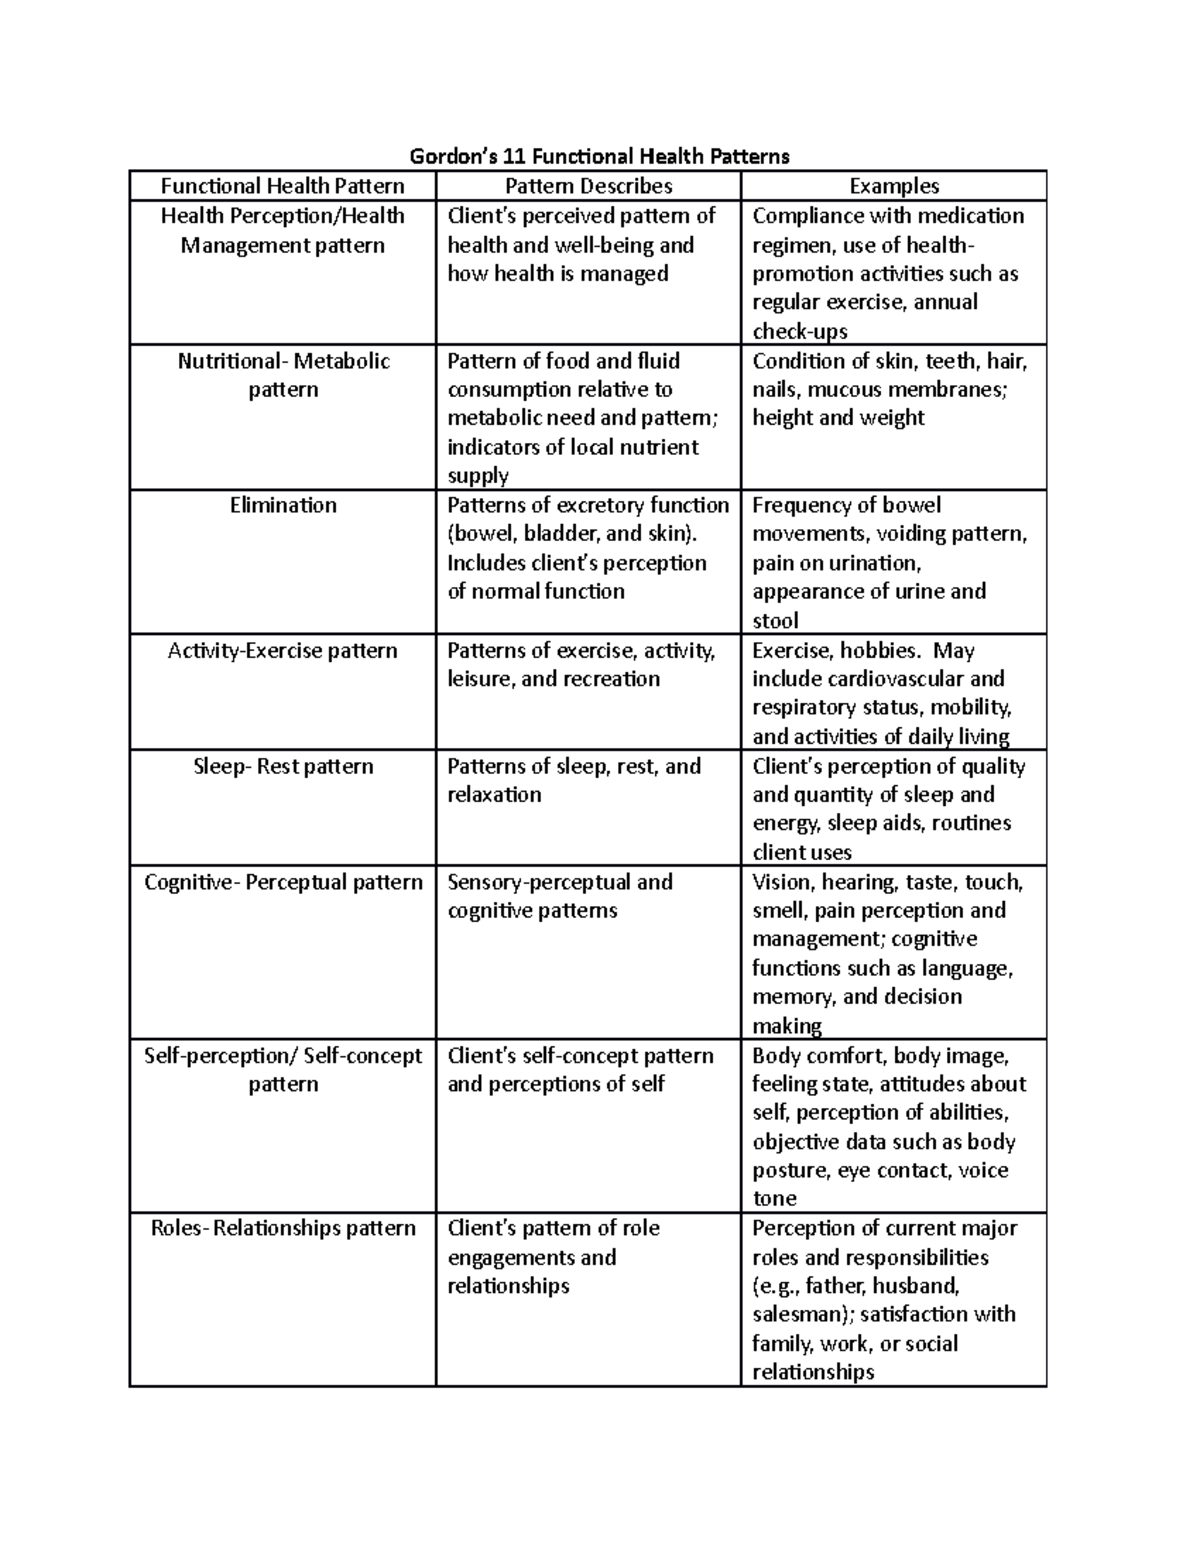
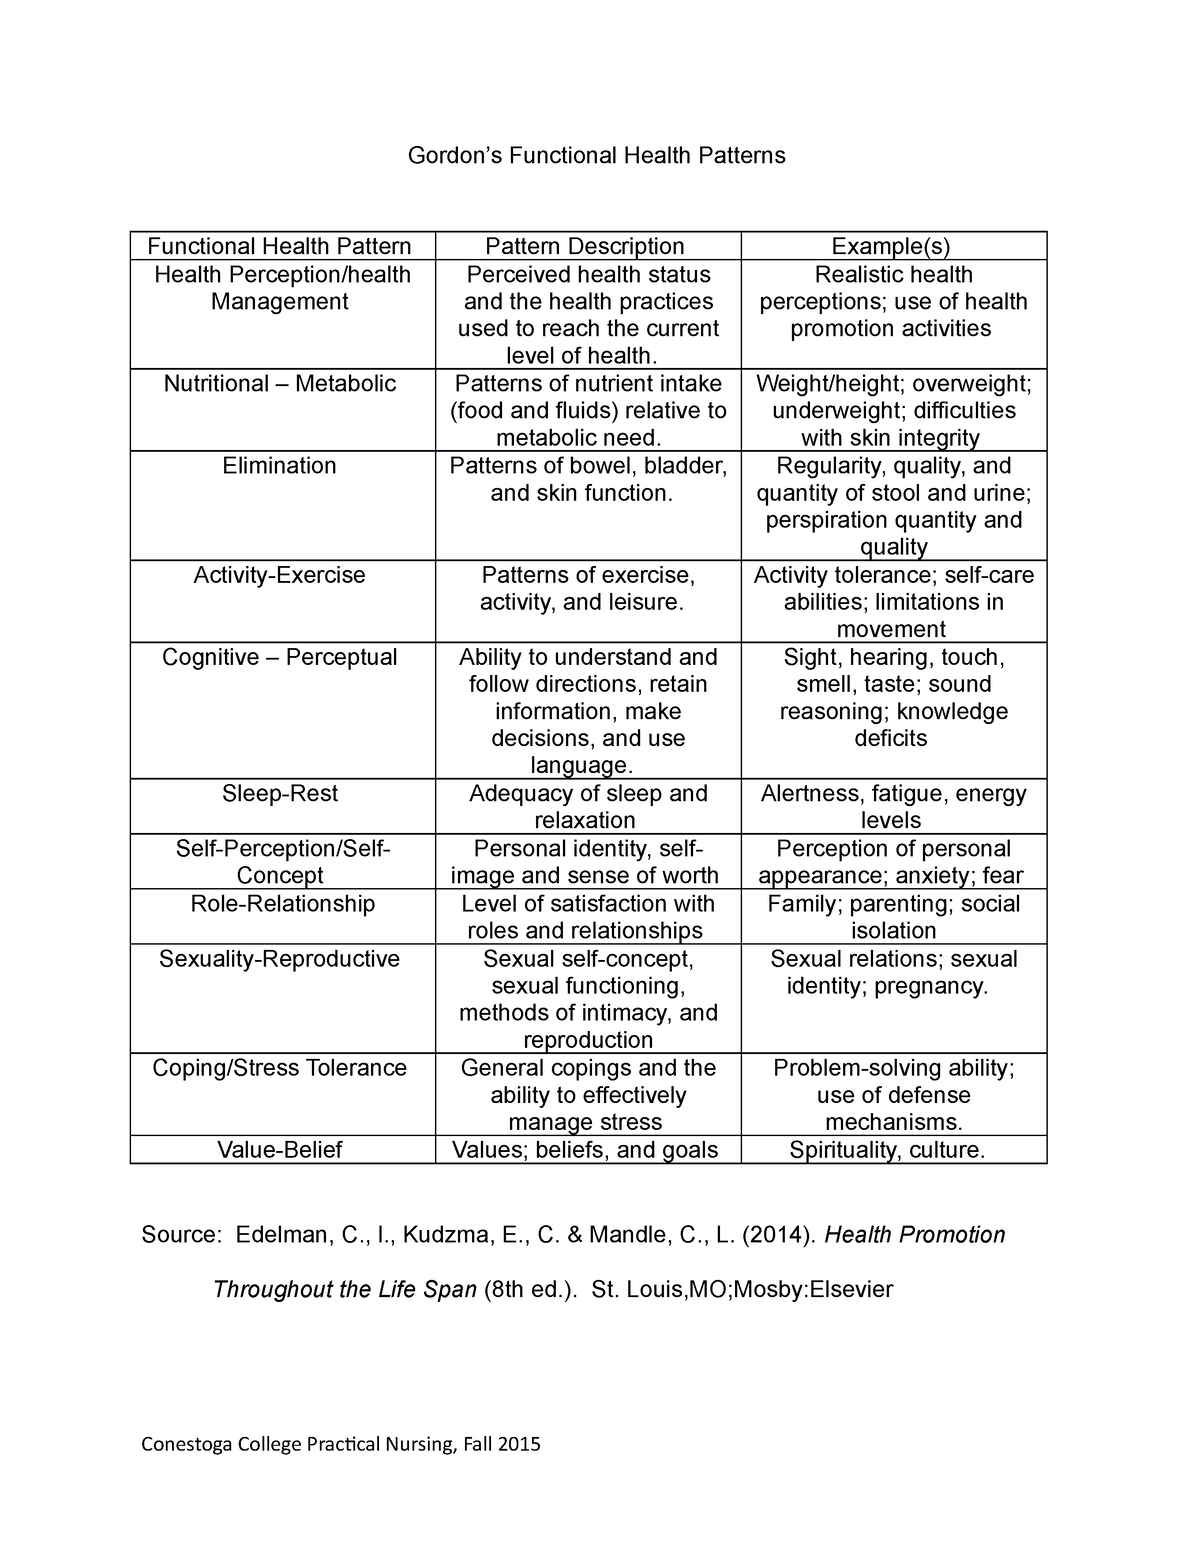
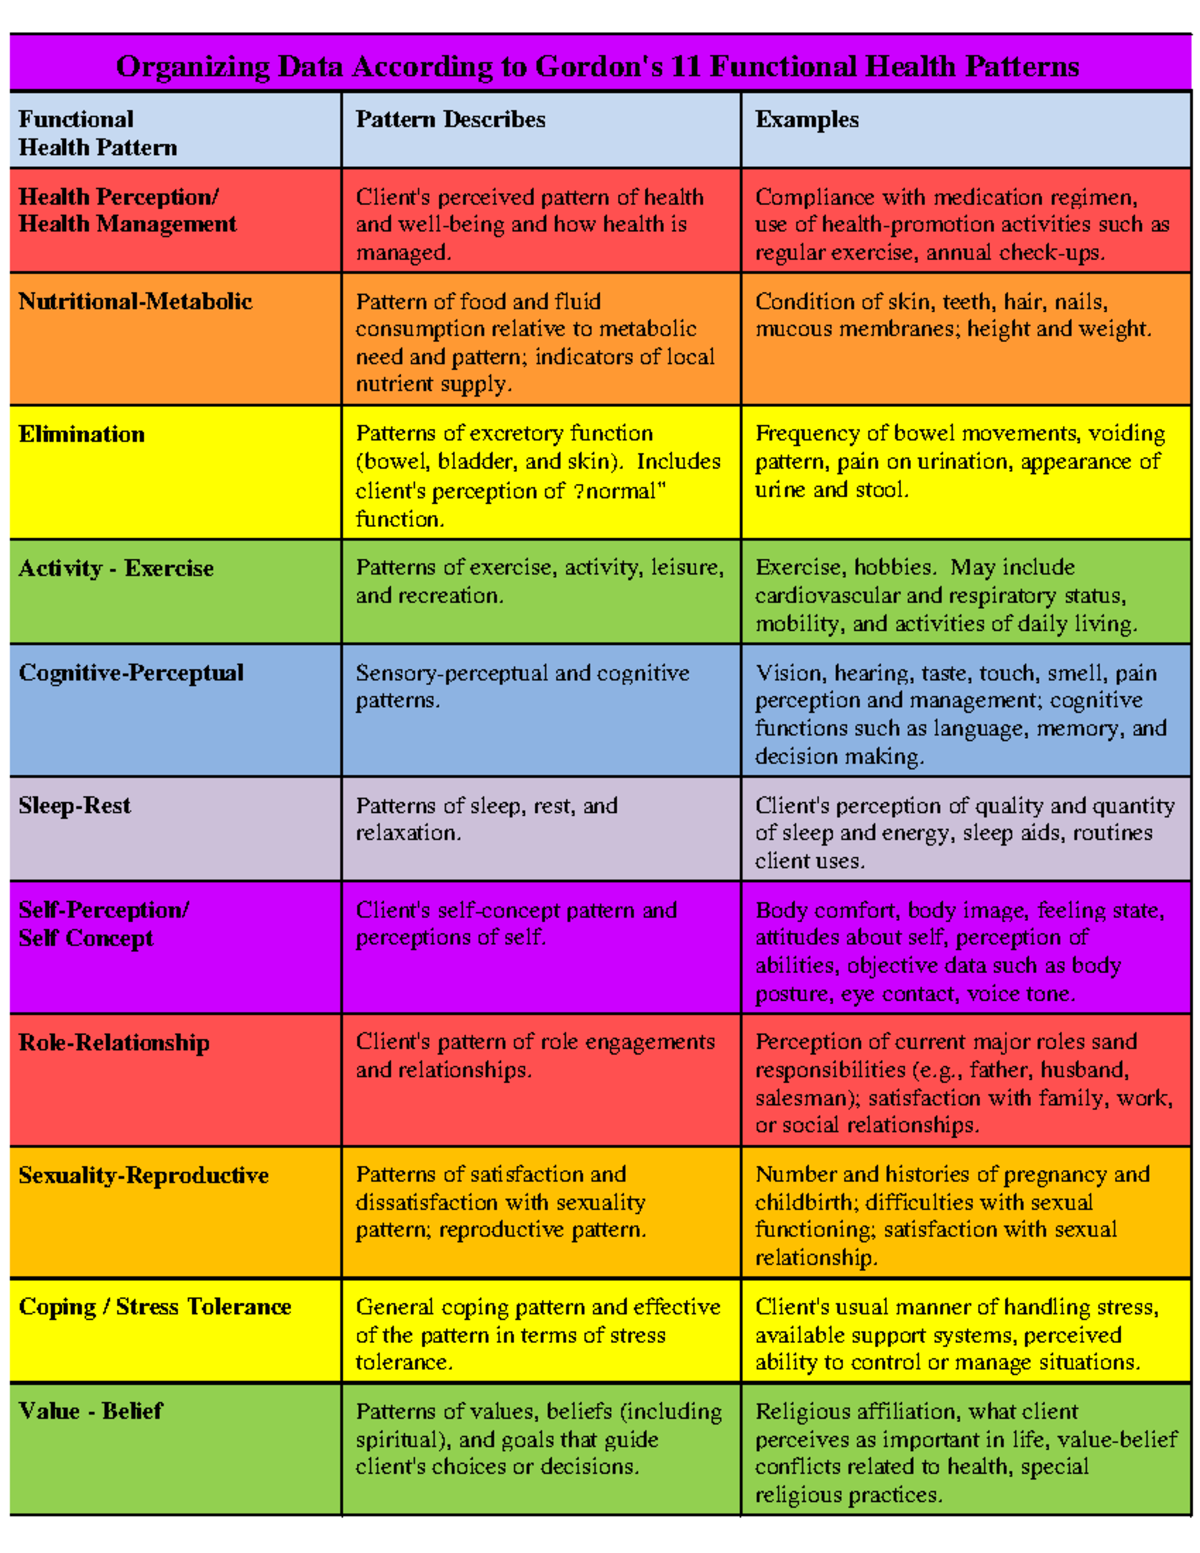
I spent years watching new grad nurses struggle with admission assessments. They would write four pages of narrative that said nothing useful, miss entire body systems because they were busy transcribing, and then spend twenty minutes trying to figure out where their nursing diagnosis actually came from. A nurse manager showed me the Gordon Functional Health Patterns framework and honestly it changed how I worked. Not because it was profound, but because it forced structure onto something that otherwise collapses into noise. The 11 patterns are: Health Perception–Health Management, Nutritional–Metabolic, Elimination, Activity–Exercise, Sleep–Rest, Cognitive–Perceptual, Self-Perception–Self-Concept, Role–Relationship, Sexuality–Reproductive, Coping–Stress Tolerance, and Value–Belief. Each one has specific cues you check. The goal isn't to fill every box perfectly every time. The goal is to stop forgetting whole domains of a patient's life because your brain defaulted to the cardiac system and forgot the rest.
Practical Use of the Gordon Functional Health Patterns in Real Assessments
Here's the straightforward way I teach it now. Pick up the assessment tool. Go pattern by pattern. For each one, answer three questions: Is there a problem? Is there a risk for a problem? Is the patient managing well? You don't need to write a paragraph per pattern. Two lines is enough. Three lines is pushing it. Most of my charge nurses cap it at six lines per pattern, and I agree with that limit. I remember one patient, male, 67, admitted for pneumonia. By the book, his Health Perception pattern looked fine. He took his meds, followed up with his PCP, denied smoking. But when I actually sat down and used the full Gordon Functional Health Patterns approach, the Nutritional–Metabolic pattern revealed he'd lost twelve pounds in three weeks without trying. His Activity–Exercise pattern showed he couldn't walk to the mailbox without stopping. The Sleep–Rest pattern flagged he was waking up every two hours. None of those would have jumped out if I was just charting organically. The weight loss alone changed the care plan. That's the actual value of this framework. It catches what free-form notes miss. Some people treat the 11 patterns as a checklist and rush through them in twelve minutes flat. Don't do that. The framework only works if you actually spend time in each domain. Twelve minutes is the absolute floor for a comprehensive admission, not the target. A decent focused assessment using the Gordon Functional Health Patterns usually takes 25 to 40 minutes depending on acuity. If you're finishing in under fifteen, you're skimming.
Common Mistakes That Make This Framework Worse Than Useless
The biggest mistake I see is treating the patterns as separate silos. They aren't. A patient with depression will show up in Self-Perception, Role-Relationship, Coping-Stress Tolerance, Sleep-Rest, and Nutritional-Metabolic simultaneously. If you document each pattern in isolation without linking them, your care plan becomes fragmented and your diagnoses contradict each other. I started adding a single cross-reference line at the bottom of each pattern section. It's usually just a phrase like "See also Activity-Exercise" or "Relates to Sleep-Rest." It takes ten seconds and saves the next nurse from reconstructing the picture yourself. Another mistake is assuming the framework covers everything. It doesn't. Social determinants of health, health literacy, insurance status, caregiver availability, transportation, food security. None of that lives cleanly in any of the 11 patterns. I've seen patients fall through the cracks because someone checked every box and moved on. When I run into that gap, I add a quickSocial Determinants subsection at the end of the assessment. It's not part of the official Gordon framework, but it keeps you honest. There's also the problem of digital templates. Most EHRs that implement the Gordon Functional Health Patterns flatten them into dropdown menus and checkbox fields. You lose nuance fast. A checkbox that says "Sleep-Rest: Adequate" tells you nothing about whether the patient sleeps six hours undisturbed or forty-five minutes in three-hour fragments with pain. I learned to use the free-text field even when the EHR makes it hard to find. It's worth the extra click. The alternative is documentation that looks compliant but is clinically empty.
Get the Full Details
When the Gordon Functional Health Patterns Framework Actually Fails You
This framework was built for adult medical-surgical populations in the 1980s. It works reasonably well there. It works poorly in pediatrics, psychiatry, and specialty areas like burn units or oncology clinics. In pediatrics you're assessing the family, not just the child, and the patterns don't account for that dynamic well. In psychiatry, Sleep-Rest, Coping-Stress Tolerance, and Self-Perception bleed into each other so completely that the framework starts duplicating work instead of organizing it. For those settings, I'd suggest using the Gordon approach as a partial scaffold and layering on a domain-specific tool on top of it. Don't try to force the full 11-pattern model into a population it wasn't designed for. Another limitation: the framework assumes the patient can self-report. When you're dealing with severe dementia, intubated patients, or toddlers, you're relying entirely on collateral history. That's fine, but you need to document the source of your information in every pattern section. "Patient reports" should become "Caretaker reports" or "Medical record review." It's a small habit that prevents liability issues down the line. If your unit is overwhelmed with census and you genuinely don't have 25 to 40 minutes per admission assessment, the Gordon Functional Health Patterns framework is going to feel like bureaucratic overhead. In that situation, I'd recommend starting with just the first five patterns, which cover the most acute physical domains, and adding the remaining six during subsequent shifts. It's not ideal. It's better than skipping the assessment entirely and writing a narrative blob that no one can read later.
The original framework was published by Marjorie Gordon in the early 1980s and adopted by NANDA International for nursing diagnosis classification. It's still in widespread use in nursing education and clinical practice. You'll find implementation guides, printable forms, and EHR templates online. Most hospital libraries have the original source material. The practical takeaway is simple: the framework only helps if you actually use it deliberately instead of checking boxes mechanically. The patterns organize your thinking. They don't replace it.