What Grip Occupational Therapy Actually Involves
Most people who come to grips with occupational therapy are dealing with something that started after a hand injury, a stroke, or a repetitive strain that just never went away. The approach is straightforward in theory: rebuild grip strength, improve fine motor control, and make everyday tasks easier again. In practice, it is messier than that. I have spent years working with patients who needed grip rehabilitation after carpal tunnel release, tendon repairs, and even amputations. The therapy itself is not one single thing. It is a collection of interventions aimed at restoring the ability to hold, squeeze, and manipulate objects with enough force and precision for daily life.
Grip Occupational Therapy
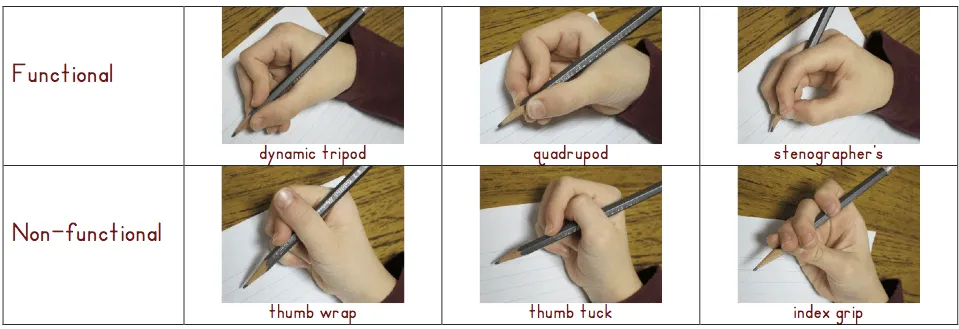
When someone asks about grip occupational therapy, they are usually looking for exercises, tools, and a general framework. Here is what that looks like on a typical workbench. You start by assessing grip type. There is power grip, which is holding something like a hammer or a bottle. There is precision grip, which is picking up a coin or buttoning a shirt. Then there is three-jug pinch, lateral key grip, and a handful of other variations that therapists use to describe exactly what is failing. Most people think their grip is weak when actually the issue is coordination or sensory feedback. Testing every variation matters more than you'd expect. The standard toolkit includes therapy putty in varying resistances, hand grippers with adjustable springs, dynamic grip trainers that measure force over time, and basic items like therapy clay, stress balls, and folded towels for wringing. Some clinics use biofeedback devices that show grip force on a screen. Others just use a dynamometer. A good one costs around two hundred dollars and reads in kilograms or pounds with decent repeatability.
Progression follows a predictable arc. Early stage work focuses on range of motion and gentle activation. You get someone moving their fingers without fighting pain. Then you introduce isometric holds. Squeeze the putty and hold it for five seconds, release, repeat. The next phase is dynamic resistance, where you're working through a range of motion under load. Fine motor control comes last, when the hand can handle force without trembling or giving out. One thing beginners miss is that grip recovery is not linear. I had a patient six weeks post flexor tendon repair who could hold a light grip for a few seconds and then seemed to plateau for three weeks straight. We changed the angle of resistance, switched from a palmar grip to a tip pinch drill, and suddenly the numbers jumped. The tissue was ready; the exercise just didn't match the deficit anymore. Here is another common pitfall. People gravitate toward the gripper with the highest resistance they can manage. That is backwards. Gripping hard with poor form reinforces bad patterns and loads the flexor tendons at awkward angles. Start light. Ten reps of a resistance that feels manageable. Build from there. Force is not the goal in early stages. Control is.
Get the Full Details

There are limitations worth stating plainly. Grip therapy does not fix nerve compression. If someone has persistent median nerve entrapment, no amount of putty work is going to resolve the underlying issue. They need a proper diagnosis and likely a splinting or surgical consult. Similarly, if a patient has active joint inflammation from rheumatoid arthritis, aggressive grip work can make things worse. You have to know when to stop pushing. For home programs, the most practical setup I have found uses a set of putty resistances, a spring-loaded gripper, and a soft therapy ball. Twenty minutes a day, split into two sessions, is enough for most people. More than that and you're just creating irritation. Consistency beats intensity every time. I've seen clients go three days hard and then quit because their tendons were sore. Better to do ten minutes daily and keep it boring. If grip strength is severely limited, you can start with assisted grip drills. Use your other hand to help close the affected one around an object, then take over the squeeze. It feels clumsy at first. It works.
Some clinicians add thermal modalities before sessions. Warm packs for ten minutes increase tissue pliability and make early exercises less painful. Ice after, if there is any swelling. Nothing fancy. Just standard rehab protocol. The bottom line is that grip occupational therapy is effective when it is specific to the person's deficits and adjusted as those deficits change. It is not a fixed routine you follow from week one to week twelve. If you are designing a program or trying one yourself, track the numbers. Write them down. Reassess every two weeks. If the same exercise stops producing results, change it. That is the whole method in practice.


