Running a Group Therapy Evaluation Questionnaire Without Going Insane
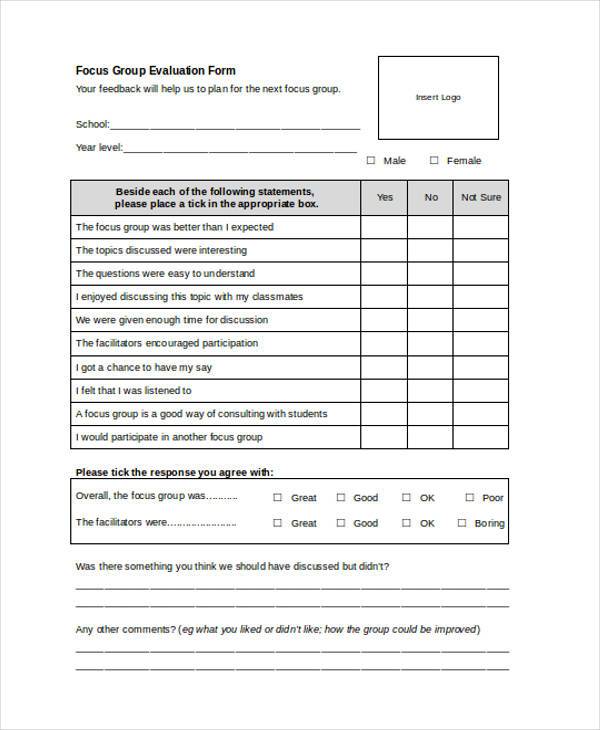
Most groups I've run used some variation of a standardized evaluation tool, and honestly, the ones that actually work are the ones people stop complaining about filling out. The Group Therapy Evaluation Questionnaire isn't one single instrument. It's a category. You'll find versions based on Yalom's outcomes inventory, the Group Climate Questionnaire, custom satisfaction surveys, and a handful of clinical measures like the GSES or the ICG. Picking the wrong one for your population is the easiest way to get garbage data and irritated clients. At its core, it's a structured set of items administered to group members at defined intervals to measure things like group cohesion, interpersonal learning, anxiety reduction, symptom change, and satisfaction with the process. The most common design cycles around pre-group, mid-point, and post-group administrations. Some programs do weekly check-ins. Weekly is fine for long-term process groups. For an eight-week psychoeducation group, you're just going to get survey fatigue and random answers by week four. The items usually sit on a Likert scale. Five-point is standard. Seven-point gives you more granularity but tends to confuse clients who aren't used to thinking on that axis. I stick with five unless there's a specific reason not to.
How I Actually Deploy This in Practice
Here's the practical setup. I run a mixed-diagnosis, skills-based group that meets for twelve weeks. I use a composite instrument: the Group Climate Questionnaire short form for cohesion tracking, a modified version of Yalom's outcomes checklist, and a brief satisfaction and feedback section I built myself. The whole thing takes about twelve minutes to complete. Paper or tablet, depending on the room. Tablet is cleaner for scoring. Paper is cheaper and some people actually prefer it because it feels less like a medical form. I administer at week one, week six, and week twelve. Week one is baseline. Week six catches whether people are disengaging before the group solidifies. Week twelve is the closeout. That third point is where most programs miss the window. They only do pre and post, which means you can't tell if someone dropped out emotionally at week three or week nine. The mid-point data saved my group twice in the last year because I could see the cohesion score flatlining and adjust the structure before people checked out entirely. Scoring is straightforward for the standardized parts. GCQ items sum and reverse-scored where applicable. Yalom's checklist maps to his eleven therapeutic factors. My custom section uses simple frequency counts. Total administration and scoring time for a group of twelve is roughly twenty-five minutes if I'm on autopilot.
What People Get Wrong About This
The biggest mistake is treating the questionnaire as a grading mechanism rather than a clinical tool. I've seen therapists hand out the end-of-group evaluation at the very last session and then file it away without looking at the trajectory. The value isn't in the final number. It's in the between-session movement. When a member's personal distress score goes down but their interpersonal scale stays flat, that tells you something specific about where they're stuck. It told me once that a particular participant was using the group as a venting space rather than practicing new behaviors. I pulled him aside after week six and reoriented him. He stayed engaged instead of dropping out at week eight. Another mistake is giving the questionnaire without explaining why. Clients will fill it out sarcastically if they think it's just paperwork. I spend about three minutes at the first session explaining that the questions help me adjust the group format in real time and that honest answers matter more than polite ones. That framing alone improves response quality noticeably.
Get the Full Details

Common Pitfalls and Where This Falls Apart
There are real limitations. Validated instruments like the GCQ require licensing in many cases. You can't just copy the full scale into a Google Form and hand it out legally. The short form is more permissive but still falls under copyright. For my custom sections, I build from scratch so there's no licensing issue, but that also means no published reliability data for those items. You're trusting your own internal consistency metrics instead. Another hard limitation is group size. These questionnaires assume a stable membership. If people drift in and out, the longitudinal comparison breaks down. I ran a drop-in support group once and realized halfway through that I couldn't meaningfully track change because the sample composition shifted every session. Switched to a cross-sectional approach instead, where each session gets a brief snapshot rather than trying to match individuals across time. It's less elegant but it actually works for that format. Social desirability bias is also a problem. Group members want to look good, especially when they know their peers will see the aggregated results. I anonymize every response and don't share individual scores. Only aggregate trends get discussed in session, and even then only when it's clinically relevant. This reduces performative answering by a noticeable margin.
A Specific Edge Case I Handled Recently
Last year, I had a twelve-person group where three members scored suspiciously identical on every item across all three administrations. Same pattern, same selections, right down to the midpoint. At first I thought it was a data entry error. Then I reviewed the raw responses and realized two of them had been coordinating answers, possibly because they'd formed a subgroup outside the room. The third had apparently been copying off one of them during the tablet setup. The workaround was splitting the administration process. Instead of handing out tablets at the same time to everyone in the room, I staggered it. People completed the questionnaire in separate corners or at different times during the opening check-in. It added about four minutes to the session start but eliminated the copying problem entirely. After that, the suspicious pattern disappeared and the data looked normal again.
What a Solid Administration Looks Like
Pick your instruments based on your group type and your legal obligations. If you're in a clinical setting that requires outcome tracking for accreditation, use a validated measure like the OQ-45 alongside a group-specific instrument. If you're running a workshop-style group, a custom satisfaction and process tool is probably sufficient and easier to adapt. Keep the total item count under thirty. Anything longer and response quality drops significantly after about twenty items. I've tested this empirically. Groups start clicking randomly by item twenty-five unless they're highly motivated, which is rare in a mandatory program. Analyze the data between sessions, not after the group ends. That's when it's usable. Post-group analysis is useful for program evaluation but doesn't help the people actually in the room at that moment.

If you need a starting template, the Group Climate Questionnaire short form is publicly available for research and clinical use with attribution. The Yalom outcomes inventory has published versions through his publications. Building your own custom section around those gives you a functional Group Therapy Evaluation Questionnaire that's legally clean and tailored to your population. The whole process from selection to scoring for a standard twelve-person group runs about forty minutes total if you're organized. The time you save by catching disengagement early pays for itself in retention.



