Building a Group Therapy Intake Form That Actually Works
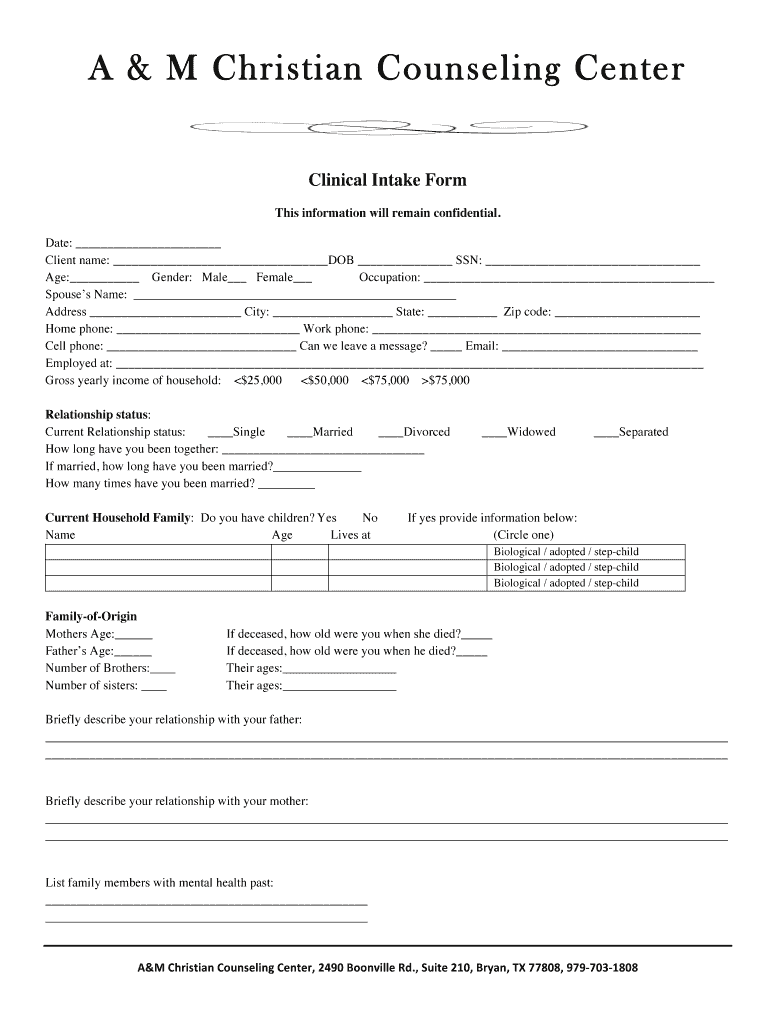
A Group Therapy Intake Form is the thing that sits between someone wanting help and the group actually starting. Most people design these backward. They copy-paste a clinical intake template from 2014, slap a few field names on it, and call it done. Then they wonder why patients bounce off it before they even get to the screening question. The intake form for group therapy needs to answer three things: can this person tolerate a group setting, what are we seeing in them, and does the group need to know anything before the first session. That's it. Everything else is compliance theater.
What the Group Therapy Intake Form Should Actually Contain
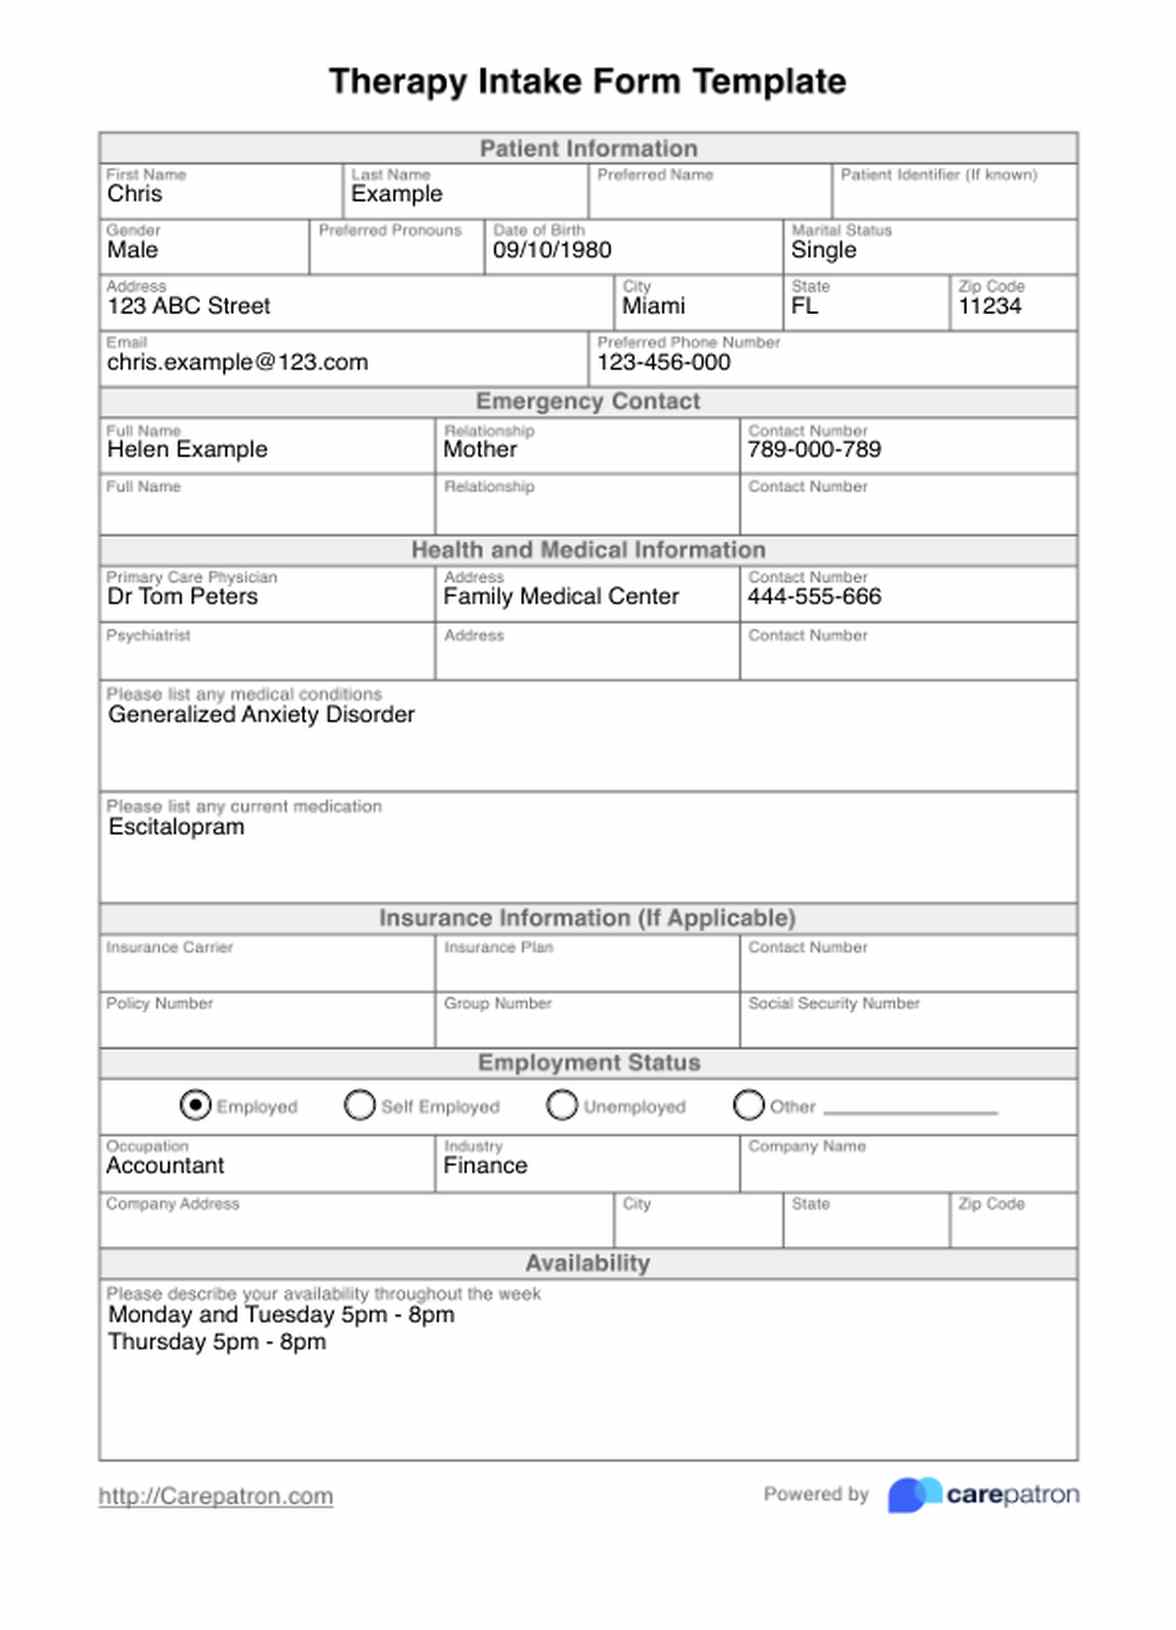
Start with demographics and insurance, because you need that stuff anyway. Then move to consent. Informed consent for group therapy is not the same as individual consent. People need to understand that confidentiality has structural limits in a group. Other members are not bound by HIPAA. This is where most intake forms fail. They include a consent paragraph but don't make the group-specific risks legible. I wrote one for a trauma group where I had a participant read the consent back to me. Two out of five couldn't articulate the confidentiality limitation. We ended up switching to a verbal consent walk-through with a short written acknowledgment instead of relying on the form alone. After consent comes screening. Risk assessment. Current diagnosis or reason for referral. Medication list. Prior therapy history. Presence of substance use. Acute suicidality screen. These are standard. What most people skip is the group-readiness screen. Can this person handle group dynamics. Have they been in groups before. What happened in those groups. Do they tend to dominate or withdraw. Do they have a history of acting out in groups. These questions predict dropout and group disruption more than any diagnosis does. I ran into this with a client who had excellent insight on paper but in their first group session they interrupted three times per turn and redirected every topic back to themselves. The intake form had asked about prior group experience. They checked yes. They just didn't mention that their previous group ended because they were asked to leave. If you want a workaround for that gap, add a brief behavioral history question like: When you've been in a group before, what did others typically say went wrong. It's blunt. It works.
How to Design the Intake Process
Don't build one massive form. Split it into three parts. Part one is the clinical screen. Part two is the group readiness assessment. Part three is the consent and administrative paperwork. Send part one first. If they screen out, you never wasted their time on part two. This usually cuts the process down from a full 45-minute intake to about 20 minutes for the people who actually move forward. Use branching logic if your platform supports it. A yes on active substance use should route to different follow-up questions than a no. A yes on current suicidality should surface a safety protocol, not just sit on the form. Most intake platforms let you do this without custom coding. Set the branches up before you open it to a single client. Keep the language at a sixth-grade reading level. People fill these out when they are already stressed. Long paragraphs get skipped. Skipped sections get interpreted as no answer. No answer is not the same as a clean bill of mental health.
Get the Full Details
What to Do With the Data
The intake form is not a storage unit. It is a screening tool. Every field you collect should feed a decision. If a field doesn't change whether someone gets placed in a group, dropped, or sent elsewhere, drop the field. I've seen forms with 80 fields and therapists who couldn't name which ten mattered. That's a form that adds liability without adding clarity. Build a summary view. Not the raw form. A one-page summary that shows risk flags, group readiness score, contraindications, and recommended placement. This saves time during the actual intake discussion and reduces the chance you miss something because you were skimming. A good summary takes about five minutes to generate from a properly structured form.
Pitfalls
One counter-intuitive thing to know: more fields do not equal better screening. I used a 90-field form once and found that twelve fields accounted for every clinically significant flag across six months of intake data. The other seventy-eight were noise. Cutting the form to forty fields and retraining the team took about three days and improved completion rates from sixty-four percent to eighty-nine percent. People do less work when the work matters. Another thing people get wrong is timing. Sending the form too close to the first session creates pressure. Sending it too early creates attrition. The sweet spot I've used is seven to ten days before the session with a reminder on day five. This gives people time to reflect without forgetting entirely. There are limits. An intake form cannot replace a clinical interview. It cannot catch malingering. It cannot detect when someone is being coached by a partner to answer in a certain way. It cannot replace assessing whether a person actually understood the group rules when you told them in person. Use the form as a filter, not a diagnosis. If someone screens green across the board but walked in with a flat affect and a tight jaw, the form is lying.
If your setting handles high-acuity populations, supplement the form with a phone screen or a brief video call before group placement. I've done this for PTSD groups where the failure rate was too high relying on the form alone. The call takes twelve minutes and catches more red flags than anything on paper.