The thing nobody tells you about group formats
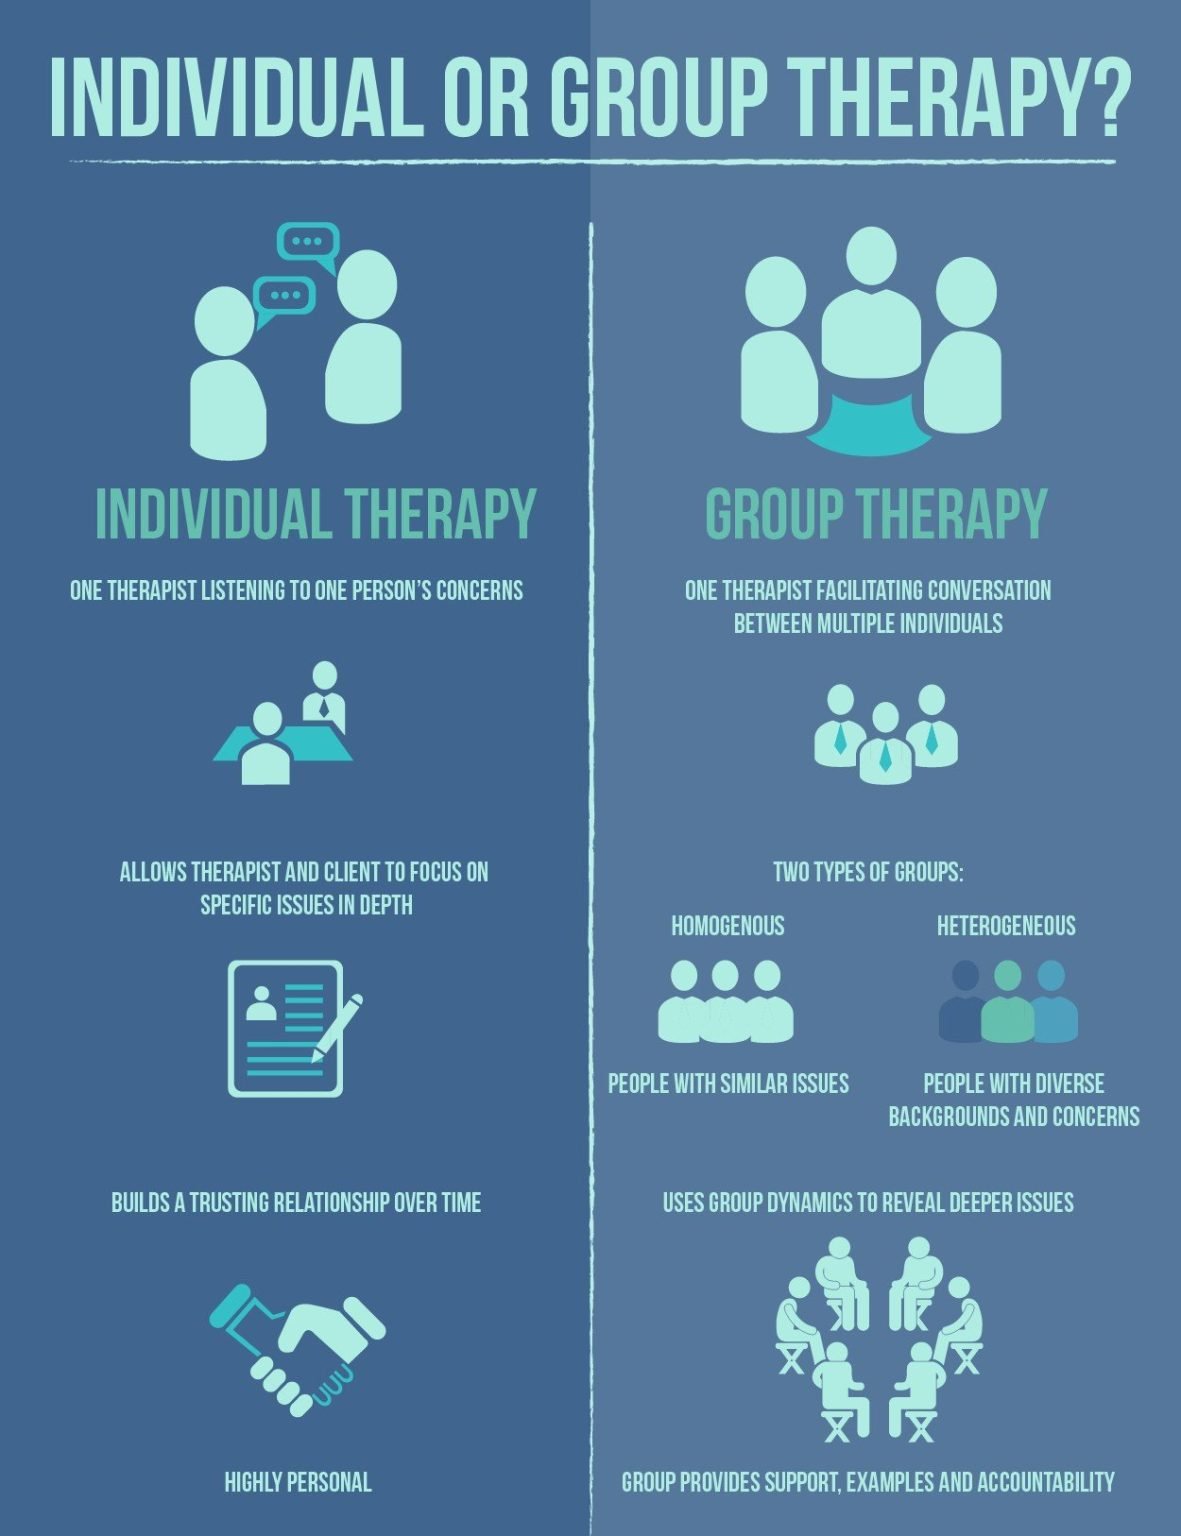
Individual therapy gets the spotlight in pop culture, and for good reason. One-on-one feels private and focused. But if you have actually sat in a treatment room with eight people and a facilitator, you know the dynamic shifts in ways textbooks barely touch on. Group therapy is typically more effective than individual therapy for patterns that are relational by nature. That phrasing matters because it narrows the field significantly. Interpersonal patterns, shame cycles, and social anxiety. Those three categories dominate the research. Yalom's work from the seventies still holds up remarkably well, even if the language around it has softened. The curative factor isn't mystery. It is corrective emotional experience repeated across multiple relationships in real time. In individual therapy, the therapist is the only mirror. In a group, there are seven other mirrors looking back at you simultaneously. That redundancy is what creates the effect. I worked in an outpatient behavioral health setting for several years before moving into consultation. One afternoon, a guy named Daniel came in for what was coded as depression. Twenty minutes in, he had dismantled the entire group's sense of safety by making passive aggressive comments that everyone felt but nobody named. In individual therapy, a clinician might spend three sessions gently exploring that pattern. In group, it played out in real time. The group turned to him and actually said what was happening. Daniel left the session shaken. He came back the next week. By session four, he was naming his own behavior before anyone else had to point it out. That is the mechanism. It is not gentle. It is efficient.
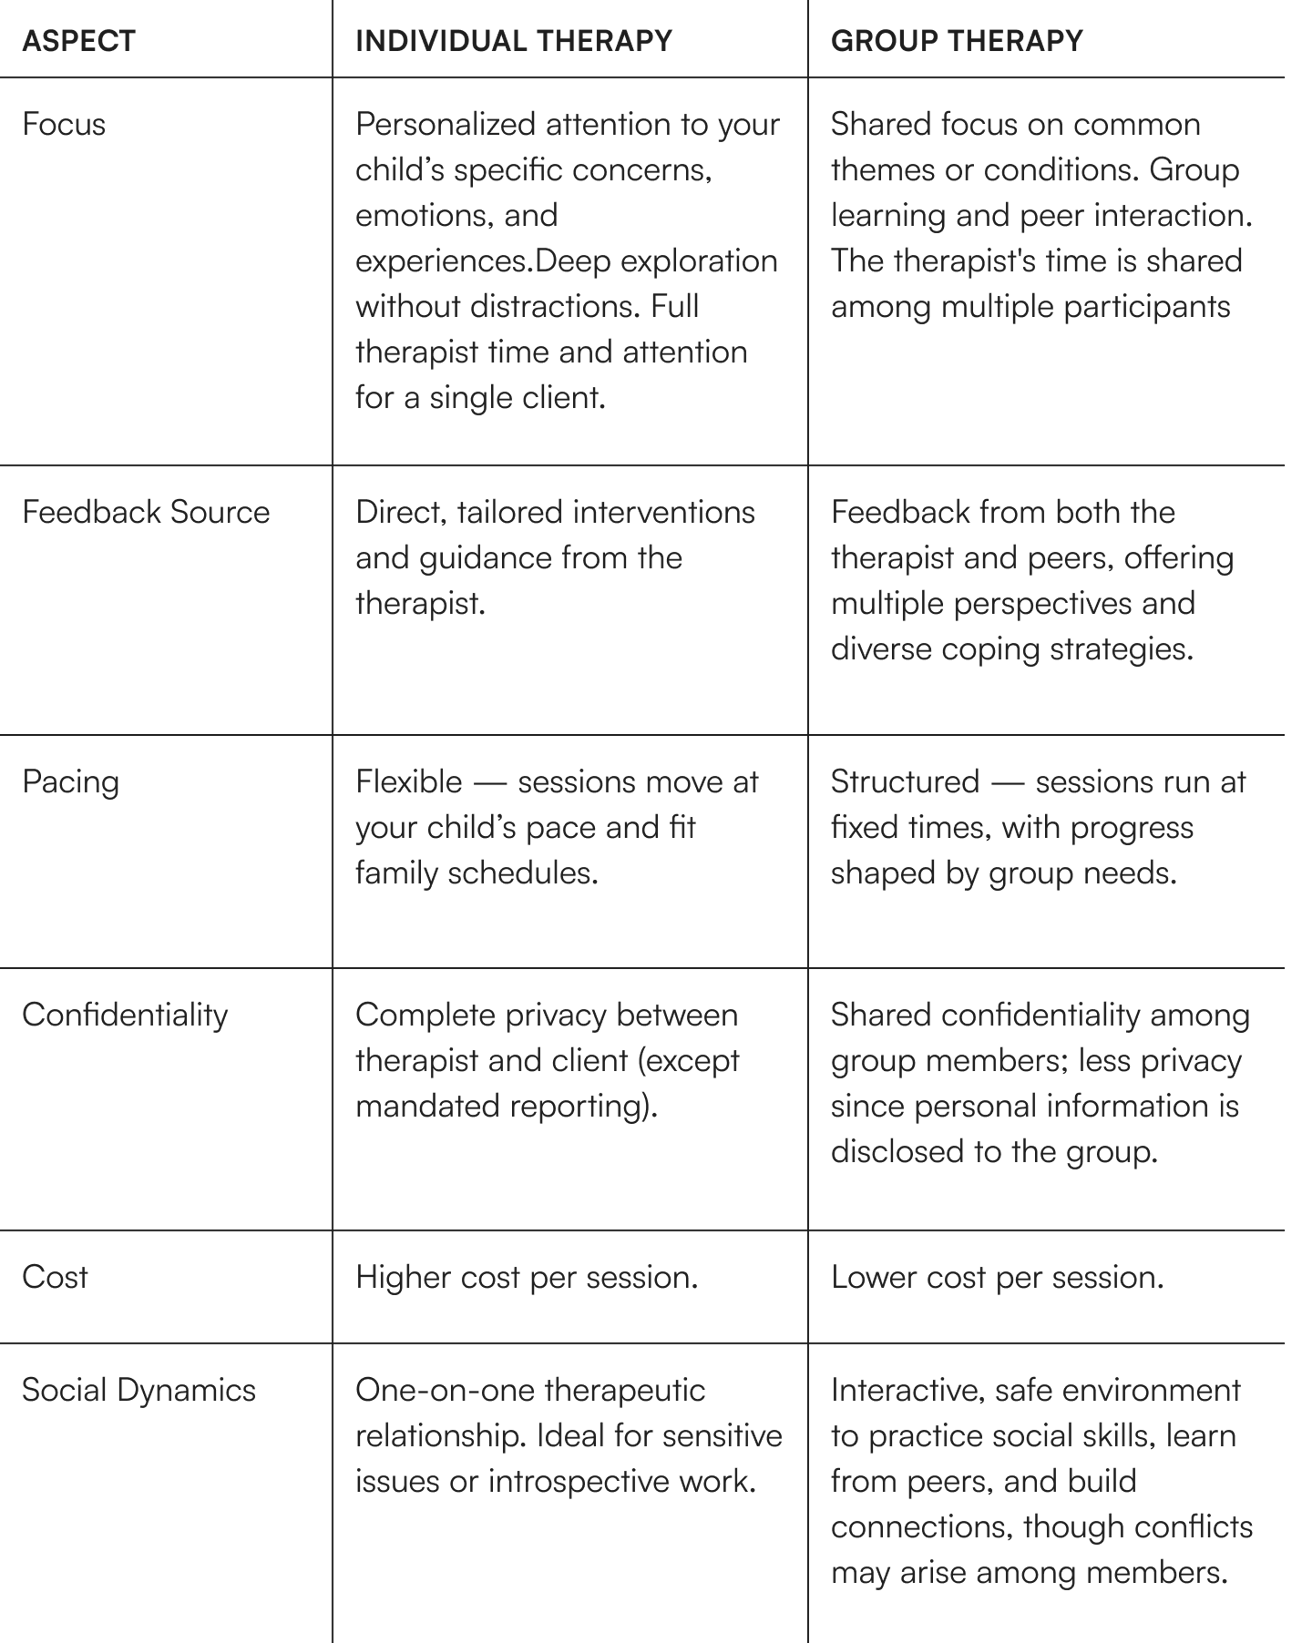
The research numbers support this but they are not dramatic. Meta-analyses on social anxiety usually show medium effect sizes for group CBT, often around d = 0.70 to 0.85. Individual CBT lands somewhere in the 0.75 to 0.90 range. The difference is small. What is not small is the cost per patient and the generalization factor. Skills learned in a room with other people actually transfer to other people more readily than skills practiced in a soundproof office. That is why psychiatric hospitals leaned heavily into group modalities before budget cuts restructured almost everything in the late nineties.
What actually happens in a session
A typical trauma-informed process group runs ninety minutes. The first ten minutes are check-in. Someone will say they had a rough week. Someone else will say nothing much happened. The facilitator does not dig. They wait. By minute twenty-five, two people will be indirectly arguing about something entirely different. That is when the work starts. The facilitator asks them to slow down and describe what is happening between them right now. Not the history. The here and now. This is where most people new to group therapy get confused. They expect insight. They get confrontation delivered with surprisingly little edge. The group punishes bad behavior through withdrawal of attention rather than through direct attack. That is a design feature. If the therapist had done that, it would feel parental. When five other people do it, it feels like reality. I once ran a substance use group where one participant, let's call her Maria, kept arriving late and checking her phone during exercises. The group stopped engaging with her entirely after the third occurrence. She escalated. Then she got quiet. The facilitator asked the group what they noticed. Someone said, she is still here but we have stopped treating her like a person. Maria broke down. It was uncomfortable. It was also the most honest conversation any of us had in that room that quarter. She stayed for eighteen more sessions after that.
Get the Full Details
Conditions where group clearly wins
Social anxiety disorder. The data is consistent. Group exposure exercises beat individual ones because the exposure is inherently social. You cannot practice ordering coffee while avoiding eye contact with your therapist and expect that skill to survive a busy cafe. Substance use recovery. The AA model exists for a reason even if the spiritual framing does not work for everyone. Peer accountability reduces relapse rates compared to solo treatment by roughly twelve to fifteen percent in longitudinal studies. Group therapy adds structure and skill building on top of that peer network. It is not magic. It is probability management. Chronic shame and personality pattern work. Borderline traits, avoidant traits, narcissistic defenses. These are relational problems. Treating them relationally produces better outcomes than treating them intrapsychically. I have seen people with avoidant personality features make more progress in twelve group sessions than in two years of individual therapy. The group does not accommodate the avoidance. The therapist in individual work often has to fight harder to prevent accommodation.
Eating disorders in adolescent populations. Multisystemic group approaches show stronger maintenance of weight restoration at six month follow up. The peer component creates a normative environment that families alone cannot replicate.
Where group therapy fails completely
Acute suicidality. Active psychosis. Severe dissociative disorders without stabilization. People in crisis need containment that a group cannot provide. A group of eight strangers is not an emergency response system. If someone is actively planning self-harm or experiencing command hallucinations, individual care with frequent monitoring is the only responsible option. Do not place these clients in groups to save money. That is negligence dressed as efficiency. Active domestic violence perpetrators. Some programs attempt group work with this population. The results are mixed at best and dangerous at worst. Victims often end up safer when accountability happens in individually monitored settings with specialized protocols. A group room is not a courtroom and a facilitator is not a parole officer. Severe autism spectrum adults without coping skills. Some autistic people benefit enormously from social skills groups. Others experience sensory overload that makes the format impossible. The difference often comes down to whether the person can tolerate unpredictable social input for ninety minutes. Screen for that upfront. It saves everyone pain.

Practical considerations most guides skip
Group composition matters more than most clinicians admit. Mixing severe eating disorder patients with mild social anxiety patients creates resentment. The eating disorder clients need intensive peer modeling. The social anxiety clients need gentler pacing. Homogeneous groups produce better outcomes within diagnosis categories. Heterogeneous groups teach more about real world diversity but require more skilled facilitation. Size is a variable. Six to eight members is the sweet spot for most process groups. Beyond ten, dominant personalities take over. Below five, there is insufficient interpersonal diversity for the corrective experience to work. Four people is basically a family. Eight gives you enough relational variety without losing control. Segregated groups for specific populations exist for a reason. Men only, women only, LGBTQ+ affirming, veteran specific. Trauma survivors often need gender-concordant groups initially. Mixed gender groups can work after stabilization but pushing traumatized clients into mixed groups too early reproduces power dynamics they are trying to process. The timeline depends on the population. Some programs wait six weeks. Others wait six months. Neither approach is wrong.
Cost analysis favors group heavily. A typical individual session runs two hundred to three fifty depending on location and insurance. A group session might cost forty to seventy per participant. That is not trivial. Health systems that understand this allocate more group slots. Clinics that do not understand it allocate fewer and wonder why waitlists are six months long.
A specific edge case I encountered
Several years ago, a client named Trevor was referred to our group program with OCD and severe contamination fears. Standard exposure and response prevention in individual therapy had helped him somewhat but plateaus at moderate severity are common. He was not ready for inpatient. Group was the next step. The problem was that Trevor could not sit near other people. Not because of social anxiety. Because of germ contamination beliefs. He sat in the corner chair, wore gloves, and declined all touch-based exercises. The group was dysfunctioning around him. People were either accommodating his rituals or resenting them. I pulled the group aside and restructured the session. Instead of forcing Trevor into standard exposure, I used him as the focus of a metacognitive exercise. The group practiced observing their own urge to accommodate or confront while staying present. Trevor practiced sitting five feet from another person while resisting the compulsion to sanitize. It was slower than standard ERP. It took eight additional sessions before he could participate in a normal group exercise. But he completed the program and maintained gains at one year follow up. The workaround was acknowledging that standard group protocols assume a baseline of participation capacity that some clinical presentations simply do not have at intake.

What the research does not emphasize enough
Hope induction. Yalom identified this as a curative factor but modern papers rarely quote it. Being in a room with people who are further along in recovery than you are changes something fundamental in how you view your own trajectory. Individual therapy has the therapist as model. Groups have multiple models. That multiplicity reduces the romanticization of the therapeutic relationship. You see the facilitator make mistakes. You see peers struggle and recover. You see that progress is non-linear across multiple lives simultaneously. Universality is the second underrated factor. People enter therapy believing their problems are uniquely pathological. Group membership contradicts that belief within the first session. Hearing someone describe the same family dynamic you described using different words collapses isolation faster than any interpretation a therapist could offer. The evidence for this is anecdoctal in quality but the effect size in practice is large enough that skip-it-if-you-can recommendations seem careless. There is a third factor that rarely appears in published studies but appears in every competent clinician's notes. Accountability. In individual therapy, missing a session is a conversation. In group therapy, missing a session is visible to seven people. That visibility changes attendance rates. Higher attendance changes outcomes. The mechanism is simple social accountability, not mystical group power. Simple social accountability is still powerful.
If you are considering this pathway for yourself or a client, the decision tree is straightforward. Relational pattern is the problem, group is likely the better first choice. Acute crisis or severe instability, individual care first. The overlap zone where both could work is where most people sit. In that zone, cost, access, and personal preference determine the route. Do not romanticize either format. Both produce change. One does it through multiple relationships. The other does it through depth in one. Neither is superior across all conditions. The evidence does not support that claim. The evidence supports a narrower, more useful claim.