.png)
Group Therapy Notes That Actually Work
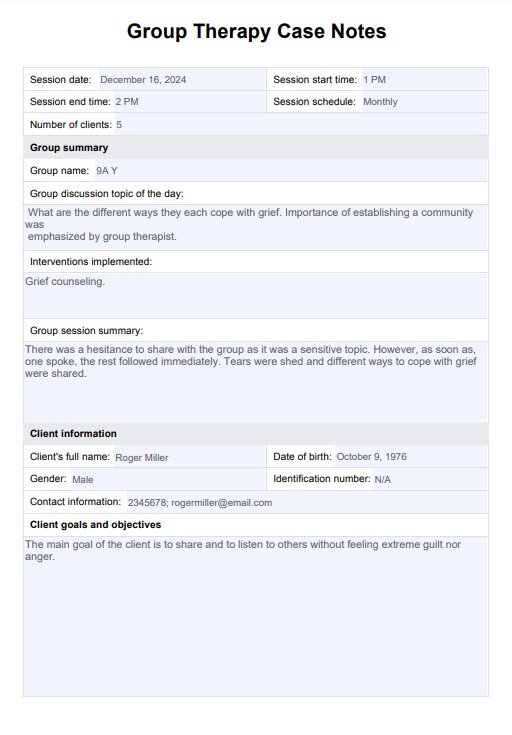
I've been writing these for about a decade across outpatient clinics and correctional facilities. The short version is that most group therapy note systems fail because they try to do too much in one document. You're tracking fifteen people's participation in a single session, plus group dynamics, plus any individual disclosures, plus your treatment plan alignment. If you don't have a tight system, you end up with notes that are either too vague to survive an insurance audit or so detailed that you spend forty-five minutes after every session just trying to finish them. The format I use is a modified SOAP structure. S for subjective, O for objective, A for assessment, P for plan. But the key difference from individual therapy notes is how you handle the subjective and objective sections when fifteen people are in the room. I use a participant shorthand system. Instead of writing full sentences for each person's comments, I note initials and brief descriptors. Something like JS rephrased T's concern about family conflict, then shared own trigger. This keeps the note readable and audit-ready without turning it into a transcript. The objective section is where most people lose clarity. You're documenting group behavior patterns, not individual behavior. I track engagement level per person on a simple scale—participating, observational, resistant, disruptive—and note any shifts mid-session. If someone who was silent for three weeks starts speaking, that matters. If the group collectively deflects away from a heavy topic, that matters. If two members have a micro-conflict that the rest of the group watches but doesn't intervene in, that's clinical data worth capturing.
Assessment ties it to treatment goals. Each member should have at least one treatment objective referenced in the note, even if briefly. CMOP for PTSD, improved emotion regulation for DBT groups, relapse prevention skills for substance abuse. You're not assessing the whole group as a single patient. You're assessing how the group environment is serving each person's plan. One common mistake I see is therapists writing assessment language that applies to the group collectively and never connects it back to individual progress. Insurance reviewers flag that immediately. They want to see the link between what happened in the room and the member's documented goals. Plan is straightforward. What happens next week? Continue curriculum topic four. Assign homework. Refer member KR for individual session due to disclosed self-harm ideation during group. That sort of thing. Keep it action-oriented and time-specific. I learned the hard way that confidentiality in group notes is different from individual notes. In individual therapy, you can be specific. In group, anything you write about what a member said is technically in a document that could be subpoenaed or accessed through records requests. I stopped using direct quotes after a client's partner filed a records request during a divorce proceeding and read another member's disclosed infidelity in my notes. Now I paraphrase everything. Instead of JS reported being cheated on by spouse, I write JS discussed relationship distress and its impact on triggers. Same clinical meaning, far less exposure risk.
Another thing nobody warns you about: the timing problem. Group sessions run long. People go over their time limits. You schedule thirty minutes for processing and it takes fifty. If you plan to write notes right after, you're already behind. I shift my documentation to begin during the last ten minutes of session. I jot shorthand marks on a scratch pad as the session winds down while everyone is still doing closure exercises. By the time I'm packing up, I have enough detail to expand into full notes within twenty minutes instead of rebuilding the session from memory an hour later. The downside of this system is that it requires discipline. If you skip the in-session shorthand, you're writing from scratch and accuracy drops. I've caught myself filling in plausible details from previous sessions when I was tired and rushed. One time I had a member marked as participating in a role-play exercise when she had actually remained silent the entire session. It went into the chart before I caught it. That's why I always do a second pass on day two, before the next session. Fresh eyes catch those errors fast. For templating, I use a basic electronic health record template with dropdowns for engagement level and treatment goal codes, plus a free-text area for the narrative. If you're using paper charts, a pre-printed grid with member initials across the top and engagement codes down the side saves probably twenty minutes per session compared to writing everything out. I've seen therapists in community mental health settings spend an extra hour a week on documentation because they don't have a structured template. That adds up to four hours a month, which is real time taken away from actual clinical work or from not working late.
Get the Full Details
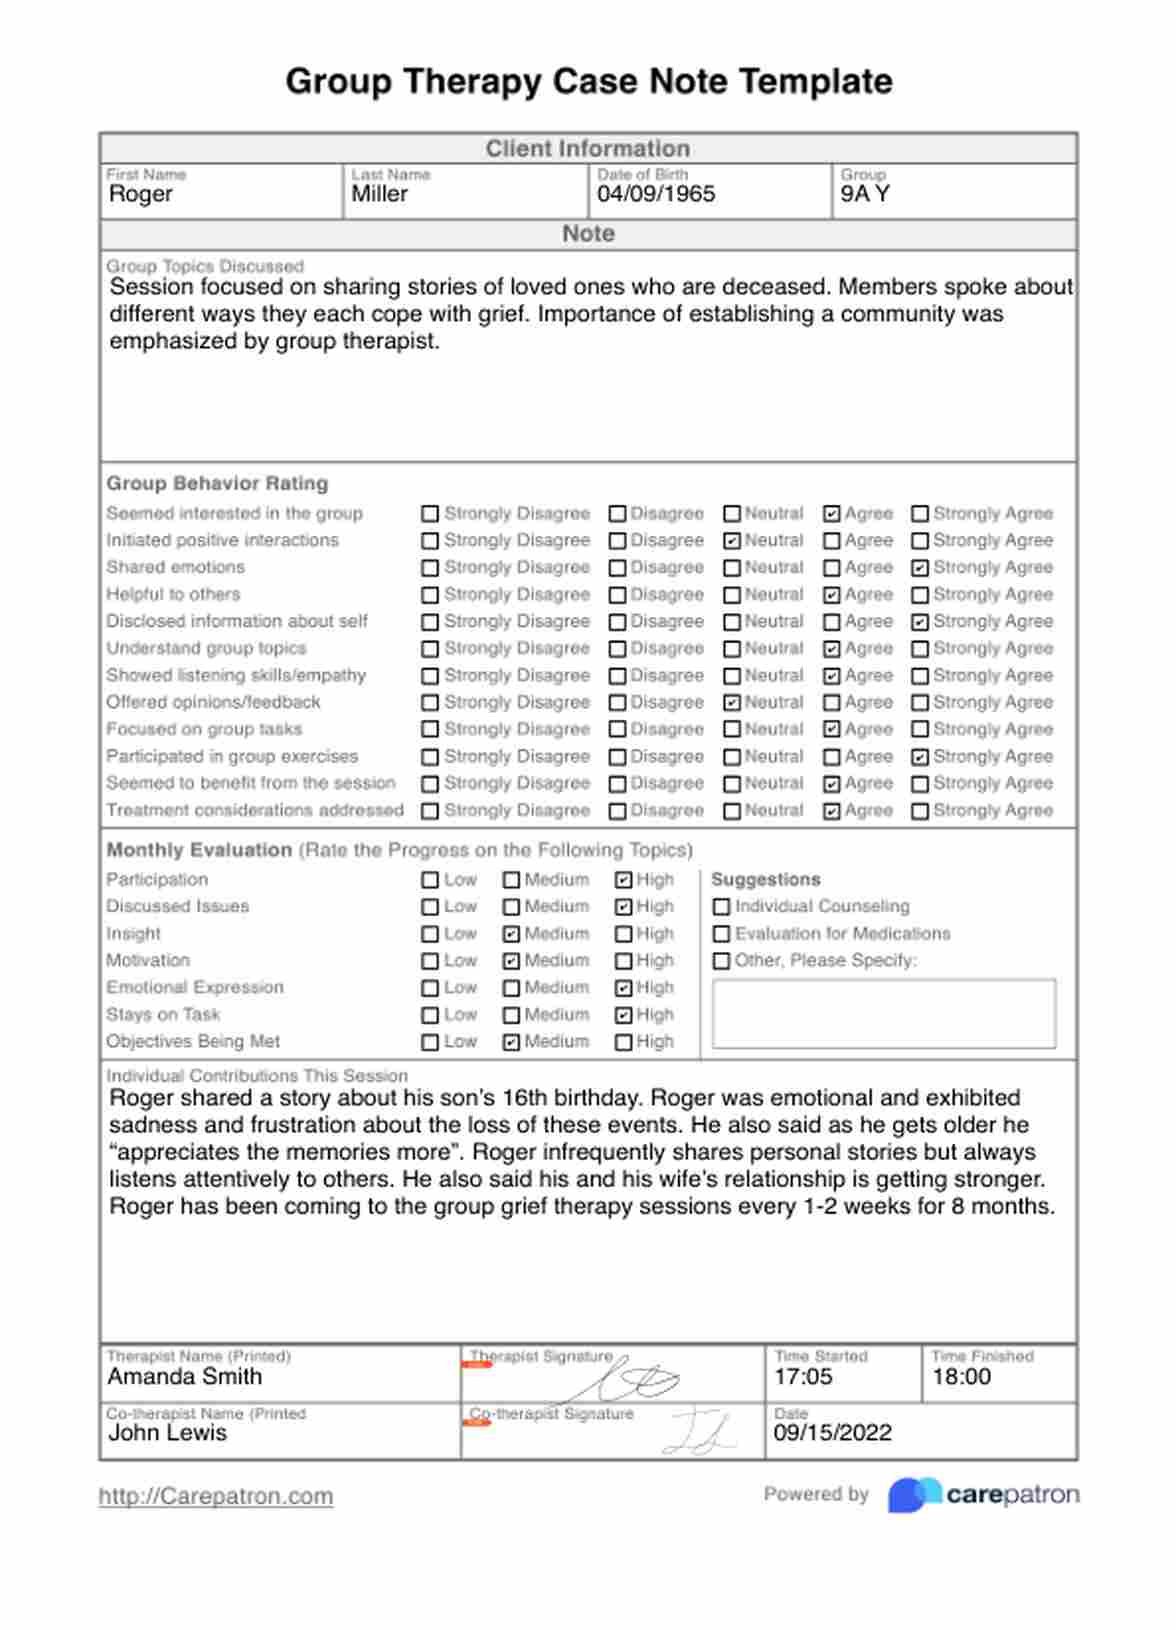
Common pitfall number two: conflating group facilitation notes with individual clinical notes. These are separate documents. The group note covers what happened in the group session. It is not a substitute for individual treatment planning. Some therapists try to merge the two to save time, and that creates problems for both continuity of care and billing compliance. Keep them separate. Reference the group note in the individual plan if needed, but don't duplicate content. If you're new to this and want something to start with today, most EHR platforms have group note templates built in. Epic, AthenaHealth, and SimplePractice all have variations. They won't be perfect for your population, but they give you a starting structure that you can trim down. The ones I recommend avoiding are the overly generic templates that ask you to check boxes for everything from attendance to homeword completion to crisis intervention. You end up filling them out without actually writing anything meaningful. Less checkboxes, more space for narrative. That's the opposite of what template vendors think you want, but it's what actually works in practice. There's also a documentation standard called DAP notes—Data, Assessment, Plan—that some groups prefer over SOAP. The data section combines subjective and objective into one stream. It's faster to write and works fine if your agency allows it. I switched to DAP for routine weekly groups because I was losing time on the separation. I kept SOAP for intake groups and forensic populations where the distinction matters more for legal review. Pick one and stick with it. Switching back and forth just adds cognitive load.
Billing correlation is worth mentioning separately. Your note has to support the CPT code you bill. 90853 is group psychotherapy, 90857 is psychoanalysis of an adult on an individual basis, and 90846 is psychotherapy with an individual plus family therapy. Don't bill 90853 on a note that reads like an individual session. Reviewers catch that. The note should clearly describe group interaction, not one therapist and one patient having a conversation in a room with other people present. The system I described isn't elegant. It's just the one that survives scrutiny and doesn't make you stay until midnight to finish documentation. You'll get better at the shorthand as you go. After about six months, the participant shorthand becomes almost automatic. You're writing JS: deflected. LC: engaged with new coping skill. MG: nonverbal resistance throughout. In your head you already know what those shorthand notations mean because you were there. The expanded note the next day is just fleshing out what you already captured.