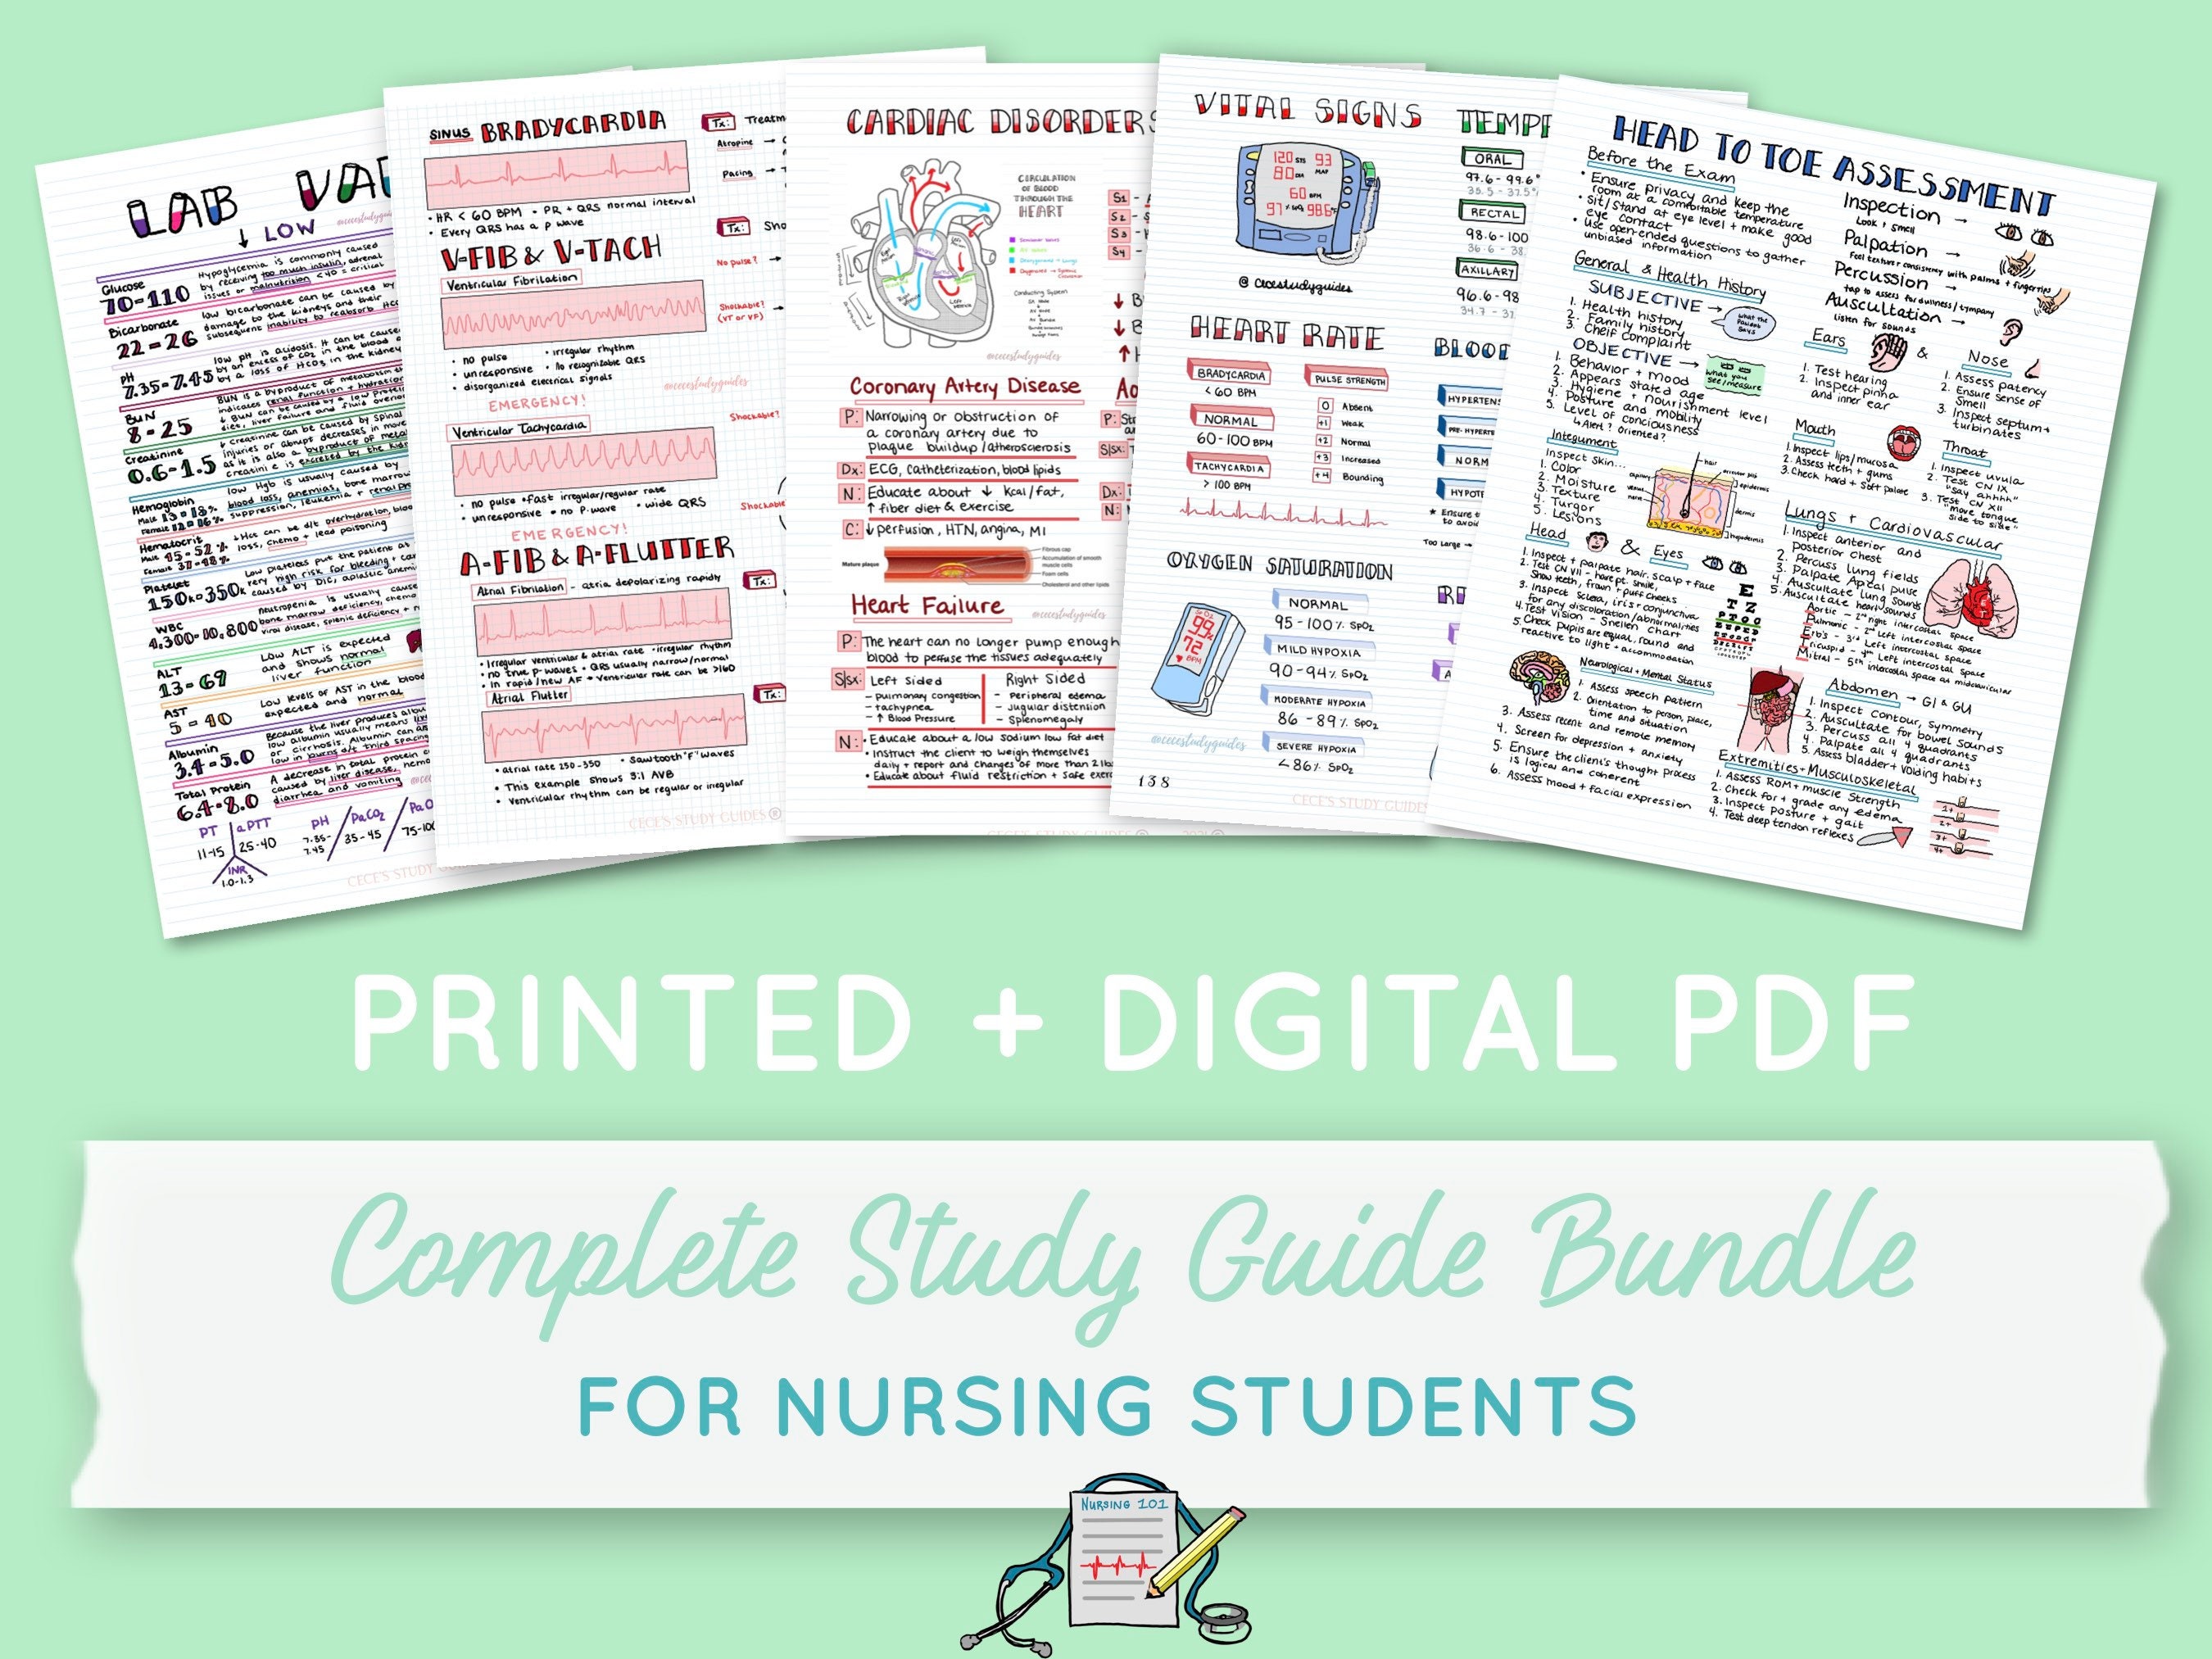
So you want to simplify nursing. Here is what actually works in practice.
Nursing isn't hard because the concepts are complicated. It's hard because there are too many steps happening at once and every step has to be perfect. A Guide For Nursing Easy is really just a mental framework for stripping away everything that isn't essential. I spent years doing med-surg before moving to ICU, and the biggest shift I made was learning when NOT to do something rather than what to add. The method is straightforward. Take any patient interaction and break it down into three buckets: clinically necessary, legally necessary, and nice to have. Most nursing anxiety comes from treating all three buckets the same. They aren't. The nice to have bucket is where you lose an hour of your shift every day and feel like you did nothing important. I started writing down my baseline checklist for every admission. For a standard post-op patient, it looked like this. Vital signs within the protocol window. Incision check. Pain assessment using a standardized scale. IV site inspection. Output tracking. That is it. Everything else gets layered on only if the patient gives you a reason. The reason could be abnormal vitals, a complaint, or a change in condition. Not the passage of time. Time alone doesn't justify extra interventions.
Here is the part nobody tells you. Documentation takes more time than the actual care for most routine patients. I used to spend twenty minutes charting for ten minutes of hands-on work. The fix was to document as I went instead of saving it all for the end of the shift. You walk into a room, you assess, you do the thing, you write one sentence in the flow sheet. Twenty minutes becomes four minutes. Your shift stops feeling like a race against paperwork at 7 PM.
A Real Problem I Faced
There was this one patient, elderly, multiple comorbidities, admitted for dehydration. Standard orders were q4h vitals, strict I&O, daily weights, basic lab work. Everything seemed normal on paper. But by day three, I noticed he was gaining weight without any fluid retention signs. His lungs were clear, extremities weren't edematous, but the scale said otherwise. This happened twice in one week on the same unit. The workaround wasn't fancy. I started weighing patients at the same time every morning, before breakfast, in hospital gown only, using the same calibrated scale. What I found was that the evening weight check on the mobile cart was consistently 1.2 to 1.8 kilograms higher than the morning weight, and the difference had nothing to do with fluid status. The mobile scale was slightly off calibration, and the carts were being pushed over threshold ramps at the end of the hall. It sounded ridiculous until I logged the data for two weeks and compared it to the bathroom scale in the room. Once I flagged it, the charge nurse pulled the mobile units for recalibration. We stopped having these phantom weight gain alerts completely.
Get the Full Details
Counter-Intuitive Things About Nursing Efficiency
The first thing is that thoroughness and efficiency are not the same thing. Being thorough means catching problems early. Being efficient means not doing things that don't catch problems. A nurse who checks blood sugar on every diabetic patient at 3 AM even when the last reading was normal at 10 PM is thorough but not efficient. A nurse who adjusts the schedule based on medication half-lives and historical patterns is both. The pattern recognition takes practice but it pays off fast. The second thing is that delegation is the skill that separates good nurses from burnt out nurses. You can do fifteen tasks yourself or you can coordinate the completion of fifty tasks. The difference is knowing what you are legally and clinically allowed to hand off. CNAs can do vitals, ADLs, intake and output tracking, ambulation assistance. LPNs can do certain medications and dressing changes depending on your state. RN scope items like assessments, teaching, and IV push medications stay with you. When I learned to delegate the first category without guilt, my caseloads became manageable again. Not everything needs your personal attention. Using a proper Guide For Nursing Easy approach also changes how you handle medication administration. The five rights are table stakes. The thing that catches people is the sixth right, right timing. Not all medications are created equal regarding when they matter. Insulin timing relative to meals, antibiotic timing relative to surgical prophylaxis windows, seizure medication timing relative to blood levels. Most errors happen because the timing is wrong even though the drug, dose, patient, route, and documentation are all correct.
Where This Approach Fails
Here is the honest part. Simplifying nursing doesn't work well in the first twelve hours of admission for complex patients. You need the full assessment, the full history, the full workup. Stripping things away too early on a new admission is how you miss something. The streamlined process kicks in after the baseline is established. If you try to run this approach on a fresh admit with unknown variables, you will miss details that would have shown up during a thorough initial assessment. It also fails in units with extremely high turnover or short-stay situations. Emergency department nursing, observation units, same-day surgery. The patients are in and out fast. There is no baseline to establish because there is no time. In those environments, the structured checklists and pattern-based thinking take longer to apply than just doing the full assessment every time. You are better off sticking to the protocol templates those units provide rather than trying to build a simplified framework on the fly. Another limitation is staffing. If you are constantly short-staffed with one nurse covering the floor alone, you do not have the luxury of delegation or pattern-based skipping. You do everything manually because there is no one else to catch what you missed. The Guide For Nursing Easy approach assumes you have a functional team. When you do not, the shortcuts become dangerous because the safety net is gone.
Practical Steps to Start Using This Today
Pick one patient type and map out their ideal care sequence. Post-op hysterectomy, CHF exacerbation, pneumonia. Write down every intervention that happens in a twelve hour shift and mark which ones are triggered by actual findings versus routine habit. You will be surprised how many items are habit. Then cut the habit items and replace them with conditional triggers. If heart rate stays between 60 and 90, skip the repeat cardiac assessment at the two hour mark. If lung sounds are clear, do not do a full respiratory exam at every pass, just check rate and effort. Use the IBAD form consistently. IBAD stands for Intervention, Baseline, Assessment, Documentation. It is an old framework but it keeps you honest about why you are doing something. If you cannot fill in the baseline and assessment parts, the intervention might not be necessary. I used this to catch myself ordering unnecessary vital sign checks on stable patients. It cut my documentation time by roughly thirty percent over a month because I was writing about actual findings instead of routine checkboxes. Build a personal reference system for common scenarios. Not a textbook, not a protocol binder, just a one-page summary for the five most common conditions on your unit. What to assess, what to monitor, what to escalate. Having this in your head or on your badge reduces decision fatigue. You stop second guessing whether a certain finding warrants action because you already decided that in advance. The mental load drops significantly after a few weeks of use.
Tools That Help Without Adding Complexity
A simple timer or alarm system for medication administration keeps you honest about timing without requiring extra documentation steps. Set it and forget it. Electronic health records have built-in reminders but they also create alert fatigue. A standalone timer for critical timing medications like insulin or antibiotics gives you the precision without the software noise. Your phone works fine for this. Flow sheets are still the best friend of a busy nurse. Instead of writing narratives for routine observations, use flow sheets with pre-printed ranges and checkboxes. Normal goes in the box. Abnormal gets a narrative line. This format reduces charting time by about forty percent for stable patients and makes it easier for the next nurse to scan the information quickly. Most hospitals already have these forms. Start using them religiously and stop writing paragraphs for normal findings. Teach patients the conditional nature of their own care early. If a patient knows that pain medication is given at scheduled intervals and PRN for breaks above a certain threshold, they stop asking for it every two hours. If they know that vital signs are checked every four hours unless something is abnormal, they stop wondering why you are not in the room constantly. Setting expectations upfront removes a huge amount of unnecessary interaction from your shift. The interaction is not bad, it is just inefficient when it is driven by anxiety rather than clinical need.
Most of this comes down to one principle. Nursing is not about doing more. It is about doing the right things at the right time. A Guide For Nursing Easy is just the discipline to stop confusing motion with progress. The patients who benefit most from this approach are the stable ones who would otherwise get buried under routine checking that serves no purpose. The unstable ones still get your full attention when they need it. The trick is learning to tell the difference quickly.