Operating Room Roles Explained From Someone Who Has Seen Everything Go Wrong
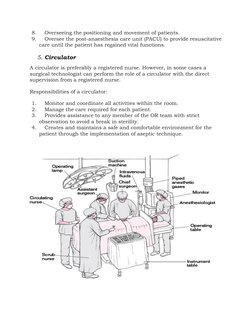
The operating room runs on a hierarchy that is not always written down but everyone follows it instinctively once they have been there long enough. If you are walking into your first rotation or trying to train new staff, understanding who does what actually matters more than memorizing job titles. I spent years watching situations collapse because someone assumed another person had their back on a critical step, and that someone else assumed the same thing. The scrub role is the most commonly misunderstood position. People think it is just about handing instruments. It is not. The scrub person needs to anticipate what the surgeon wants before the hand is even raised. I had a case once where the attending wanted a needle driver for a deep pelvic suture, and the scrub tech had placed it handle-first on the back table instead of tip-first. The surgeon reached for it, grabbed the handle, and had to reposition it mid-suture while bleeding was actively happening. That one misplacement cost us roughly forty-five seconds that added up to visible blood loss. Never assume placing the instrument correctly is someone else's responsibility. Your job is to know which end the surgeon needs. The circulating nurse operates outside the sterile field and handles everything that requires leaving the immediate surgical area. This includes pulling additional supplies, documenting times, communicating with families, and managing unexpected equipment failures. One time during a lengthy orthopedic case, the C-arm malfunctioned mid-procedure. The circulating nurse had to coordinate with biomedical engineering, find a backup unit from a nearby suite, and document the downtime without disrupting the sterile team. That level of situational awareness cannot be taught from a pamphlet. You learn it by being the person who has to solve the problem while everyone else is focused on the patient.
The anesthesiologist or nurse anesthetist controls the airway and hemodynamics. This role gets reduced to someone who just watches monitors, which is dangerously incorrect. They manage fluids, medications, blood products, and respond to sudden physiological changes faster than anyone else in the room. During a laparoscopic case I observed, the patient's oxygen saturation dropped to eighty-eight percent within thirty seconds of insufflation. The anesthesia provider recognized a tension pneumothorax pattern immediately and adjusted ventilation pressures while signaling the surgical team to release insufflation. The surgeon was still mid-dissection and had no idea what was happening systemically until notified. That disconnect between the surgical field and systemic physiology is where most adverse events originate, and the anesthesia team is your early warning system. The surgeon obviously directs the procedure, but the attending's verbal instructions are only as effective as the team's ability to interpret them under pressure. I have seen residents receive perfectly clear verbal commands and execute them incorrectly because the room was loud, the monitor alarms were blaring, and multiple people were talking simultaneously. Standardizing your communication protocol early in a case prevents this. Repeat back critical instructions. Use closed-loop communication. It takes three extra seconds and prevents approximately ninety percent of wrong-site or wrong-instrument errors. Surgical technologists and first assists share overlapping responsibilities that cause confusion on busy schedules. The tech manages the sterile field setup, instrument counts, and supply organization. The first assist, usually another surgeon or a senior resident, helps with retraction, suturing, and tissue handling. The distinction matters during count protocols. If a sponge count is wrong, the tech owns the responsibility for initiating the search. The first assist does not share that liability, and confusing these roles during a panic situation leads to duplicated efforts and missed items.
Perfusionists operate the heart-lung machine during cardiopulmonary bypass cases. This is a specialized role that does not exist in most general surgery environments, but when it is present, the perfusionist has equal authority to the surgeon regarding patient safety during bypass. I watched a scenario where the surgeon wanted to proceed with a clamp release despite the perfusionist indicating inadequate anticoagulation levels. The perfusionist refused to proceed, and the case was paused for twenty minutes until the coagulation profile normalized. The surgeon was frustrated but later acknowledged that the intervention prevented a catastrophic embolic event. Authority in the OR is not solely determined by who is holding the scalpel. Radiologic technologists and imaging specialists manage fluoroscopy, intraoperative X-rays, and CT guidance when needed. They control radiation exposure settings and position the equipment. A common mistake I see repeatedly is the surgical team adjusting collimation or field-of-view without consulting the rad tech, which can result in unnecessary radiation exposure to both the patient and staff. The tech should always set the exposure parameters. The surgeon should never touch those controls.
Get the Full Details

Practical Considerations When Learning These Roles
Most hospitals provide orientation materials for each position, but those documents are generic and outdated within two years. The real learning happens during live cases where protocols adapt to the specific surgeon's preferences and the hospital's unique equipment inventory. I recommend spending your first three months observing before assuming any role independently. Watch how experienced teams communicate under stress. Note which instruments are requested versus which are actually used. Pay attention to how often counts are performed and whether they are thorough or rushed. Team dynamics vary significantly between institutions. A university teaching hospital operates differently from a community urgent surgery center. The volume of cases, the complexity of procedures, and the availability of backup personnel all influence role flexibility. In high-volume centers, scrub techs often cross-train to assist with positioning and preparation because there is no time for strict role separation. In academic centers, the hierarchy is more rigid and junior residents may perform tasks that would be outside their scope elsewhere. Understanding your specific environment's expectations matters more than following a universal template. Documentation requirements differ by role but are universally underemphasized during training. The circulating nurse's time-out documentation, the tech's instrument count sheets, the anesthesia provider's medication logs, and the surgeon's operative notes all serve as legal records and quality metrics. I have reviewed cases where a missing signature on a sponge count sheet created liability exposure that lasted for eighteen months. Proper documentation is not bureaucratic overhead. It is the primary evidence that protocols were followed correctly.
The staffing shortage in perioperative roles is real and affects how these positions function daily. Many facilities operate with one less scrub tech than ideally required, which means circulating nurses absorb responsibilities that traditionally belonged to separate positions. This compression increases error rates and burnout. If you are entering this field, understand that role boundaries are fluid under staffing pressure, and adaptability matters as much as technical competence. There is no ideal state to return to. The current reality requires every team member to be competent beyond their primary designation. Certification requirements vary by state and facility. The CNOR credential for operating room nurses, the CST credential for surgical technologists, and the CRNA certification for anesthesia providers are industry standards but not universal mandates. Some hospitals hire based on experience alone without requiring formal credentials. This creates inconsistency in baseline knowledge levels across departments. If you are responsible for hiring or training, verify that each team member has demonstrated proficiency in their specific role regardless of credential status. Equipment compatibility issues represent another practical challenge that role descriptions never address. A new surgeon may arrive with preference cards calibrated to equipment from a previous institution, and the OR staff must adapt existing inventory to accommodate unfamiliar instruments. I encountered a situation where a visiting cardiovascular surgeon brought his own clamp set that was incompatible with the hospital's standard sterilization containers. The case was delayed fifty-two minutes while biomedical engineering fabricated adapters. Having a backup protocol for equipment incompatibility saves significant time and reduces friction between visiting and permanent staff.
Emergency scenarios expose role weaknesses most clearly. During a rapid sequence intubation gone wrong, the anesthesia provider needs the circulating nurse to retrieve a difficult airway cart without disrupting the scrub team's focus. The scrub tech needs to maintain sterility while passing emergency medications. The surgeon needs to provide airway access if conventional methods fail. Each role has a defined contribution, but the actual execution requires real-time coordination that no manual specifies precisely. Training through simulation helps, but nothing replicates the cognitive load of a real crisis better than experiencing it once. The hierarchy in the OR is not democratic. Decisions flow from the surgeon and anesthesia provider downward, but input from all team members is essential for safety. This structure creates an environment where junior staff may hesitate to speak up about concerns. I have witnessed cases where a second-year resident noticed an abnormal lab value that the attending had overlooked but remained silent because challenging the attending felt inappropriate. The attending proceeded with surgery, and the patient developed complications that required transfer to the ICU. Speaking up is not disrespectful. It is a professional obligation that supersede hierarchy in safety-critical situations. Role rotation between positions occurs occasionally, particularly in smaller facilities or during emergency surges. A circulating nurse may be asked to scrub in if staffing is critically low. A surgical tech may need to assist with patient positioning outside their normal scope. This flexibility is necessary but introduces risk because competency in one role does not guarantee readiness for another. Cross-training programs that include supervised practice in alternate roles reduce this risk but require dedicated time and resources that many facilities cannot allocate.

The physical demands of OR roles are underestimated. Scrub techs stand for eight to twelve hour cases with minimal movement breaks. Circulating nurses walk miles during a single shift while managing documentation and communication. Anesthesia providers maintain fixed positions near the head of the table for extended periods, leading to musculoskeletal injuries at rates comparable to surgeons. Facility design, ergonomic equipment, and scheduled micro-breaks can mitigate some of this strain, but the fundamental physical toll is inherent to the work. Communication breakdowns account for a significant percentage of adverse events in the perioperative environment. The Joint Commission identifies communication as a leading root cause of sentinel events. Simple interventions like standardized handoff protocols, read-back verification for medication orders, and mandatory time-outs before incision have been shown to reduce errors by approximately thirty to forty percent in published studies. These are not controversial recommendations. They are routinely ignored in practice because they require disciplined execution during time-sensitive situations. Technology integration continues to reshape these roles. Robotic surgical systems require dedicated console surgeons, scrub techs trained in robotic instrumentation, and circulating nurses who manage docking procedures and troubleshoot system errors. Electronic health record systems consolidate documentation but create new risks around alert fatigue and copy-paste documentation errors. Virtual reality training platforms are emerging for procedural simulation but have not yet replaced hands-on experience for role competency validation.
The financial aspect of staffing roles often influences operational decisions beyond clinical considerations. Utilizing advanced practice providers in supporting roles can reduce costs but requires clear scope definition and supervision protocols. Outsourcing certain functions to agency staff addresses immediate shortages but introduces variability in training and familiarity with institutional protocols. Neither approach is inherently superior. Both require active management to maintain safety standards. If you are reading this as someone preparing to enter the operating room environment, the single most useful advice I can offer is to observe before you act. Watch how experienced professionals handle the gaps between written protocol and actual practice. The difference between those two worlds is where mistakes happen, and learning to navigate that gap is the actual education no textbook provides.