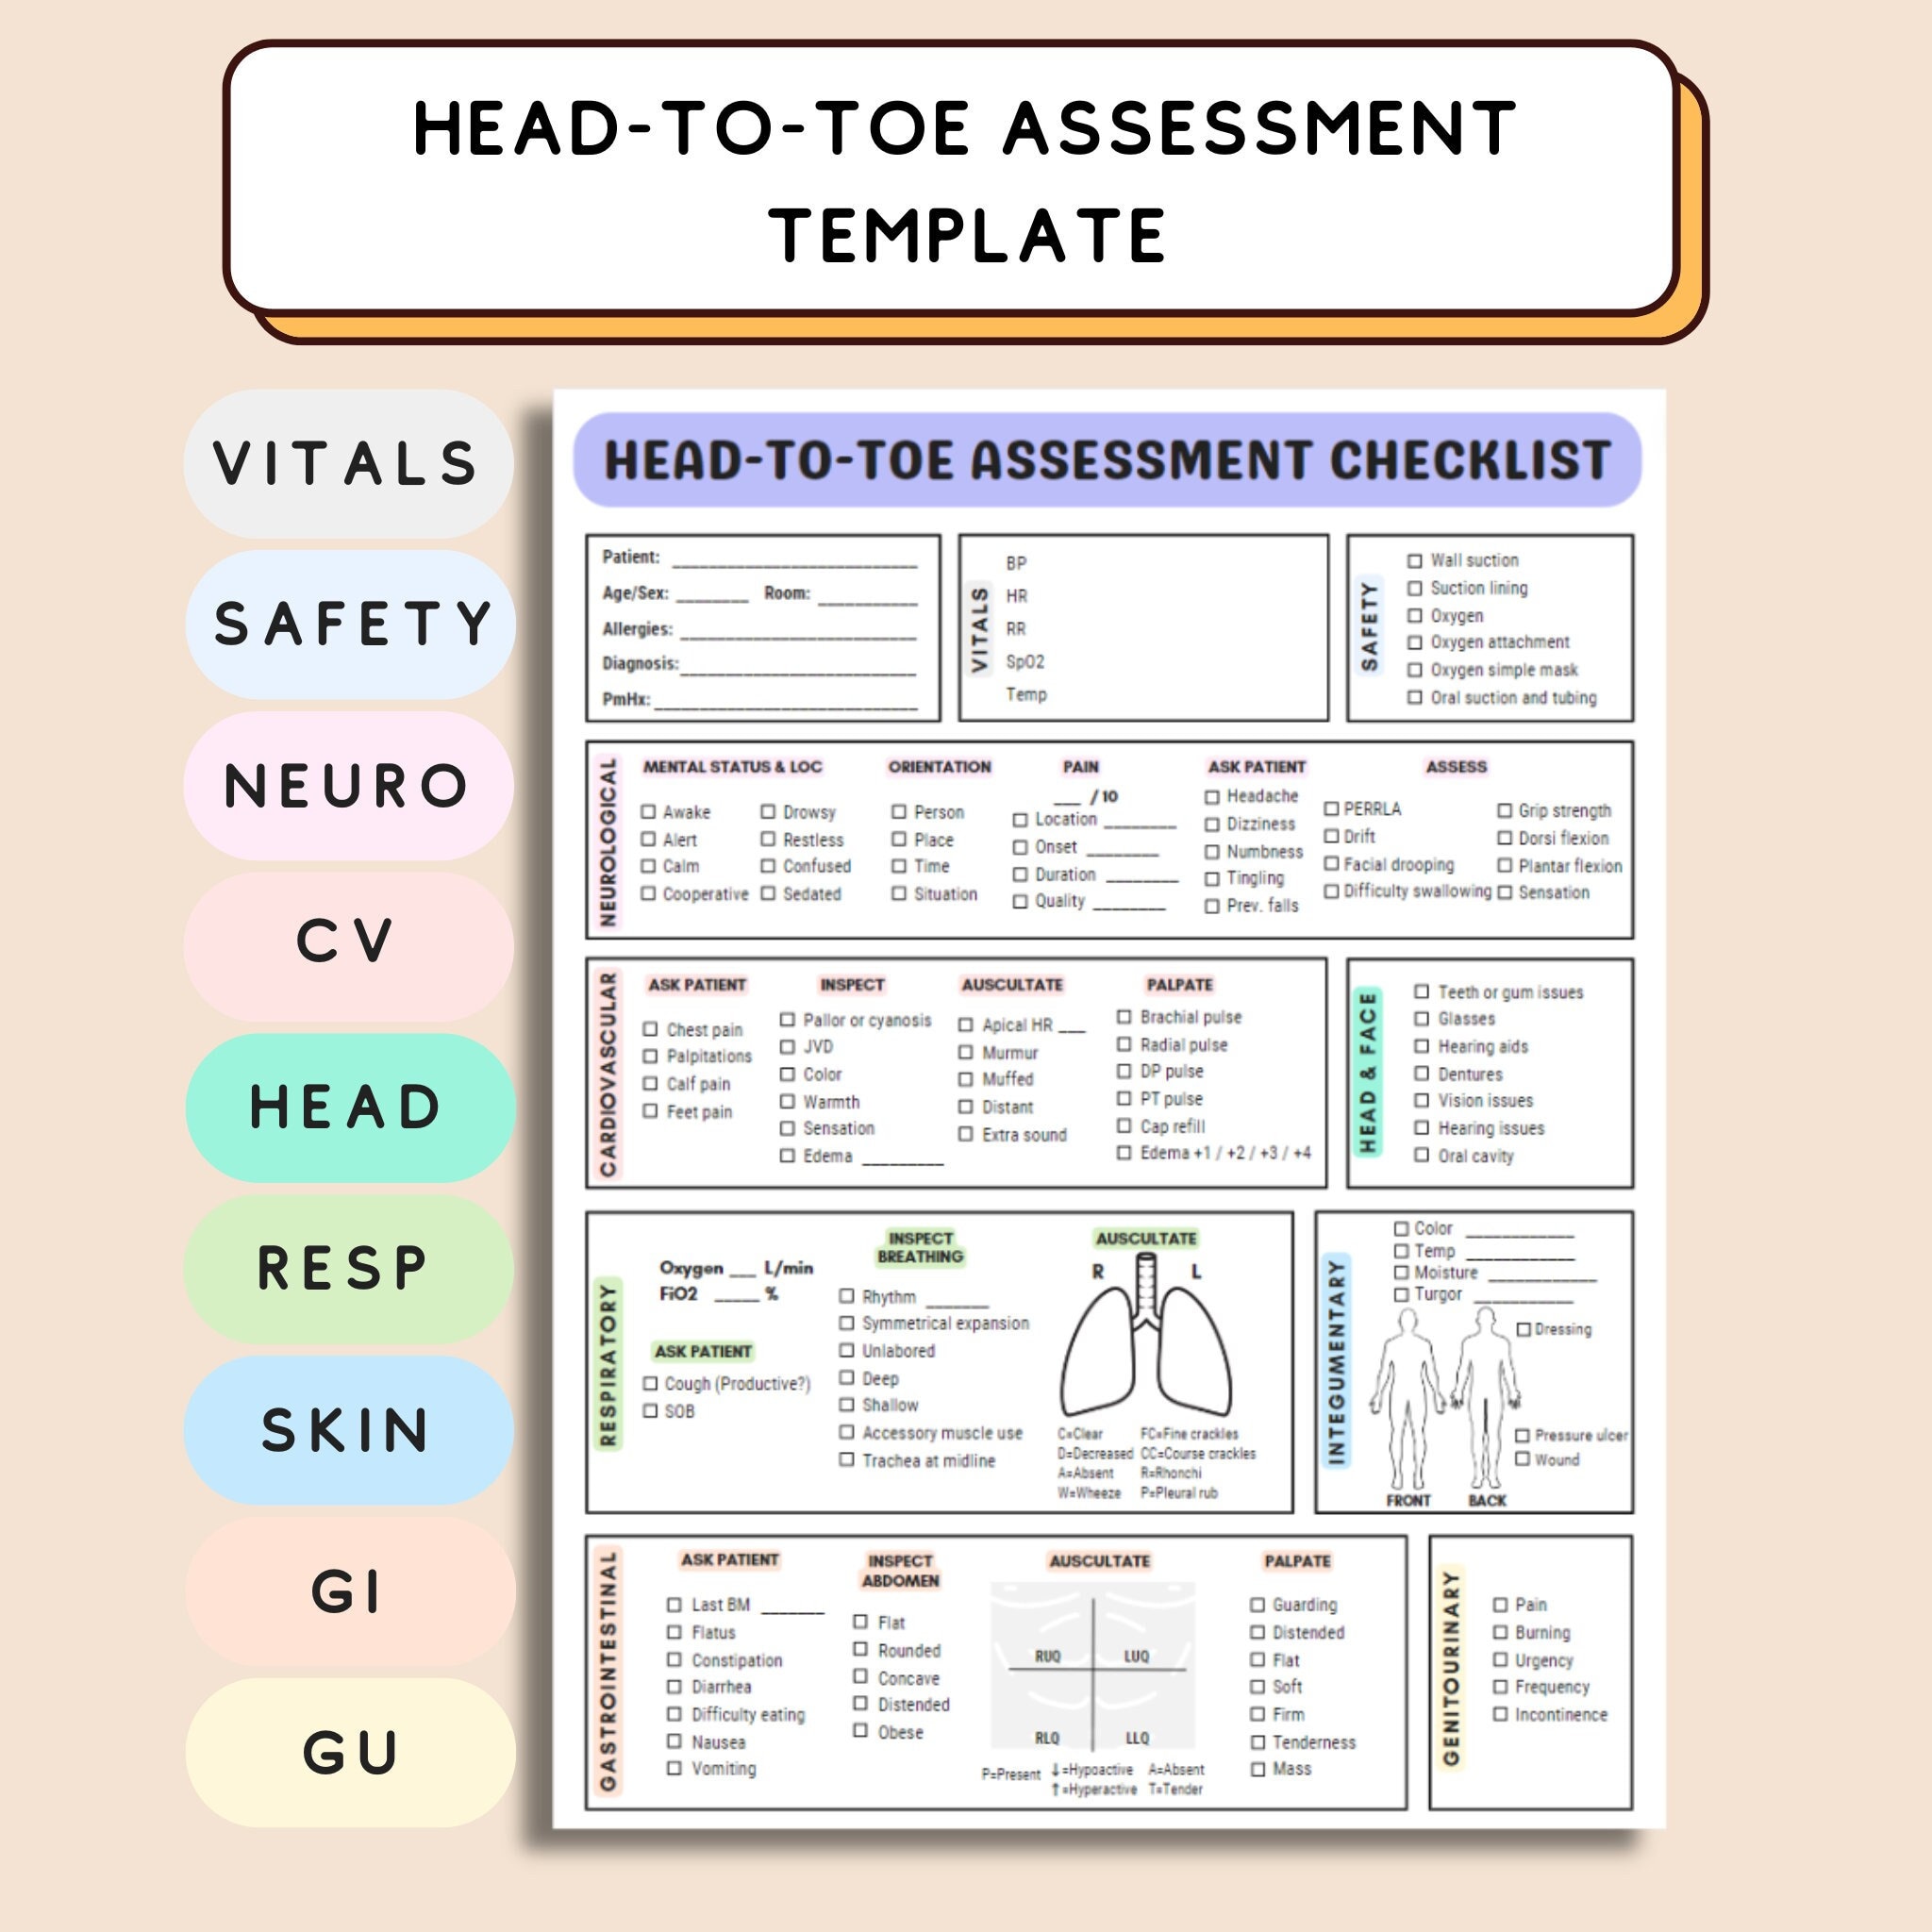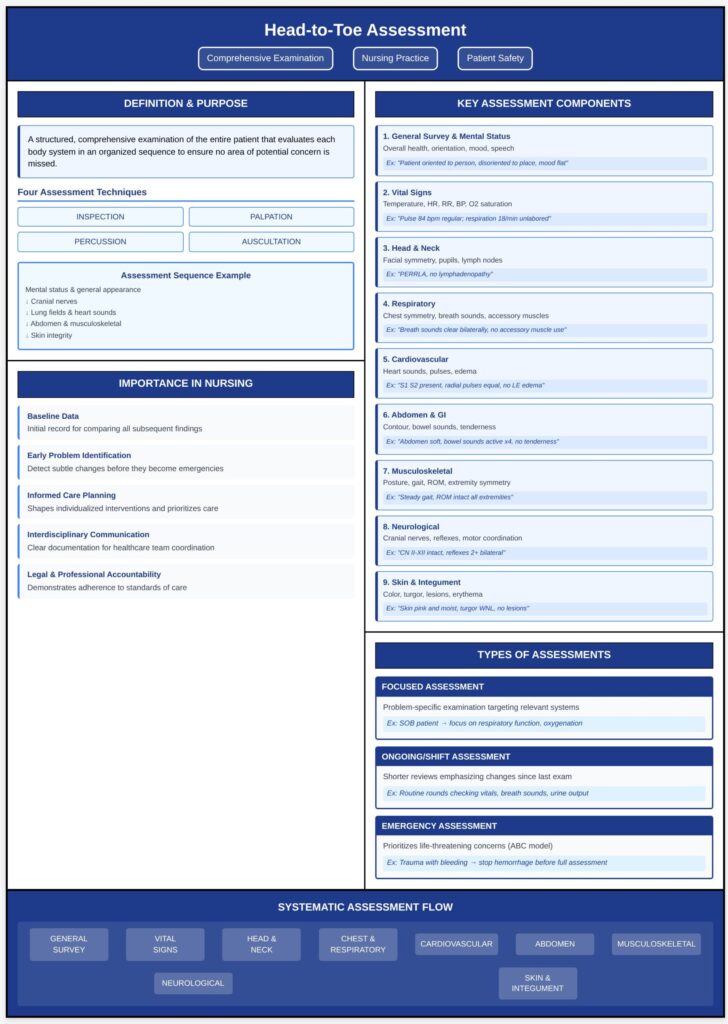
What Head To Toe Documentation Actually Looks Like In Practice
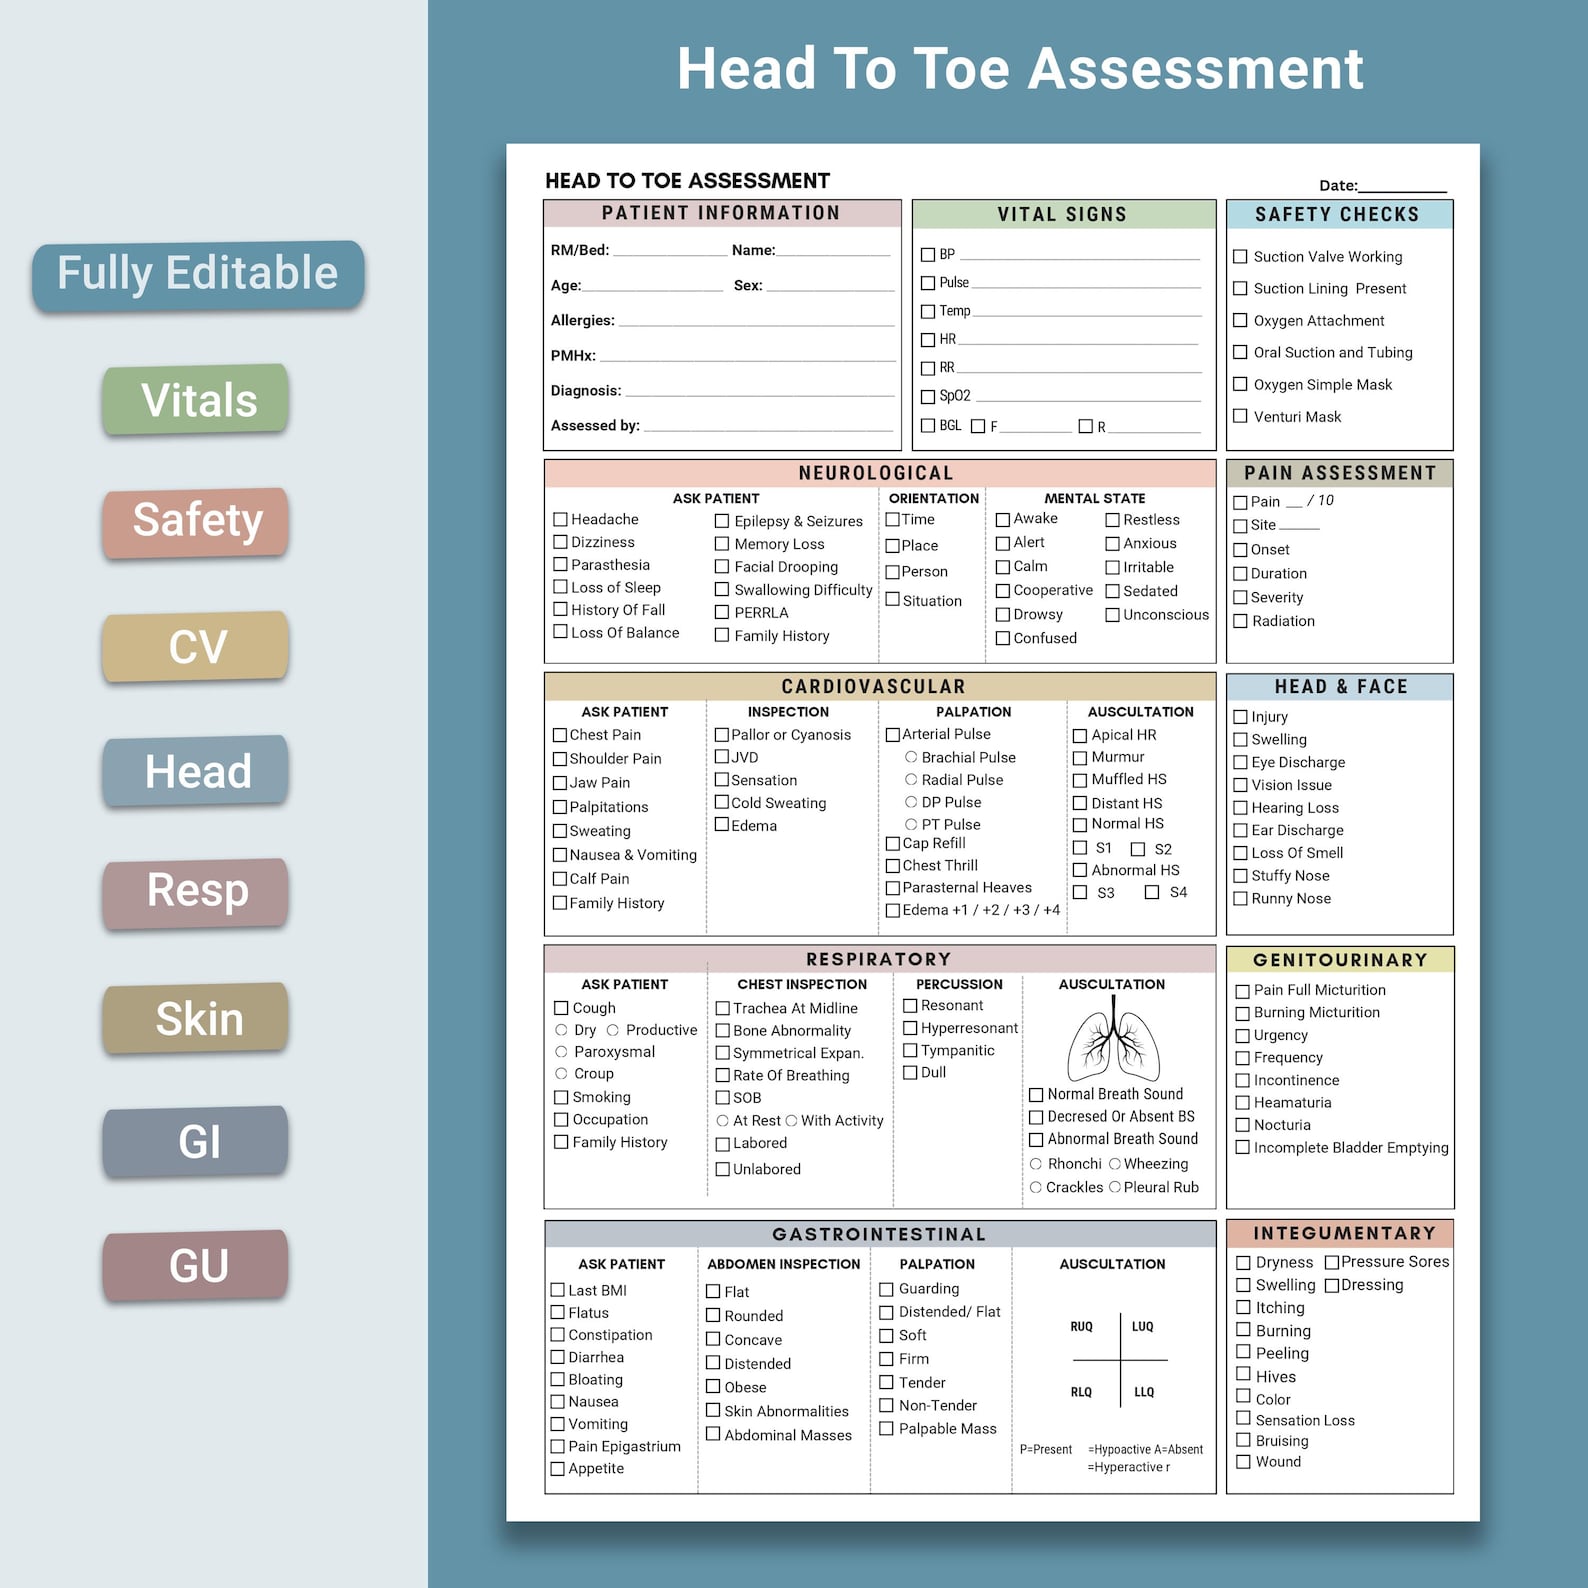
Head to toe documentation is a systematic method of recording a full patient assessment, moving from the top of the head down to the feet. It is standard practice in nursing, emergency medicine, and primary care settings. The purpose is straightforward: ensure nothing gets missed during an assessment, and create a legal record that shows the clinician's thought process. The structure is linear. You start with general appearance and vital signs, then move through each body region methodically. There is no magic to it. The real challenge is doing it thoroughly without turning it into a form-filling exercise that takes twenty minutes per patient.
Guide Head To Toe Documentation Sample
Here is a practical example of what a completed sample looks like for a general medical admission: General Appearance: Alert and oriented x4. No acute distress observed. Afebrile. Vital signs: BP 128/82, HR 76, RR 16, SpO2 98% on room air, Temp 37.1°C. Head: Normocephalic. Pupils equal, round, reactive to light and accommodation. Extraocular movements intact. Oral mucosa moist, no lesions. Teeth in good condition.
Neck: Supple. No lymphadenopathy. Trachea midline. No JVD. Thyroid non-enlarged, no nodules palpable. Lungs: Clear to auscultation bilaterally. No wheezes, rales, or rhonchi. Good air movement. Respiratory effort unlabored. Cardiovascular: Regular rate and rhythm. S1 and S2 heard clearly. No murmurs, gallops, or rubs. Peripheral pulses 2+ and symmetric in all four extremities. Capillary refill under 2 seconds.
Get the Full Details
Abdomen: Soft, non-tender, non-distended. Bowel sounds present in all four quadrants. No organomegaly. No masses palpable. Extremities: No edema. Strength 5/5 in all groups. No cyanosis or clubbing. Skin warm and dry. Skin: Intact. Good turgor. No rashes, lesions, or pressure injuries. Pigmentation normal.
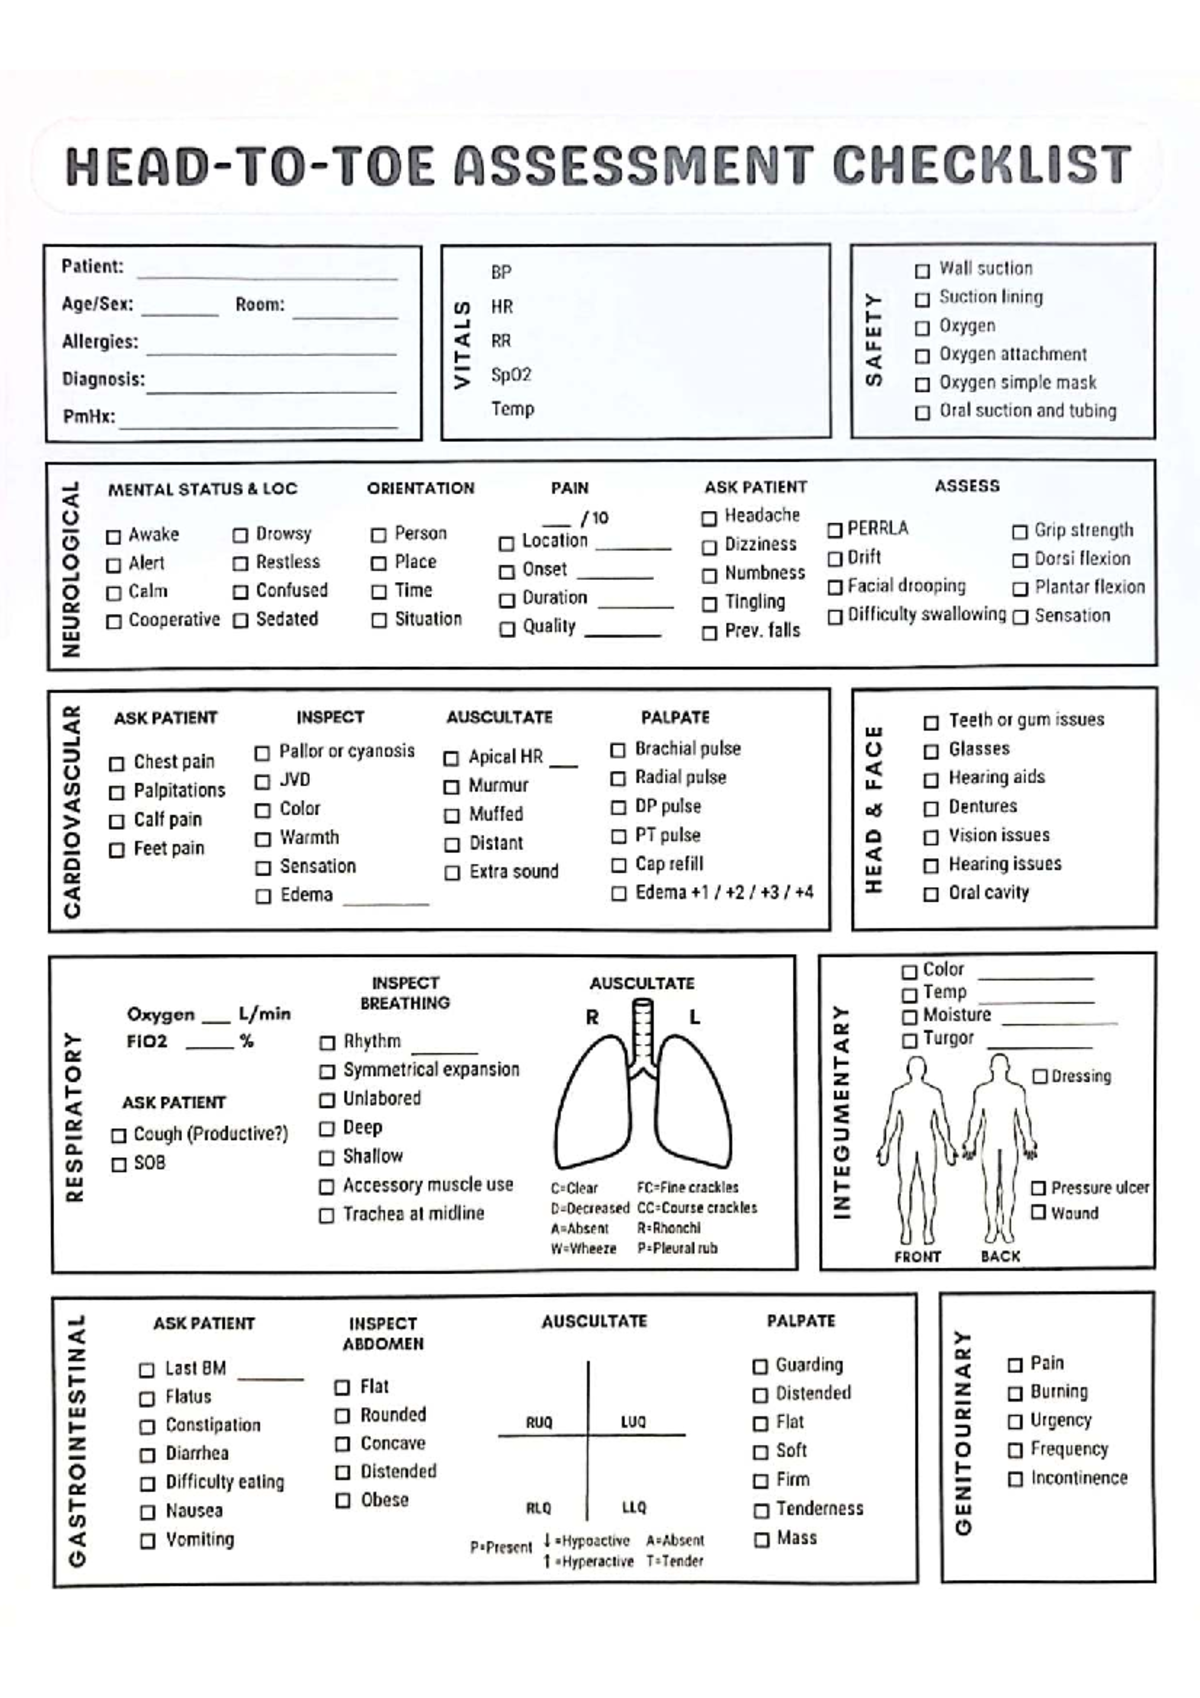
Neurological: CN II-XII grossly intact. Motor strength symmetric. Sensation intact to light touch. Gait steady. Reflexes 2+ and bilateral. I spent three years in an ER where we transitioned from paper to electronic health records, and head to toe documentation became one of the most contentious issues on the floor. The problem wasn't the format itself. It was the way the EHR vendors designed the templates. They created collapsible sections that nurses would collapse, then click through without actually documenting anything meaningful inside. I saw entire assessments reduced to checkboxes with generic phrases like "normal exam" repeated across multiple systems. That is not defensible in court, and it is not useful for clinical decision-making. My workaround was simple but required discipline. I stopped using the checkbox macros for anything beyond routine screening patients. For any patient with a complaint, I wrote out the findings in narrative form within the assessment section, even if the template offered pre-built options. It took longer upfront, maybe an extra four or five minutes, but it actually captured what was happening. More importantly, when a patient deteriorated later, that narrative gave the next clinician something concrete to compare against. The checkbox version was useless for that purpose.
There are nuances that most beginner guides miss. One is the order of systems. The standard head-to-toe sequence is not arbitrary. Starting with the head and moving down lets you catch abnormal findings early and adjust your approach. If you find significant abdominal tenderness near the top of your assessment, proceeding methodically prevents you from missing it later due to fatigue or rushing. Another nuance is documenting negatives. Writing "no JVD" is clinically meaningful when the patient has a history of heart failure. Omitting it creates a gap that implies you did not check, not that you checked and found nothing. Here is a counter-intuitive point: over-documenting can be as problematic as under-documenting. I worked a case where a patient complained of bilateral leg pain. The head to toe documentation was exhaustive, but the writer included irrelevant findings from every system rather than focusing on the musculoskeletal and vascular assessment of the lower extremities. When the case went to review, the reviewer could not quickly locate the relevant data. The document was technically thorough but functionally opaque. Specificity matters more than comprehensiveness. Document the systems you are assessing for the presenting complaint in detail. Briefly note the rest as within normal limits unless there is a reason to go deeper. Another pitfall is template drift. Over time, clinicians develop their own shorthand versions of head to toe documentation that become personalized and inconsistent. One nurse might document "PERRLA" and consider that sufficient for eye assessment. Another might write out "pupils equal, round, reactive to light and accommodation" because their facility training emphasized it. Both are acceptable, but mixing approaches across a care team creates confusion during handoffs. Standardize your terminology at the unit level. It does not need to be rigid, but having a shared language reduces errors during shift changes.
The legal dimension deserves mention. Head to toe documentation serves as evidence of the standard of care in malpractice proceedings. A complete, contemporaneous record that shows systematic assessment protects both the patient and the clinician. Gaps or contradictions in the documentation can be interpreted as neglect regardless of what actually happened. I had a colleague whose documentation showed normal lung sounds on admission, but the patient was later found to have developed pneumonia. The chart review revealed that the initial assessment had been done while the patient was in a supine position with poor inspiratory effort, yet the documentation did not note this limitation. The implication was that the examiner missed the early signs. The reality was more complicated, but the documentation told a simpler and less favorable story. For acute care settings, the frequency of head to toe reassessment depends on acuity. Stable outpatients may only need it at intake. ICU patients require continuous monitoring with periodic formal assessments. Post-operative patients typically get head to toe checks every four to eight hours depending on the surgical type and recovery status. Documenting the timing is important. Note the time of each assessment so future reviewers can track changes over the clinical course. One edge case that caught me off guard was documenting cognitive status as part of the neurological section. I once assessed a patient who was clearly confused but wrote "alert and oriented" because they opened their eyes and made vocalizations when prompted. A later reviewer flagged this as inaccurate, and the discrepancy mattered when the patient's family questioned the level of monitoring. The fix was to use standardized tools like the Glasgow Coma Scale or the Mini-Mental State Examination instead of free-text descriptions that leave room for interpretation. I started documenting orientation status with specific questions answered rather than blanket statements.
For wound care documentation, head to toe assessments need additional detail in the affected area. Wound location, dimensions, stage, exudate characteristics, surrounding tissue condition, and dressing type all require precise notation. Vague terms like "moderate drainage" should be replaced with specific descriptors such as "serosanguinous drainage, approximately 3cm diameter, moderate volume." I found that using a wound measurement kit and photographing the site with consent improved documentation accuracy significantly. The photos become part of the permanent record and help track healing progress visually. Electronic documentation systems have introduced new challenges. Auto-population of vital signs is convenient but can lead to copy-forward errors where outdated information persists in the current assessment. I have seen head to toe documentation pulled up from a previous shift still showing the prior day's lung sounds because a nurse clicked "copy from last assessment" without reviewing the content. Set your systems to flag auto-populated data so reviewers know it requires verification. This is a small step that prevents serious documentation integrity issues. If you are building a head to toe documentation workflow for a new team, start with a standardized template but leave room for narrative customization. Require completion of all sections before signing off. Implement peer review of random charts monthly to catch patterns of incomplete documentation. Train staff on the legal implications of gaps, not just the clinical ones. Documentation quality improves when people understand why it matters beyond compliance checklists.
The most common mistake I see across all settings is treating head to toe documentation as a bureaucratic obligation rather than a clinical reasoning tool. The assessment format exists because systematic examination reduces diagnostic errors. When you use it that way, the documentation writes itself with accurate, relevant information. When you treat it as a box to tick, you get boxes filled and patients underserved.