What Clinical Cultural Competence Actually Looks Like in Practice
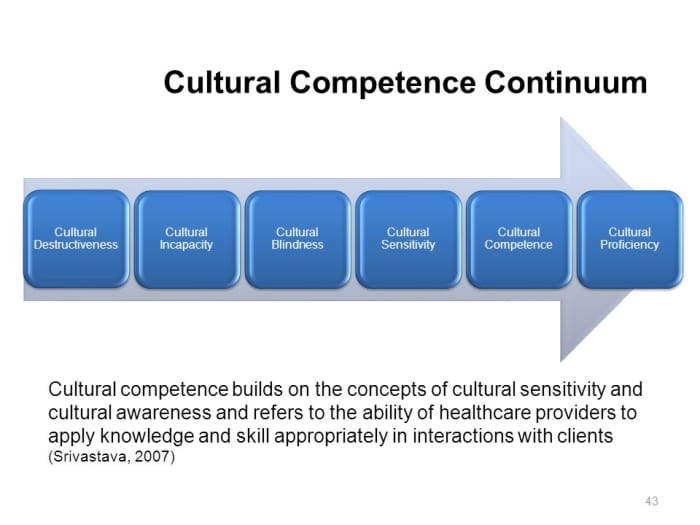
Clinical cultural competence is the ability of healthcare providers to deliver care that respects and responds to the cultural and linguistic needs of patients. It sounds straightforward on paper but in a busy clinic it falls apart quickly if you don't have a system for it. Most institutions treat it like a checkbox training module and expect outcomes to change. They don't. I spent years in outpatient mental health where we dealt with a patient population that was roughly 60% non-English speaking and came from at least a dozen different cultural backgrounds. The first time I realized the standard protocols weren't covering my ass was when a Vietnamese elderly patient kept nodding through my entire intake assessment. I assumed she understood everything I was saying. She didn't understand a word. She was too polite to correct me. That costs you credibility, accuracy, and sometimes safety.
Guide To Clinical Cultural Competence
Here's how I built something that actually works instead of relying on annual compliance videos. The framework has four moving parts and they need to function together or the whole thing becomes performative. Awareness comes first and it's the hardest part because it means recognizing your own biases without having a crisis about them. You can't do this work if you're defensive about every assumption you hold. I had a fellow provider who literally quit after a diversity workshop because he felt attacked. He wasn't wrong to feel uncomfortable but he was wrong to walk away from it. Awareness isn't about guilt. It's about mapping your blind spots so you stop mistaking your normal for everyone else's normal. Knowledge is the factual layer. You need to know the health disparities, communication styles, help-seeking behaviors, and stigma patterns relevant to the populations you serve. This isn't about memorizing cultures like trivia. It's about knowing that in some collectivist cultures, a family member will make medical decisions on behalf of the patient and the patient will not object. If you go in expecting individual autonomy as the default, you look rude and you lose trust instantly. I learned this the hard way with a Hmong family who brought their patriarch into the room for consent discussions about a treatment plan. My initial reaction was to request private conversation per standard protocol. The family looked at me like I was an idiot. I backed off, included the patriarch, and we got the cooperation we needed.
Skills is where most training programs fail. They teach you what to think about culture but not what to actually do when a cultural difference hits your workflow mid-appointment. The skill set includes things like using qualified interpreters instead of family members, recognizing when a patient's symptom presentation is culturally shaped, and knowing when to pause and ask instead of assuming. I once had a patient describe his anxiety as "heat in my chest" rather than using clinical terminology. A less observant provider would have written that down and moved on. I recognized it as a culturally idiomatic expression of panic symptoms and adjusted the assessment accordingly. The diagnosis was still panic disorder. The documentation was just more accurate. Encounters is the practice component. You get competent by doing it repeatedly in real situations, not by reading about it. Each patient interaction is a chance to calibrate. The key is debriefing yourself after difficult cross-cultural moments. What went wrong? What did I assume? What would I do differently? This takes maybe five minutes and it compounds over time. The biggest pitfall I see is treating cultural competence as a finite achievement. It's not. It's a continuous practice. You will make mistakes. The mistake isn't the problem. The problem is ignoring the mistake or getting defensive when someone points it out. I had a patient tell me once that I sounded dismissive when I asked about her dietary habits because I framed it like an interrogation. She was right. I had been rushing and my delivery was cold. I apologized, adjusted my approach, and never forgot that moment. That's the whole game right there.
Get the Full Details

Another counter-intuitive thing: assumed competence is worse than assumed ignorance. When you assume a patient is already culturally competent or already has the resources to navigate a complex healthcare system, you skip essential steps. I used to assume patients understood insurance codes and referral processes because I did. Many didn't. Building in extra explanation time — maybe ten minutes per visit — prevented a huge amount of follow-up confusion and missed appointments. There are limitations to this approach. It doesn't work well in high-volume settings where you have twelve-minute slots. The system itself becomes the barrier to cultural competence. No amount of training helps when you're being measured on throughput. In those environments, the best workaround is building structured checklists and incorporating interpreter services into the scheduling process upfront. Don't wait until the patient is already in the room to figure out language access. That's when it becomes a disaster. I also want to be blunt about where this breaks down completely. Cultural competence frameworks assume both parties want engagement. Some patients don't care about cultural considerations and want direct, clinical interaction. Forcing a cultural discussion on someone who just wants their prescription filled is just as insulting as ignoring culture entirely. Read the room. Not every patient wants the cultural competence treatment. Some want efficiency and clinical competence. Both are valid.
If you're building a practice or program around this, start with the interpreter infrastructure. It's the single highest-leverage investment you can make. Qualified medical interpreters reduce misdiagnosis rates, improve adherence, and decrease unnecessary referrals. The cost is real but the alternative — using family members or app-based translations for complex clinical conversations — is far more expensive in errors and repeat visits. I've seen a single miscommunication through a smartphone translation app lead to a patient taking medication incorrectly for three weeks before anyone caught it. The bottom line is that clinical cultural competence is less about being perfect and more about being systematically attentive. It requires ongoing self-correction, institutional support, and the humility to admit when you're wrong. Anything less is just window dressing.