What This Theory Actually Is
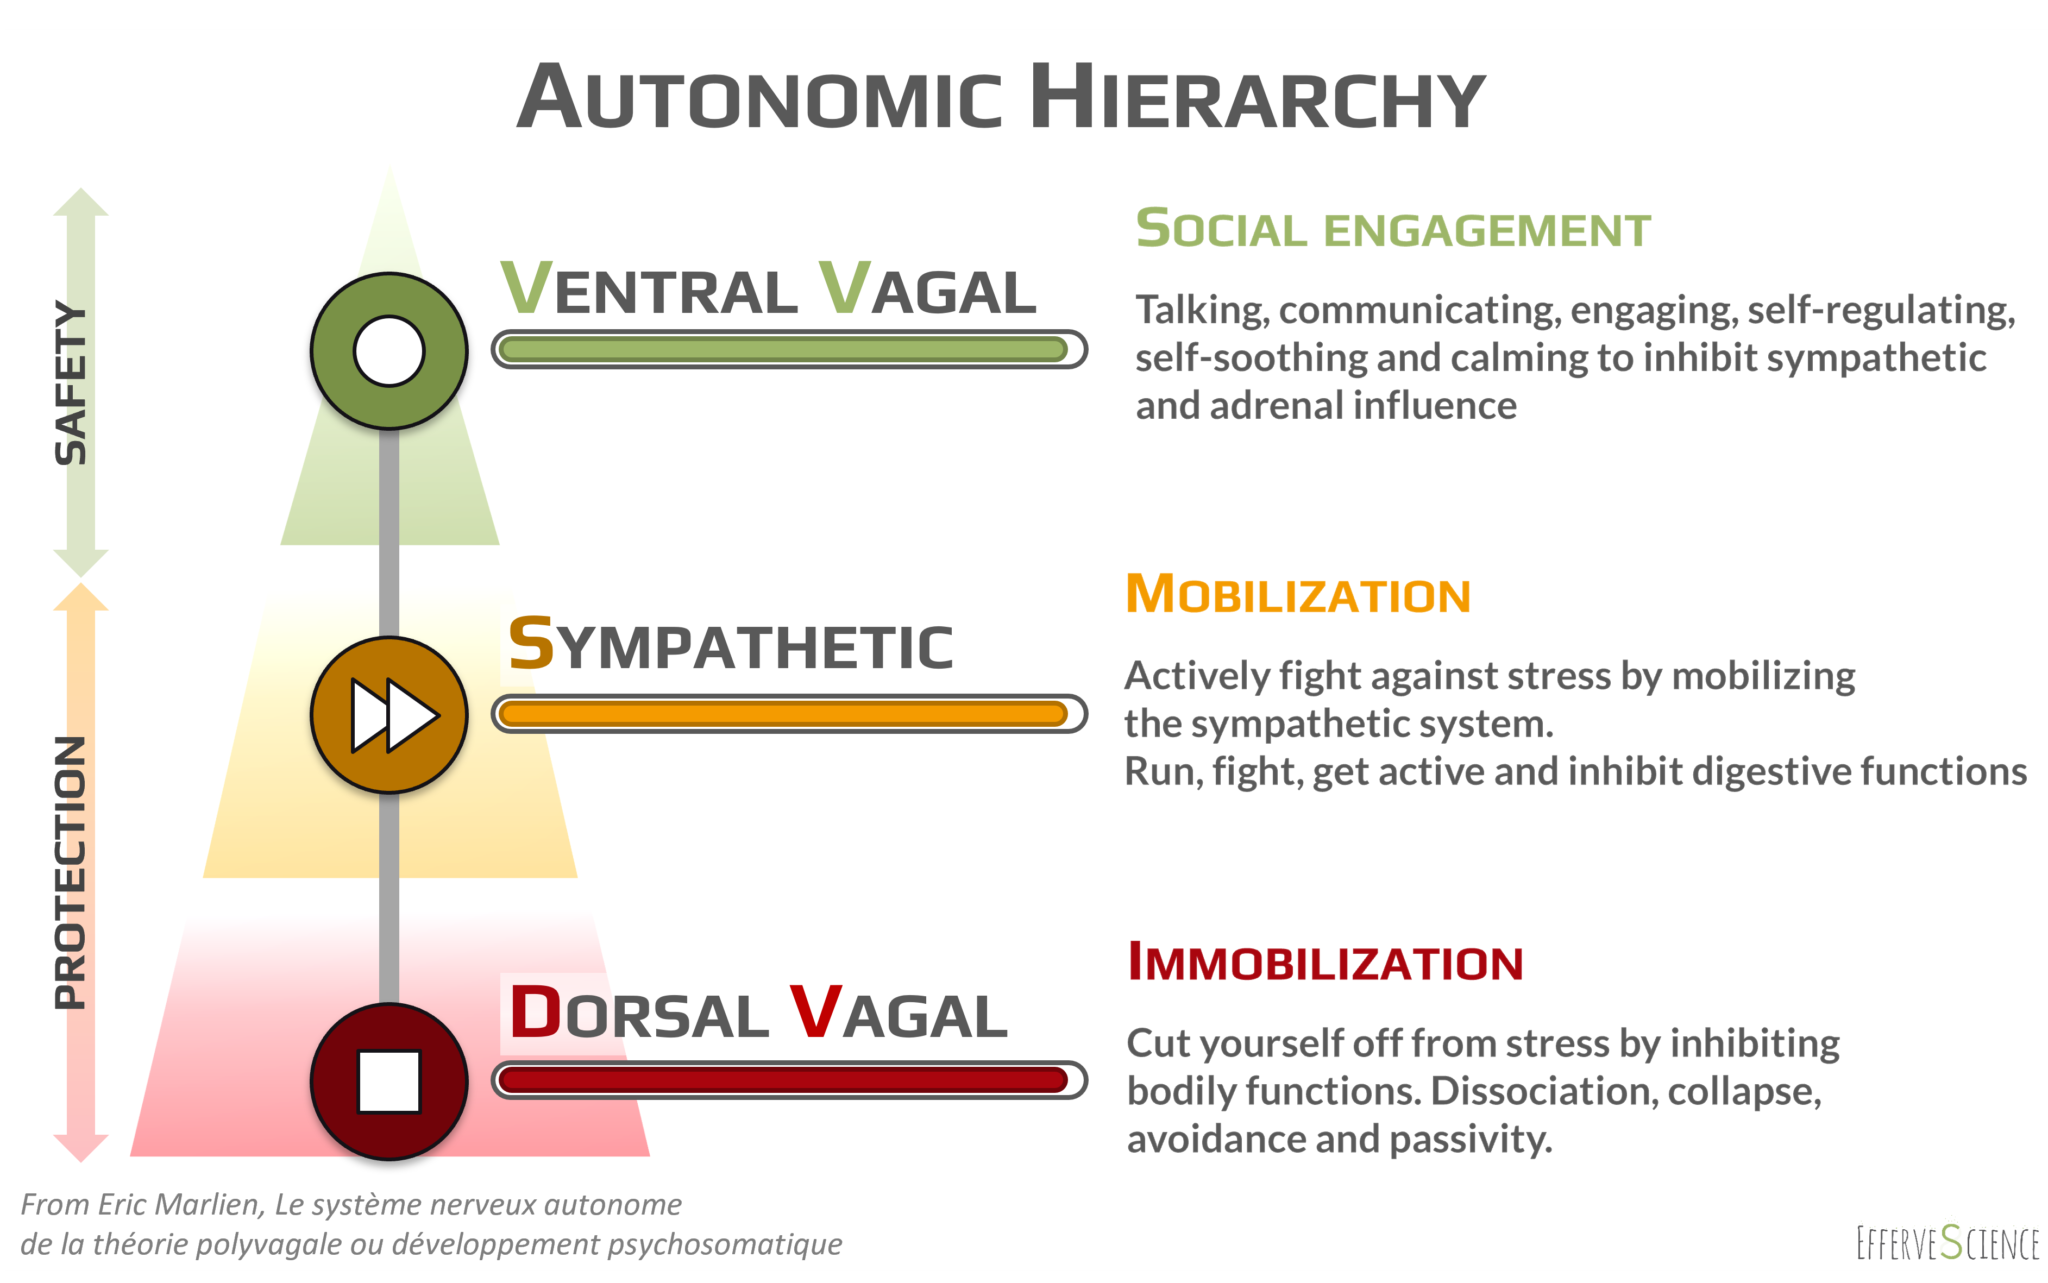
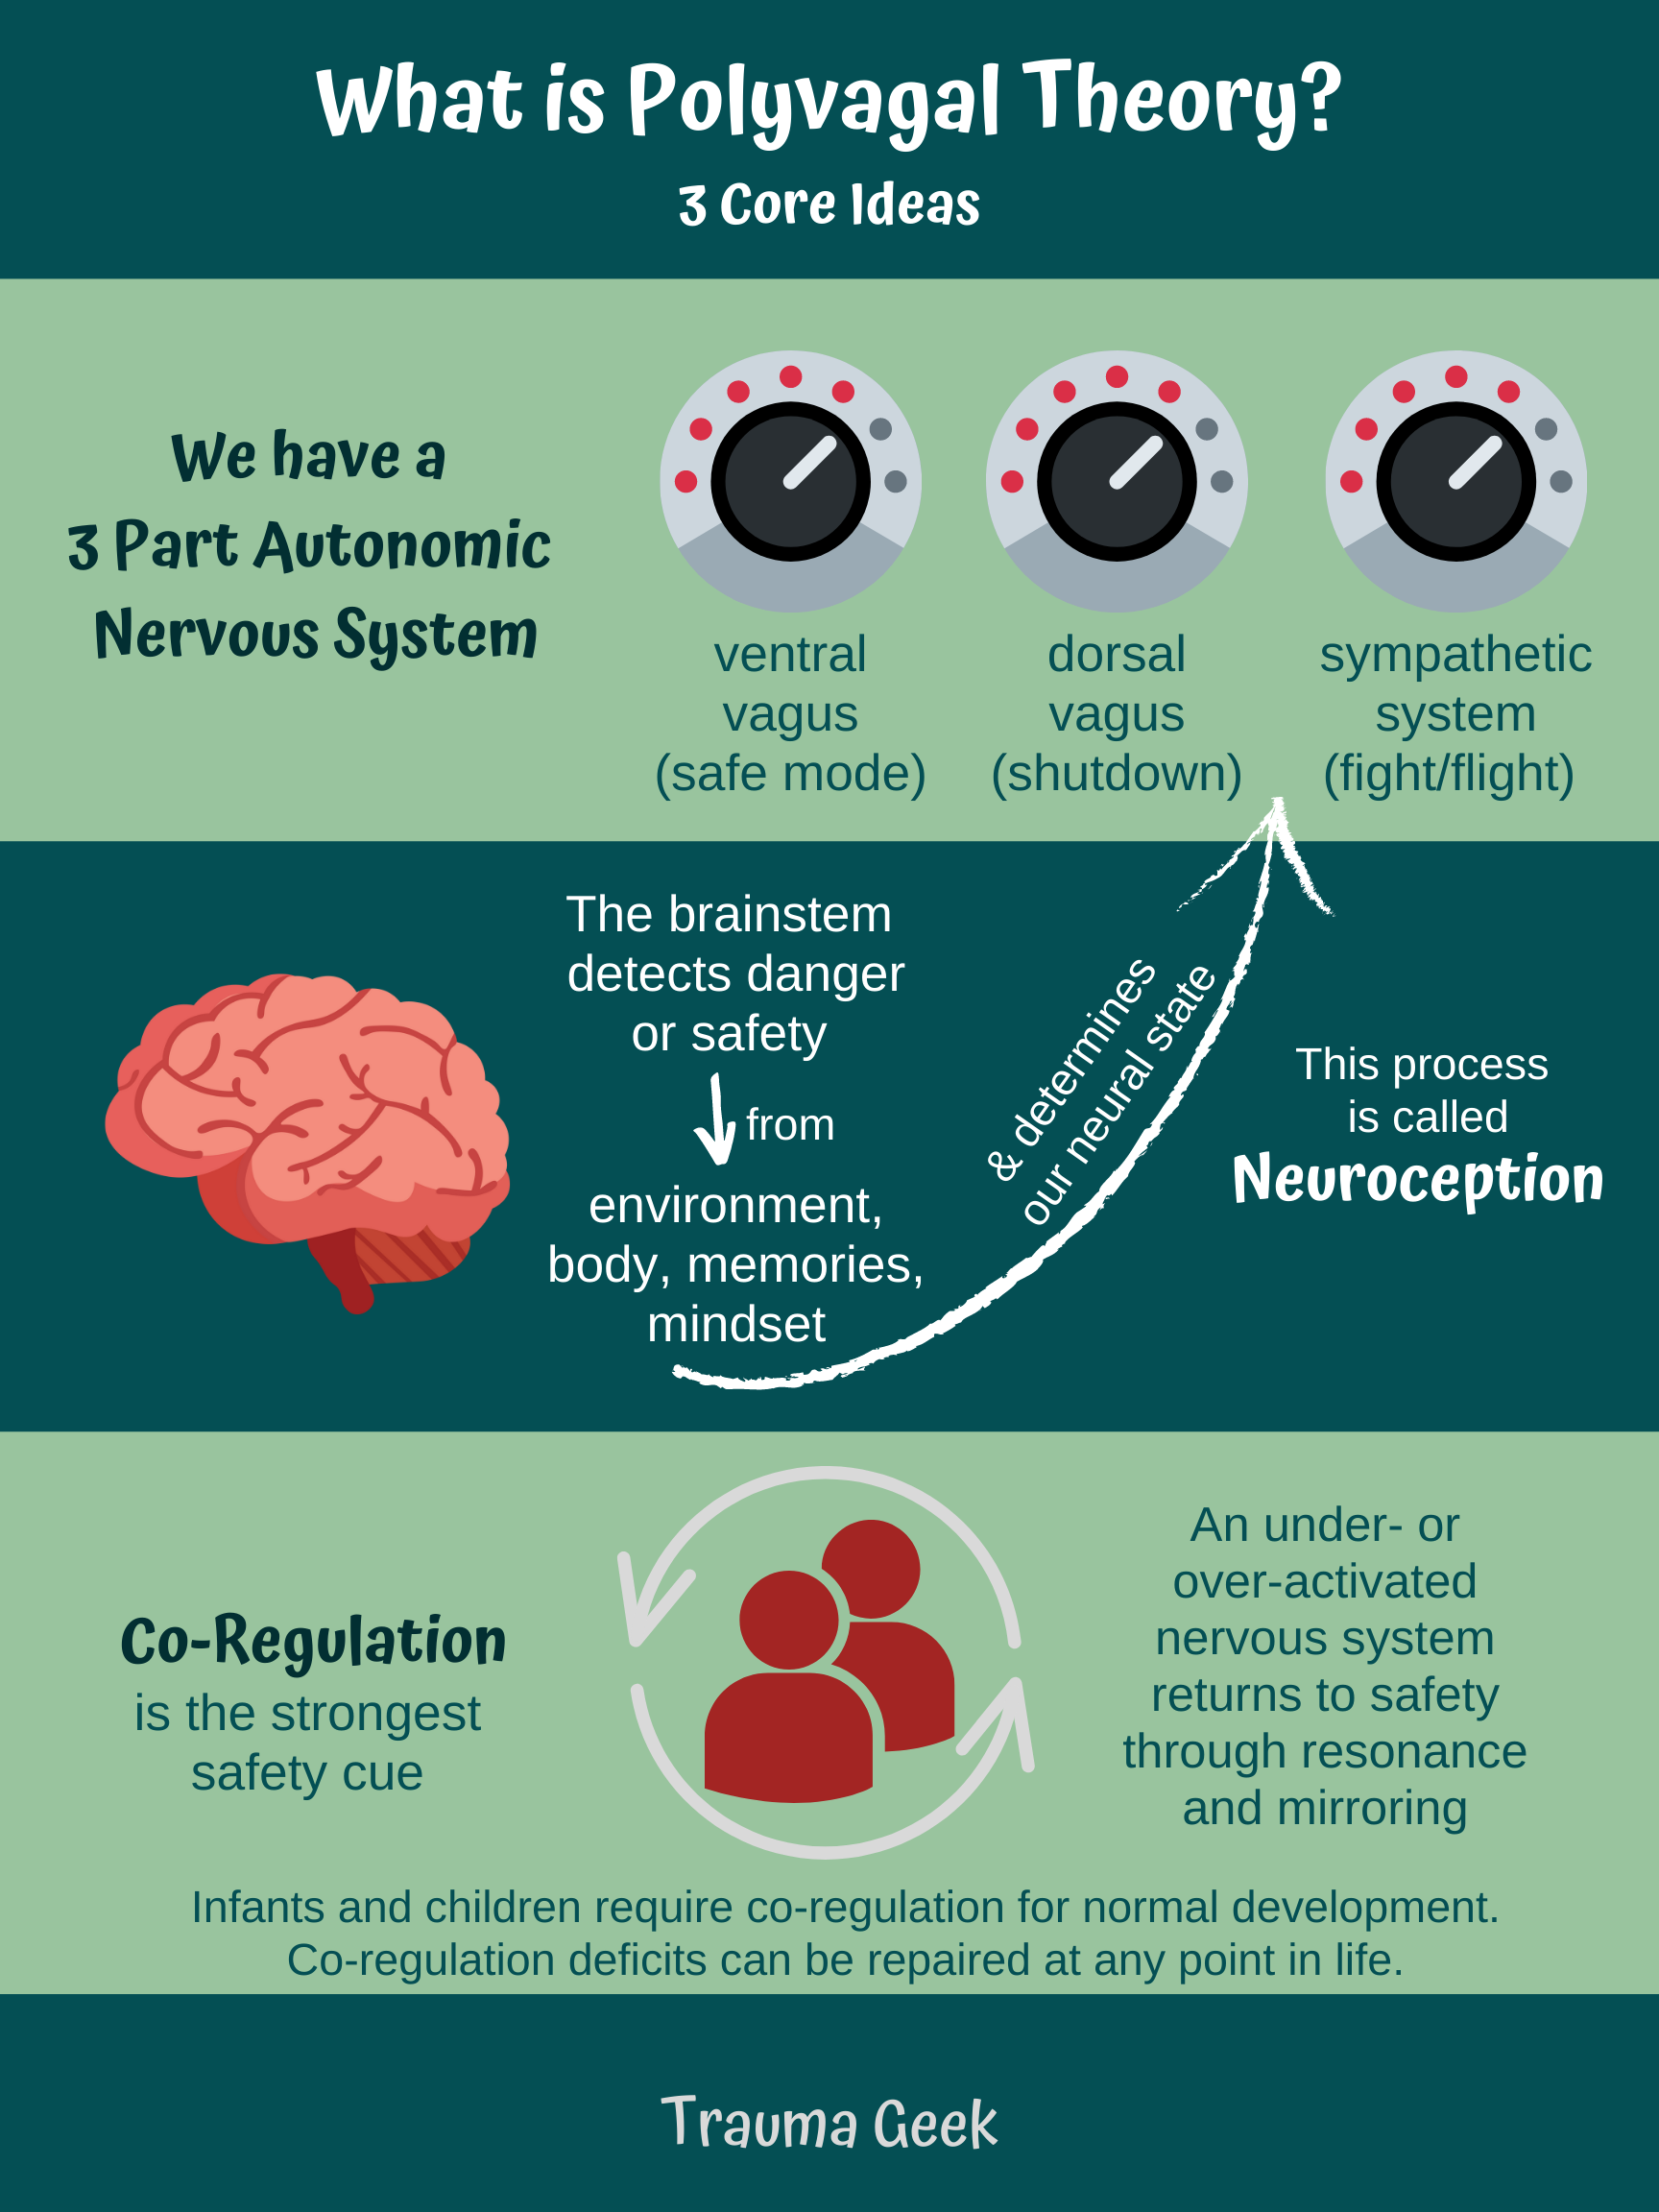
Polyvagal Theory was proposed by Stephen Porges in 1994. It's a model of the autonomic nervous system that explains how humans and mammals regulate safety, danger, and life threat through three distinct neural pathways. The theory builds on earlier work by Cannon and Magoun but adds a hierarchical framework based on evolutionary development of the vagus nerve and its branches. The model has three states. Ventral vagal is the most recent evolutionary layer — it supports social engagement, calm, and connection. Sympathetic drives mobilization: fight, flight, or forced activity. Dorsal vagal is the oldest layer and handles immobilization: shutdown, dissociation, collapse. These aren't choices you make. Your nervous system cycles through them automatically based on what neuroception detects in your environment. Neuroception is Porges' term for the subconscious process where your nervous system constantly scans for cues of safety or threat. It happens below conscious awareness. You don't decide whether you feel safe. Your body decides first, then your thoughts catch up.
Guide To Polyvagal Theory
If you're trying to use this model in practice — therapy, coaching, self-regulation — the first thing you need to understand is that the states are hierarchical but not strictly linear. You don't always climb down the ladder one step at a time. A person can jump from dorsal vagal shutdown directly into a sympathetic explosion. That's common in complex trauma. The ladder metaphor is useful but it's also slightly misleading if you treat it like a staircase you can only descend one rung at a time. Here's how I approach it with clients. First, identify the current state. Look for physiological markers, not just behavior. A person scrolling endlessly on their phone isn't necessarily in ventral vagal. They could be in a sympathetic freeze — high arousal masked as calm. True ventral vagal shows up as relaxed facial muscles, steady breathing, the ability to make eye contact without discomfort, and a voice that carries natural melodic variation. When someone is in sympathetic dominance, the body is in motion. Increased heart rate, shallow breathing, muscle tension, irritability, racing thoughts. Interventions focus on burning off the mobilized energy. Cold exposure, vigorous exercise, breathwork with extended exhales, even rhythmic tapping on the chest. I had a client once who couldn't regulate after a panic episode no matter what we tried. We sat with her for twenty minutes doing nothing. Then she stood up and started aggressively shaking her arms and legs for about thirty seconds. The panic lifted. Turns out her body had been trying to discharge the sympathetic activation the whole time and we'd been accidentally blocking it by suggesting grounding exercises that required stillness. Sometimes the nervous system needs to complete the mobilization response, not suppress it.
When someone is in dorsal vagal states — collapsed, numb, dissociated, unable to speak or move — sympathetic techniques make things worse. Pushing a dissociated person to "take action" or "exercise" can trigger further shutdown. The workaround here is gentle, slow re-engagement. Humming, sighing, slow rocking, listening to familiar music at a comfortable volume. The goal is to stimulate the ventral vagal branch of the vagus nerve, which Porges identified as the newer evolutionary pathway that modulates both sympathetic and dorsal responses. Vagal tonicity matters more than people realize. Higher vagal tone correlates with better emotional regulation, faster recovery from stress, and stronger social connection. You can measure it indirectly through heart rate variability, specifically the high-frequency component of HRV. But measuring isn't the same as improving. Vagal tone increases through repeated experiences of safety, not through intellectual understanding of safety.
Get the Full Details

Common Mistakes People Make
The biggest problem I see is people using polyvagal theory as a labeling system instead of a descriptive one. Someone gets labeled "stuck in dorsal vagal" and then everyone around them treats them as broken rather than as a person whose nervous system is doing exactly what it evolved to do under perceived life threat. The model explains the mechanism. It doesn't assign character. Another issue is the oversimplification of the dorsal vagal state as simply "bad." In extreme situations — severe trauma, prolonged illness, chronic pain — dorsal vagal shutdown is an adaptive survival mechanism. Calling it pathological ignores that it kept the person alive. The question isn't whether the state is good or bad. It's whether the state is appropriate to the current threat level and whether the person can return to ventral vagal when the threat has passed. Porges himself has acknowledged that some interpretations of his work go beyond what the data supports. The idea that you can directly increase vagal tone through specific techniques has limited empirical backing. What has stronger evidence is that social engagement behaviors — face-to-face interaction, synchronized breathing with a trusted person, vocal resonance — correlate with improved autonomic regulation. The mechanism may not be exactly what Porges originally described, but the practical outcomes are real.
There's also the risk of neuro-narcissism, where people become obsessed with tracking their own nervous system states to the point where normal emotional experiences get reinterpreted as trauma responses. Feeling anxious before a presentation isn't necessarily a sympathetic surge that needs interventions. It's a normal human reaction. The model becomes counterproductive when it pathologizes ordinary physiology.
What the Research Actually Says
Polyvagal Theory has influenced a lot of therapeutic practice, but the peer-reviewed support is mixed. Some studies show correlations between polyvagal-based interventions and improvements in anxiety, PTSD, and autism symptoms. Other studies find effects that don't hold up under controlled conditions. The theory's core claim — that the ventral vagal complex is a distinct neural structure with specific functions — remains debated among neuroscientists. What's well-established is that the autonomic nervous system has multiple regulatory pathways beyond the simple fight-or-flight model. The ventral and dorsal vagal branches do have different anatomical origins and functional profiles. Social engagement involving facial expression, vocalization, and listening is genuinely regulated by cranial nerve pathways that interact with autonomic output. That part is solid neuroscience. The broader theoretical framework built around it is where the controversy sits. If you're looking for resources, Porges' original work is in the journal papers from the 1990s and his book The Polyvagal Theory. For a more accessible and critically balanced introduction, Deb Dana's The Polyvagal Theory in Therapy is widely used by clinicians. The research community also points to work by Stephen Porges, Arielle Schwartz, and Pat Ogden on trauma and nervous system regulation, though their approaches diverge in important ways from strict polyvagal doctrine.
Practical Application
Use the model as a map, not a diagnosis. When someone (or you) is dysregulated, ask which state is dominant and what kind of support that state actually needs. Sympathetic arousal often responds to movement and discharge. Dorsal shutdown responds to gentle connection and slow re-engagement. Ventral vagal is maintained through consistent, predictable safety over time. The model doesn't replace trauma therapy, psychiatric care, or medical treatment. It's a lens for understanding autonomic responses. Some of the most effective uses I've seen combine polyvagal-informed awareness with somatic experiencing, EMDR, or parts work. Used in isolation, it tends to either become a self-diagnosis tool or a vague wellness buzzword. One thing I want to stress: this isn't a quick fix framework. Nervous system regulation takes repeated, consistent practice over months or years. Nobody retrains their autonomic responses in a weekend retreat. The theory describes a real biological system. Working with that system honestly means accepting that progress is non-linear and that setbacks are part of the process, not proof that the model failed.