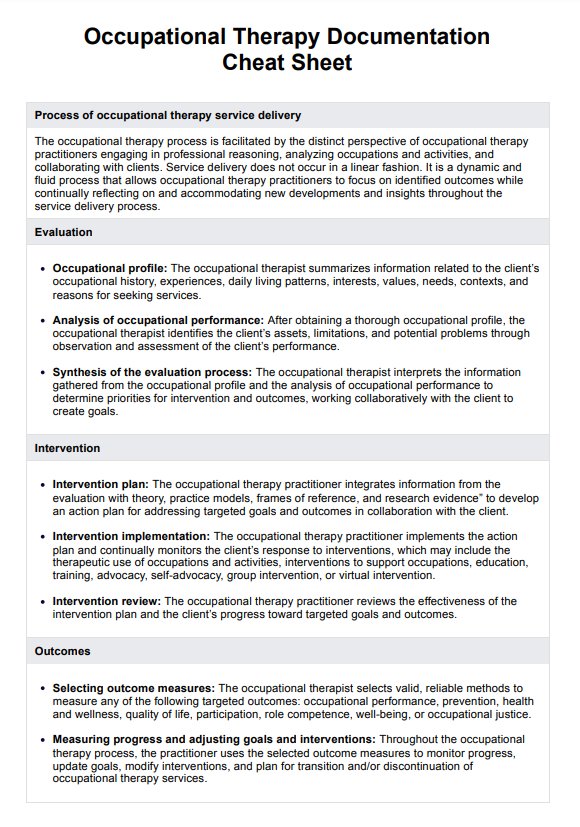
What Actually Gets Documented in OT Notes
Most people think documentation is just filling out boxes so the insurance company doesn't complain. It's not. It's the difference between a therapist who gets audited and one who retires without an incident. The Guidelines For Documentation Of Occupational Therapy are less about bureaucracy and more about creating a paper trail that holds up when someone with a grudge and a clipboard asks questions. I've spent years watching people fail at this. Not because they're bad clinicians. Because they treat notes as an afterthought instead of a clinical tool. You write a note like you're talking to a coworker who needs to understand exactly what happened. Not like you're performing for a billing auditor three months later.
Guidelines For Documentation Of Occupational Therapy
The core guidelines come from several sources: the AOTA Practice Guidelines, CMS Manual System Chapter 15, and payer-specific requirements. You'll also see your state licensing board requirements layered on top. They overlap heavily but aren't identical. AOTA gives you the professional standard. CMS gives you the federal billing standard. Payors give you the nitty-gritty that actually determines whether you get paid. Here's the practical framework most clinics actually use: Every session note needs a date, a CPT code, the procedure time with minutes documented, the specific intervention performed, patient response, functional improvement or lack thereof, and the plan for next session. That's it. But the devil is in the details. A CPT code without a qualifying diagnosis is just a number. A time stamp without a unit count is useless for billing. An intervention description without measurable outcome is just someone's diary entry.
I remember one specific case that almost cost my clinic a contract with a major managed care organization. We were documenting group OT for a vocational rehabilitation program. The payer required documentation of each individual's participation level in the group setting. My documentation habit was to write a single group note summarizing the session collectively. That worked fine for internal communication. It failed a payer audit because I couldn't prove individual progress for each of the six participants. The workaround was straightforward but tedious. I created a tracking matrix where each group session had a row for each participant with columns for their specific activity, time spent, response quality, and measurable outcome. Takes about ten minutes per group session. Saved us from having to reconstruct three months of notes from memory, which would have been a nightmare. Never again did I document a group session the lazy way.
Get the Full Details

The Counter-Intuitive Stuff Nobody Teaches
Beginners think more documentation is better. Experienced therapists know that strategic documentation is better. There's a meaningful difference. Wading through twenty pages of narrative every session doesn't help anyone. What helps is writing enough to defend your clinical decisions without drowning the reader in irrelevant detail. One thing that catches people off guard: the difference between medical necessity and functional improvement in documentation. Medical necessity justifies why therapy started. Functional improvement justifies why it continues. Insurers don't audit the start. They audit the continuation. If your notes only show that the patient keeps coming back but never document measurable functional change, you're leaving the door open for a denial. Every single session note should contain at least one data point showing where the patient was, where they are now, and what's different. Another counter-intuitive point: the 15-minute rule for timed codes. CMS requires at least 15 minutes of direct patient contact to bill a 15-unit block. But here's what most people miss. If you bill a 30-minute block and only document 25 minutes, you're underreporting. The documentation must match the billing exactly. I've seen therapists accidentally document 45 minutes for a CPT they billed for 60 minutes because they rounded numbers in their head. That creates a discrepancy that auditors flag immediately. Document to the minute. Bill to the unit block. Keep them aligned.
Realistic Pitfalls That Cost People Their Jobs
Copy-paste documentation is the fastest way to get caught. It sounds efficient. It is not. When two patients' notes end up with different names but identical activity descriptions, dates, and even typos, that's a red flag. Payers and OIG auditors look for exactly this pattern. They have software for it. It runs automatically against claims databases. Here's a scenario I've seen play out: a therapist documents a patient as "cooperative and engaged throughout the session" on Monday. On Tuesday, the same patient is described as "distracted and resistant." Wednesday brings "poor cooperation and limited engagement." These are vague, non-measurable descriptors that don't actually tell anyone anything useful. Replace them with observable behaviors. "Patient required verbal redirection three times during task initiation. Completed 4 of 6 prescribed activities independently. Stopped working twice to fidget with clothing material." One version is fluff. The other is documentation. There's also the problem of template fatigue. Many clinics use pre-built templates to save time. Templates are fine. Blank templates are dangerous because they create the illusion that something was documented when nothing was added. I once reviewed notes where the template fields were populated with generic placeholders like "[Patient demonstrated improvement]" that nobody had bothered to replace. That note is legally worthless and creates liability exposure for every provider who signed it.
What Happens When Documentation Falls Apart
Let me be blunt about the downsides and limitations of even well-maintained documentation systems. They create a bottleneck. Detailed, compliant documentation takes time. A thorough one-hour session note that meets all payer requirements can take 10 to 20 minutes to complete if you're doing it right. That's after you've already spent the hour with the patient. In high-volume settings where therapists see eight to ten patients a day, that's 80 to 200 minutes of documentation time on top of direct care. It adds up. Some clinics absorb this through staffing. Others don't, and the quality of documentation suffers as a result. There's no clean solution to that tension. Another hard truth: documentation doesn't protect you from everything. You can follow every guideline perfectly and still face an audit. You can write the most thorough note in the world and an auditor can still interpret it against your favor. Good documentation raises the bar for what a defensible record looks like. It doesn't guarantee immunity. Accept that upfront and you'll approach it with the right level of care rather than false confidence. If you're working in a setting where documentation time isn't factored into your productivity expectations, consider advocating for protected documentation blocks or reducing patient panels slightly. No amount of efficiency training will eliminate the time required for compliant notes. It's a fixed cost of practice. Budget for it.

Practical Workflow for Daily Documentation
Start writing during the session whenever possible. I keep a small pad or a tablet with me and jot brief markers as activities happen. Instead of trying to recall everything after the patient leaves, I capture three things in real time: the intervention, the patient's response level (independent, modified independent, needs standby assist, needs minimal assist, needs moderate assist, needs maximal assist, or dependent), and the time elapsed for that specific activity. By the time the patient is disrobing or washing up, I have the skeleton of the note already done. When I sit down to finalize the note, I'm filling in gaps, not reconstructing the entire session from memory. This usually cuts documentation time by half compared to doing it all after the fact. For a 30-minute session note, that drops it from roughly 15 minutes to about 7. The difference is significant over a full week. Use standardized language for common interventions. "Therapeutic exercise to improve upper extremity strength" is a standard phrase. It's also too vague if you're billing for a specific CPT. Instead, "Therapeutic exercise to improve right upper extremity strength using resistance bands at 3 pounds for 2 sets of 10 repetitions." Same concept. More defensible. Takes about five seconds longer to write.
For progress notes, follow a structure that links intervention to outcome directly. State what was done, what the baseline was, what the current status is, and what the plan is. Don't bury the outcome in the middle of a paragraph about equipment used. Lead with the clinical reasoning and follow with the supporting details. Auditors read bottom to top sometimes. Make sure they find the justification early.
Special Situations That Require Extra Care
Legal cases change the documentation landscape entirely. If there's any possibility of a workers' compensation claim, personal injury lawsuit, or disability appeal involving your patient, your notes become evidence. Write them the way you'd want them to withstand cross-examination. That means including the patient's own reported symptoms verbatim when relevant. If a patient says "my hand hurts when I grip things," write that. Don't paraphrase it into "patient reports hand pain." The original wording matters in legal proceedings. Telehealth documentation is another area where shortcuts cause problems. The pandemic normalized remote OT sessions, but billing requirements for telehealth still vary by payer and change frequently. Some require a specific modifier. Some require documentation of patient consent for telehealth. Some require a separate note structure. Before you schedule your first telehealth session, check with your payer about their current requirements. Having to retroactively document telehealth elements for past sessions is expensive in terms of both time and risk. Group documentation deserves its own attention because it's where most people cut corners. The matrix approach I mentioned earlier works, but there's a simpler alternative if your group size is small: individual notes that reference the group context. "Participated in group session focusing on ADL skills. Working on buttoning with adaptive button aid. Required moderate verbal cueing for sequencing. Improved from 3-button accuracy to 5-button accuracy this session." This gives you individual documentation while acknowledging the group setting. Much easier to produce than a full matrix and still defensible.

The bottom line is that documentation is a clinical skill, not an administrative burden. The people who treat it as an afterthought are the ones who end up spending far more time later dealing with denials, audits, and remediation. The people who treat it as part of their clinical process write notes that actually serve the patient, the provider, and the system. There's a reason the best therapists aren't the ones with the shortest note turnaround times. It's because they're building a record that lasts.