How I Approach GBS Rehab After the Acute Phase Ends
Most occupational therapists I work with get stuck waiting for physicians to clear patients before doing anything meaningful. That delay costs weeks of neuroplastic potential. Here is what I actually do once a GBS patient has medical clearance to begin rehab.
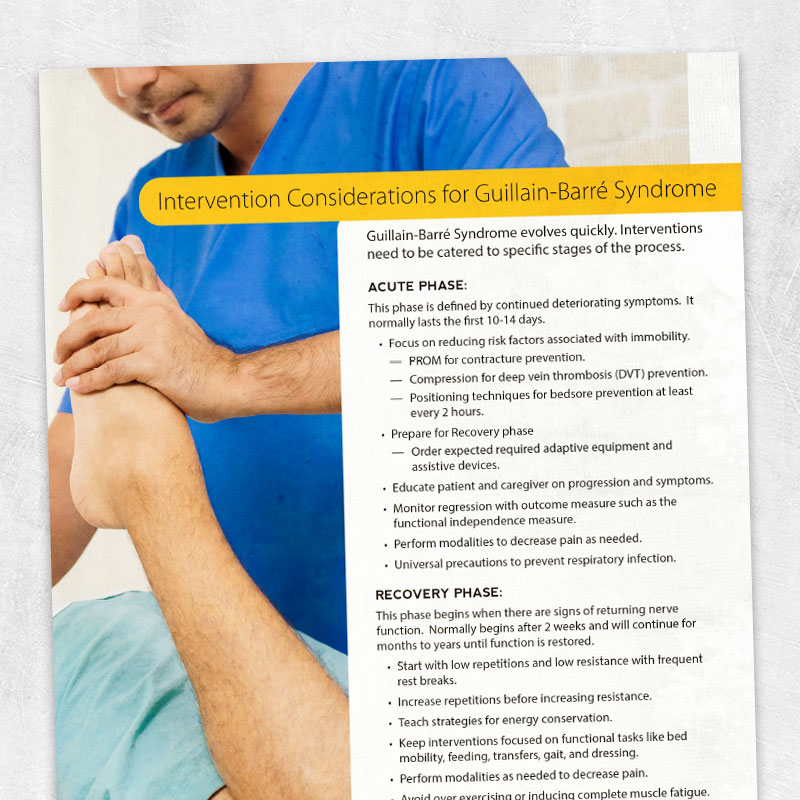
Guillain Barre Syndrome Occupational Therapy
The acute phase of GBS involves progressive symmetric weakness, often starting in the lower extremities and moving upward. Sensory symptoms can accompany the motor deficits. By the time a patient reaches me, they are usually at or near their nadir. The immune system has already done its damage, and we are entering the plateau or recovery phase. What matters then is not diagnosis anymore. It is functional preservation and preventing secondary complications.
My standard assessment begins with active range of motion in all four extremities, seated and supine. I note what movement persists voluntarily and where it is absent. I check for any residual sensation in the hands and feet, because tactile feedback changes everything when you are retraining grip and manipulation. I also screen for autonomic dysfunction - blood pressure fluctuations, heart rate variability issues. These are not rare in GBS and they affect tolerance for upright positioning.
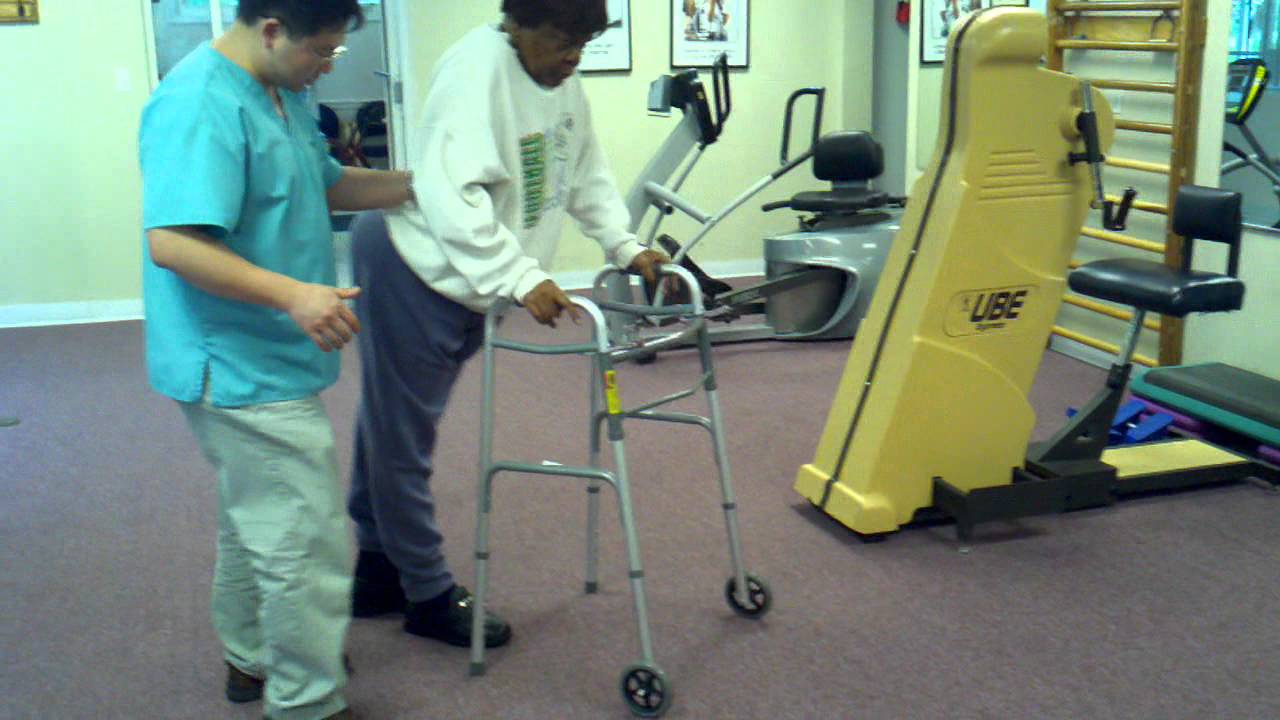
For orthotic intervention, I usually start with wrist-hand orthoses in neutral extension for patients with zero wrist extensor strength. It prevents flexion contractures and keeps the hand in a position where tenodesis grasp can eventually function. A forearm crutch walker or front wheeled walker comes next for standing tolerance. I do not rush standing without upper body strength present. GBS patients often have significant shoulder girdle weakness that people overlook because they focus entirely on the legs.
I ran into a case last year where a 54-year-old male with a good prognosis for ambulation still had near-zero triceps activation at six weeks post-diagnosis. He was determined to transfer independently using a slide board. Every attempt resulted in him sliding backward onto his sacrum because he could not lock his elbows to support his weight. Standard therapy would have had me simply strengthen the triceps and hope for improvement. Instead, I ordered a bilateral elbow brace with a locking mechanism and installed a transfer belt with a broad handle. The elbow brace allowed him to achieve full elbow extension under load, and the transfer belt gave him something secure to push from. He achieved independent slide board transfers within two weeks instead of possibly months of failed attempts.
Progressive resistance training begins only after active movement returns to at least grade 3. Early strengthening before voluntary control is present can cause abnormal recruitment patterns that persist long-term. I use light bands for shoulder abduction and external rotation first because those are where patients tend to decondition fastest. Grip retraining comes later. Adaptive equipment like button hooks, reachers, and modified utensils are introduced early, not as concessions but as ways to maintain participation in activities while the nerves regenerate. Nerve regeneration occurs at approximately one millimeter per day, sometimes slower. A patient with prolonged weakness can expect three to six months before meaningful motor return begins, depending on the initial severity.
One counter-intuitive point most clinicians miss: GBS recovery is not perfectly symmetrical. I have seen patients with noticeable strength asymmetry in the upper extremities by the time they reach subacute rehab, and those patients often struggle more with bimanual tasks than patients who remain symmetrically weak. When one hand recovers slightly faster than the other, coordination suffers because the CNS has to recalibrate to an uneven input pattern. I address this with bilateral activities that do not demand fine grip from the recovering side, like weighted push-up boards or assisted rowing machines.
Spasticity during recovery is another unexpected issue. GBS is classified as a demyelinating or axonal peripheral neuropathy, not a central nervous system disorder, so spasticity should not theoretically occur. In practice, I have encountered it in about 10 percent of cases, usually during the recovery phase when muscle tone shifts from flaccid to increased. It does not present like UMN spasticity. It is more of a sustained contraction pattern, often in the finger flexors and ankle dorsiflexors. I manage it with sustained stretching and splinting rather than botulinum toxin, which is generally unnecessary at this dose level.
The main limitation of this approach is that it requires consistent patient engagement over a long timeframe. GBS recovery is slow and non-linear. Some weeks show real progress. Other weeks feel like stagnation. Patients and families often interpret plateau periods as regression and lose motivation. I address this by keeping a simple log of independent activities completed each week. Even if strength measurements stay the same, the number of daily tasks the patient can perform without assistance usually climbs. That data point tends to sustain adherence better than grip dynamometer readings.
For patients with severe autonomic instability, this entire framework changes. Blood pressure drops during positional changes can make standard sitting tolerance assessments dangerous. In those cases, I begin with recumbent positioning and gradual upright progression measured in five-minute increments while monitoring vital signs. The functional goals remain the same, but the pacing is completely different.
I usually recommend the standard Barthel Index combined with the FIM for tracking progress in GBS. Both are validated, both capture the relevant domains, and both are quick enough to administer weekly without consuming therapy time. Self-administered versions exist if you need patient-reported outcomes between sessions.
Guillain Barre Syndrome Occupational Therapy at Stephen Lee blog
Occupational Therapy Activities For Guillain-Barre Syndrome at Wilbur ...
Occupational Therapy Activities For Guillain-Barre Syndrome at Wilbur ...
Occupational Therapy Activities For Guillain-Barre Syndrome at Wilbur ...
Physical Therapy Exercises For Guillain Barre Syndrome at Kristie ...