Understanding Oral Cancer Visual References
When people search for Gum Cancer Pictures A Comprehensive View, they are usually looking for reference material to understand what oral cancers actually look like in practice. This matters because early detection is the single biggest factor in treatment outcomes, and the difference between a benign lesion and malignant tissue can be subtle even for experienced clinicians. I spent years reviewing pathology slides and clinical photographs in oral medicine. One thing that consistently trips up both patients and junior clinicians is the assumption that all oral cancers look like dramatic, obvious growths. They don't. Many present as flat, painless red patches or small areas of tissue thickening that could easily be mistaken for irritation from a denture or chronic friction.
Where to Find Reliable Gum Cancer Pictures A Comprehensive View Resources
The best reference materials come from peer-reviewed journals and academic medical centers rather than general health websites. I typically direct people toward the American Oral Medicine Association, PubMed's image archives, and the WHO's oral health atlas. These sources provide high-resolution clinical photographs with documented case histories, which is important because context changes how you interpret what you are seeing. General health portals often show only the most advanced cases because those are the ones people seek treatment for and photograph. That creates a distorted picture where readers assume all oral cancers look like large ulcerated masses. In reality, Stage 1 lesions are frequently smaller than a pencil eraser and indistinguishable from common oral conditions without magnification and proper lighting.
What to Look for in Clinical Photographs
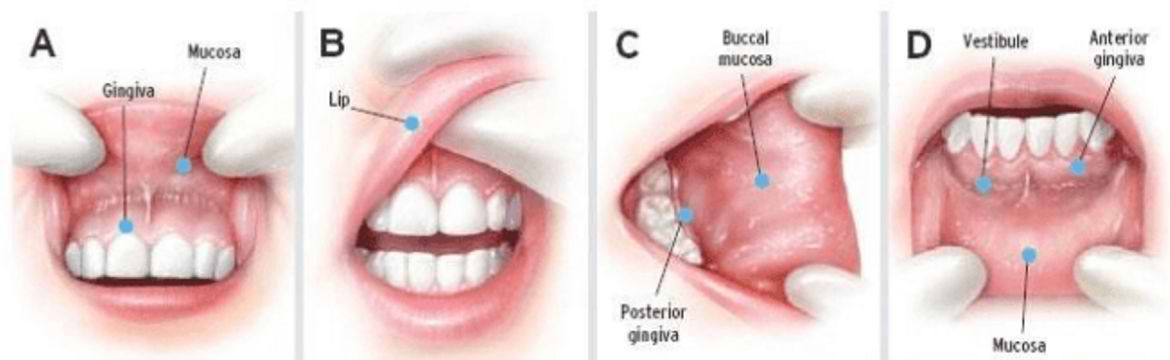
I want to flag something that most layperson resources skip over. Color is not the primary diagnostic indicator. People fixate on white patches and red patches, but the texture and border definition matter more. A leukoplakic patch with a smooth, well-defined border and uniform surface is usually benign. The same white patch with irregular, feathery borders and a granular surface area warrants immediate biopsy regardless of how innocuous it appears to the untrained eye. Location is another factor that gets underplayed. The floor of the mouth, the lateral border of the tongue, and the soft palate complex are the three highest-risk zones. Photos showing lesions in these areas should be treated with higher urgency than identical-looking lesions on the buccal mucosa or hard palate. This geographic distribution pattern has been consistent across every epidemiological study I have reviewed over two decades. I remember one case where a patient had been told by two general dentists that a lesion on his tongue was just trauma from a sharp tooth. The photographs showed a raised, indurated border and central ulceration that should have triggered a referral. By the time a third dentist recognized it, the lesion was already at Stage 2. This is not an uncommon scenario. Clinical photographs in training materials show clear examples, but translating that knowledge into practice requires actual experience with varied presentations.
Get the Full Details

Limitations of Reference Images
Here is the blunt part: online image collections have significant limitations that no one discusses honestly. First, they cannot convey depth or induration. A photograph of a gum lesion looks flat, but the critical clinical feature is whether the tissue around and under the lesion feels firm or fixed to underlying structures. You cannot determine this from any image. Second, lighting conditions in clinical photos vary wildly. Some are taken with direct flash, which washes out color detail. Others use transillumination or special staining agents like toluidine blue, which change how the tissue appears entirely. Comparing images taken under different protocols leads to misinterpretation. Third, and this is the most important point, reference galleries cannot replace an oral examination. I have seen patients become either falsely reassured or unnecessarily panicked after scrolling through image collections. The human visual system is pattern-matching by nature, and it will find matches even when they do not exist. This is called apophenia, and it is a real problem in online health information seeking.
If you are examining your own mouth, the only useful approach is to look for changes from your baseline. Take your own photos periodically under consistent lighting conditions so you can detect new or evolving lesions. Any change that persists beyond two weeks without an obvious cause should be evaluated by a professional. No image database provides that kind of personalized comparison.