What Quadruple Therapy Actually Is and Why It Changed Everything
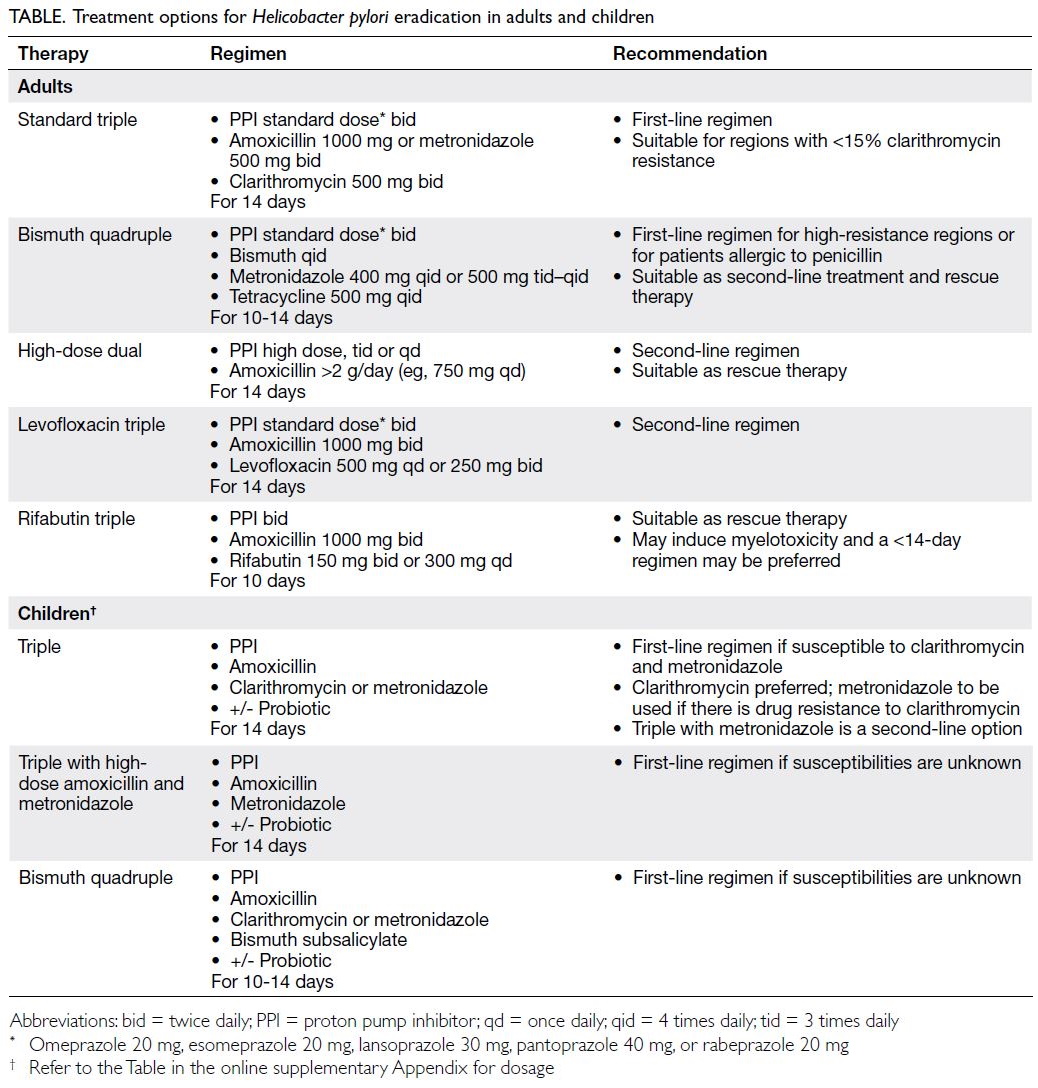
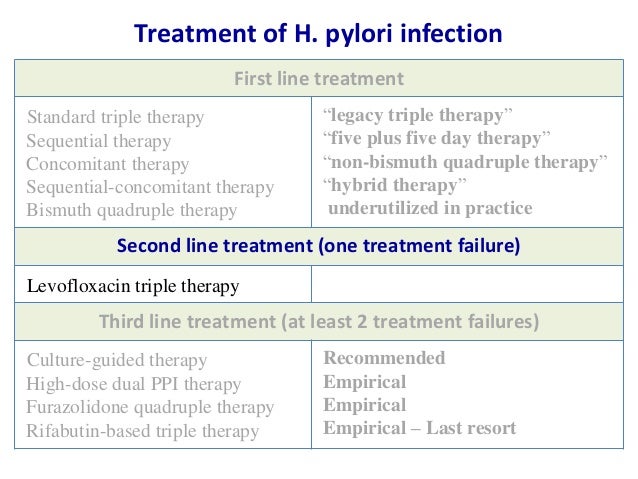
The old standard triple therapy — a proton pump inhibitor plus amoxicillin and clarithromycin — has been falling apart for years. Resistance rates to clarithromycin are now well over 15% in most regions, and in some areas approaching 30%. When resistance is that high, calling triple therapy the default approach is just wrong. The bismuth quadruple therapy regimen replaced it as first-line treatment in the ACG clinical guidelines back in 2017, and most gastroenterologists have been prescribing it since. If you're still getting triple therapy as first-line anywhere, you should probably ask why. The four-drug regimen combines a proton pump inhibitor, bismuth subsalicylate (or subcitrate), tetracycline, and metronidazole, taken four times daily for 10 to 14 days. That's it. No fancy protocol. The PPI reduces gastric acidity so the antibiotics can actually reach the bacteria, bismuth directly damages the H pylori cell wall and has its own anti-adhesive properties, tetracycline inhibits protein synthesis, and metronidazole creates DNA strand breaks in the organism. The synergy between bismuth and metronidazole is particularly important because bismuth can inhibit the enzymes that would otherwise deactivate metronidazole.
H Pylori Treatment Quadruple Therapy: What You Need to Know Before Starting
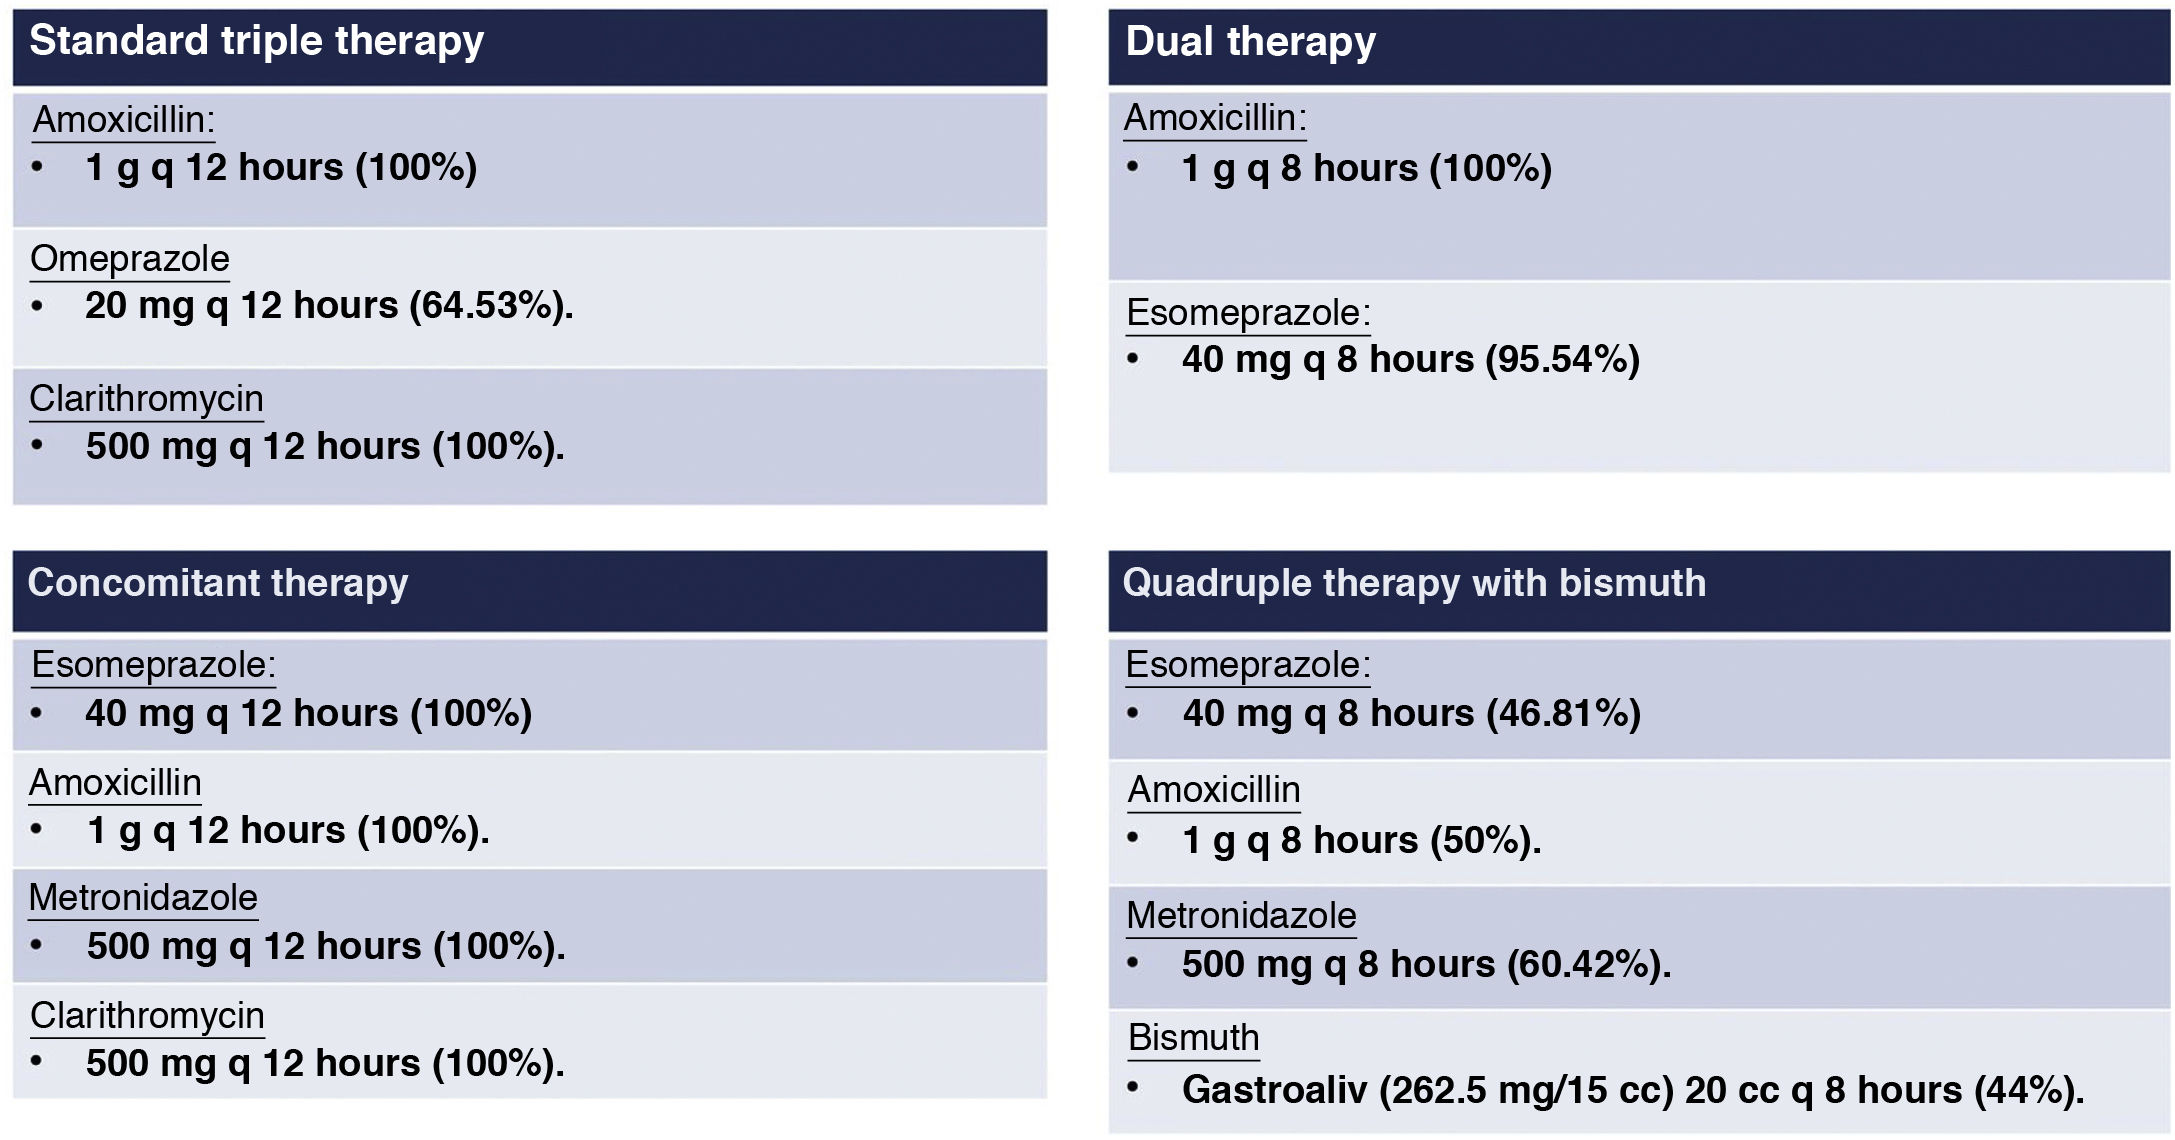
Dosing breakdown: The typical adult prescription looks like this. PPI taken twice daily — omeprazole 20mg, lansoprazole 30mg, or preferably a higher-dose formulation like esomeprazole 40mg or rabeprazole 20mg, both taken 30 minutes before breakfast and dinner. Bismuth subsalicylate 525mg four times daily, or bismuth subcitrate potassium 300mg four times daily if you can get it. Tetracycline 500mg four times daily. Metronidazole 250 to 500mg four times daily, with 500mg being more common in modern protocols. All medications are taken on a strictly timed schedule throughout the day, roughly every six hours while awake, for the full duration. Here's something most patients don't expect: the treatment is aggressively hard on the gastrointestinal system. I've seen multiple patients report that the side effects during the second week are worse than the original infection symptoms. Nausea, metallic taste, dark stools from the bismuth, and in some cases vomiting that makes compliance nearly impossible. The metallic taste from metronidazole alone is significant enough that some patients attempt to stop early. A good workaround I've found is recommending they take the metronidazole dose with a small amount of food — not a full meal, which would interfere with absorption, but just a few crackers or a piece of bread to buffer the stomach lining without significantly affecting bioavailability. Another thing worth noting is the alcohol restriction. Metronidazole causes a disulfiram-like reaction with alcohol, and patients often forget about hidden sources of ethanol in mouthwash, liquid cold medications, and even certain flavoring extracts. The reaction isn't always dramatic — sometimes it's just pronounced flushing and headache — but it's real and it can absolutely tank your compliance if you're dealing with it on top of an already rough treatment course.
Practical Considerations Most Guidelines Don't Emphasize
Probiotic co-administration: There's moderate-quality evidence that Lactobacillus and Saccharomyces boulardii supplements reduce antibiotic-associated diarrhea and possibly improve eradication rates. The mechanism appears to involve competitive exclusion of pathogenic organisms and modulation of the local immune response. I typically recommend starting the probiotic on day one of treatment and continuing for at least two weeks after the antibiotics finish. The timing matters — take the probiotic at least three hours apart from any antibiotic dose, or you're just killing the cultures you're trying to supplement. The test-of-cure timing is another area where people consistently mess up. You need to wait at least four weeks after finishing all antibiotics and PPIs before doing a urea breath test or stool antigen test. If you test while still on a PPI, you'll get a false negative because the acid suppression temporarily reduces bacterial load without actually eradicating it. If you test too soon after antibiotics, residual bacterial debris can trigger a positive result even though the infection is gone. Four weeks minimum, two weeks off PPIs if clinically feasible. Some clinicians prefer a six-week window to be safe, and honestly, there's no downside to waiting longer. I ran into a specific edge case recently that illustrates why timing matters more than most people realize. A patient of mine completed a 14-day course of bismuth quadruple therapy and returned for testing at exactly three weeks. The PPI had been stopped five days before the UBT. The result was negative, and we declared cure. Two weeks later, he developed recurrent epigastric pain and a repeat test came back positive. The initial negative was a false negative caused by lingering PPI effect on the gastric mucosa — even though he'd stopped the pill, the acid-suppressive changes to the gastric environment hadn't fully reversed. We restarted treatment with a different antibiotic combination, this time using levofloxacin-based triple therapy, and confirmed eradication at six weeks post-treatment. The lesson: if someone has borderline compliance or had been on PPIs for a long time before treatment, push the test-of-cure to six weeks out.
Get the Full Details

When Quadruple Therapy Fails and What Comes Next
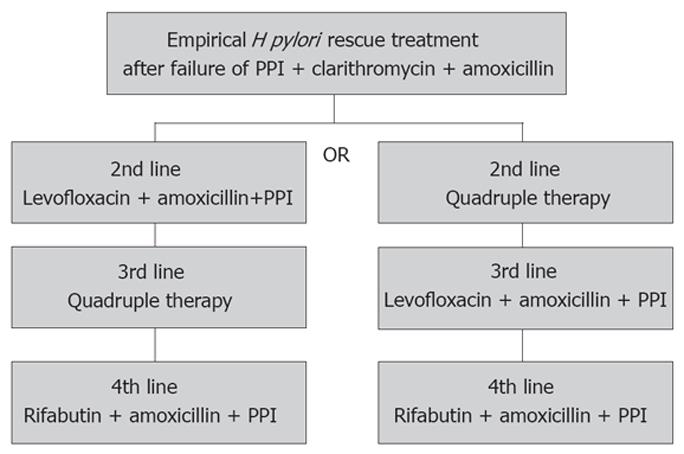
Eradication rates for bismuth quadruple therapy in treatment-naive patients typically range from 85% to 95% when compliance is good. That means roughly one in ten patients will still have active infection after a full course. When that happens, you don't just repeat the same regimen. You need a different antibiotic combination, and the choice depends heavily on what was used before and local resistance patterns. The standard salvage approach is levofloxacin-based triple therapy — a PPI, amoxicillin, and levofloxacin 500mg daily for 14 days. Levofloxacin resistance is generally low in most populations, usually under 5%, which makes it a reliable second-line option. But if your patient has already taken a macrolide like clarithromycin previously, or if they've been exposed to fluoroquinolones for any reason, resistance can be significant. In those cases, rifabutin-based therapy becomes an option, though it's expensive and carries its own side effect profile including potential bone marrow suppression. There's also a growing body of evidence supporting personalized therapy guided by culture and sensitivity testing. Endoscopic biopsy specimens can be cultured to determine exact antibiotic susceptibility, and this approach has shown eradication rates exceeding 90% even in multiply-treatment-failed cases. The downside is that culture takes time — usually 3 to 7 days — and not all centers have the capability. Molecular testing for resistance mutations via PCR is faster but more expensive and not universally available.
The most important factor in treatment success, regardless of which regimen you choose, is compliance. Missing even a few doses across a 14-day course dramatically reduces the odds of eradication. The four-times-daily dosing schedule of quadruple therapy is inherently harder to maintain than once-daily regimens. Using a pill organizer, setting phone alarms, and linking doses to specific daily activities — meals, brushing teeth, bedtime routines — actually makes a measurable difference. Patients who use these strategies report significantly better adherence and higher cure rates. The difference between 85% and 95% eradication is often just whether the patient actually took every dose on schedule.