
Getting Started With Healthcare Standards Without Losing Your Mind
The healthcare IT space has this weird habit of wrapping simple concepts in layers of compliance jargon until nobody remembers what the original problem was. I spent about four years dealing with HL7 interfaces, Meaningful Use attestations, and FHIR implementations across three different health systems before I stopped fighting the process and just learned to work within it. This guide is basically the document I wish existed when I was starting out. "Hacking healthcare" in this context doesn't mean breaking into systems. It means finding efficient, often unconventional pathways through the maze of regulatory requirements and technical standards that slow down actual clinical work. The term comes from the broader hackathon culture that migrated into healthcare IT around 2012-2014, and it stuck because it describes something real: the gap between what the systems are supposed to do and what clinicians actually need them to do. Standards work is the foundation here. If you don't understand HL7 v2 message structures, you're going to struggle with anything beyond basic data entry. I'm not going to dump a full HL7 tutorial on you, but you need to know that ADT messages, ORU messages, and SIU messages are the bread and butter of hospital interoperability. Most integrations in the wild still run on HL7 v2 despite everyone talking about FHIR. The transition is happening, slowly. You'll encounter both for the next decade at least.
Meaningful Use, now called Promoting Interoperability, is the regulatory framework that motivated most of the EHR adoption we see today. It's managed by CMS and ONC. The stages changed over time, and the requirements shifted. Stage 1 was about data capture and basic exchange. Stage 2 added more sophisticated criteria around e-prescribing and patient access. Stage 3, which is where things get complex, introduced the Continuous Improvement Track and the final iteration of objectives that most hospitals had to meet by 2017. After that, the program rebranded entirely. I ran into a specific problem with CME certification during a Stage 3 attestation for a mid-sized hospital. The requirement was that patients could view, download, and transmit their health information within 24 hours of a discharge or encounter. The EHR we were using would generate the summary documents, but the actual file delivery mechanism was asynchronous and prone to queuing delays. On busy discharge days, the 24-hour window would get breached regularly. The compliance team was panicking because we were already behind on other metrics. The workaround wasn't elegant but it worked. I configured a batch process that pre-generated discharge summaries for all patients with a discharge order placed within a 12-hour lookahead window. Instead of waiting for the actual discharge event to trigger document creation, we pulled scheduled discharges from the scheduling module and created draft summaries in advance. When the discharge actually occurred, the system just needed to finalize and timestamp the document rather than generate it from scratch. This cut the average generation time from about six hours down to roughly forty minutes. It wasn't perfect. Occasionally a patient would be discharged early and we'd have a stale summary sitting there. But for attestation purposes, the 24-hour window requirement was consistently met, and that's what the auditors checked.
Workflows in healthcare IT are where most projects quietly fail. Not because the technology is wrong, but because the workflow design assumes a linear process that doesn't exist in practice. I once watched a perfectly designed CCD implementation fail because no one had accounted for the fact that attending physicians routinely co-sign notes from residents hours after the initial encounter. The system generated the CCD at note completion time, which was before the attending review, meaning the final document was missing critical assessment and plan sections that got added during sign-off. The fix was to implement a post-signature CCD generation trigger rather than a post-completion one. That meant rethinking the entire document management pipeline. It also meant training medical staff that their signature action was the actual workflow boundary, not the completion of the note itself. That training piece took longer than the technical change. FHIR is the modern standard you need to understand. Resources like Patient, Observation, MedicationRequest, and Composition form the backbone of contemporary healthcare data exchange. The RESTful API approach is significantly cleaner than HL7 v2's pipe-delimited complexity. If you're building anything new in 2024 and beyond, you should be designing for FHIR capabilities even if your current integration layer still speaks HL7. Most EHR vendors now expose FHIR endpoints alongside their legacy interfaces, though the quality of those FHIR implementations varies wildly between vendors.
Get the Full Details
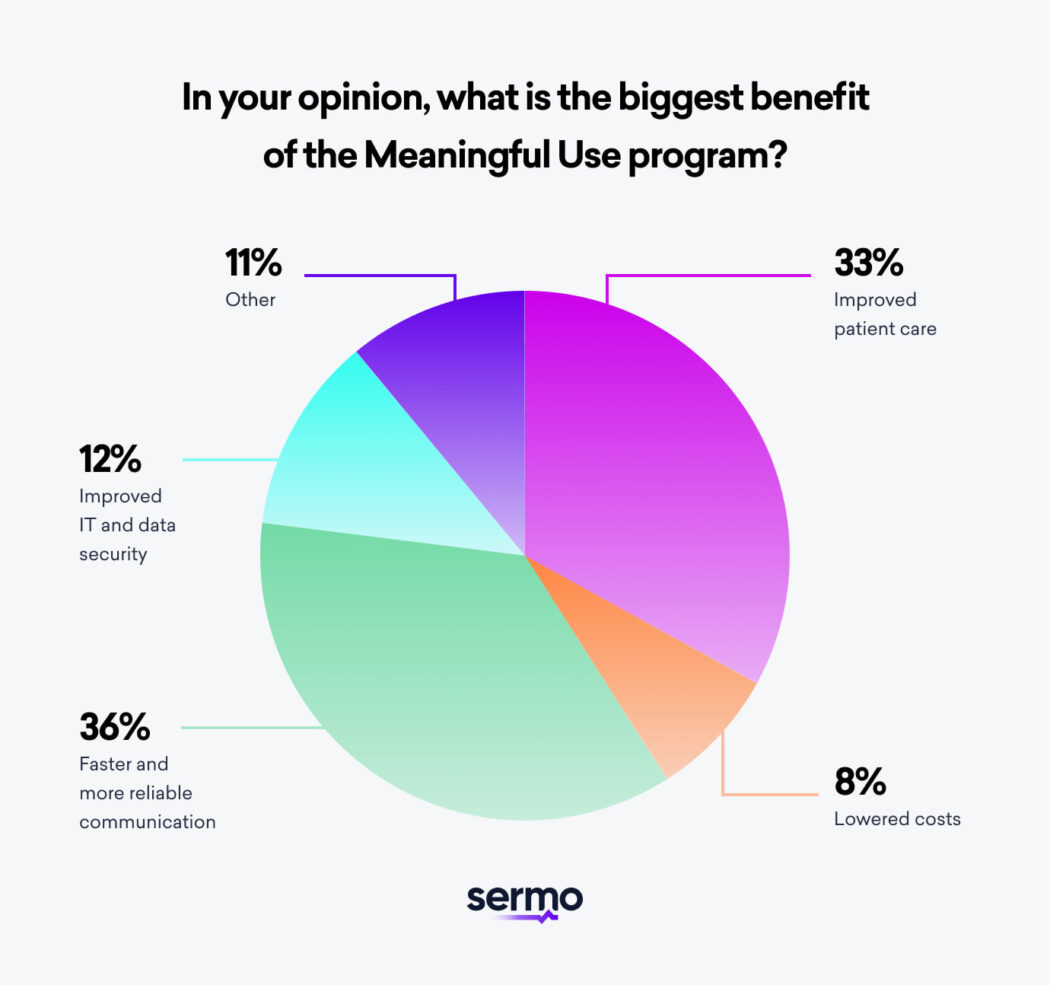
Here's something most beginners miss about Meaningful Use compliance. Passing the attestation is not the same as having a system that works well. I've seen hospitals meet every single objective with minimal clinical impact because they treated the requirements as checkboxes rather than workflow improvements. The data quality for attestation purposes was technically adequate but clinically useless. This matters because once you attest, you're locked into maintaining those capabilities for ongoing reporting periods. Building a weak foundation early creates debt that compounds over years. Another counter-intuitive thing: the security and privacy requirements under Meaningful Use and the subsequent ONC certification criteria are actually more demanding than most people expect. It's not just about having audit controls enabled. You need demonstrated evidence that access controls are functioning correctly across role-based hierarchies, that encryption is in place for data at rest and in transit, and that your business associate agreements cover all the entities touching patient data. During an actual audit, I've seen organizations lose points not because their technology was inadequate but because their documentation trail was incomplete. The difference between certified technology and compliant deployment is often just paper trails. If you're looking to implement standards workflows in your organization, start with an interoperability assessment before you touch any configuration. Map out which data elements matter most to your clinical workflows, which external systems you need to exchange with, and what your current gaps are. Don't start with the technology. Start with the data. The common failure mode is buying into a vendor's integrated solution that looks comprehensive but doesn't actually solve your specific exchange requirements. I've reviewed integration architectures where the vendor claimed full CDA support but the actual implementation only handled demographic data and lab results. The rest was marketing.
Meaningful Use reporting requires careful attention to the measurement period. You can't just pick any twelve-month span. There are specific rules about consecutive months, partial year options for new participants, and the distinction between the calendar year and the federal fiscal year depending on your program. Getting this wrong means you either extend your attestation period unnecessarily or you miss objectives entirely and have to wait a full cycle to retry. The practical reality is that healthcare IT standards work is mostly about translation. You're constantly translating clinical intent into technical requirements and back again. The clinicians speak in workflows and outcomes. The engineers speak in interfaces and data models. The compliance officers speak in objectives and thresholds. Nobody is speaking the same language, and your job is to make sure the translations are accurate at each boundary. When a translation breaks down, you get systems that technically satisfy a requirement but fail to deliver the intended clinical value. I'd recommend starting small if you're new to this space. Pick one interface type, one data standard, and one regulatory requirement. Get deep proficiency there before expanding. The temptation is to try to learn everything at once, and that rarely works. HL7, FHIR, CCD, C-CDA, X12, DICOM, SNOMED, LOINC, ICD-10 — that's a lot of acronyms to absorb simultaneously. You'll burn out faster than you'll become competent.
There's also a community aspect that most people underestimate. The HL7 work groups, the FHIR developer forums, the ONC stakeholder meetings. These aren't just networking opportunities. The real-time discussion about implementation pitfalls and workarounds is where you learn things that don't appear in any official documentation. I solved more problems by reading forum threads from other integration engineers than I did from any certified study guide. The biggest limitation of the current standards ecosystem is that it was built for reporting and compliance first, clinical utility second. This isn't a new problem and it won't be solved by another version number. FHIR improves the developer experience but the underlying incentive structure hasn't fundamentally changed. Organizations comply because they have to, not because the data exchange genuinely improves patient care. Until the economics shift, you're going to keep seeing systems that are certified but not particularly useful in daily clinical practice. If you need a starting point for actual implementation resources, the ONC.gov website has the current Promoting Interoperability program materials, the CDC maintains HL7 implementation guides, and the FHIR documentation at.fhir.org is actually well-maintained compared to most government technical resources. The HL7 International website has work group schedules and draft specifications that you can access if you register. Most of this is free. The paid components are usually just the formal published standards documents themselves.




