The Actual Treatments That Move The Needle On Male Hair Loss
Male pattern hair loss is androgen-driven. That is the starting point. Every viable intervention targets either the hormone pathway or the follicle environment. Everything else is noise, usually wrapped in clever packaging and sold at a premium. I started dealing with this around age twenty-six when my hairline began receding in that classic temple pattern. By twenty-nine it was obvious enough that people at the gym started asking if I was losing weight. I went down every rabbit hole you can imagine before settling on what actually works. The ones that matter are finasteride, minoxidil, and in select cases, procedural interventions. The rest are supplementary at best.
Finasteride And The DHT Problem
Dihydrotestosterone is the hormone shrinking your follicles. Finasteride blocks the 5-alpha-reductase enzyme that converts testosterone into DHT. It is the single most effective pharmaceutical option available and it is backed by decades of peer-reviewed data. The standard dose is one milligram daily, taken orally. You will see a halt in shedding within three to four months and visible regrowth, usually along the crown, over six to twelve months. Results vary, but the majority of men stabilise their loss and some regain meaningful density. The side effects are real and affect roughly two to five percent of users. Libido reduction, erectile dysfunction, and decreased semen volume are the most commonly reported. Most resolve after stopping the medication, but there are documented cases of persistent symptoms that linger even after discontinuation, which the medical community calls post-finasteride syndrome. It is rare, but it exists and anyone claiming it cannot happen is not being honest with you. I ran into a specific issue with finasteride when I combined it with alcohol one weekend after starting treatment. The next morning I had a severe headache and noticeable brain fog that lasted well past midday. That did not happen again after I stopped mixing the two, but it was a concrete example of how individual responses can be unpredictable. If you notice something like this, adjusting your routine or switching to topical finasteride might be worth discussing with a doctor rather than just pushing through it.
Minoxidil: A Different Mechanism
Minoxidil is a vasodilator. It widens blood vessels around the follicle, which increases nutrient delivery and pushes hair follicles into the anagen or growth phase. The standard is five percent solution or foam applied topically twice daily. It works for some men, particularly on the crown, and is often used alongside finasteride because the two mechanisms are complementary rather than overlapping. The downsides are practical. The liquid formulation contains propylene glycol, which causes scalp irritation and flaking for a significant number of users. The foam version avoids that issue for most people but costs more. There is also the initial shed phase, where weakened hairs fall out to make way for new growth. This usually happens between weeks two and eight and makes it look like things are getting worse before they get better. People quit during this window all the time because they do not expect it. I found that applying minoxidil at night and making sure my scalp was completely dry before application reduced the greasy feel and made it less obvious if I had company over. The absorption is still effective whether you apply it in the morning or evening, so consistency matters more than timing.
Get the Full Details

Hair Fall Solution For Men Who Want A Combined Approach
The combination of finasteride and minoxidil is what most clinicians consider the first-line protocol for male pattern baldness. They target different pathways, so using both gives you roughly double the mechanism working against the same problem. Studies show the combination outperforms either treatment alone by a significant margin, especially for crown thinning. The typical timeline is a solid four to six months before you can honestly judge whether it is working for you. This is also where most men hit a wall and stop, usually because they do not see dramatic changes in the first sixty days and assume it is not working. It is not about nothing happening. It is about microscopic changes that take time to become visible. Committing to at least six months of consistent use before evaluation is the minimum reasonable standard.
Low-Level Laser Therapy And Adjuncts
Low-level laser therapy devices, often called LLLT or red light therapy, use wavelengths between 650 and 670 nanometers to stimulate cellular activity in the follicle. These are available as caps, combs, and in-clinic units. The evidence is moderate but real. It is not a standalone miracle, but it works well as an add-on to finasteride and minoxidil. Sessions typically run twenty to thirty minutes, three times per week. The cap devices are expensive, ranging from four hundred to over a thousand dollars, and the results are incremental at best. If you have limited funds, putting them toward finasteride or minoxidil first makes more sense than buying a laser cap as your primary intervention.
Procedural Options When Medication Is Not Enough
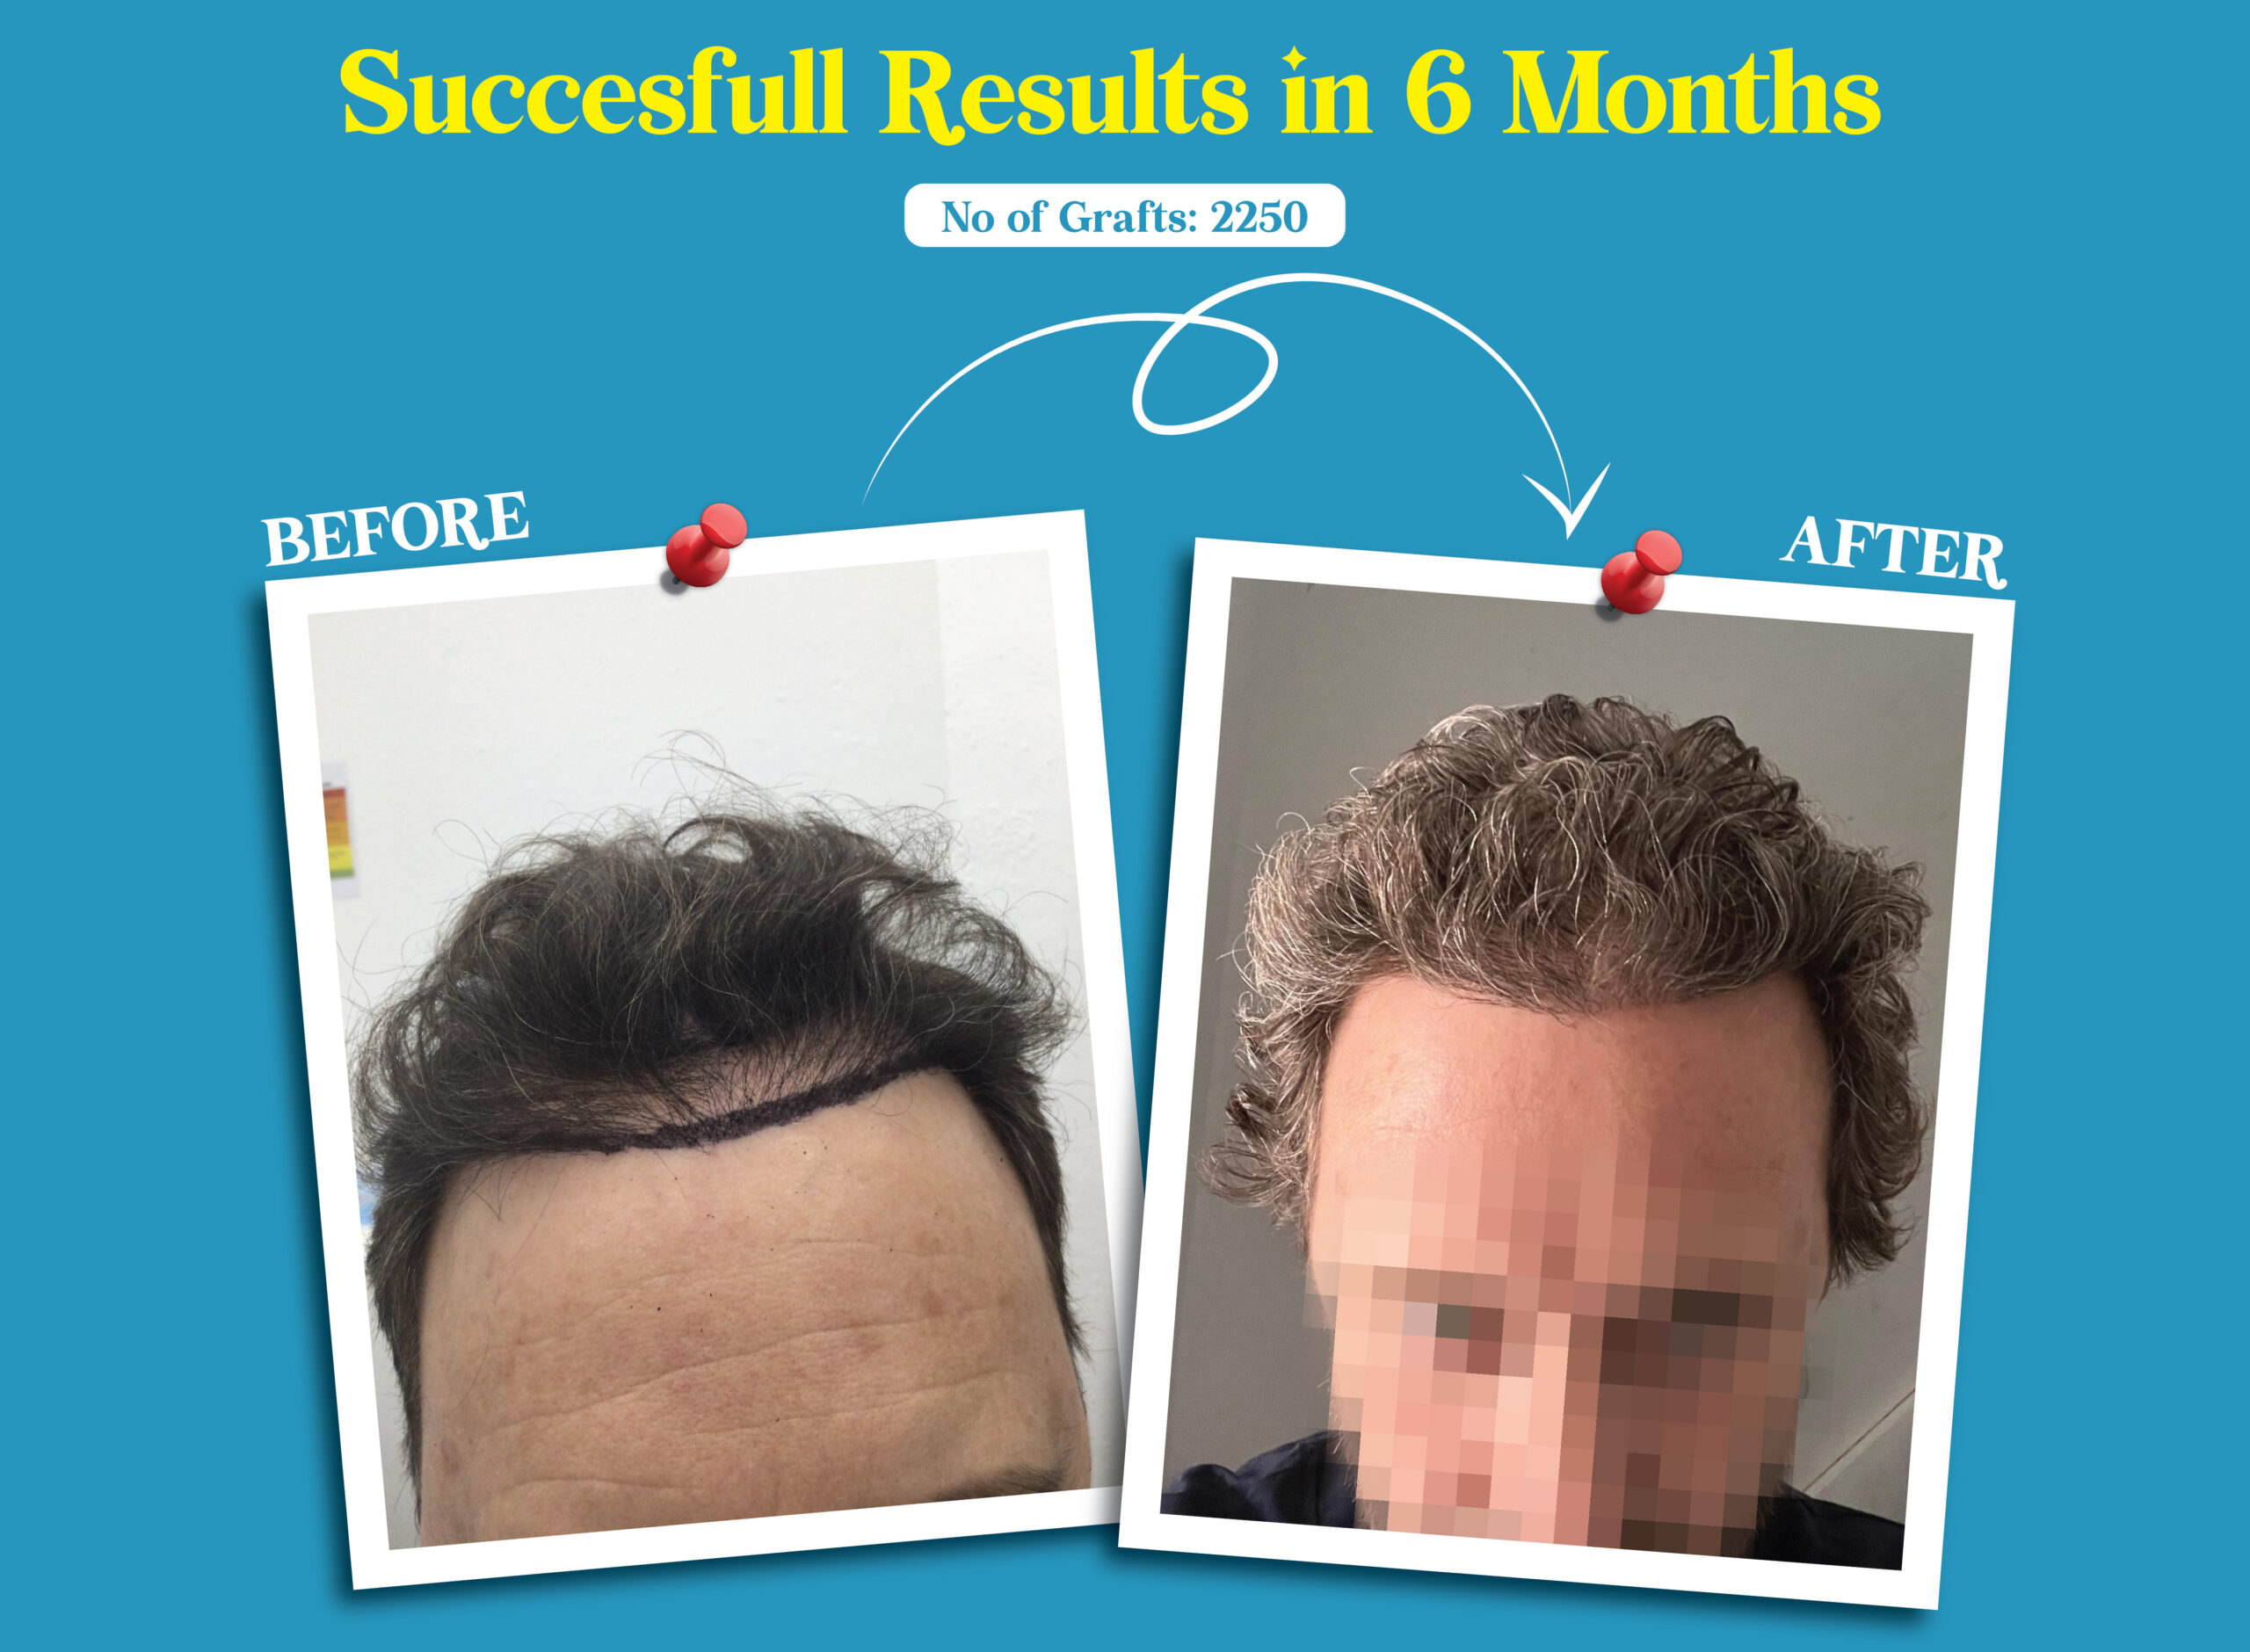
PRP, or platelet-rich plasma therapy, involves drawing your blood, centrifuging it to concentrate the platelets, and injecting the plasma into your scalp. The growth factors in platelets are thought to stimulate dormant follicles and prolong the growth phase. It requires ongoing sessions, usually every three to six months after an initial series, and costs between four hundred and eight hundred dollars per session. Results are variable and it works better for early-stage thinning than for areas that are already slick bald. Hair transplantation is the permanent structural solution. Follicular unit extraction or strip harvesting moves resistant follicles from the back and sides of your scalp to thinning areas. This is not a cosmetic procedure you should rush into. A skilled surgeon can give you a natural result that ages with you, while a bad one can leave you looking like a doll's house with patchy, unnatural hairlines that will become increasingly obvious as your native hair continues to thin underneath the grafts. I strongly recommend consulting with at least three different clinics before committing, and watching actual unedited before-and-after videos from those specific surgeons rather than relying on promotional imagery.

What Does Not Work And Why People Keep Buying It Anyway
Caffeine shampoos, biotin supplements, rosemary oil, and scalp massagers are everywhere in the men's hair loss market. The science behind them is thin. Rosemary oil has one small study comparing it to two percent minoxidil after four months, but the study was underpowered and the results were modest at best. Biotin deficiency causing hair loss is extremely rare in people without an underlying medical condition. Shampoos sit on your scalp for ninety seconds and then get rinsed off, which makes them a very inefficient delivery method for anything. These products are not dangerous in most cases, but they create a false sense of action. People feel like they are doing something productive while the underlying DHT-driven process continues unchecked underneath. The opportunity cost of spending money and attention on these instead of finasteride or minoxidil is real.
The Brutal Parts That Nobody Puts In Marketing Materials
If you stop finasteride, you lose the DHT blockade. Hair loss resumes and any gains you made over the previous months will gradually shed over the following six to twelve months. There is no way to cycle it on and off and keep the results. You take it continuously or you accept that you are balding. Minoxidil has the same requirement. Stops applying it and the new hairs fall out within a few months. This is why these treatments are better described as lifelong commitments rather than cures. Genetics set the ceiling. Finasteride can slow or partially reverse loss in many men, but it cannot resurrect follicles that have been dead and scarred over for years. Once an area is completely smooth and shiny with no visible miniaturised hairs, medication alone will not bring it back. That is when transplantation or acceptance become the only real options.
A Practical Starting Sequence
If you are reading this and you are actively losing hair, here is the order most clinicians would suggest: get a proper diagnosis from a dermatologist to confirm it is androgenetic alopecia and not something else like thyroid dysfunction or alopecia areata. Then start finasteride if you are a candidate, add five percent minoxidil to the routine, and give it six months of consistent daily use before judging results. Consider LLLT or PRP only after the basics are in place and you still want to push further. Transplantation is a separate decision that should come after you have stabilised your loss medically. I wish there were a simpler answer, but the truth is straightforward and not particularly exciting. Consistency with proven treatments beats novelty products every time, and the earlier you start the better your outcomes tend to be.



