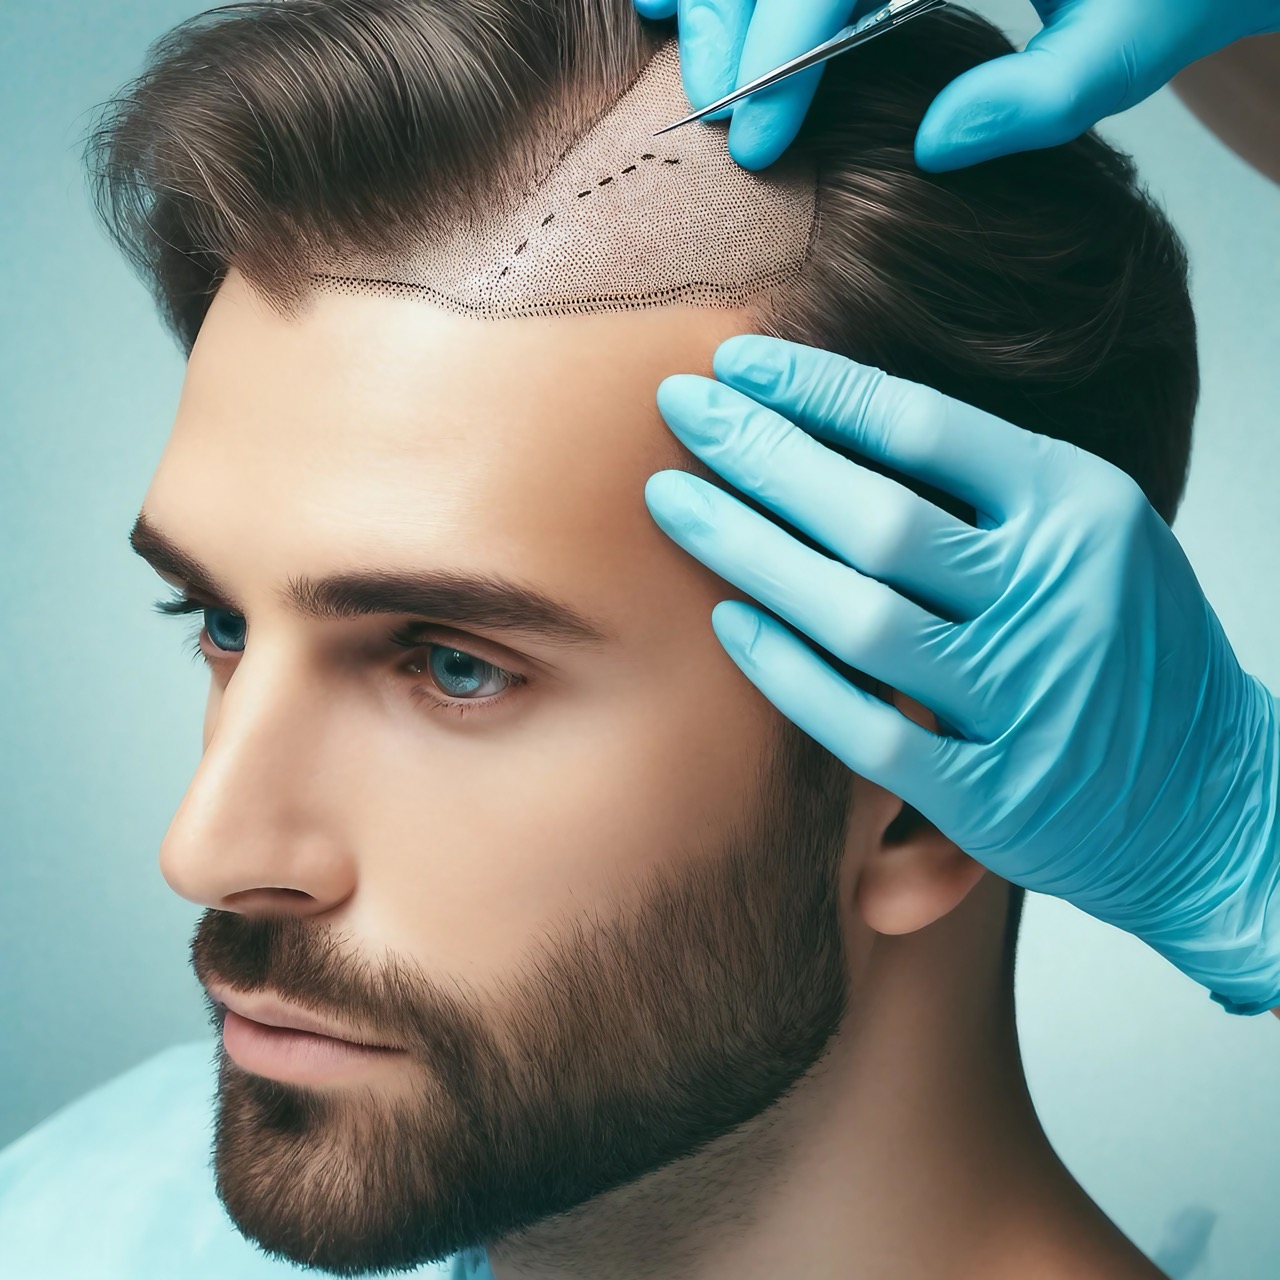
What Actually Changed in Hair Restoration Last Few Years
The biggest shift isn't some single breakthrough. It's the convergence of better imaging, refined extraction techniques, and longer graft survival data that actually matches clinical outcomes to what patients see six months out. Most clinics still market the same FUE and FUT labels they used five years ago. The real updates are buried in the details—motor torque settings, graft holding solution composition, and the move toward shorter, denser harvesting sessions that reduce ex vivo time. I want to talk about the method itself before defining anything. Here's how a modern FUE session runs on a well-tuned clinic floor. The patient is prepped with local anesthesia using a 30-gauge needle in a linear infiltration pattern along the donor zone, usually the occipital scalp. This takes about 10 to 15 minutes for a standard 2,000-graft case. Then the surgeon selects the punch size based on graft type and hair caliber. Modern setups commonly use punches between 0.7mm and 0.9mm for single-hair follicular units, and up to 1.0mm for double or triple-hair grafts. Motor speed is typically set between 800 and 1,200 RPM. Higher speeds don't mean better results—they increase transection risk when the operator hesitates or when the angulation isn't precise.
Extraction uses either a robotic assist system or a manual oscillating device. The Artas system, which is one of the most widely deployed robotic platforms, uses high-resolution imaging to map follicular units before the robot even touches the scalp. It evaluates angle, depth, and direction for each target unit, then marks them. The actual extraction still depends heavily on the technician running the machine. You can have a perfectly programmed map and still lose grafts if the hand-off from automated targeting to manual extraction is sloppy. I've seen this firsthand in places where the same operator switched machines and saw their transection rate jump from under 5% to over 15% in a single week. After extraction, grafts are kept in a holding solution. The standard is cold saline mixed with platelet-rich plasma or specialized media like Hypromellose-based solutions. The goal is to keep the bulb cells alive while they're outside the body. Average ex vivo time should stay under 8 hours for optimal survival. Beyond that, you're just gambling with each graft. Most high-volume clinics complete their extraction and implantation within 4 to 6 hours total, which keeps graft viability solid. Implantation is where the real skill difference shows up. The choice between forceps, Implanter pens (Choi instruments), and manual slits changes everything about graft handling time and trauma. I prefer the Choi pen for single-hair grafts in the hairline because it reduces handle time to nearly zero—you load the graft and place it in one motion. But for the mid-scalp and crown where density matters more than natural line placement, many surgeons still use forceps for better control over angulation and depth. Both methods work. The difference is in the outcomes you get after a year.
I ran into a specific problem with a patient who had previously had a failed strip procedure leaving a wide linear scar. His donor area was compromised with significant scar tissue and reduced blood flow in that zone. Standard FUE extraction would've been a disaster there because the scar tissue makes punch penetration unpredictable and graft retrieval unreliable. I switched to a DHI-style approach using a 0.7mm Choi pen with very shallow insertion angles, only harvesting from the healthy tissue just below the scar line where the scalp still had normal mobility. I also lowered the motor torque significantly and used a slower oscillation pattern. That patient ended up with around 1,400 grafts from a much smaller usable zone than usual, but the survival rate was high because I wasn't fighting dead tissue. It took longer, obviously—about four hours for that zone alone—but it was the only realistic way to proceed.
Get the Full Details

Defining What Each Method Actually Is
Let me clarify the terminology since marketing departments have deliberately muddied these definitions. FUE stands for Follicular Unit Extraction. It's a method where individual follicular units are removed one at a time using a small circular punch. The donor area heals with tiny dot scars that are virtually invisible to the naked eye at normal viewing distances. Recovery is faster than FUT, usually 5 to 7 days for surface healing, and patients can return to light activity within 3 to 4 days. The downside is that it removes grafts from a larger surface area over time, which can thin the donor zone if too many sessions are done without adequate spacing. FUT, or Follicular Unit Transplantation, involves removing a strip of scalp from the donor area, then dissecting it under microscopes into individual grafts. The scar is linear and permanent, though it's usually hidden beneath surrounding hair if the patient keeps it at a reasonable length. FUT allows for higher graft yields in a single session because the entire strip comes out at once, but it requires a longer recovery—10 to 14 days for suture removal, and the scar can widen over time depending on individual healing characteristics. It's not obsolete. It's just been unfairly demonized by clinics that only do FUE and want to avoid the conversation about linear scarring.
DHI, or Direct Hair Implantation, is technically a subset of FUE but uses a different delivery tool. Instead of creating recipient sites first and then placing grafts, the surgeon loads each graft into a Choi pen and implants it directly. This eliminates the need for pre-made incisions and can reduce graft handling time significantly. The trade-off is that it requires more manual dexterity per graft, which slows the overall pace. A skilled surgeon can place maybe 800 to 1,200 grafts per hour with a Choi pen versus 1,500 to 2,000+ with forceps and pre-made slits, depending on complexity. PRP, or Platelet-Rich Plasma, is often bundled into these procedures as an add-on. Blood is drawn, centrifuged, and the concentrated platelet fraction is injected into the scalp before or after graft placement. The science is mixed. Some studies show modest improvement in graft survival and early growth speed. Others show no statistically significant difference compared to sham injections. It's not a scam, but it's not a miracle either. Expect maybe a 10 to 15% improvement in early hair density at three months if it works for your biology. Don't expect it to make a borderline case viable.
What People Miss About These Procedures
Here's something most guides won't tell you: the number of grafts you get is almost never the limiting factor. The limiting factor is how those grafts are distributed across the recipient zone. I've seen patients who got 4,000 grafts placed uniformly across a large bald area and ended up looking no better than someone who got 2,000 grafts placed strategically in the right zones. Hairline design, crown density mapping, and temporal point preservation matter far more than raw count. A good surgeon will tell you 2,500 perfectly placed grafts will outperform 4,000 poorly distributed ones every time. Another thing: the age of the patient matters more than the stage of baldness. A 28-year-old with Norwood 3 pattern loss has a very different prognosis than a 45-year-old with the same pattern, simply because the younger patient's future hair loss trajectory is unpredictable. Good surgeons limit the first session to what addresses the current visible baldness plus a small buffer for expected progression. They don't max out the donor zone on day one because that leaves nothing for when the loss continues. This is where I see the most damage—clinics that extract aggressively upfront and then have nothing left when the patient returns five years later with expanded loss. There's also the question of hair caliber and texture. Straight, coarse black hair gives the best cosmetic coverage per graft because each strand is highly visible. Fine, wavy, or blonde hair requires significantly more grafts to achieve the same visual density. A patient with fine blonde hair might need 3,500 grafts where a patient with thick dark hair would only need 2,000 for a similar appearance. Surgeons who don't account for this difference end up underestimating what's actually required.

When These Methods Don't Work
Let's be straightforward about failure modes. FUE and FUT both require an adequate donor supply. If you're Norwood 6 or 7 with significant thinning in the occipital region, you may simply not have enough viable grafts to create meaningful coverage. No technology changes that basic math. In these cases, the only realistic options are a very limited low-hairline restoration, scar camouflage techniques, or accepting that you'll remain partially bald in the crown area. Unrealistic expectations are another failure mode, and they're the most common one I encounter. Patients who expect a full head of hair from a single session, or who think PRP alone can regrow a bald crown, will be disappointed regardless of surgical skill. Hair restoration is about redistribution, not regeneration. You're moving existing hair from a permanent zone to a thinning zone. You're not creating new follicles. Any clinic claiming otherwise is selling something that doesn't exist. There's also a specific limitation with automated robotic systems that the marketing material rarely mentions. The Artas and similar robots struggle with patients who have significant scalp laxity issues or unusual follicular angulation patterns. They work best on standard cases with uniform hair direction. When the anatomy deviates from the norm—which happens more often than you'd think with people who've had previous surgeries—the robot's accuracy drops noticeably. In those cases, a skilled human hand with manual extraction consistently outperforms the machine. I've had patients bring me scans from other clinics where the robot had transected 20% or more of their grafts simply because the scalp topology was outside the system's optimal parameters.
If you're considering any of these procedures, the single most important decision isn't which technology you choose. It's which surgeon you choose. The technology is a tool. The outcome depends entirely on who's holding it and how much experience they have dealing with the edge cases that textbooks don't cover. Look at before-and-after photos from actual patients, not the rendered examples on the clinic website. Ask about their transection rates, their average graft survival at one year, and what they do when a case doesn't go as planned. Those answers tell you more than any brochure about the latest FDA clearance or patent filing.