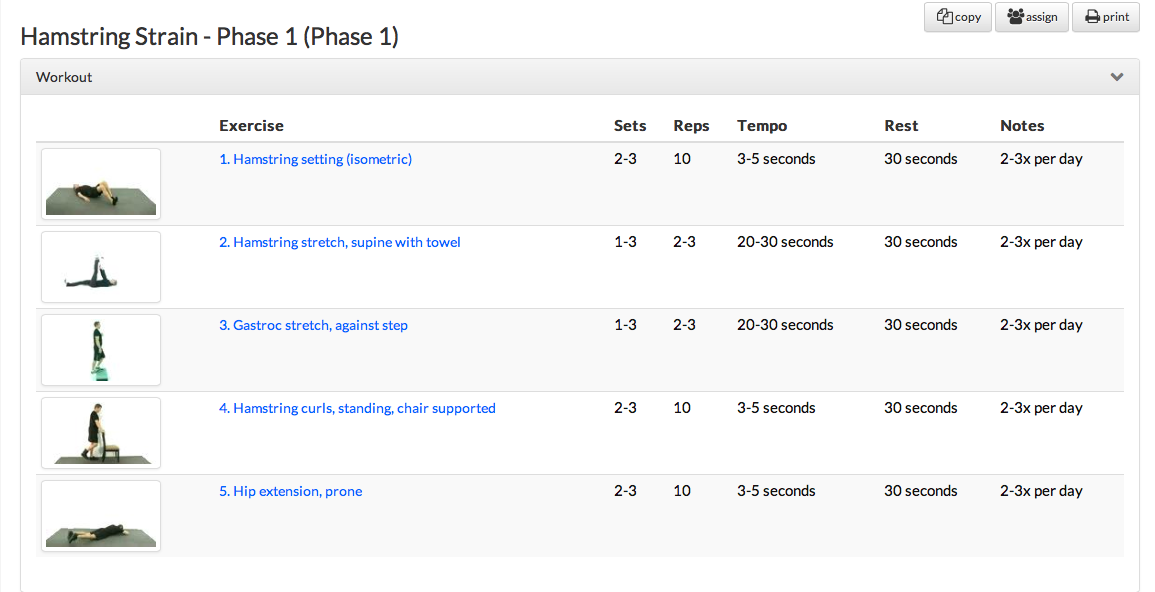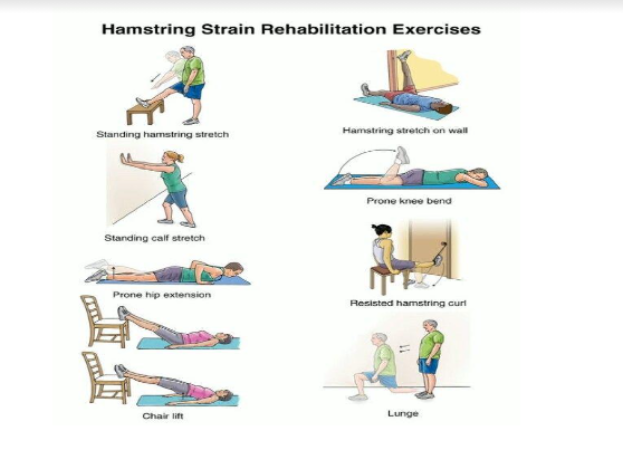
Hamstring Strain Physical Therapy Protocol
I've been running hamstring rehab for the better part of fifteen years, mostly sports physio, some orthopedic work, and a ridiculous amount of people who thought they could just bounce back after a sprint workout. The protocol I use isn't revolutionary, but it keeps people healthy and getting them back to sport without the recurring strains that make everyone miserable. Here's what the framework actually looks like when you're not trying to sell it to anyone. You split it into phases, and each phase has clear criteria for moving forward. I used to rush people through, which was stupid, and my worst offender was a collegiate soccer player who came back at week three because she couldn't miss another tournament. She re-injured it within two days, worse than before, Grade 2 instead of Grade 1. Cost me trust and cost her time I couldn't give back. Phase one runs from injury through the first week or so. The priority is pain control and protecting the tissue. You don't push ROM much here, you just keep the knee from going fully straight if it hurts, and you let the inflammation settle. Ice helps for the first forty-eight hours, compression, maybe some gentle cycling on a recumbent bike at zero resistance. I don't make people do isometrics until pain drops below three out of ten. Early strengthening can actually irritate things more than help if the tissue isn't ready.
Phase two starts when the person can walk normally without a limp, and the hamstring tolerates light stretching without reactive pain. This is where most protocols fall apart because clinicians and athletes get impatient. You introduce isometric holds first, then progressive loading through partial ranges. Nordic curls are gold standard here, but only in the early part of the curve where it feels manageable, not the deep stretch position where the muscle is under maximum length and tension. I'll usually have people do three sets of thirty-second holds at sixty percent effort, building up over ten to fourteen days. If pain spikes during or after, you backed off too far and you go back a step.
Strength and Length Work
Once isometrics are dialed in, you move into eccentric loading and then full range work. The evidence base favors Nordic hamstring exercises heavily, and I'll say this without hedging: most people do them wrong and blame the exercise. They arch their lower back, they drop too fast, they use momentum. The actual cue is simple: brace your core, keep your hips neutral, lower yourself slowly, catch yourself with your hands, and push back up. That's it. Three sets of five to eight reps, twice a day if you can tolerate it. The soreness after is normal; sharp pain during is not. Running mechanics come back in phase three, usually around week four or five for Grade 1 strains, sometimes later for Grade 2. You don't sprint yet. You jog, you build volume, you watch for compensatory patterns. I have a go-to test: single-leg deadlift at bodyweight. If the person can't hold it for five seconds per leg without their trunk leaning or knee collapsing inward, they're not ready for sprinting. The hamstring isn't just a knee flexor; it's a hip extensor too, and rehab programs that ignore that produce the exact same injuries I saw twenty years ago when we only worked biceps curls and leg curls.
Get the Full Details

The Return-to-Sport Decision
This is where I see the most variance in practice. You need objective criteria, not just someone saying they feel good. My threshold list is basic: full pain-free ROM, strength at least ninety percent of the uninjured side on isokinetic testing or a good manual muscle test, successful completion of sport-specific drills without pain, and no swelling after training. If any of those are missing, you don't send them back. Period. I once had a rugby player who passed every test and still reinjured on his first game. Turns out he'd been hiding pain for two weeks because he didn't want to lose his spot. The protocols exist to prevent exactly this. You document everything. You communicate with the athlete. You set expectations clearly.
Common Pitfalls
Stretching too early is the biggest mistake I see. Hamstring strains often involve the proximal tendon near the sit bone, and aggressive stretching in the first two weeks disrupts healing. People feel tight afterward and assume they need more stretch, which is backwards. The tightness comes from protective muscle guarding, not actual shortening. You address that by letting the tissue heal first, then gradually loading it through range. The second common error is skipping eccentric work. A lot of clinics do cycle and elliptical for weeks and call it rehab. That's maintenance, not rehabilitation. Eccentric strength at length is what actually prevents reinjury, and the literature supports it pretty strongly. If you want numbers, Nordic hamstring exercises reduce reinjury risk by about forty to fifty percent in athletes who complete a proper program.
What Doesn't Work
Cross-friction massage over the injury site in the first two weeks. It makes things worse. I know clinicians who swear by it, and they're usually working on chronic cases, not acute strains. For acute tears, you're disrupting the clot and the new tissue formation. Ultrasound therapy has marginal evidence at best; don't rely on it as a primary treatment. Corticosteroid injections are a terrible idea for hamstring strains because they weaken the tissue and increase re-rupture risk. Just don't do it. Pregnancy doesn't change much here. I've treated pregnant athletes with the same phased approach, just with modifications for balance and comfort. The tissue heals the same way. Gravity and center of mass shift aren't factors in hamstring strain mechanics.

A Real Case
Last year I had a trail runner, forty-two, who tore his right hamstring about four centimeters above the knee during a steep descent. Grade 2, confirmed on MRI. He came to me because he'd been told to rest for two weeks and then start stretching. He'd been in pain since day one because he'd pushed through it, thinking tougher was better. By the time he saw me, he had significant scar tissue forming and he couldn't extend his knee past forty-five degrees without sharp pain. We stripped the protocol back to phase one and stayed there for eleven days. I used gentle oscillatory mobilizations around the knee, not directly on the tear, and introduced pain-free isometrics at twenty percent effort. Walking was fine by day nine. Cycling by day twelve. We missed the usual fourteen-day mark for isometrics because his pain was higher, and that's fine. The criteria drive the protocol, not the calendar. By week four he was doing single-leg Romanian deadlifts with bodyweight, no pain. Week five introduced Nordic negatives at partial range. Week six he was jogging on soft ground, alternating with pool running. Week eight he was back to trail running, full volume, no restrictions. He hasn't had another strain in fourteen months, which is the actual measure of success, not just whether he passed a test.
Documentation and Communication
You need to write down what you're doing and why. Not for insurance, though that helps sometimes, but because the next clinician, the coach, and the athlete all need to know where they are in the process. A simple timeline with phase markers, pain levels, and functional milestones works. I use a one-page template: injury date, grade, location, phase one start date, criteria met for each phase, and return-to-sport date. If something goes wrong, you can look back and see where the decision points were.
When to Refer Out
Grade 3 strains, complete tears, proximal tendon avulsions, or injuries that aren't improving after two weeks of appropriate care. Sometimes you're dealing with something that isn't a hamstring strain at all, like a lumbar radiculopathy or a referred pain from the sacroiliac joint. If the history doesn't match the mechanism, or the exam findings are inconsistent, you get imaging and a second opinion. I had a case once where the patient kept failing rehab because it was actually a piriformis syndrome mimicking hamstring pain. Took six weeks to figure out.

The Bottom Line
Hamstring strain recovery follows a predictable timeline if you respect the biology. Early protection, progressive loading, eccentric work, sport-specific reintegration. The people who rush phases or skip criteria are the ones coming back with weaker tissue and higher reinjury rates. It's not complicated, but it does require patience and honest assessment. The protocol works when you actually follow it.