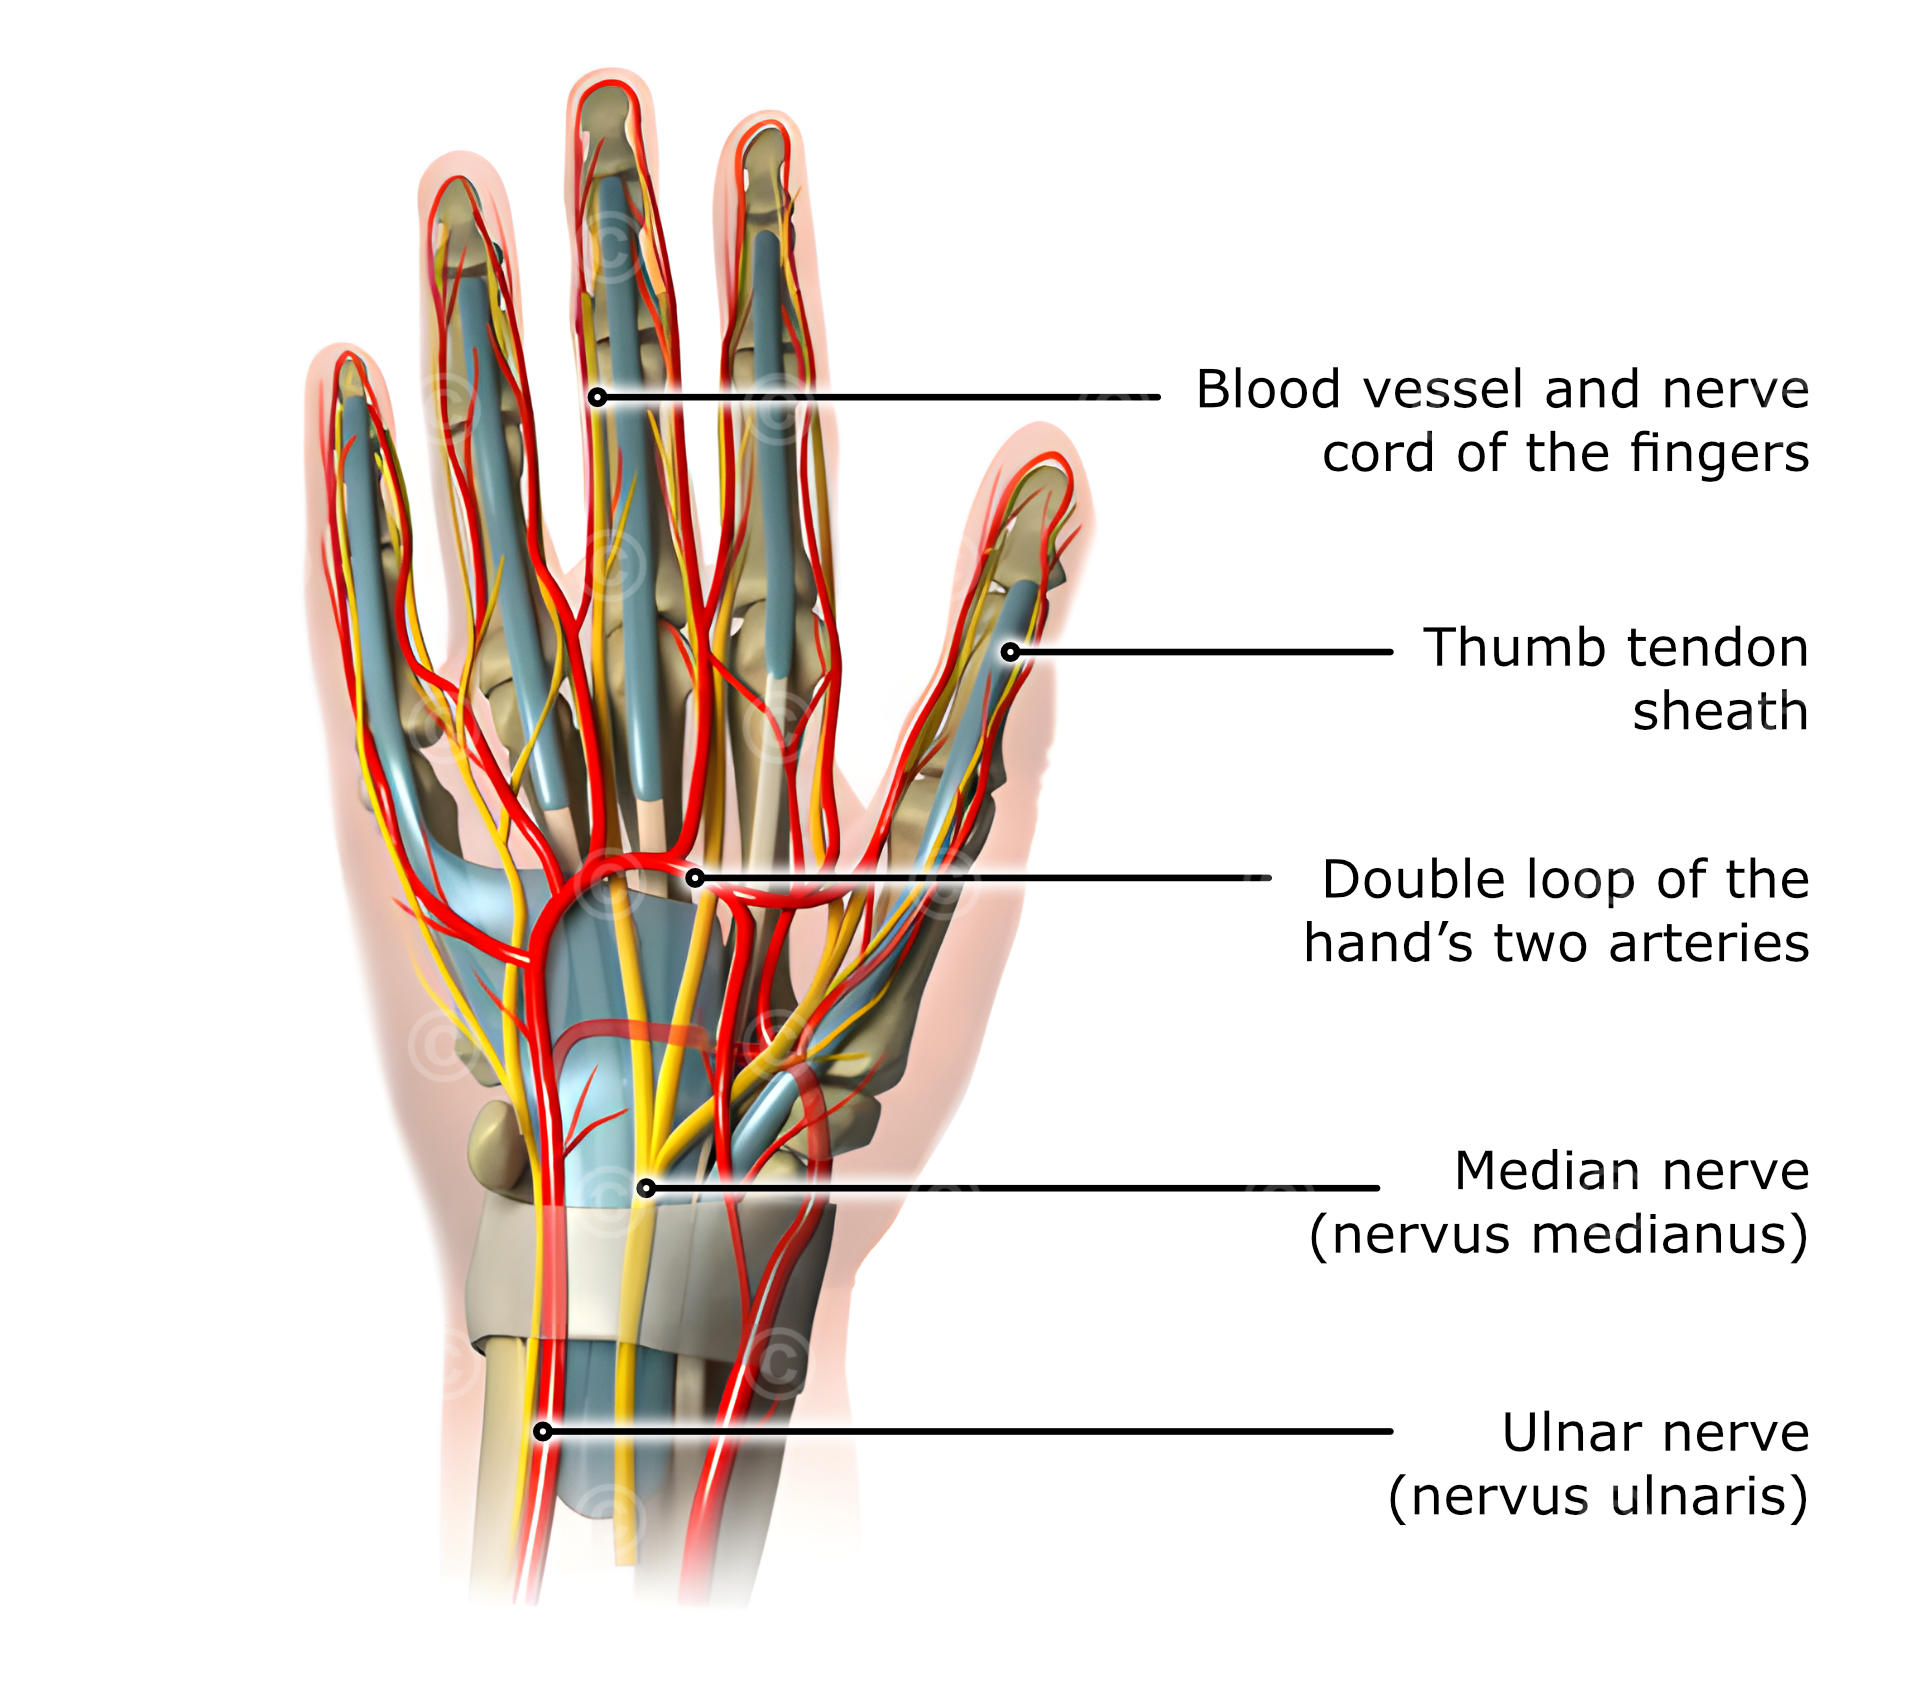
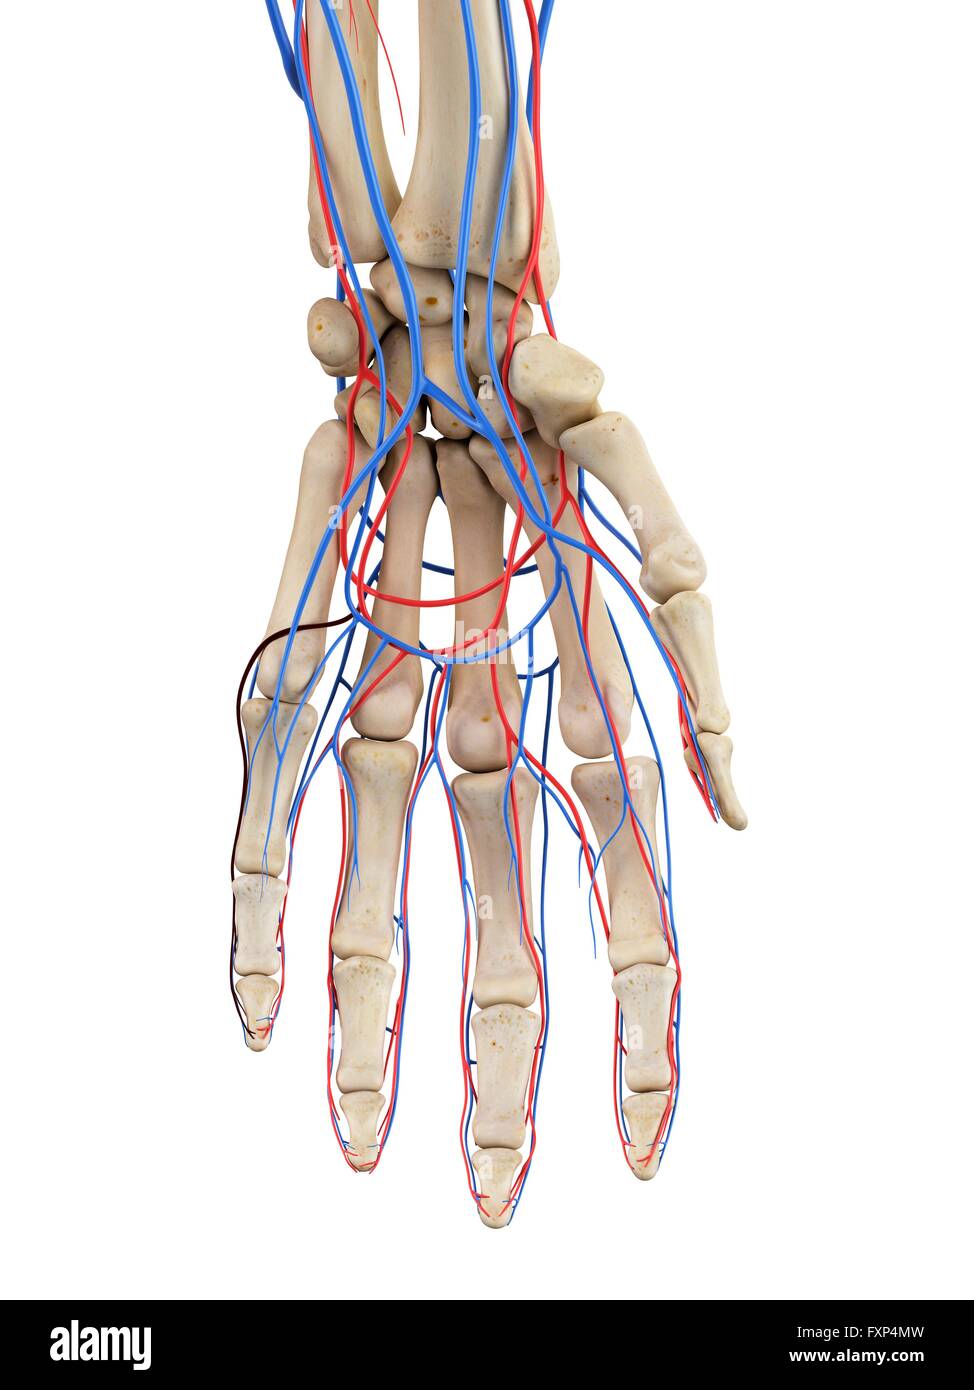
Reading the vascular map of a hand isn't something you pick up from a textbook diagram and immediately apply.
I spent three years working in a hand surgery assisting unit before I could actually anticipate where a vessel would be under the skin without scanning ultrasound. The difference between knowing the labels and knowing the terrain is enormous, and most people skip straight to the labels because that is what every exam tests. But when you are dealing with Hand Anatomy Veins And Arteries in a real clinical or procedural setting, the labels almost never line up with what you find. The first thing I learned the hard way was that arterial trees in the hand are aggressively redundant. The classic teaching says the radial artery forms the superficial palmar arch and the ulnar artery forms the deep palmar arch, but that pattern shows up in roughly forty percent of cadavers. The rest of the time the arches flip, or both get contributions from one vessel, or there is an accessory branch coming from the anterior interosseous that nobody told you about. If you are doing anything that requires predicting where blood is going—vein access, arterial line placement, surgical exposure—you need to work with the assumption that your mental map might be wrong.
What Actually Determines Vein Visibility
Veins in the hand sit in two distinct compartments: the dorsal venous network and the deep palmar system. The dorsal network is what you see when you flip a hand over, and it is deceptively complex. The cephalic vein begins at the radial side of that network and tracks up the lateral forearm. The basilic vein starts at the ulnar side and does the same on the other end. Between them you have the median antebrachial vein, which often splits into an H shape near the elbow and sends branches to both systems. That H configuration matters because if you are drawing blood from someone whose median vein has split unusually high, you might actually be accessing two separate vessels at once and confusing yourself about where the sample is coming from. I encountered this exact problem with a patient who had recurrent hematoma formation at routine phlebotomy sites. Her median vein bifurcated about eight centimeters above the antecubital fossa, which is higher than standard texts describe. Every time I aimed for what looked like a single vein, I was actually sticking across both branches and creating a channel between them. The workaround was simple but counter to everything I had been trained on: I stopped using the raised vein as my landmark and instead tracked the vessel ultrasound-guided from proximal to distal, confirming it was a single lumen before committing the needle. That one change dropped her complication rate from roughly one in three attempts to zero over six months.
Arterial Supply Patterns That Cause Problems
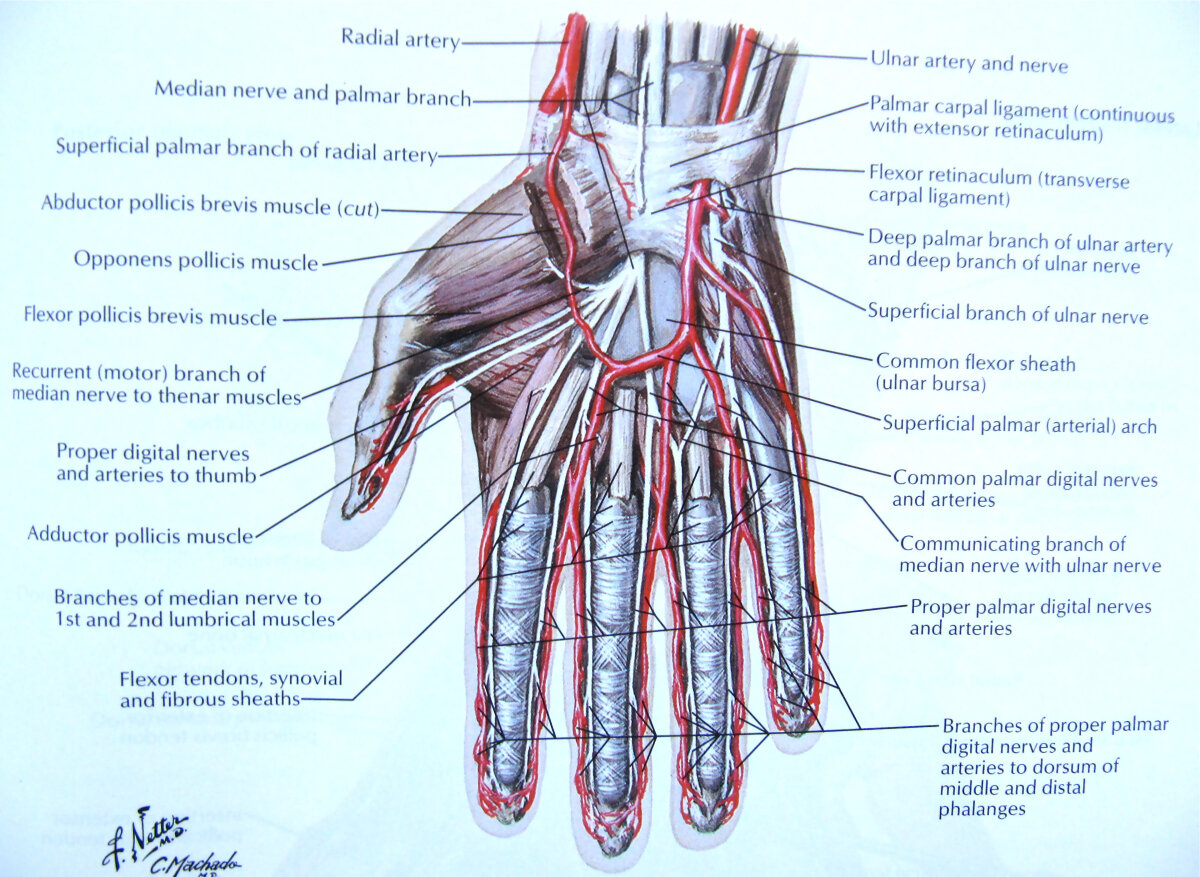
The radial artery runs along the lateral forearm, passes behind the anatomical snuffbox, and contributes to the deep palmar arch. The ulnar artery runs along the medial side and contributes to the superficial palmar arch. This is the version you will find on every anatomy exam and in every first-year textbook. The version you find in actual hands is messier. A high-riding origin of the radial artery, where it branches off the brachial artery two or three centimeters above the elbow instead of at the normal bifurcation level, shows up in about twelve percent of limbs. When this happens, the radial pulse at the wrist can be surprisingly weak or absent even though perfusion to the hand is completely normal. I once spent twenty minutes searching for a radial pulse before an attending stopped me and pointed out the patient's radial artery had originated proximally. The ulnar pulse was bounding. Checking the Allen test would have told us everything we needed to know in about thirty seconds instead of twenty minutes of fruitless palpation. The superficial palmar arch is more variable than the deep arch. It is formed primarily by the ulnar artery in most people, but the princeps pollicis and radialis indicis arteries can supply it directly from the radial system, creating a dual-source arrangement that changes collateral flow patterns significantly. If you are ligating or grafting in the hand region, this variability determines whether your proximal clamp will actually stop flow through the arch or whether collateral channels will keep the distal tissues perfused regardless.
Get the Full Details
Practical Implications for Procedural Work
When you are doing peripheral IV placement or arterial blood gas sampling in the hand region, the dorsal veins are your primary target. They are superficial, relatively mobile, and easier to stabilize than anything in the palmar creases. The palmar veins are deeper and surrounded by critical nerve and tendon structures, which is why they are largely avoided for routine access. The risk of hitting the superficial branch of the ulnar nerve or the palmar cutaneous branch of the median nerve in that region is real and not worth taking for a standard blood draw. I learned this from a colleague who attempted a palmar vein stick on a trauma patient with poor peripheral access. He nicked a branch of the ulnar nerve and the patient developed chronic neuropathic pain in the small finger that lasted four months despite conservative management. The lesson was straightforward: when the dorsal veins are usable, use them. When they are collapsed or inaccessible, escalate to ultrasound-guided access rather than digging into the palmar compartment. The extra time—about three to five minutes for probe positioning—is negligible compared to the downside of iatrogenic nerve injury. Temperature also dramatically affects vessel visibility and palpability. Cold hands constrict superficial veins within seconds, making them disappear from view even in patients who normally have excellent access. Warm the extremity with a warm pack for five to seven minutes before attempting stick, and visibility typically improves by two to three vessel diameters. This is not a minor consideration for patients who are already anxious about needles because the combination of cold and anxiety creates the worst possible conditions for successful access.
When Standard Anatomy Completely Fails You
The biggest limitation of relying on textbook hand vascular anatomy is that it describes neither pathology nor variation well. Diabetic patients with medial calcinosis can have arteries that feel like rigid wires regardless of body habitus, making pulse assessment through palpation alone nearly useless. Patients with previous trauma or surgery in the forearm can have segmental occlusions that redirect flow through collateral pathways, creating a situation where a vessel appears patent on imaging but carries minimal actual flow. I worked with a patient whose radial artery was occluded from the mid-forearm distally due to prior catheterization, but whose hand was perfused entirely through ulnar-to-radial collateral channels via the deep palmar arch. Standard pulse checks at the wrist showed no radial signal, which would have led a less careful examiner to conclude the hand was ischemic. The hand was warm, cap refill was under two seconds, and grip strength was normal. Doppler ultrasound confirmed the collateral flow pattern and saved us from an unnecessary vascular consultation that would have recommended angiography and likely surgical intervention for a circulation that was adequate without any help. The takeaway here is that pulse assessment, imaging, and clinical examination each have blind spots, and relying on any single method gives you an incomplete picture. Combining at least two approaches—palpation plus Doppler, or clinical exam plus ultrasound—catches the variations and pathologies that solo methods consistently miss. This is not a sophisticated recommendation. It is the minimum threshold for working safely with hand vascular anatomy in any clinical setting where the consequences of getting it wrong are significant.
The Core Structures You Need to Know By Heart
The cephalic vein, basilic vein, and median antebrachial vein form the superficial drainage system on the dorsal and palmar aspects. The radial artery and ulnar artery form the primary arterial inflow, with the superficial and deep palmar arches providing collateral distribution to the digits. The digital arteries run along the lateral aspects of each finger, which is why puncture should always be attempted from the midline or palmar aspect rather than the side—lateral sticks risk dividing the digital artery and compromising flow to the distal phalanx. I have seen this mistake repeatedly. A resident attempted a lateral digital stick on a construction worker with a infected wound on the radial side of the index finger, assuming the digital artery would be easy to access from that direction. He divided the proper digital artery on the radial aspect, and the patient required microsurgical repair three hours later. The artery had been accessible from the palmar side the entire time, but the infection and swelling made that approach less obvious. Palmar sticks are harder to visualize but significantly safer when you are working in an infected field where tissue planes are already distorted. Understanding Hand Anatomy Veins And Arteries at this level—beyond labels, into actual variability and clinical consequence—is what separates someone who can pass an anatomy exam from someone who can safely work in a region where the margins for error are measured in millimeters and the consequences are measured in function lost.