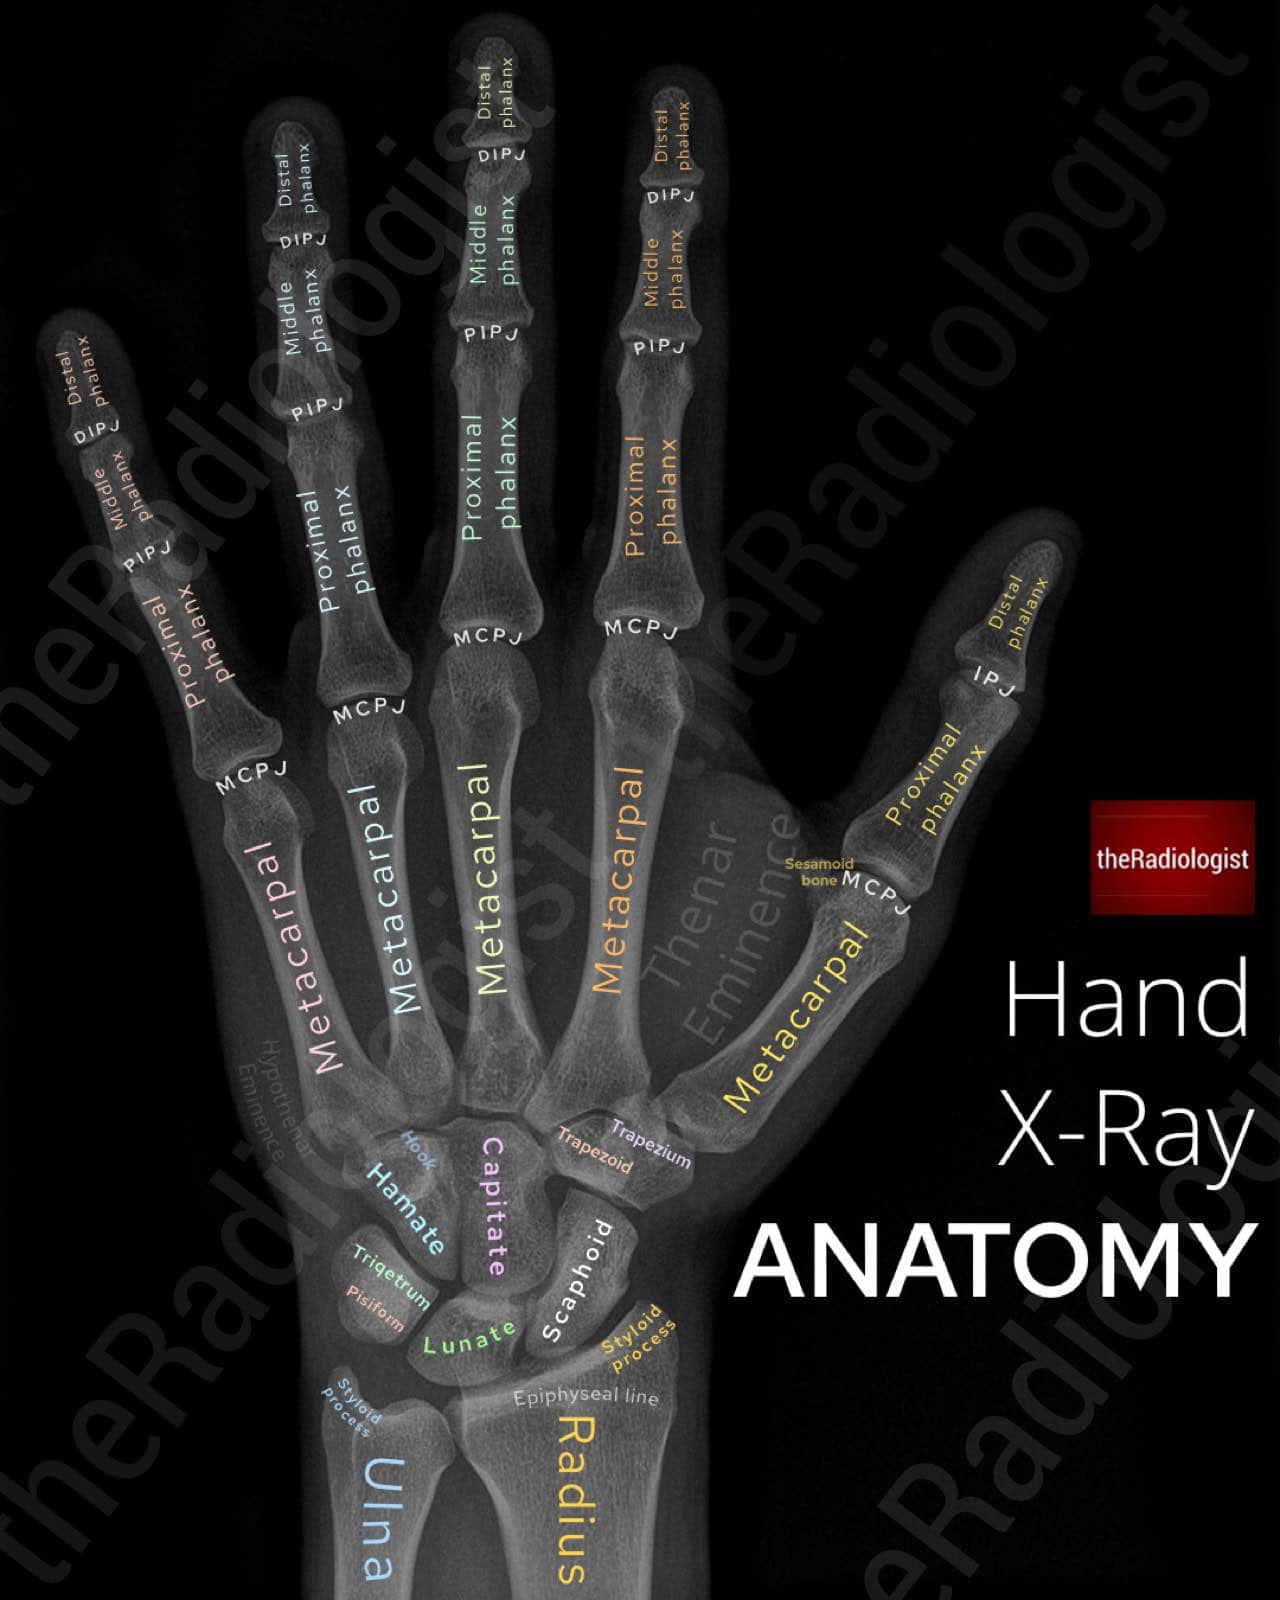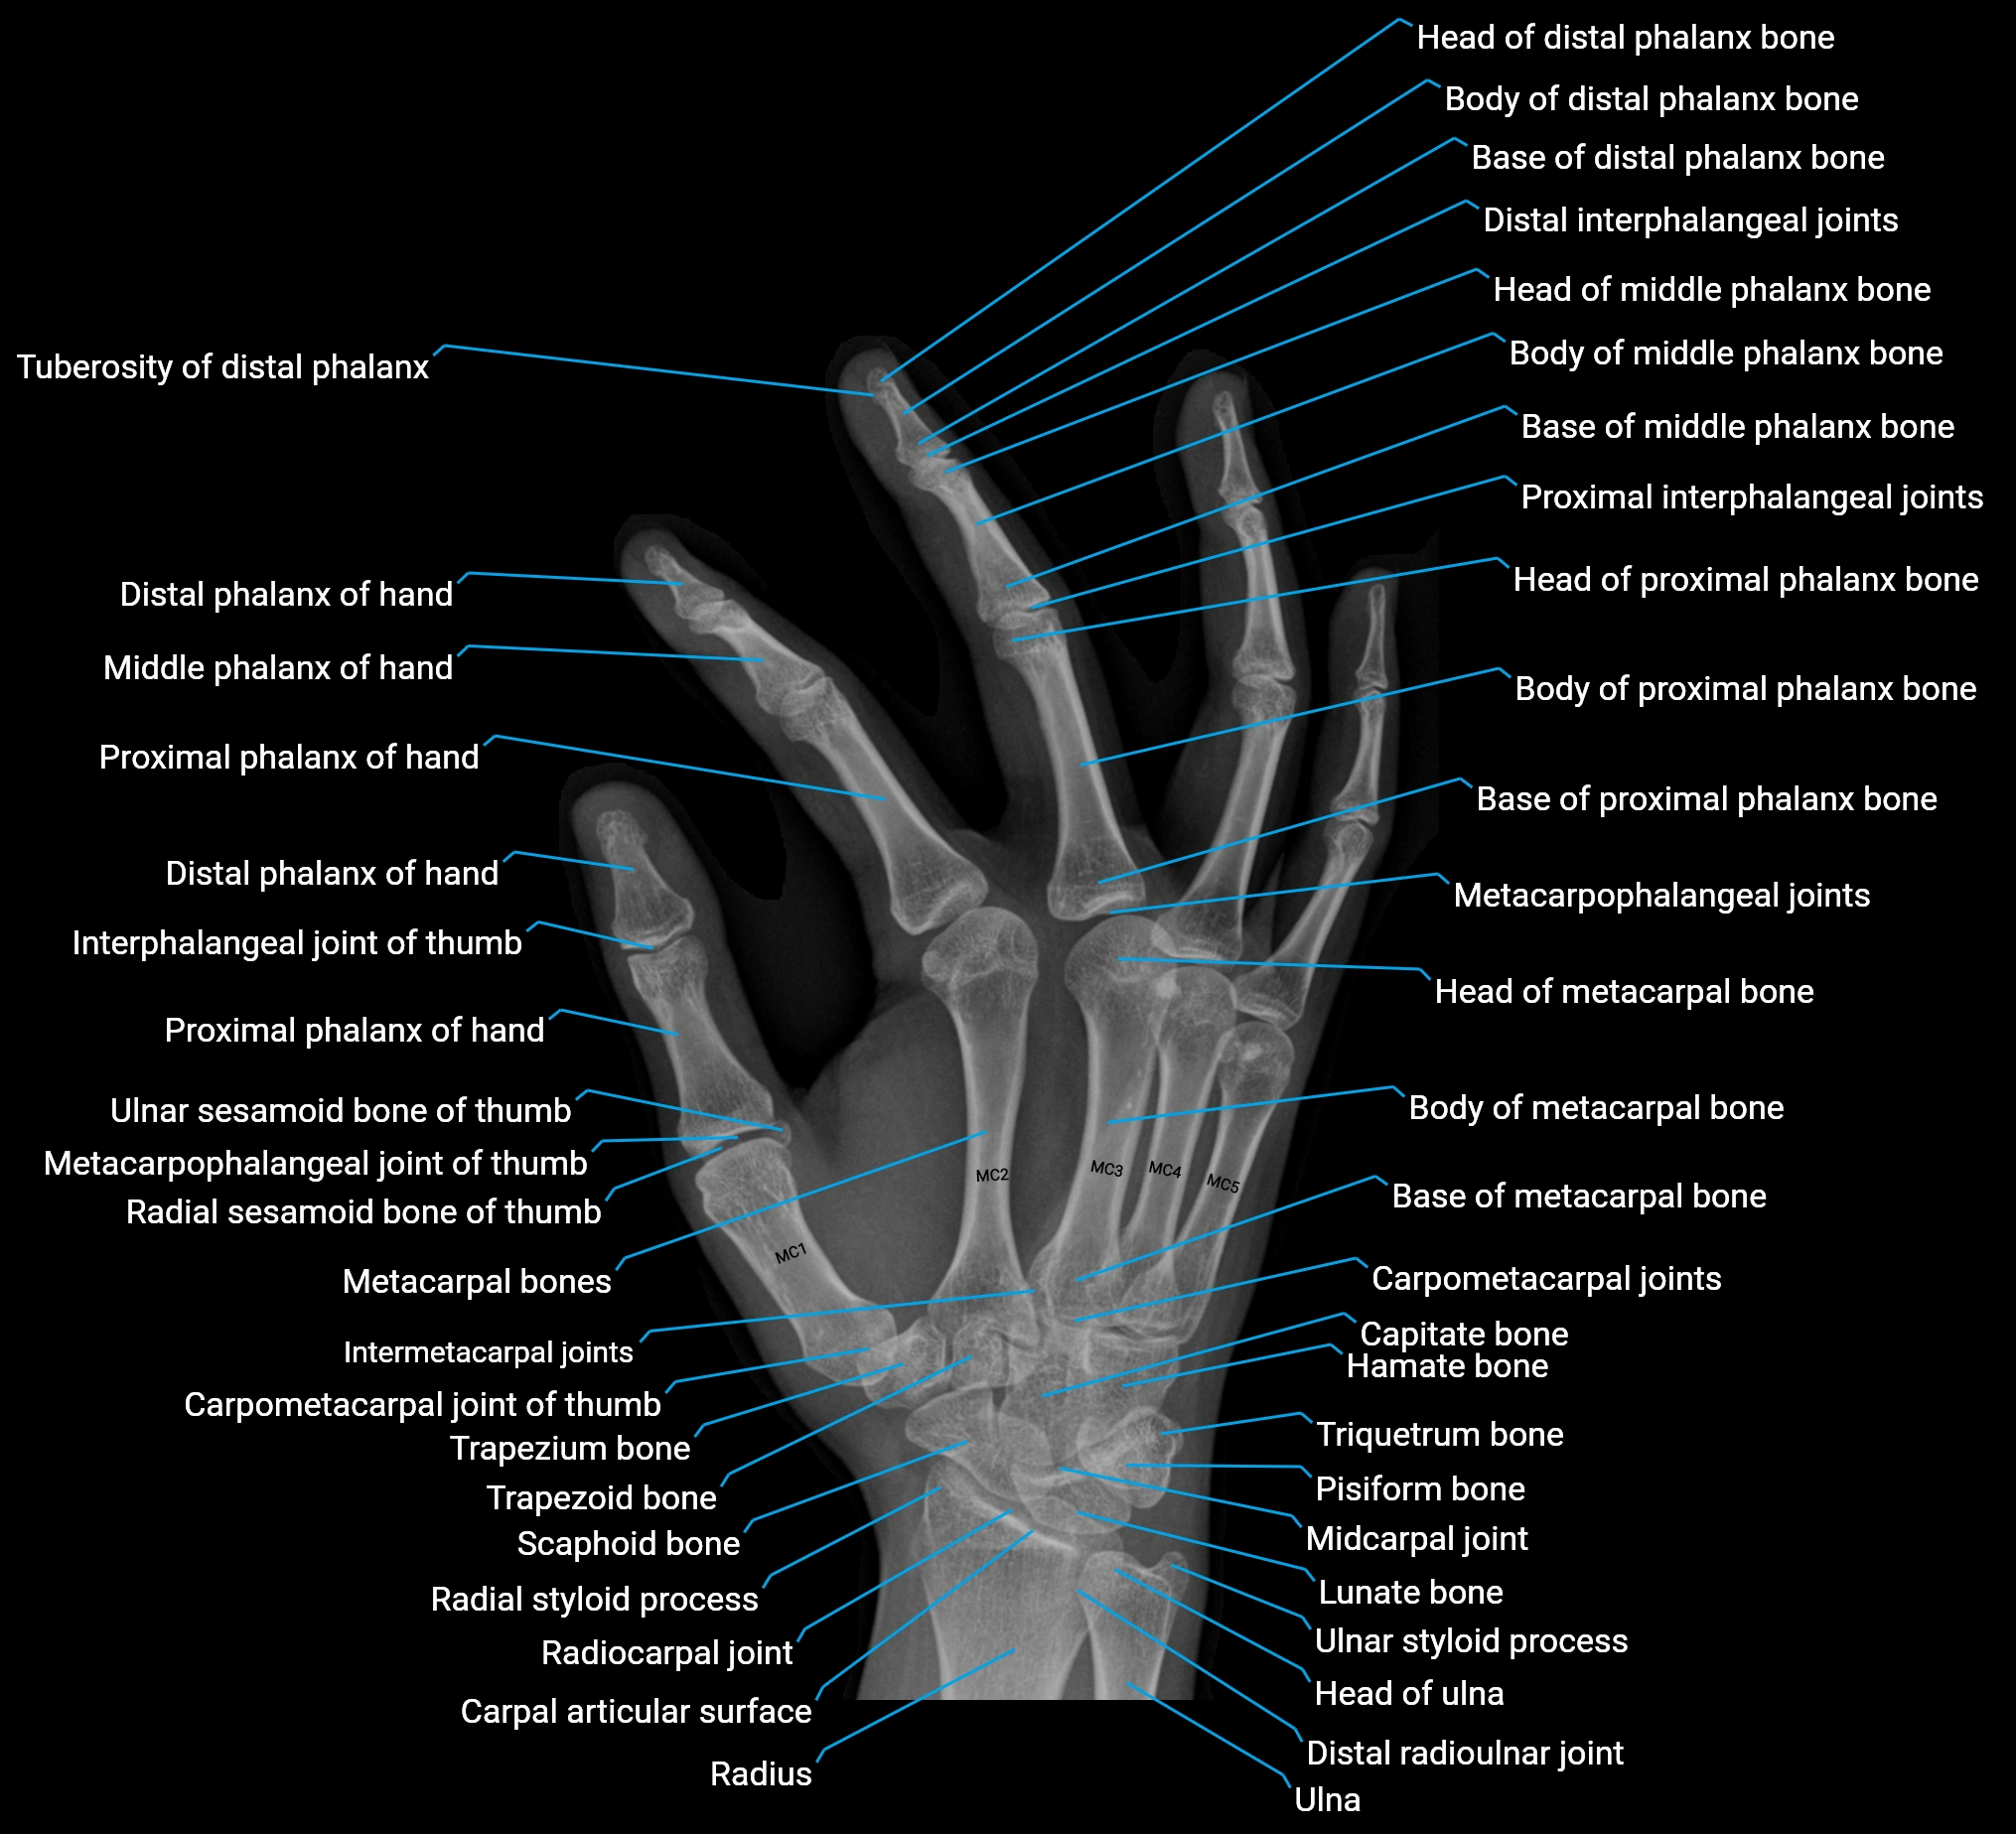
Positioning matters more than most residents admit
I spent years reading hand films for fracture detection, and the single biggest source of missed injuries was never a subtle dislocation. It was a PA view where the wrist was tilted slightly, superimposing the scaphoid against the radius and making a non-displaced fracture look like normal cortex. I caught this pattern so often I stopped waiting for the attending to confirm it. The film that looked fine became a second-set protocol when a patient had radial-sided pain with anatomical snuffbox tenderness. We would add a dedicated scaphoid series on the spot instead of sending them home with an NSAID prescription. That's the practical reality of a Hand Anatomy X Ray. It is not just ordering a three-view series and moving on. It is understanding which projections reveal which structures, recognizing when the standard views are inadequate, and knowing when to request additional angles before the patient leaves the department.
Hand Anatomy X Ray Projection Standards
The standard series for a hand radiograph includes three projections: posteroanterior, lateral, and oblique. The PA view requires the hand to be flat on the image receptor with fingers slightly spread and the wrist extended. You should see the metacarpophalangeal joints open evenly and the interphalangeal joints clearly separated. If the fingers are curled or the wrist is flexed, the carpals stack on each other and you lose diagnostic information in the scaphoid and lunate regions. The lateral view is taken with the hand in true lateral position, meaning the humerus, radius, ulna, and metacarpals all overlay properly. The key marker is the pisiform sitting centered over the triquetrum and the distal radius and ulna overlapping equally. When the lateral is rotated, you might miss a dorsal scapholunate dissociation or a subtle perilunate dislocation. The oblique view is obtained with the hand pronated at roughly forty-five degrees. This opens the intermetacarpal spaces and puts the scaphoid in profile. A proper oblique shows the scaphoid as an elongated boat shape without foreshortening.
What each projection actually demonstrates
The PA view is the bread and butter of hand imaging. It shows the metacarpals, phalanges, and the carpal rows in a frontal plane. You assess cortical continuity, joint space width, and soft tissue swelling. Fractures of the metacarpal shafts, avulsion fractures at the base of the fifth metacarpal, and distal radius fractures are typically visible here. The PA also gives you a baseline for tracking callus formation during healing. The oblique view exists for one primary reason: the scaphoid. On the PA, the scaphoid is foreshortened and superimposed over other carpals. On the oblique, it stretches out and you can trace the waist and proximal pole. I have seen scaphoid fractures missed on PA and lateral views that jumped off the screen on the oblique. It is not a rare occurrence. It happens regularly enough that any protocol without a dedicated oblique is incomplete. The lateral view is where you assess alignment. The lunate articulates with the radius in a normal configuration. The capitate sits centered over the lunate. If the capitate is dorsally displaced relative to the lunate, you are looking at a perilunate injury pattern. The lateral is also where you spot dorsal angulation of distal radius fractures, which directly determines whether closed reduction is reasonable or whether orthopedic consultation is needed immediately.
Get the Full Details
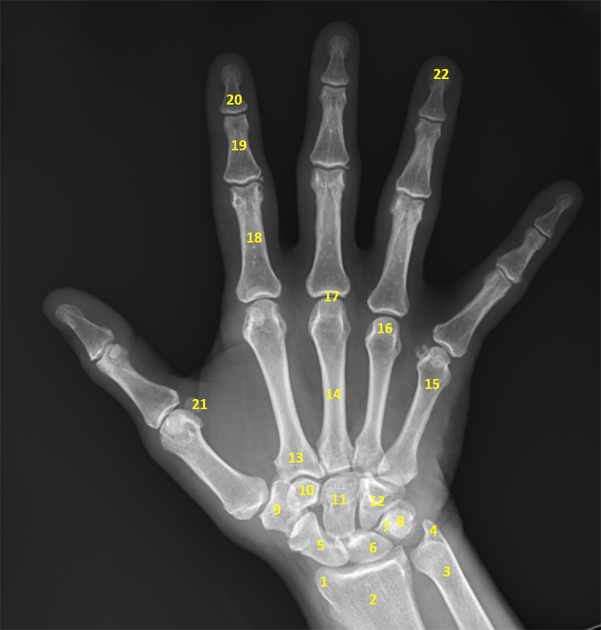
A specific problem I ran into and how I fixed it
Last winter I had a patient with a suspected Bennett fracture. The PA and oblique showed a fracture line at the base of the first metacarpal, but the intra-articular step-off was impossible to quantify. The fracture fragment was tiny, maybe four millimeters, and the standard projections could not separate it from the trapezium. I added a dedicated first metacarpal axial view with the tube angled twenty degrees cephalad. That single extra projection revealed a three-millimeter articular step-off that changed the management from casting to surgical fixation. The patient ended up with a better outcome because we knew the displacement before we decided on treatment. This is the kind of thing that does not make it into the textbooks. You learn it from seeing the same problem repeatedly and developing a mental index of when the standard series is insufficient. The standard three-view hand protocol covers most cases, but fifteen percent of them benefit from at least one additional projection depending on the clinical question.
Technical factors that actually matter
Hand x-rays require relatively low kilovoltage compared to other extremity studies. A typical setup uses sixty to seventy kVp with a low milliampere-second product. The goal is maximum contrast between bone and soft tissue. Automatic exposure control on modern units usually handles this correctly, but manual technique lets you compensate for patient size and clinical suspicion. A thin patient needs less exposure, and overexposing a hand film washes out the trabecular detail you need to spot a stress fracture. Focal spot size is another factor. A small focal spot, ideally one millimeter or less, reduces geometric unsharpness. The hand contains structures measured in fractions of a millimeter, particularly the scaphoid waist and the hook of the hamate. Large focal spots blur those details. Some institutions use a dedicated extremity cassette or digital detector with high-resolution mode for these cases. It makes a measurable difference in fracture detection rates.
Common pitfalls and what they hide
Soft tissue swelling is the most frequently overlooked finding. A patient presents with hand pain after a fall, the bones look intact on all three views, and the report reads normal. But the swelling over the dorsal aspect of the wrist, measured by comparing it to the contralateral side, indicates a significant ligamentous injury. Scapholunate ligament tears often present exactly this way. The bones do not fracture. The ligaments do. Plain radiography shows indirect signs: the Terry Thomas sign, which is a widened scapholunate gap greater than three millimeters, or the round lunate sign on the PA view when the lunate is volarly flexed. Another pitfall is the spina ventosa appearance in pediatric patients. Tuberculous dactylitis or Langerhans cell histiocytosis can cause lytic expansion of the phalanges that mimics a cyst on initial review. The lesion has a characteristic fusiform ballooning of the bone with thinning of the cortex. Without clinical correlation, it is easy to dismiss as a benign fibrous cortical defect.

When plain radiography hits its limits
A Hand Anatomy X Ray is excellent for cortical disruption and gross alignment, but it cannot reliably visualize scapholunate ligament integrity, early osteomyelitis, or carpal instability patterns without bony displacement. Bone scans and MRI detect marrow edema weeks before a fracture becomes visible on plain film. If clinical suspicion for a scaphoid fracture is high and the initial x-ray is negative, the standard approach has historically been immobilization and repeat imaging in ten to fourteen days. Modern practice increasingly favors early MRI or CT to avoid unnecessary casting and missed diagnoses. CT is particularly useful for intra-articular fractures of the distal radius and the carpal bones. It provides submillimeter resolution of fracture fragments and articular step-offs. MRI remains the modality of choice for ligamentous injuries and occult fractures. Both are expensive and not universally available in emergency departments, which is why the plain film series remains the first-line investigation in most settings.
A note on labeling and laterality
This sounds trivial but it is one of the most common errors in my experience. A right hand labeled as left throws off the entire clinical pathway. Surgeons plan incisions based on laterality. Radiologists compare against prior studies with the wrong side identified. I once read a series where the lateral view was clearly a right hand but the marker said left, and it took twenty minutes of questioning the technologist to resolve. Always verify laterality markers before signing out the report. Check the thumb position on the PA view. The right thumb is on the lateral side of the hand on a standard PA projection. The left thumb is on the opposite side. Cross-reference with the clinical history if there is any doubt. Protocol design varies by institution. Some emergency departments use a clinical decision support rule that determines whether a hand x-ray is indicated based on mechanisms like direct blow, axial loading, or deformity. Others rely on physician judgment. Understanding when to order and what projections to include is the difference between a useful study and one that returns nothing actionable. The anatomy is straightforward. The execution is where most mistakes happen.