Understanding hCG in Twin Pregnancies
hCG stands for human chorionic gonadotropin. It's the hormone your placenta starts producing after implantation. In a twin pregnancy, the numbers tend to run higher than in singletons, but that's not a hard-and-fast rule. You can have twins with hCG right in the normal singleton range, and you can have a singleton with sky-high readings. The test itself is just a blood draw. The interpretation is where people get confused. I've sat through more ultrasound confirmations than I care to count where someone was panicking because their week 6 hCG was "too low" or "too high." Usually neither. Just context-dependent.
Hcg Level Twin Pregnancy
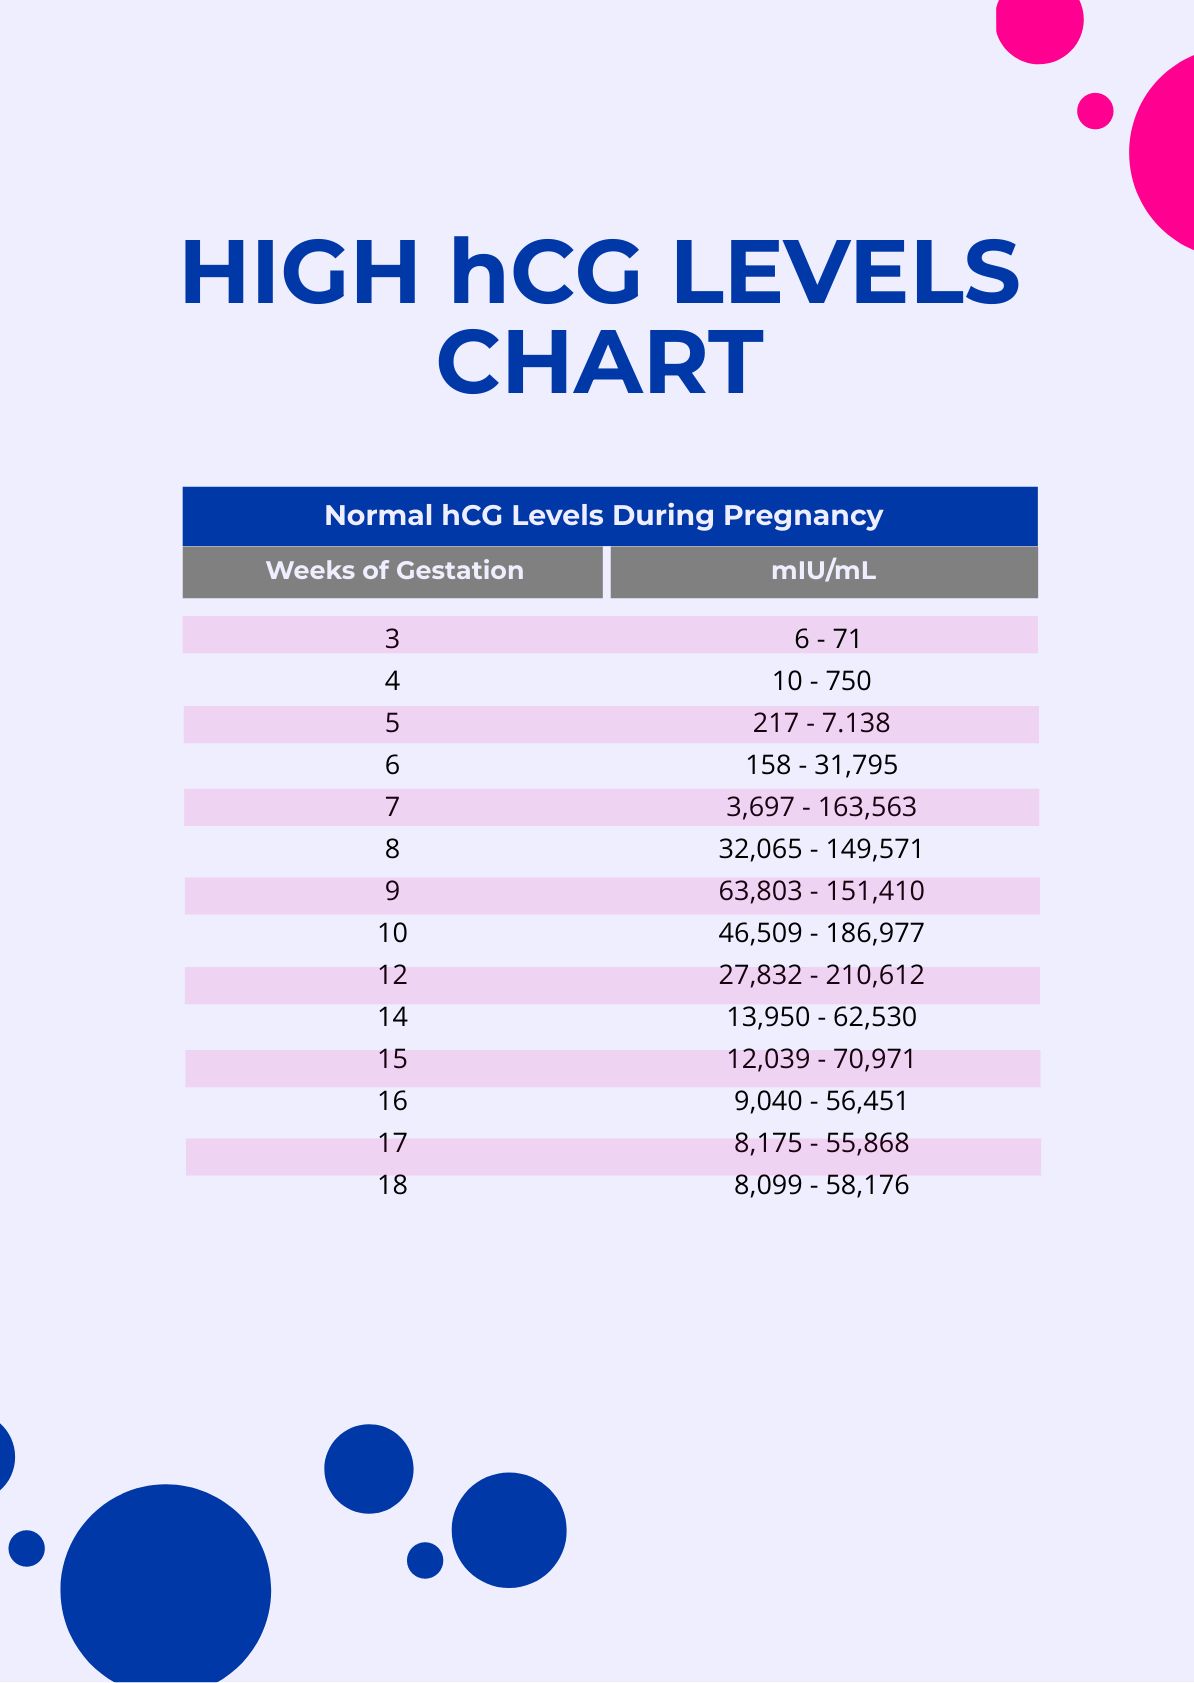
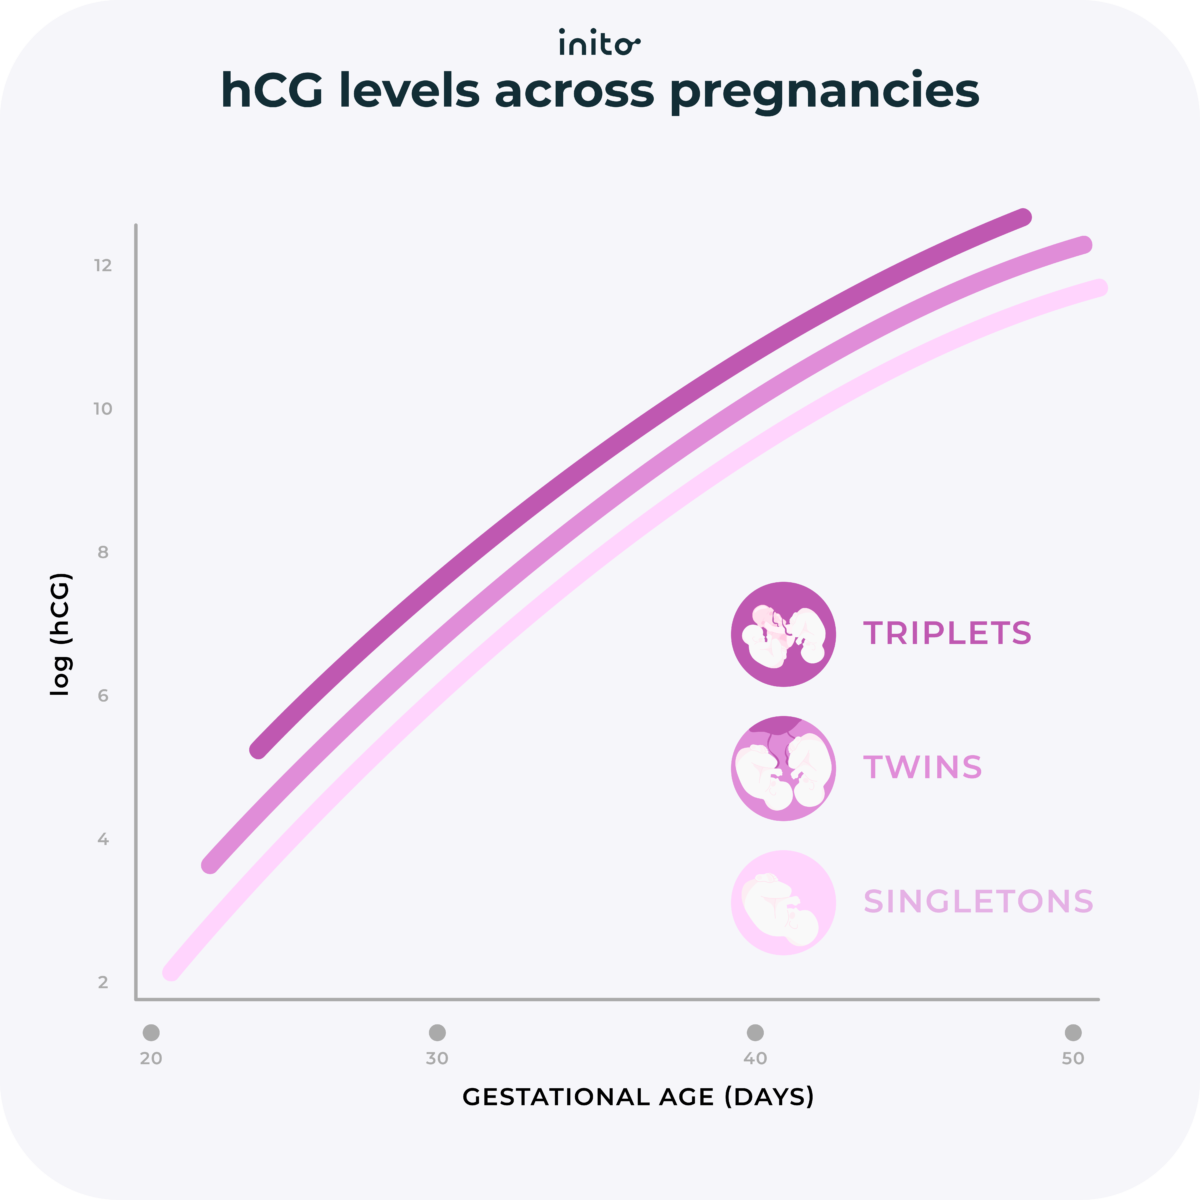
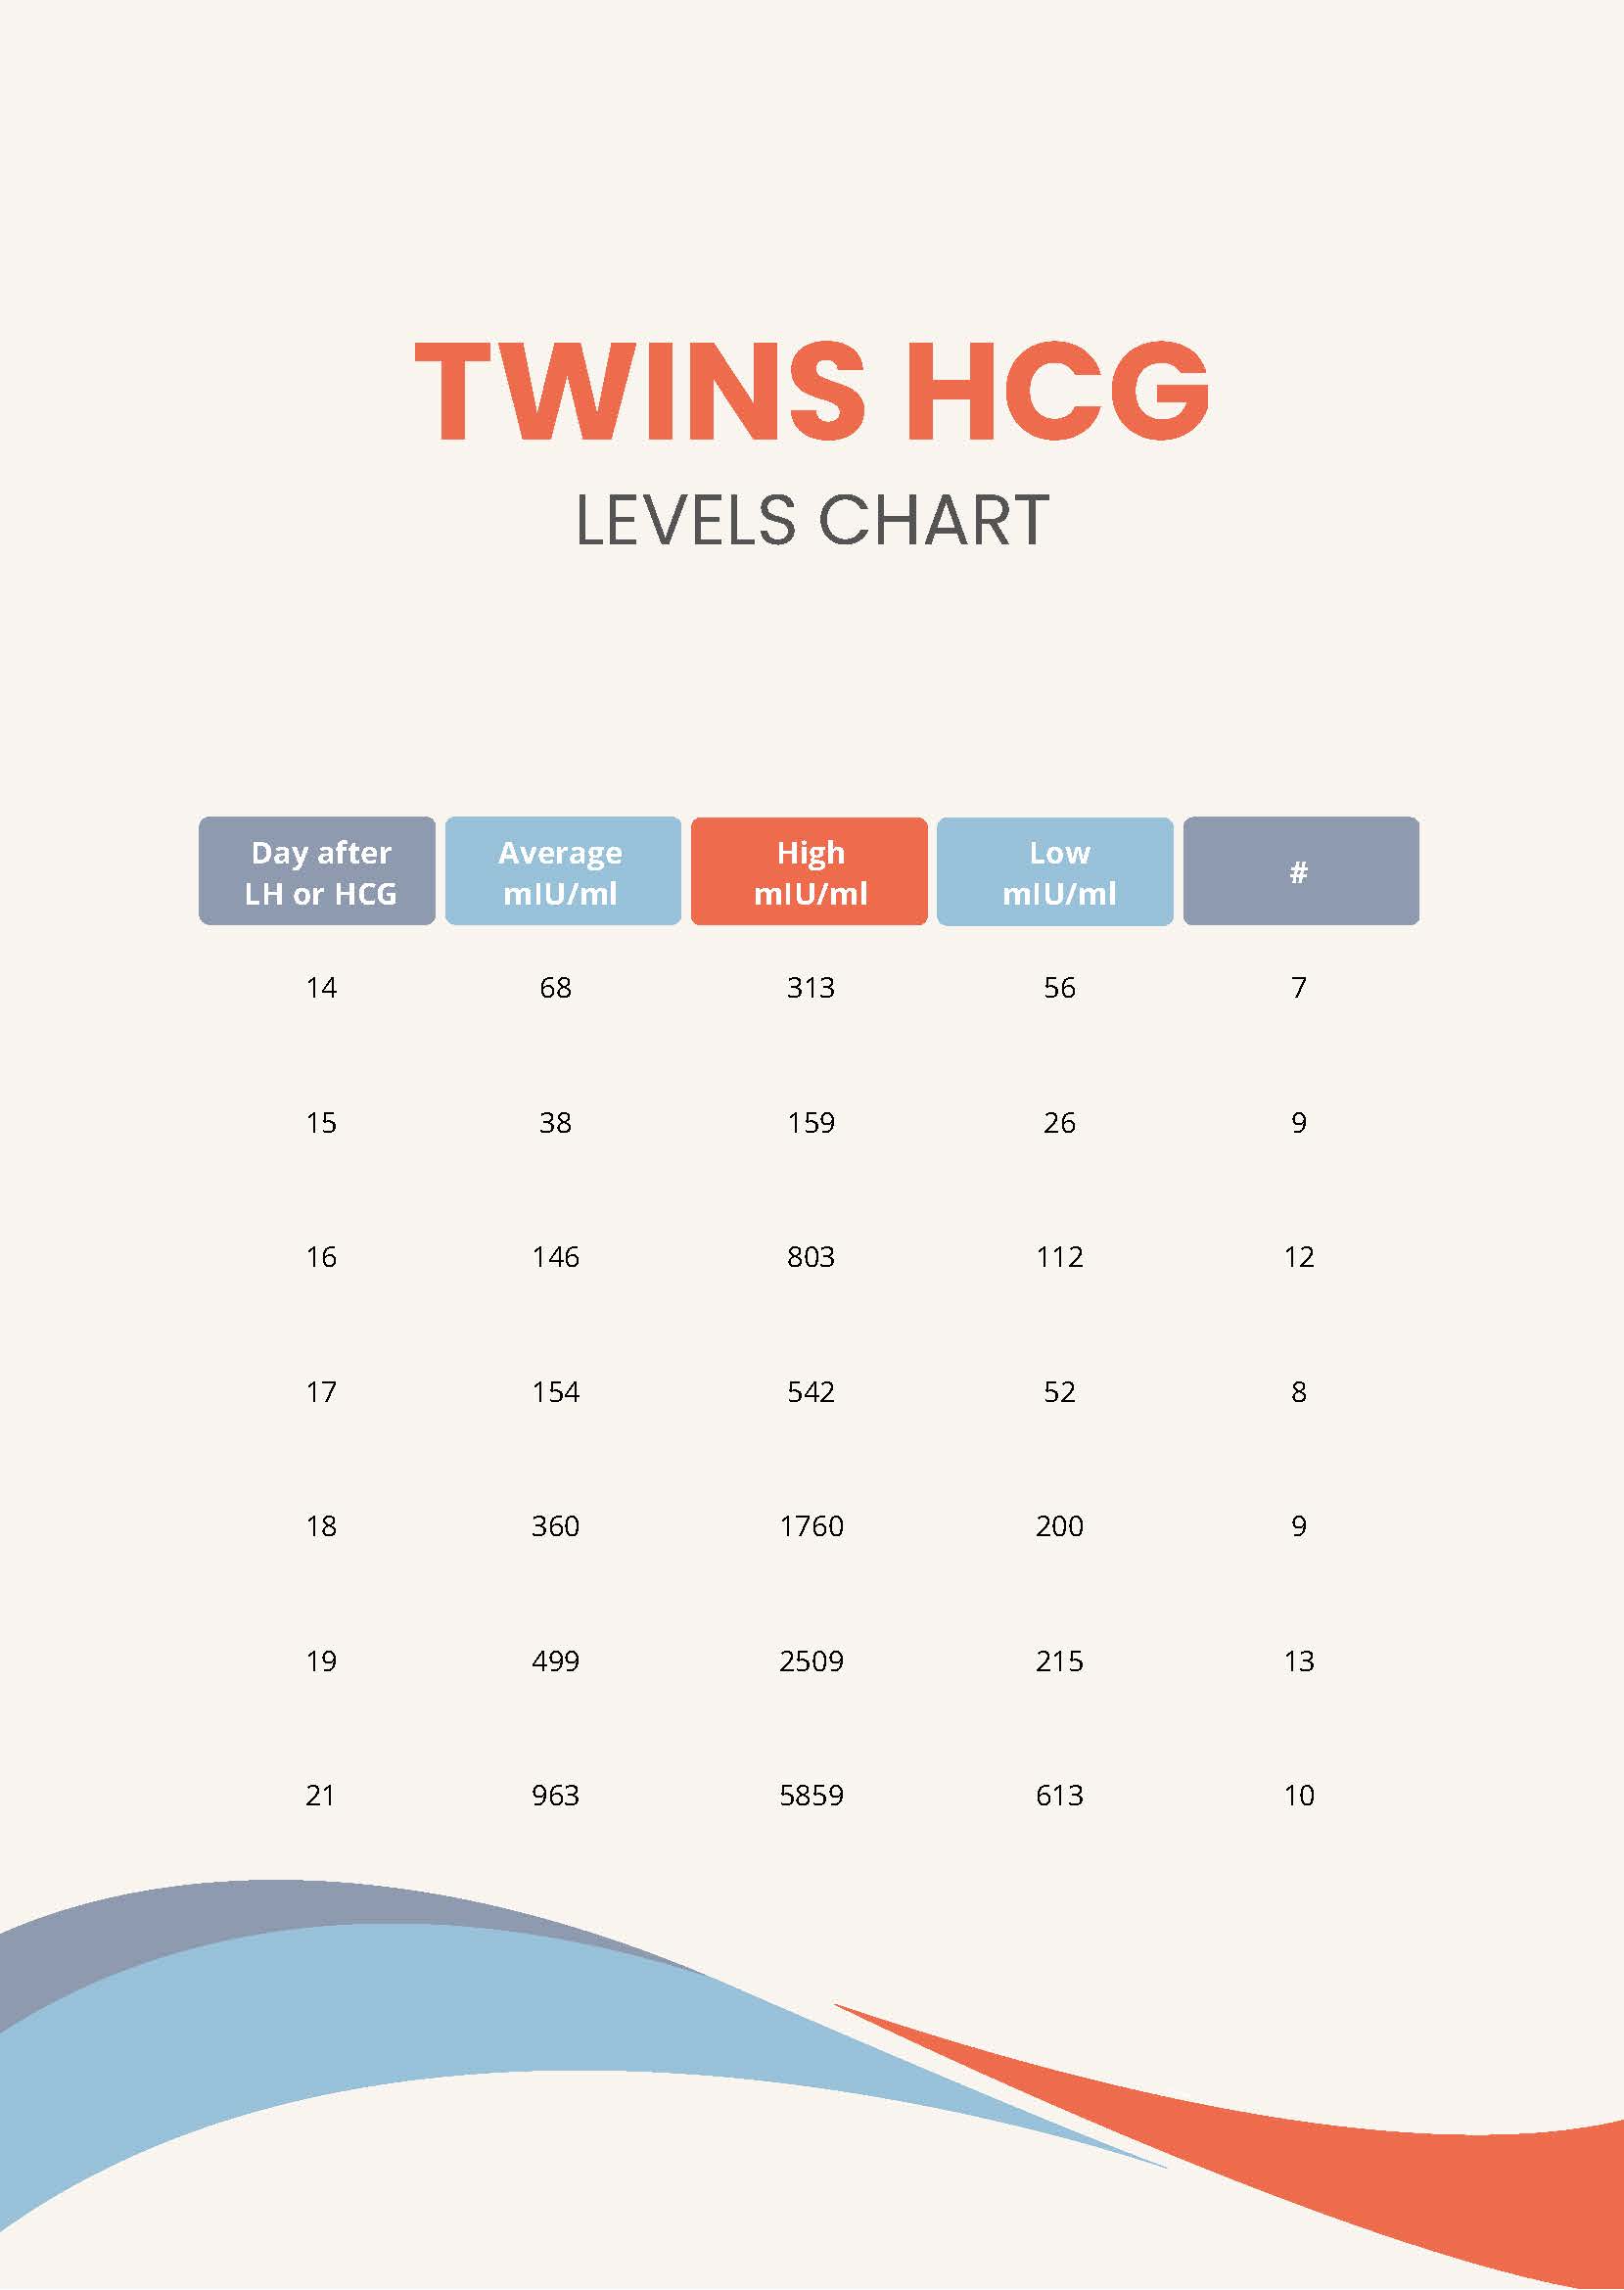
When you're tracking hCG in a twin pregnancy, the baseline expectation shifts. At 4 weeks from your last period, singleton hCG typically lands between 5 and 426 mIU/mL. By week 6, that range jumps to somewhere around 7,600 to 229,000 mIU/mL. Twins often push the upper end of those brackets, sometimes into the 50,000 to 150,000 range by week 6 or 7. But looking at the absolute number alone tells you very little without the gestational age nailed down precisely. Here's what most guides don't mention: the doubling time matters more than the single value. In early viable singleton pregnancies, hCG roughly doubles every 48 to 72 hours. With twins, the doubling can be faster early on, but it slows as the numbers climb. Once you hit above 6,000 mIU/mL, the doubling time stretches out regardless of how many embryos you're carrying. A drop from expecting a rapid climb to seeing a slower rise at week 7 doesn't automatically signal a problem. It's just the math of the hormone plateauing. I ran into a case last year where a patient at 5 weeks 4 days had an hCG of 18,200 and was convinced something was wrong because her previous draw at 5 weeks 1 day had come back at 9,400. She'd read online that it should double every two days and started spiraling. In reality, the doubling time at that level was about 84 hours, which is completely normal. The embryo was growing, the numbers were appropriate for twins, and the follow-up ultrasound at 6 weeks confirmed two heartbeat-positive gestations. The lesson here is that doubling-time calculators assume exponential growth in the low-number phase. Once you cross into the thousands, the curve flattens and the calculators start giving you false alarms.
Another thing people miss: different labs use different assays. One lab might report 42,000 where another reports 38,000 for the same sample. That 10 percent variance is normal laboratory noise, not a clinical difference. Always compare results from the same lab if you're tracking trends over time. Jumping between facilities introduces variables that have nothing to do with your actual hormone levels. There's also the hook effect to worry about at very high concentrations. When hCG exceeds roughly 500,000 mIU/mL, some immunoassays can give falsely low readings because the excess hormone saturates the antibodies in the test. I've seen this happen around week 10 to 12 in multiple gestations, where a woman's hCG was actually climbing but the lab report showed it dropping. The fix is simple: request a dilution test. The lab dilutes the sample and re-runs it, which resolves the interference. Without that step, you could be misreading a healthy pregnancy as nonviable based on bad data. Ultrasound remains the gold standard for confirming twin viability, not serial hCG. Once you can see two gestational sacs with fetal poles and cardiac activity, the hormone numbers become largely irrelevant for monitoring. That transition usually happens around week 6 to 7. After that point, ongoing care follows the standard twin pregnancy protocol: earlier and more frequent ultrasounds, screening for complications like twin-twin transfusion syndrome if they're monochorionic, and routine prenatal visits adjusted for the higher-risk classification.
Get the Full Details
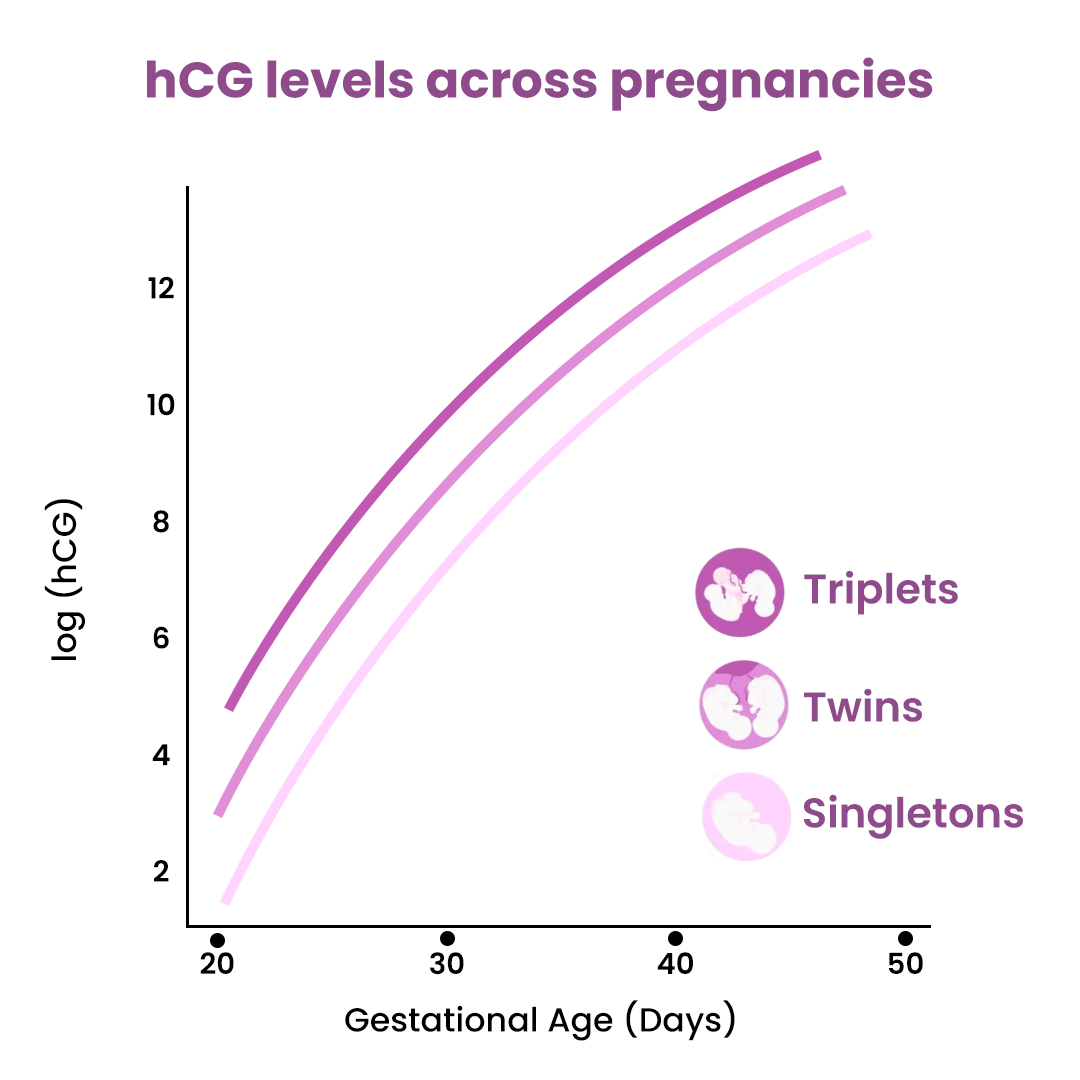
If you're comparing your numbers against published ranges, keep in mind those ranges are derived from singleton populations. Twin-specific reference intervals exist but aren't universally standardized across laboratories. Some fertility clinics maintain their own twin tracking data from IVF cycles, which tends to show slightly higher and earlier-rising hCG compared to naturally conceived twins. If you conceived through IVF, your clinic will have the most accurate baseline because they know your exact transfer date and can calculate gestational age to the day rather than guessing from a last period that may have been irregular or suppressed by prior medication.