Understanding HCG Patterns When You're Carrying More Than One
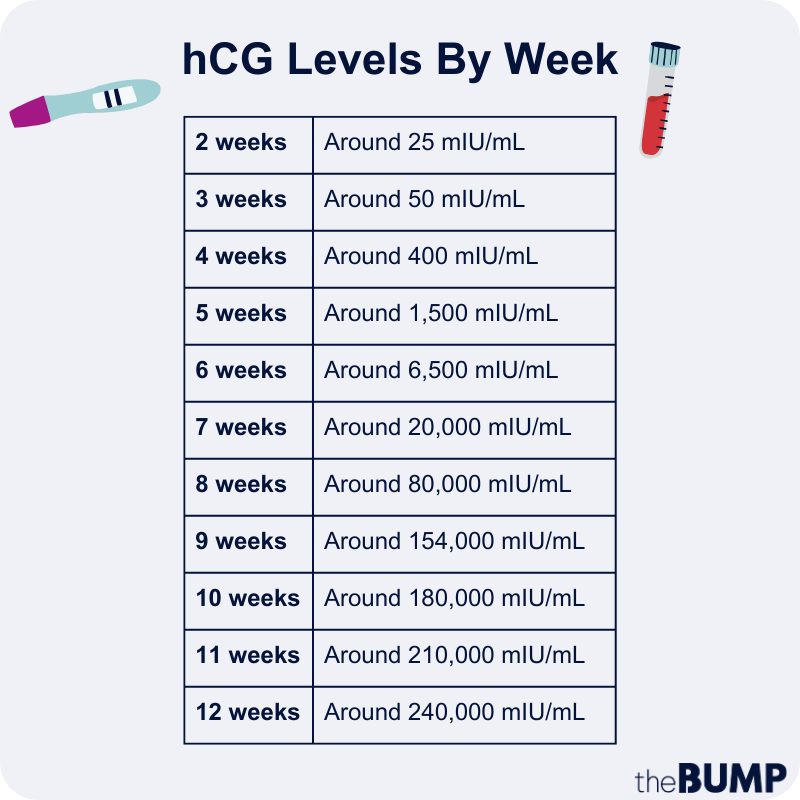
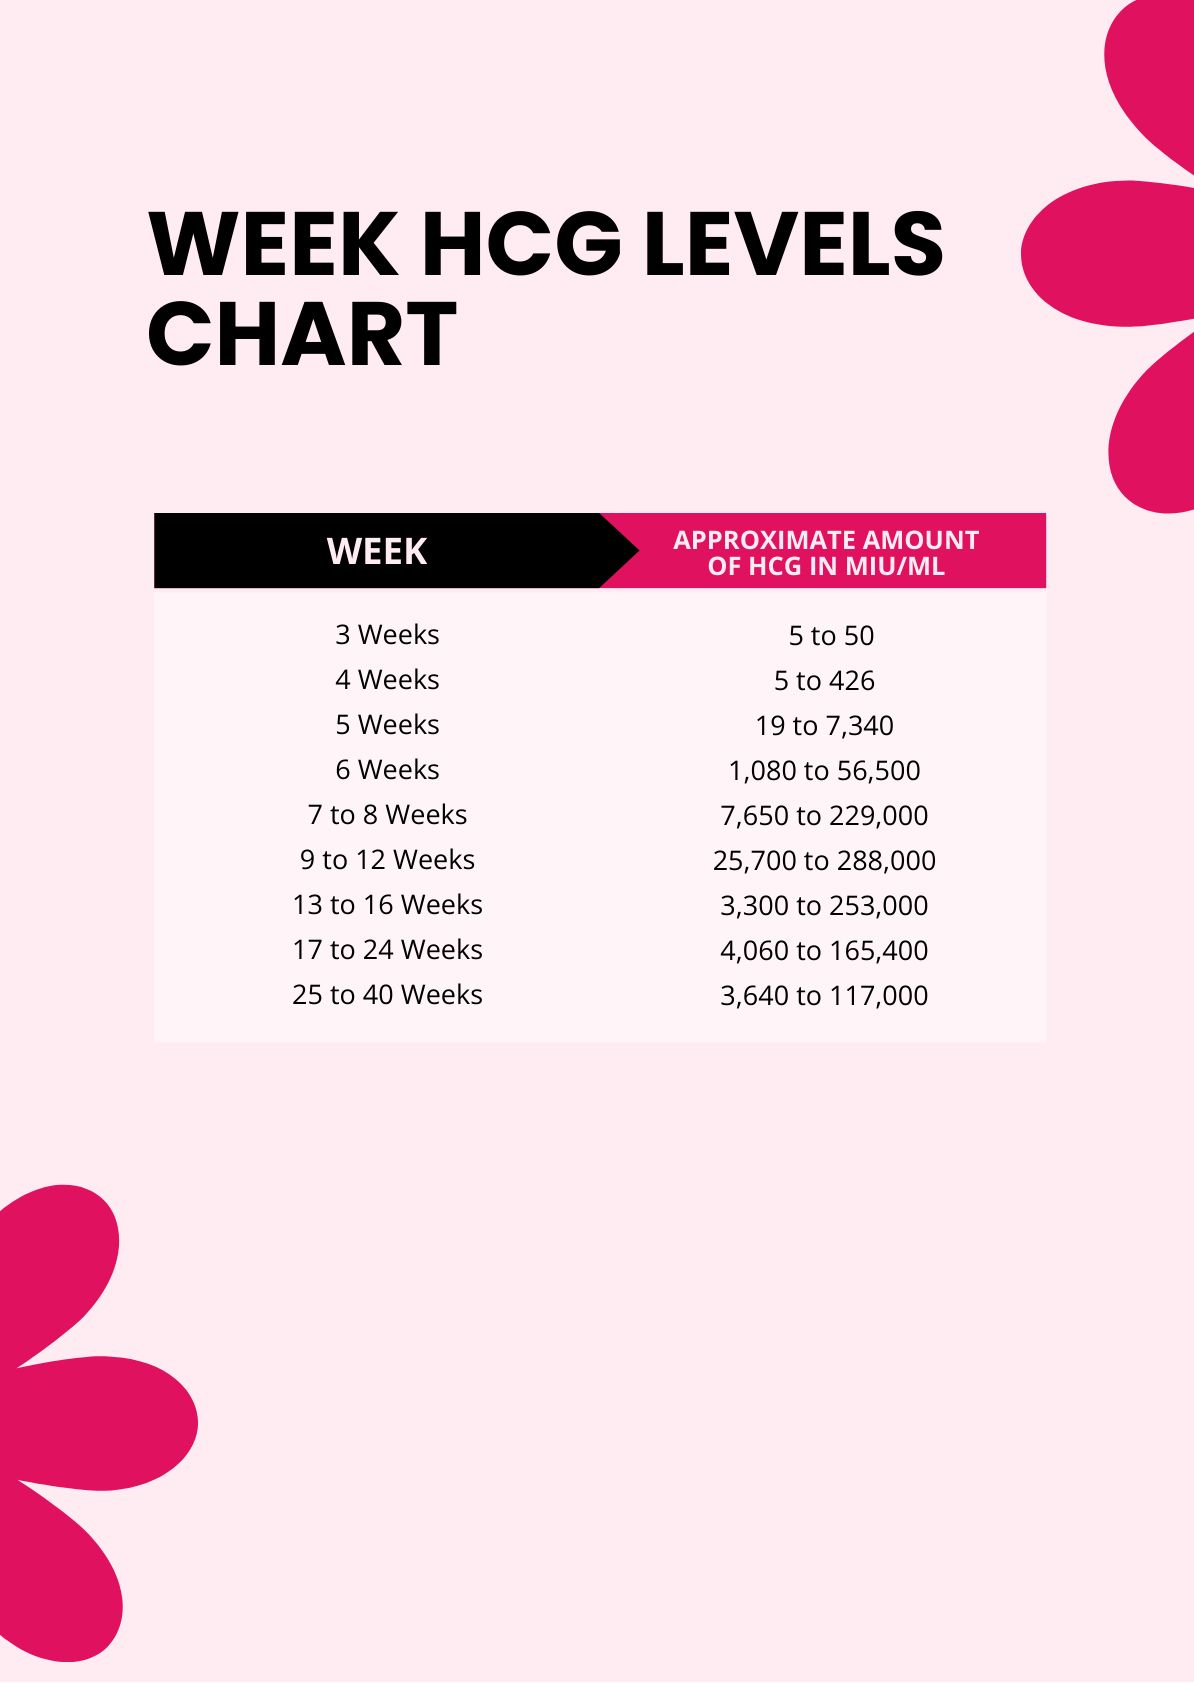
HCG Levels For Multiples At 4 Weeks tend to run higher than singleton pregnancies, but the ranges overlap so much that a single blood test rarely gives you a definitive answer. At four weeks gestational age, hCG typically sits between 5 and 426 mIU/mL for a singleton pregnancy, while twins usually land somewhere between 18 and 1,080 mIU/mL. Triplets can push that upper range even further. The problem is that both the lower end of multiples and the higher end of singletons exist in roughly the same neighborhood, which makes hCG alone nearly useless for diagnosing multiples at this stage. I got pulled into a situation last year where a patient came in at 4 weeks and 2 days with an hCG of 980 mIU/mL. Her husband and her OB were already talking about twins before the ultrasound was even scheduled. I ran the serial quantitative hCGs over 48 hours and watched it jump from 980 to 1,820. That doubling time is actually pretty typical for a normal singleton at that level. We weren't being dramatic about the singleton possibility because the rate of rise mattered more than the absolute number. Two days later, the transvaginal ultrasound showed a single gestational sac with a yolk sac and a tiny flicker of a fetal pole. Twins would have been visible by then if they were actually there. This is exactly why I tell people to stop fixating on the raw hCG number and start tracking the delta instead. With multiples, the hCG doesn't just sit higher overall. It also tends to climb faster because more trophoblastic tissue is producing the hormone. In practice, that means you might see a 60 to 70 percent rise over 48 hours with twins, whereas a singleton usually hits the textbook 53 to 87 percent window. Some women with twins show the faster doubling early on, then the rate normalizes as pregnancy progresses past eight weeks, which is when hCG peaks anyway. That plateau phase makes serial monitoring even less useful for determining whether multiples are present.
The real utility of hCG at four weeks is confirming that something is progressing in the right direction, not mapping out how many embryos are in the uterus. If you want to know about multiples, a transvaginal ultrasound at five to six weeks gestation is the actual diagnostic tool. By that point, you can count gestational sacs and later fetal poles with reasonable confidence. Anything before five weeks is essentially guesswork with extra blood draws attached. A few practical things to keep in mind. First, if you conceived through IVF with multiple embryo transfers, your baseline hCG will naturally be higher and the numbers will reflect that from day one. Second, if you have a known fertility diagnosis like PCOS or prior ectopic history, your provider should be moving quickly toward an early scan rather than cycling you through repeated hCG draws. Third, don't order an at-home urine test expecting it to tell you anything about multiples. Those qualitative strips only confirm presence or absence above a certain threshold, usually 25 mIU/mL, and they give you zero quantitative data to work with. The digital "pregnant" readout on a test strip means absolutely nothing when it comes to predicting how many embryos are developing. The biggest pitfall I see is people ordering their own lab work and then spending three weeks in a diagnostic loop because a number looked either too high or too low. Normal variation in hCG at four weeks is enormous. A result of 150 mIU/mL could be a perfectly healthy singleton on the earlier side of implantation, or it could be a multiples pregnancy where implantation happened a couple days later than expected. The only way to resolve that uncertainty is a follow-up draw in 48 hours and then an ultrasound, not another random hCG test three days later.