Why the Standard Head To Toe Assessment Template Keeps Failing You
I've spent years watching nurses and med students struggle with assessment templates that look perfect on paper but fall apart in real clinical settings. The problem isn't usually the template itself. It's how people use it, or don't use it, and what gets lost in the shuffle when you're rushing between patients. A head to toe assessment is simply a systematic approach to examining a patient from top to bottom. You start at the head and work your way down, checking each system in order. The template is just a structured way to document what you find. That's it. Nothing fancy about it. But getting it right in practice is where things get messy.
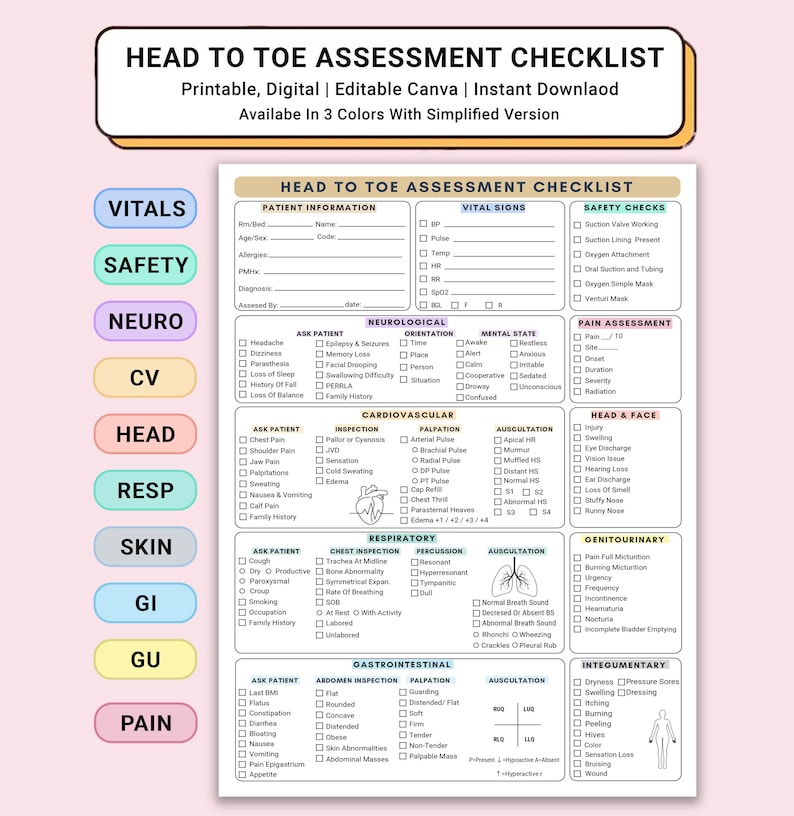
Head To Toe Assessment Template: What It Actually Is
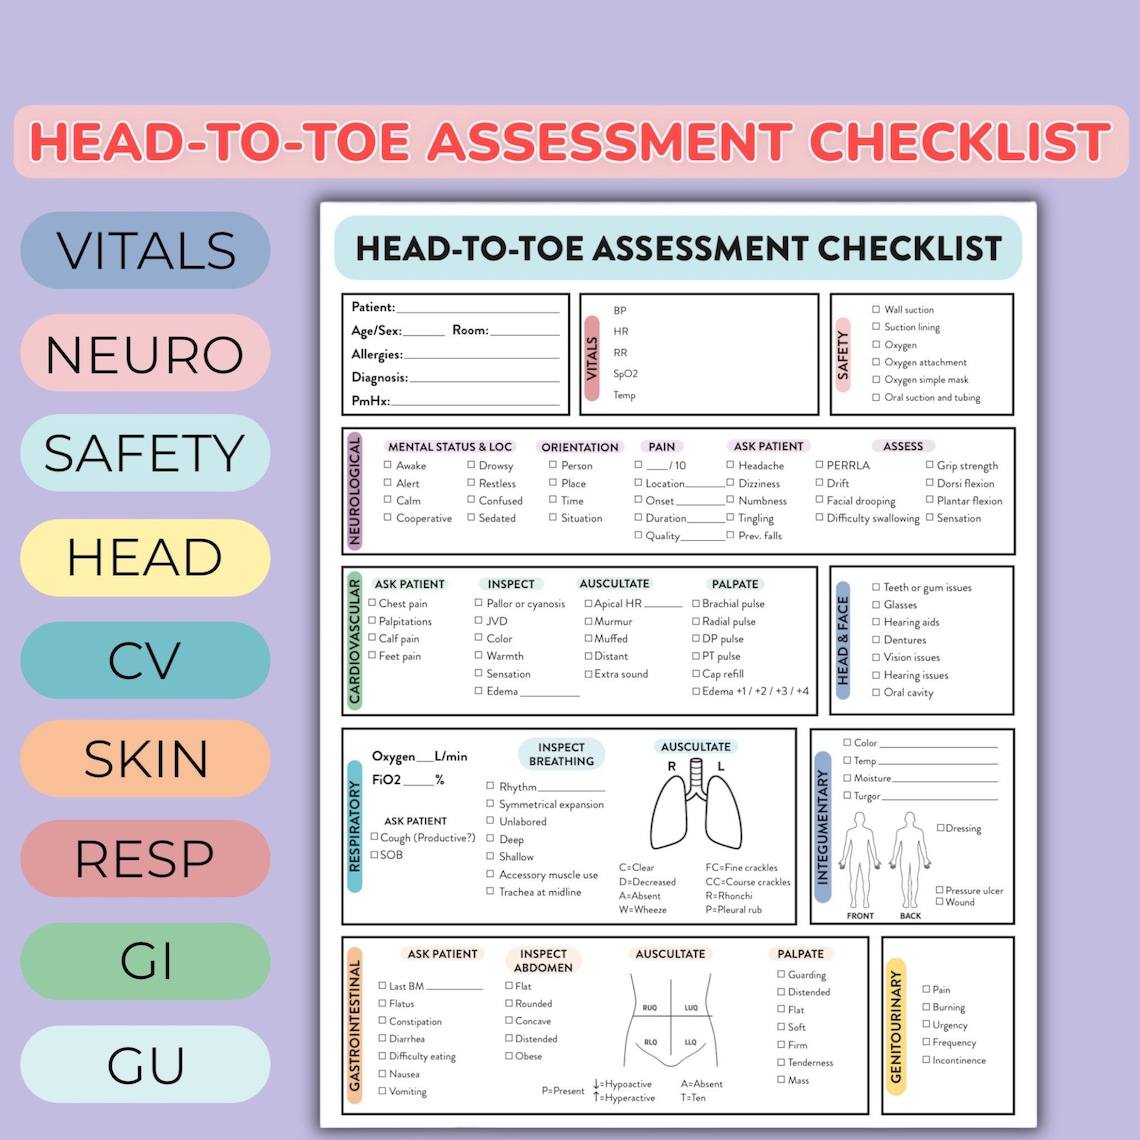
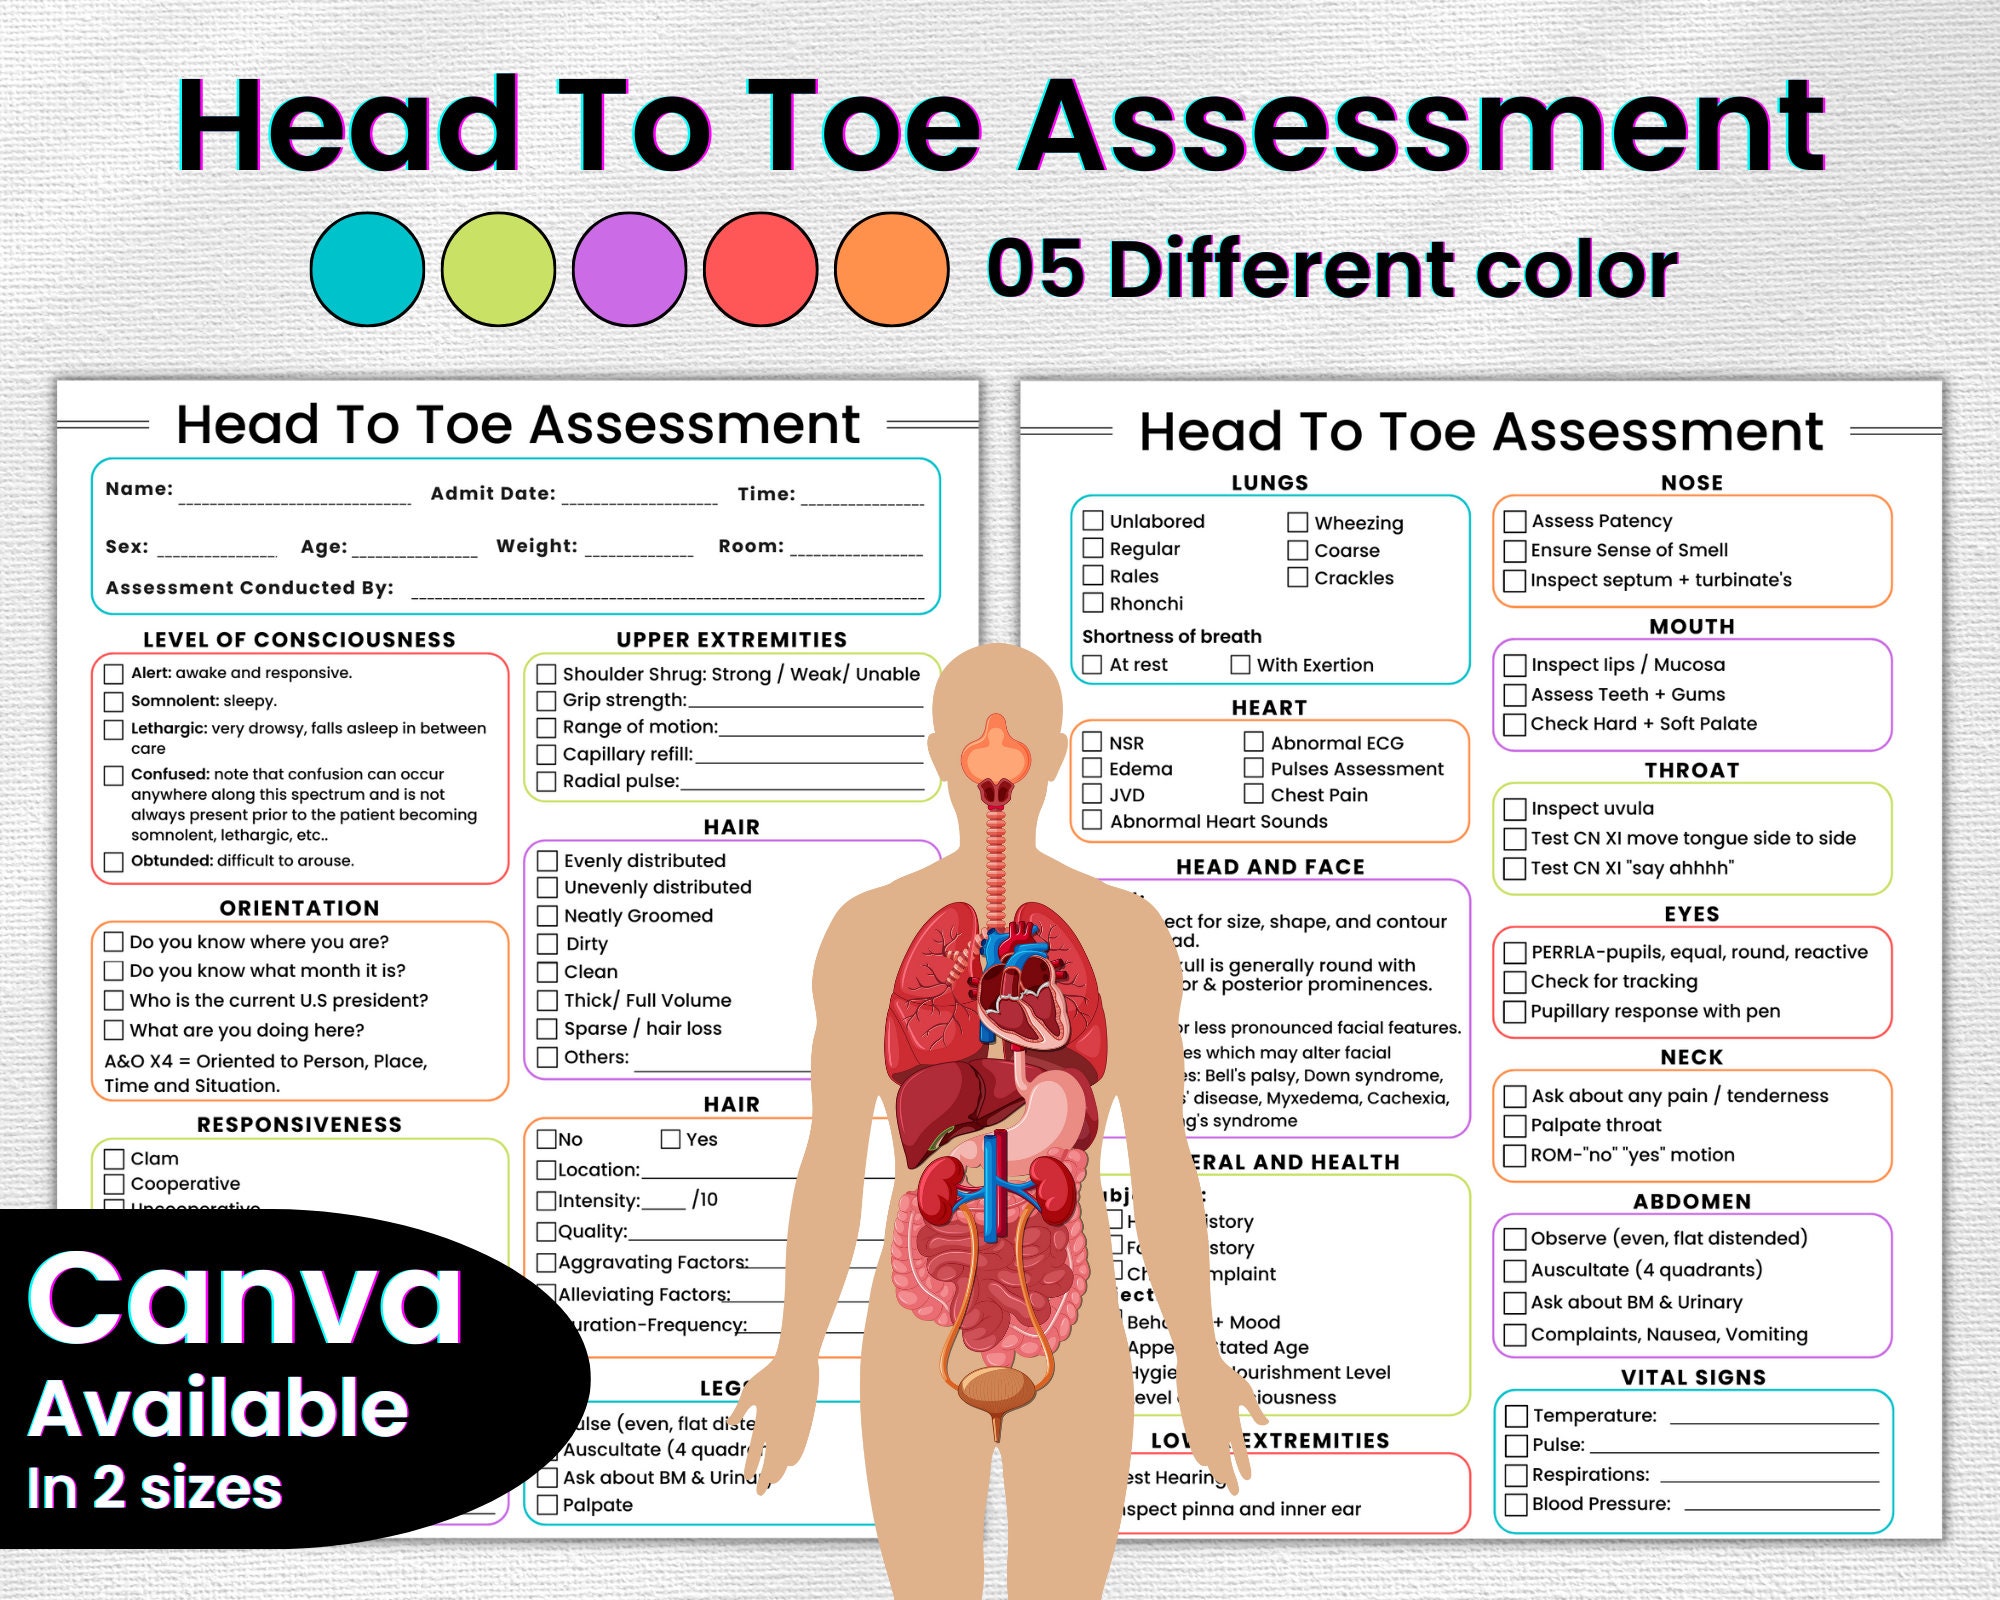
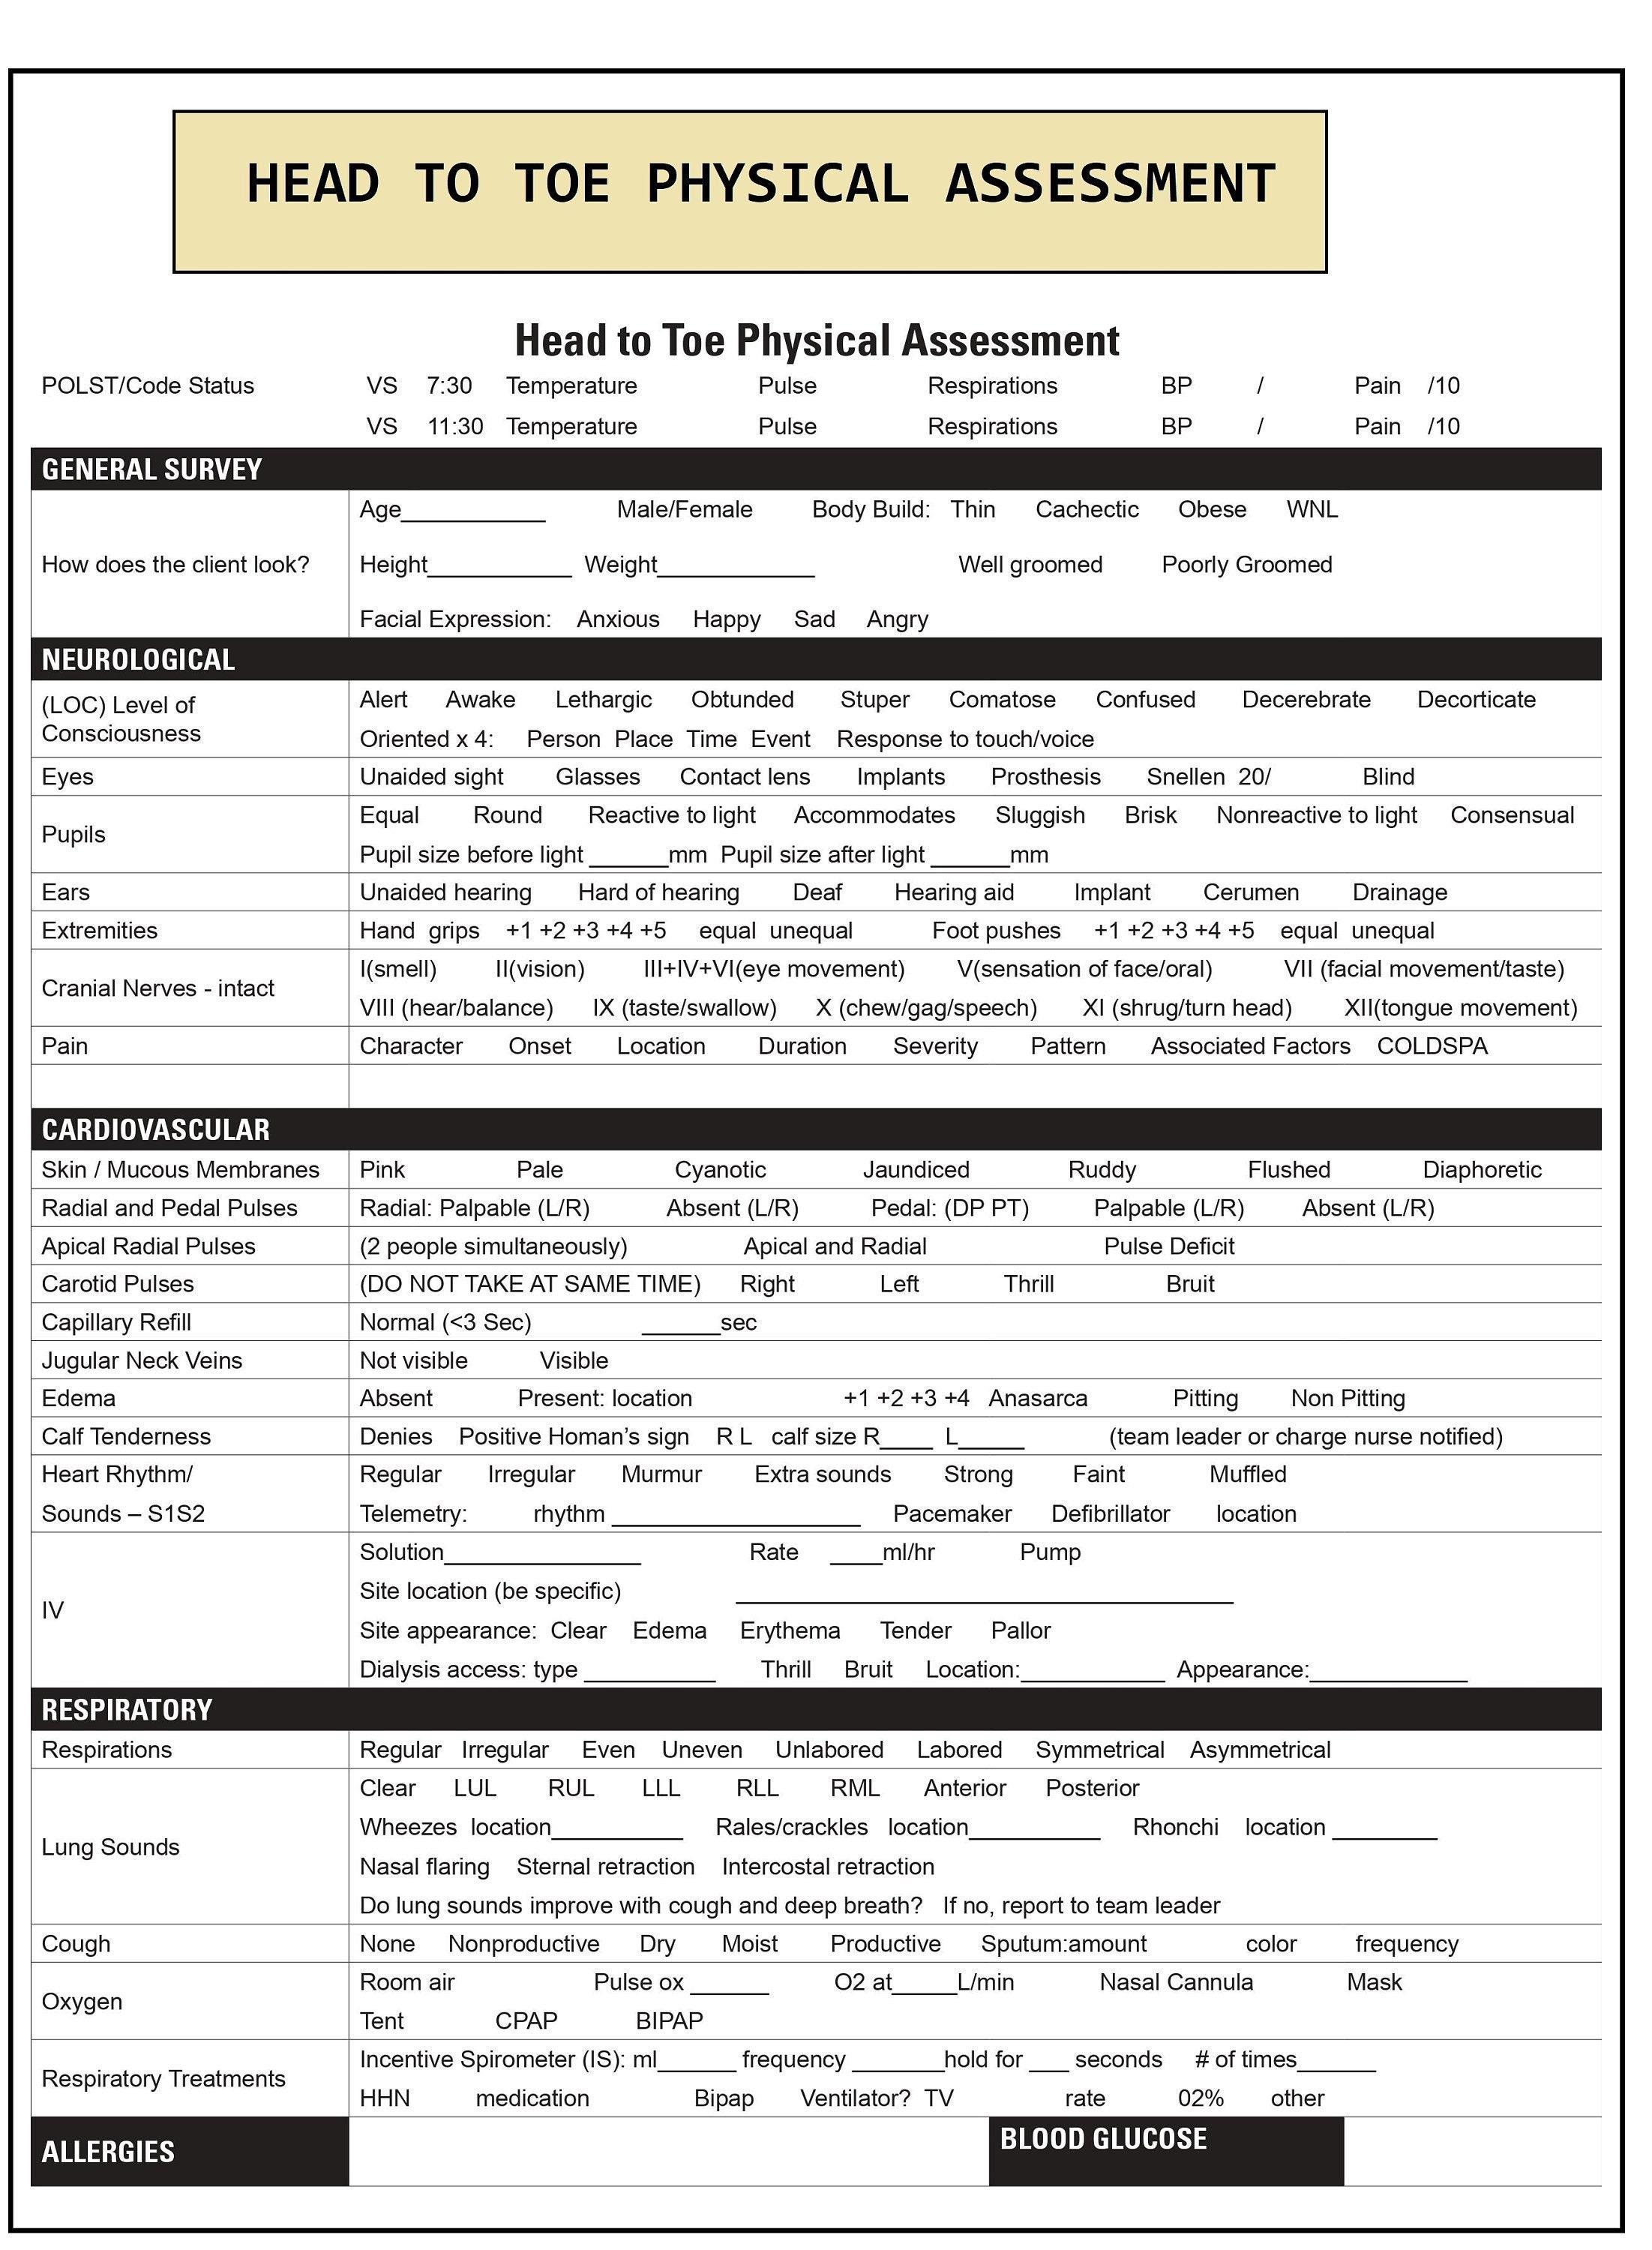
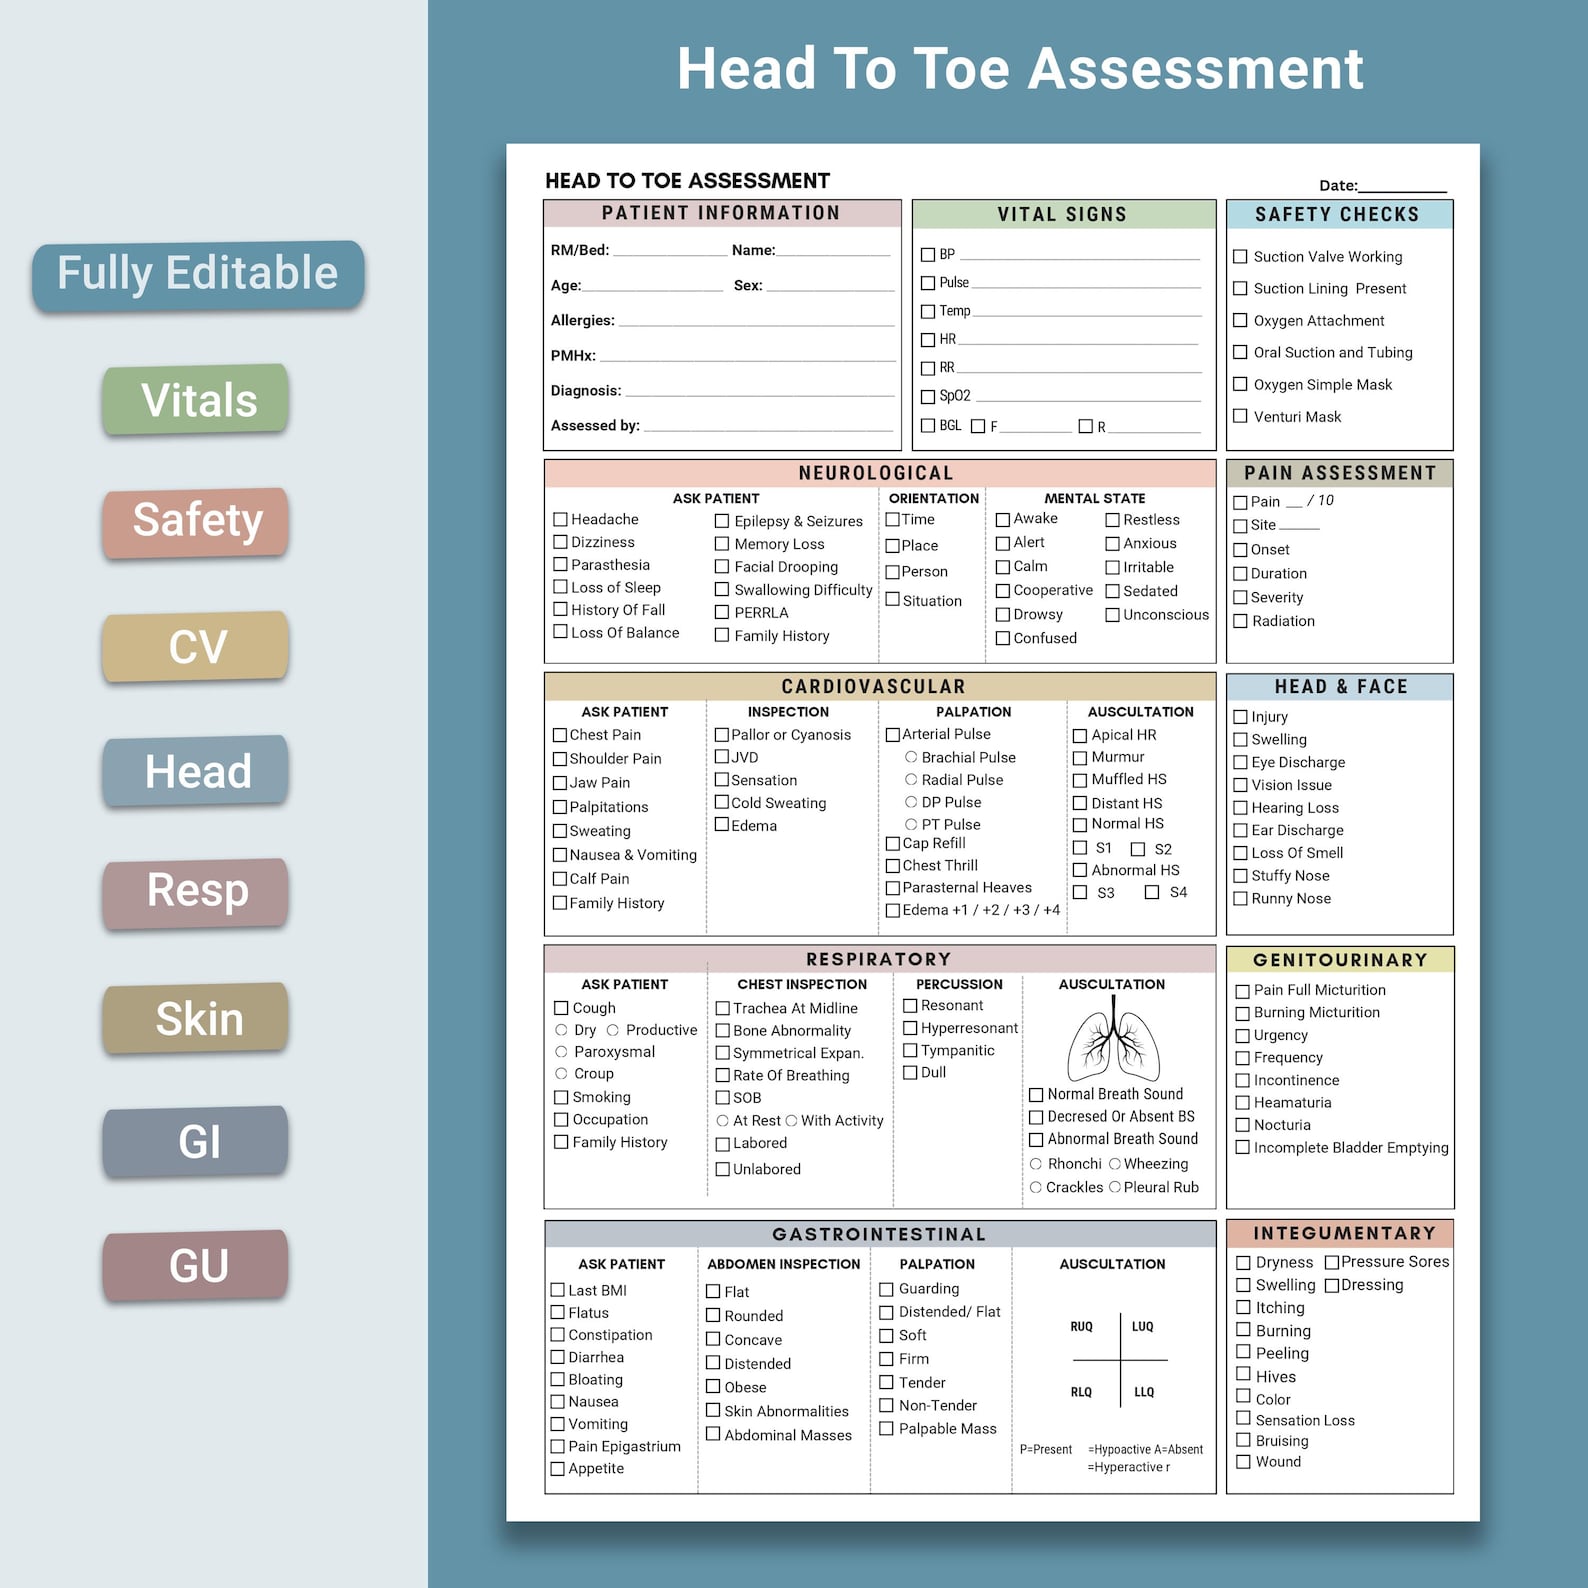
At its core, the template is a checklist organized by body region and system. It typically covers general appearance, vital signs, neurological status, head and face, eyes and vision, ears and hearing, nose and sinuses, mouth and throat, neck, cardiopulse system, respiratory system, abdomen, extremities, skin, and then back and neurological reassessment depending on your setting. Different institutions modify this based on their protocols and the patient population they serve. What most people don't realize is that the template's real value isn't in documentation compliance. It's in ensuring you don't miss things because you're tired or distracted. The structure forces a sequence that prevents cognitive shortcuts. When you skip the sequence and just do whatever feels urgent, you start missing findings that show up later in subtle ways.
How to Actually Use This Without Hating Your Life
Here's the practical approach I learned after burning through too many half-complete assessments. Start with general survey and vital signs. Don't rush this part. The first thirty seconds of looking at a patient in distress tells you more than any single system check will. Work your way down methodically but stay flexible. If you find something abnormal, document it there and then rather than circling back later. Your brain will not remember those details accurately after you've moved on to three other patients. The key insight most beginners miss is that the order matters less than you'd think, but the completeness matters enormously. I've seen experienced clinicians go head to toe efficiently while simultaneously gathering information from multiple systems because they were competent enough to assess cardiac sounds while palpating the abdomen, or check pupillary response while noting general appearance. That's efficiency. But you can't skip sections entirely and call it efficient. When I was doing floor assessments, I ran into a persistent problem with patients who had extensive peripheral edema in both legs. The template had a section for extremity assessment that basically said "check pulses, capillary refill, edema." Standard approach wasn't catching the asymmetry because both legs had similar swelling levels. What worked for me was measuring calf circumference at a consistent point above the patella and comparing left to right. A difference of more than two centimeters flagged deep vein thrombosis risk much earlier than pulse checks ever did. I added this to my personal template and it caught two DVTs in six months that I genuinely believe would have been missed otherwise.
Get the Full Details
Common Mistakes That Make the Template Useless
The biggest mistake I see is treating the template as a box-checking exercise rather than a diagnostic tool. You can fill out every field perfectly and still miss the diagnosis. Documentation that reads "lungs clear to auscultation" without noting respiratory rate, effort, or symmetry of chest expansion is technically complete and clinically useless. Rate and effort tell you more about respiratory status than whether you heard crackles or wheezes. Another persistent issue is the assumption that normal findings don't need documentation. If you documented nothing about the lower extremities, the medical record shows you didn't assess them. Period. Normal findings deserve explicit notation. "Cranial nerves II through XII grossly intact" is a valid and important statement. It means you actually tested or observed those functions rather than skipping over them because the patient looked fine. There's also the problem of temporal context. A head to toe assessment captures a snapshot in time. It doesn't track changes. I've lost count of how many times a nurse documented a neuro check as normal, the patient deteriorated three hours later, and the medical team had no baseline to compare against because the previous assessment didn't include specific details like pupillary size in millimeters or motor strength graded on the standard scale.
Advanced Nuances You Won't Find in Textbooks
One counter-intuitive point: you should frequently reassess the abdomen early in your exam, not late. If you save it for the end, the patient's discomfort from your stethoscope on their chest and your hands on their legs can make abdominal palpation artificially tense. You get false findings of guarding or rigidity. Palpate the abdomen before you do anything that might increase abdominal tension. Another thing that catches people off guard is the relationship between cardiovascular and respiratory assessment. Listen to lung bases before you assess cardiac function. Basilar crackles are easily missed when you're focused on heart sounds, and they're often the first indicator of early congestive heart failure. The template lists these as separate sections, but in practice they inform each other constantly. A patient with bilateral crackles and a S3 gallop is a completely different clinical picture than one with clear lungs and a murmur.
Where This Approach Breaks Down Completely
The head to toe model assumes a standard anatomical arrangement and a cooperative patient. It fails when neither condition exists. In trauma situations, the primary survey follows ABCDE protocol, not head to toe. Starting with the head in a polytrauma patient can be lethal because you're ignoring airway and breathing. Some institutions have separate trauma assessment pathways for this reason. The model also struggles with pediatric patients because the sequence doesn't match their developmental presentation. A terrified toddler will not tolerate a head-to-toe approach. You start with the least invasive observations and work toward more intrusive procedures, which often means ending at the ears and throat rather than starting there. The template structure needs significant modification for pediatric populations. For patients with multiple chronic conditions and complex comorbidities, the template can create a false sense of comprehensiveness. You can check every box and still miss the interaction between conditions that matters most for that specific patient. A diabetic patient with foot ulcers and peripheral vascular disease needs a vascular assessment that goes well beyond pulse checks and capillary refill. The standard template doesn't accommodate that depth without customization.

Practical Download and Implementation
Most hospitals provide their own institutional versions of the head to toe assessment template through their electronic health record systems. If you're in an academic setting, your program likely has a standardized form you're expected to use. For independent practitioners or students wanting a solid baseline, I'd recommend starting with a custom-built template based on the Joint Commission's recommended assessment domains and adjusting it based on your specific patient population. The template I ended up using consistently was a modified version that incorporated the standard head-to-toe structure but added fields for pain assessment, functional status changes, and patient-specific risk factors. It ran about two pages for inpatient assessments and took roughly twelve to fifteen minutes to complete thoroughly for a stable patient. Unstable patients require more time obviously, but the structured format actually speeds you up because you know exactly what to document and where rather than deciding in real time what information is relevant. If you're building your own, keep it to the essential fields. Every extra checkbox that doesn't change clinical decision-making just becomes noise. I've seen templates with forty-two fields where only fourteen actually influenced treatment decisions. The rest were documentation theater.
Bottom Line
The head to toe assessment template works when you treat it as a clinical reasoning tool rather than a bureaucratic requirement. The systematic approach prevents errors of omission. The documentation creates a baseline for future comparisons. But neither of those benefits materialize if you're going through the motions without actually assessing. Fill out the template properly, document normal findings explicitly, respect the sequence for clinical reasons not administrative ones, and customize it when the standard version doesn't fit your patient population. That's all there is to it.