Abdominal Assessment Order: Why Sequence Matters More Than Anything Else
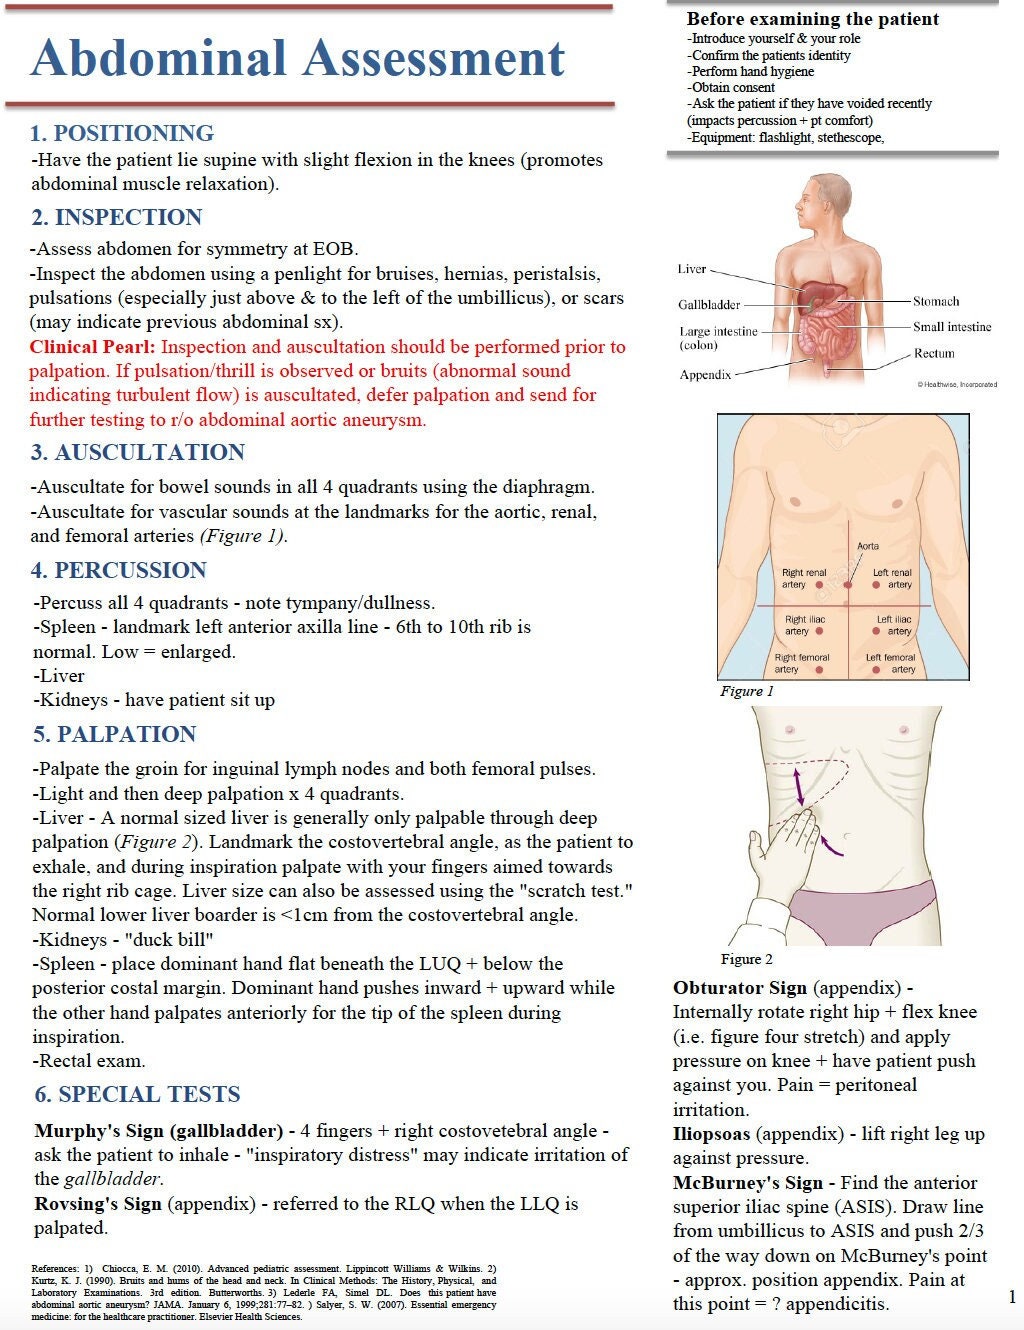
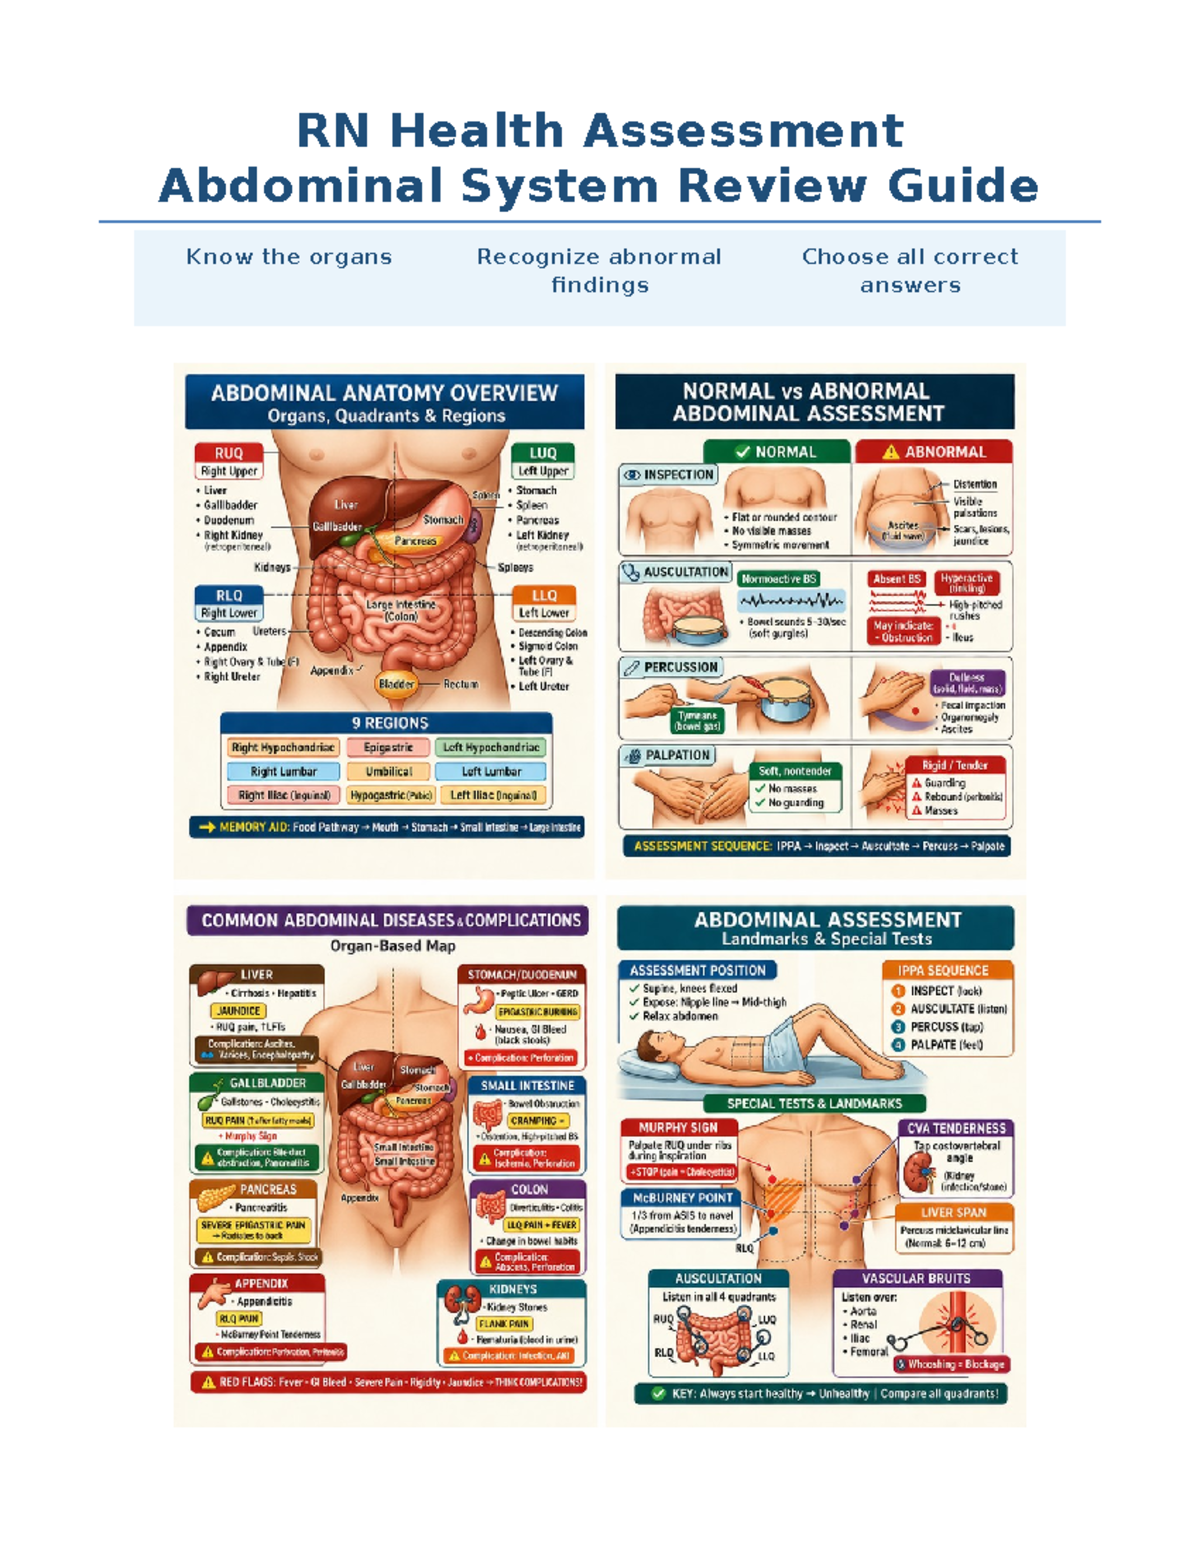
The standard Health Abdominal Assessment follows a strict sequence: inspection, auscultation, percussion, then palpation. This isn't tradition for its own sake. Palpating the abdomen first changes everything. It makes the patient guard their muscles, tenses the rectus sheath, and masks tenderness that auscultation and percussion would otherwise reveal. If you palpate before listening, you're going to miss bruits, you'll get garbage bowel sound data, and your percussion notes will be unreliable because the patient won't relax enough for resonant versus dull to be meaningful. I ran into this exact problem last year with a post-op cholecystectomy patient who had been through three different nurses' assessments before my shift. Each one had palpated first. When I listened before touching, I caught a high-pitched metallic tympany consistent with a partial small bowel obstruction that the earlier nurses had dismissed as "post-surgical gas." The auscultation finding alone got us a CT ordered three hours earlier than it would have happened otherwise. We caught the complication before it became a re-operation.
Health Abdominal Assessment: The Practical Breakdown
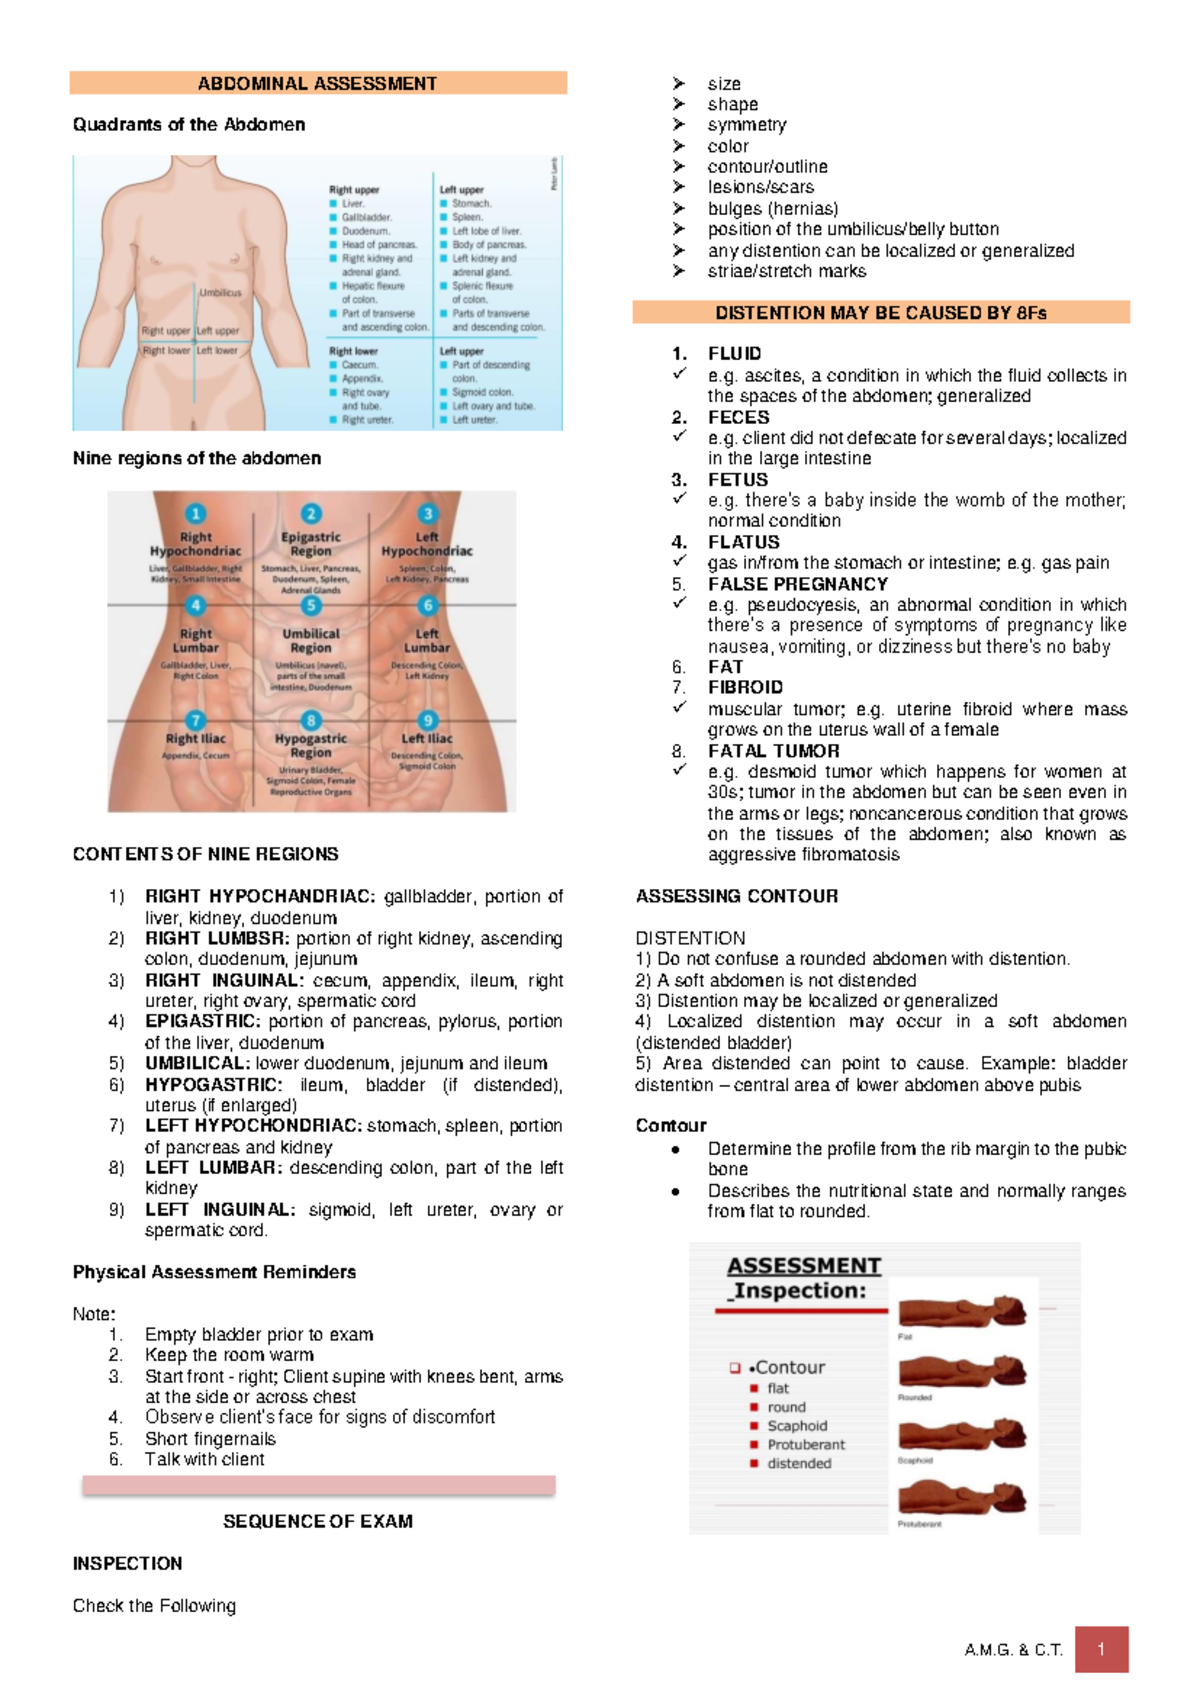
Inspection starts with the patient supine, arms at their sides, abdomen exposed from xiphoid to pubis. You want room lighting, not a dark exam room. Look for contour: scaphene, flat, rounded, or protuberant. Note asymmetry, visible peristalsis, scars, striae, umbilical appearance, and any pulsations. A pulsatile midline mass in an older patient should trigger immediate vascular concern. Don't skip looking at the flanks for Cullen's or Grey Turner's sign — those bruising patterns indicate retroperitoneal hemorrhage and show up days after the actual bleed. Auscultation uses the diaphragm for bowel sounds and vascular bruits, the bell for venous hums. Normal bowel sounds occur 5 to 30 times per minute. Hypoactive sounds (fewer than 5) suggest ileus, peritonitis, or late obstruction. Hyperactive, high-pitched sounds with clicking or rushing indicate early mechanical obstruction. Listen for at least 60 seconds in each quadrant before calling sounds absent. What you're actually checking for is whether the gut is working or if something is physically blocking it. For vascular auscultation, listen over the aorta (midline between xiphoid and umbilicus), renal arteries (lateral to aorta at L1-L2 level), iliac arteries (midway between ASIS and pubic symphysis), and femoral arteries just below the inguinal ligament. A systolic bruit over the renal artery in a hypertensive patient warrants a renogram or CT angiography. Don't confuse a transmitted carotid sound with a renal bruit — lean the patient forward slightly and relisten; if the sound disappears, it was transmitted, not generated at the renal artery.
Percussion establishes baseline resonant tones across all four quadrants. Dullness over the liver span (right midclavicular line, roughly 6 to 12 cm), the spleen (left 9th to 11th intercostal space, anterior axillary line), and the bladder (suprapubic when full) is normal. The unexpected finding is new dullness somewhere else, or altered liver span. A liver edge palpable below the costal margin with dullness extending 15 cm upward suggests hepatomegaly; the reverse — hyperresonance replacing liver dullness — points to subphrenic free air from a perforated viscus. Percussion over the midline above the symphysis pubis distinguishes urinary retention from constipation. Full bladder = suprapubic dullness. Distended sigmoid colon = often more tympanic. A quick water-fluctuation test (ballottement) can confirm large-volume ascites when the exam is equivocal. Tap one flank with your fingertips and press firmly on the opposite flank — if you feel a fluid wave travel across, you've got ascites. It only works reliably with moderate to large volumes, so a negative doesn't rule it out at low volumes. Palpation is light first, then deep. Light palpation (about 1 to 2 cm depth) detects surface tenderness, guarding, and superficial masses. Deep palpation (7 to 10 cm) assesses organ size, deeper masses, and rebound. Always palpate the painful area last. If the patient points to right lower quadrant pain, start in the left upper quadrant and work clockwise, finishing at McBurney's point.
Get the Full Details

Guarding is either voluntary or involuntary. Voluntary guarding is the patient clenching because they're anxious or ticklish — you can distract them by having them bend their knees and take slow breaths, then re-palpate. Involuntary guarding is a reflex from peritoneal irritation. It doesn't respond to distraction. The difference matters because voluntary guarding gets you a nervous patient; involuntary guarding gets you an acute abdomen workup. Rebound tenderness (Blumberg's sign) is tested by slowly depressing the abdominal wall several centimeters away from the suspected area and releasing quickly. Pain on release, not on pressure, indicates peritoneal inflammation. The test is uncomfortable and often unnecessary if you've already identified localized tenderness through direct palpation. I stopped using it routinely years ago because it adds patient distress without adding diagnostic value in most cases. If focal tenderness is present on light palpation, you already know the peritoneum is irritated.
Edge Cases Where the Standard Approach Breaks Down
Obese patients are the most common problem. Adequate fat layer makes light palpation nearly impossible and deep palpation requires aggressive force that still doesn't reach visceral structures reliably. In these patients, percussion becomes your primary tool for liver span and splenic dullness. Ballottement of the kidney and liver becomes essential. I learned to use the heel of my hand for deep compression in patients with significant adipose tissue — it distributes pressure more evenly than finger pads and can reach deeper structures without causing the patient excessive discomfort. Pregnant patients require modified technique. The gravid uterus displaces abdominal organs, changes resonance patterns, and makes palpation of the uterus itself the priority over organ assessment. Fundal height measurement replaces liver span estimation in the third trimester. Bowel sounds are often pushed cephalad and may sound different due to displacement, which is normal and not pathological. You also need to avoid supine hypotensive positioning — tilt the patient left or use a wedge under the right hip. Post-surgical patients present a special challenge. Incisional tenderness makes palpation difficult and can produce false-positive guarding. The incision site itself will be tender regardless of underlying pathology. Start palpation far from the incision and work toward it. Sutures and staples change percussion notes locally. A surgical patient with new-onset diffuse tenderness and absent bowel sounds 48 hours post-op has a different differential than one with the same findings on day 7. Timeline changes everything.
One specific edge case I encountered involved a patient with a massive ventral hernia. The hernia sac contained bowel loops, making the abdominal contour obviously abnormal, but the real problem was that the hernia rim created a ring of firm resistance around the defect. I initially mistook the hernia border for organomegaly on palpation until I traced it back to the fascial defect. The workaround was simple: have the patient cough or bear down while you palpate. The hernia contents will push against your fingers at the defect margin, making the fascial ring unmistakable. Once you identify the ring, you know what you're feeling is the hernia boundary, not an enlarged organ.

Common Pitfalls That Beginners Keep Making
The biggest mistake is rushing auscultation. Bowel sounds are variable. A quiet interval of 15 to 30 seconds is normal. Calling sounds absent after 10 seconds of listening is incorrect. The second biggest mistake is palpating the epigastrium before the patient has warmed their hands or had a moment to adjust to the exam table. Cold hands trigger immediate guarding that lasts for minutes. I keep a warming cabinet for my stethoscope and always rub my hands together before touching an abdomen. It sounds trivial but it cuts examination time significantly because the patient relaxes faster. Another pitfall: not having the patient empty their bladder before assessment. A distended bladder sits in the suprapubic region and mimics a mass on palpation and creates dullness on percussion. It's easily confused with a uterine fibroid, ovarian cyst, or pelvic abscess. A quick ultrasound or even a bladder scan eliminates this confusion in seconds. I now ask every ambulatory patient to use the restroom before the exam as a standard step. It prevents misinterpretation and usually makes the abdominal exam more comfortable for the patient anyway.
Limitations and When to Stop
Physical examination of the abdomen has well-documented sensitivity and specificity limits. Palpation detects liver enlargement with about 50 to 60 percent sensitivity compared to imaging. Splenic enlargement is similarly unreliable by palpation alone. Percussion for ascites detects roughly 100 mL or more but frequently misses smaller volumes that ultrasound will catch immediately. The physical exam is a screening tool, not a definitive diagnostic one. If the physical assessment is equivocal, if you find a mass you cannot characterize, if there are red flag findings like unexplained weight loss, anemia, or persistent vomiting, or if the patient has known malignancy with new abdominal symptoms — stop guessing and order imaging. Ultrasound is the first-line modality for most abdominal assessments. CT with contrast provides more detail for retroperitoneal and vascular evaluation. The physical exam tells you where to look and how urgent it is; imaging tells you what you're actually looking at. I once spent 20 minutes trying to characterize a left upper quadrant mass through palpation in an elderly patient with a history of lymphoma. The mass was deep, the patient was obese, and my fingers weren't giving me useful information. I ordered a stat ultrasound instead and identified a 4 cm splenic lesion in under five minutes. The lesson was straightforward: when your hands can't figure it out, don't spend more time with your hands. Switch modalities.