The Practical Reality of Patient Evaluation
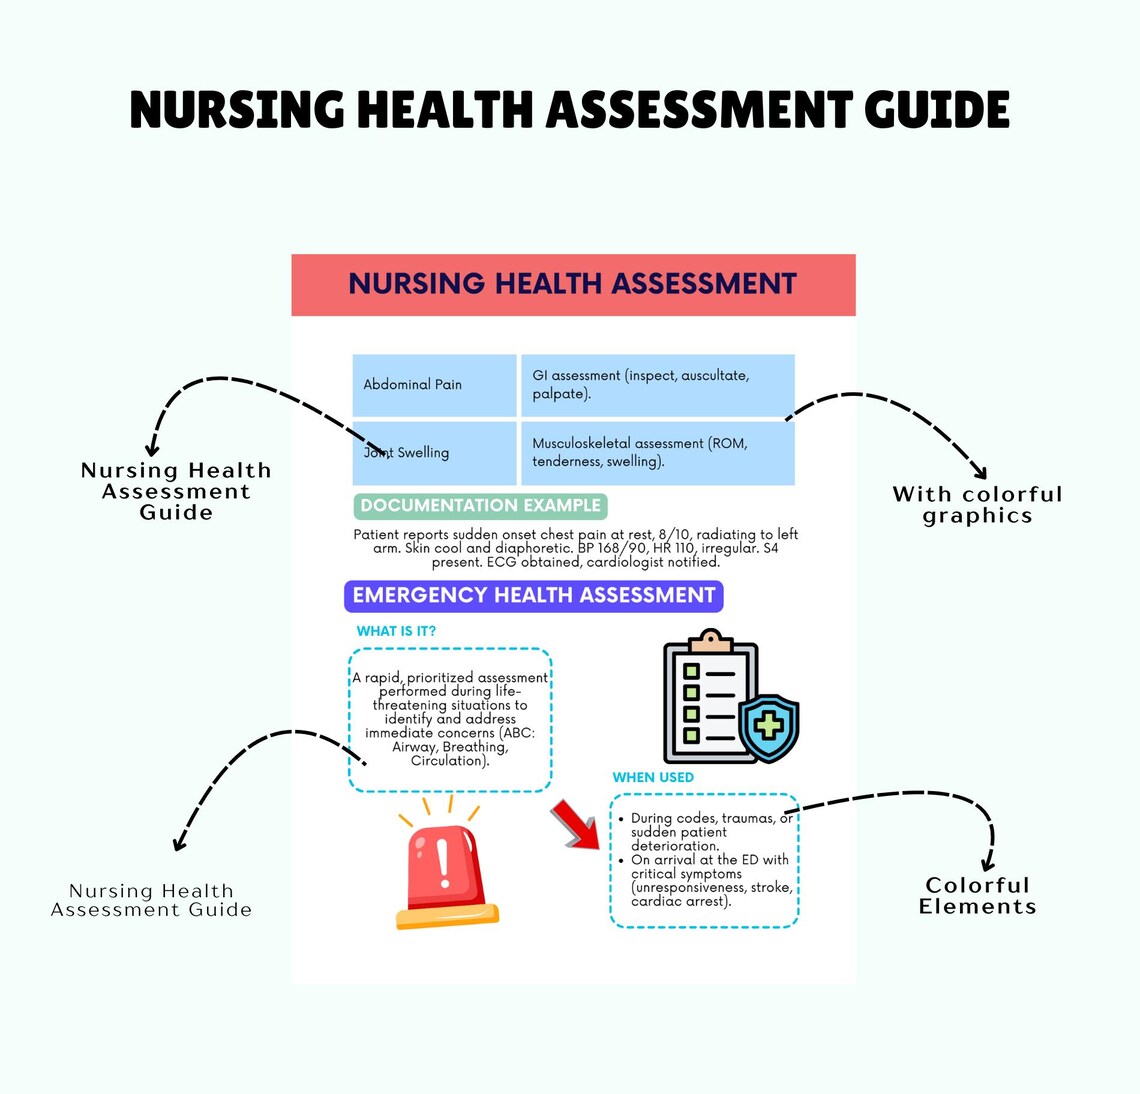
Most people think health assessment is just filling out forms and checking boxes. It is that, but also something much messier. I learned this early on when a patient's vitals looked fine on paper but their skin was cool and mottled, their capillary refill was 4 seconds, and they barely responded to verbal commands. The numbers didn't tell the full story. I relied on the gestalt of them looking clinically unwell instead. That saved the order for a stat lactate and a sepsis workup before their blood pressure even dropped. Health Assessment In Nursing is the systematic collection of subjective and objective data about a patient's health status. It is not a single event. It is ongoing, iterative, and usually happens in parallel with actual care delivery rather than as a separate structured activity. The subjective component comes from the patient or their family. The objective component comes from your observations, vital signs, and physical examination findings. Both are essential. Neither is sufficient alone.
Conducting a Health Assessment In Nursing: Step by Step
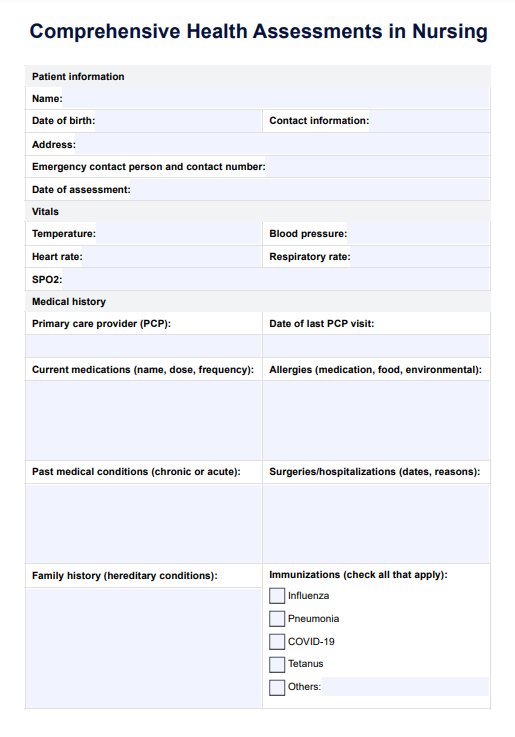
Start with the chief complaint and history of present illness. Don't rush this. A complete HIPPE provides more signal than any screening tool. Onset, location, duration, characteristics, precipitating factors, exacerbating factors, and associated symptoms. Take four minutes here and you might save twenty minutes of wrong-direction work later. Move to past medical history, medications, allergies, and social history. I always check the medication list against what the patient actually reports taking. Discrepancies show up in roughly 30 to 40 percent of admissions according to several studies. A patient may not know the correct dose, may have stopped a medication on their own, or may be taking over-the-counter supplements that interact with prescribed drugs. Flag everything and verify when possible. Then do the physical exam. Head to toe is the standard sequence because it reduces the chance of skipping a system. Palpateinspect. Auscultatepercuss where relevant. Know which findings matter most for which conditions. A unilateral decreased breath sound on the right side with tracheal deviation to the left is a tension pneumothorax until proven otherwise, not a case for watchful waiting.
Document as you go or immediately after. Memory degrades fast in busy clinical environments. I used to rely on my mental notes during a shift and then try to write everything at the end. That approach collapsed during a night where I had six admissions. I missed documenting a crucial skin breakdown finding on one patient, and by morning the wound was Stage 3. After that, I carried a small notebook and jotted key findings in real time, then transferred to the official chart within ten minutes of finishing each assessment. This cut documentation errors significantly and kept my notes honest.
Get the Full Details

What Beginners Miss About Clinical Evaluation
One thing that catches most new nurses off guard is that the textbook presentation of disease is actually the exception, not the rule. Elderly patients frequently present with atypical symptoms. A urinary tract infection might show up as confusion without fever or dysuria. Myocardial infarction can present as isolated fatigue or nausea in older adults and women. If you wait for classic textbook presentations, you will miss diagnoses. Another counter-intuitive point is that a normal vital sign does not rule out serious pathology. I worked a shift where a patient had a blood pressure of 128 over 82, a heart rate of 78, and an oxygen saturation of 98 percent on room air. They had abdominal pain radiating to the back, a pulsatile abdominal mass on palpation, and a history of smoking and hypertension. The normal vitals were misleading. The aortic aneurysm was leaking. Early recognition came from the physical exam and clinical suspicion, not from the monitors. Normal vitals in a symptomatic patient should raise your level, not lower it. A third nuance is that assessment tools have limited sensitivity in certain populations. The pain scale, for example, depends heavily on the patient's ability to self-report and their willingness to disclose discomfort. Nonverbal patients, cognitively impaired patients, and those from cultural backgrounds where stoicism is valued will not reliably use a numeric rating scale. I switched to using the FLACC scale for nonverbal adults when appropriate and paid attention to behavioral cues like guarding, grimacing, and restlessness. These indirect markers often reveal more than a self-reported number ever could.
Common Pitfalls and How to Avoid Them
Confirmation bias is the biggest threat to accurate assessment. Once you form an initial impression, your brain naturally seeks information that supports that impression and discounts information that contradicts it. This is especially dangerous when handoff communication already plants a seed. If the outgoing nurse says the patient is just anxious and has a history of panic attacks, you might underweight genuine cardiac or pulmonary findings. I make it a habit to intentionally look for evidence that contradicts my initial hypothesis before finalizing my assessment impression. Another common error is insufficient time allocation. Some facilities expect a full admission assessment within 8 hours, but a thorough assessment with proper documentation often requires 45 to 90 minutes depending on patient acuity and complexity. Rushing this process leads to missed findings and incomplete baselines. When I have been stretched thin, I prioritize the most clinically relevant systems first, document core findings immediately, and return for a more detailed examination once the acute situation stabilizes. Completing the full assessment within the first shift is better than filing an incomplete one and forgetting about it. There is also the problem of over-reliance on technology. Pulse oximetry can be inaccurate with poor peripheral perfusion, dark nail polish, motion artifact, and certain hemoglobin variants. Blood pressure cuffs that are too narrow or too wide give falsely high or low readings. Point-of-care testing like glucometers has acceptable margins of error but can drift without proper calibration. I cross-check critical values with laboratory results when possible and correlate technology readings with clinical context rather than accepting them at face value.
When Standard Assessment Falls Short
No assessment framework captures every relevant variable. A standard head-to-toe approach may miss subtle neurological changes in a patient with a baseline cognitive impairment. It may underweight psychiatric contributors to physical symptoms. It may not adequately address cultural or spiritual factors that influence health behaviors and treatment adherence. I add focused components based on context rather than treating the standard template as universally sufficient. For patients with chronic conditions, establishing a true baseline requires comparing current findings against previous assessments whenever those records are available. Without that comparison, you cannot accurately determine whether a change in weight, edema, or lung sounds represents a new problem or expected progression of a known disease. I always pull prior assessment data when it exists and note deviations explicitly in my documentation. The documentation itself is part of the assessment process and deserves attention. Charts serve legal, clinical, and continuity purposes. Incomplete or vague entries create liability and increase the risk of medical errors during handoffs. I use standardized frameworks like SOAP or DAR for structuring my notes, but I ensure each section contains specific, observable data rather than generic statements. "Patient reports pain" is not useful. "Patient reports sharp right lower quadrant pain rated 7 out of 10, radiating to the right groin, onset 3 hours ago, exacerbated by movement and palpation" is actionable.

Communication with the interdisciplinary team is where assessment data becomes clinical action. A well-documented assessment means little if the relevant findings do not reach the right providers in a timely manner. I use SBAR for briefings and ensure that abnormal or changing findings are communicated verbally in addition to being documented, because written notes are not read in real time by everyone who needs that information.