What This Actually Looks Like When You're Doing It
A Health Comprehensive Assessment isn't some magical diagnostic tool that produces a perfect picture of a patient's health on the first pass. It's a structured collection process, and most people who hear about it for the first time imagine it's something more authoritative than it really is. You take a patient's history, you run through physical findings, you look at labs and imaging, you assess functional status and psychosocial factors, and then you try to synthesize all of that into a workable clinical plan. That's it. The devil is entirely in the execution. I've been doing these for over a decade across different clinical settings, and the ones that frustrate me aren't the medically complex patients. They're the ones where the assessment itself is incomplete because someone checked boxes without actually listening. I had a patient recently where the initial Health Comprehensive Assessment came back essentially blank on the psychosocial domain because the nurse who started the process pulled up the standard template and moved through it too fast. The patient had just been discharged from an inpatient stay three days prior and was clearly struggling with medication adherence and financial stress, but none of that was captured. I caught it because I read the note rather than just scanning the flags. The workaround was straightforward but time-consuming: I scheduled a dedicated 30-minute follow-up visit specifically for the psychosocial portion and used open-ended questions instead of relying on the template checkboxes. It added about 45 minutes to the total process but fundamentally changed the care plan for that patient.
The Health Comprehensive Assessment Breakdown
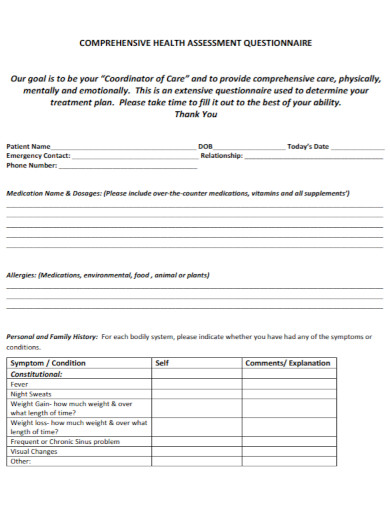
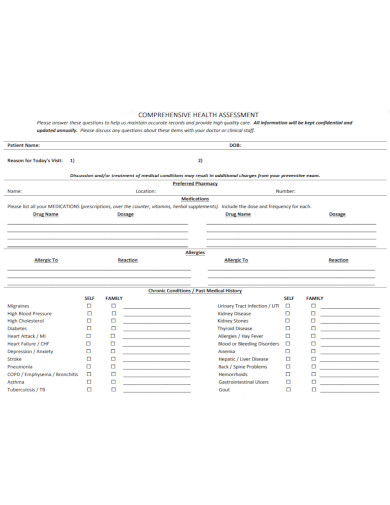
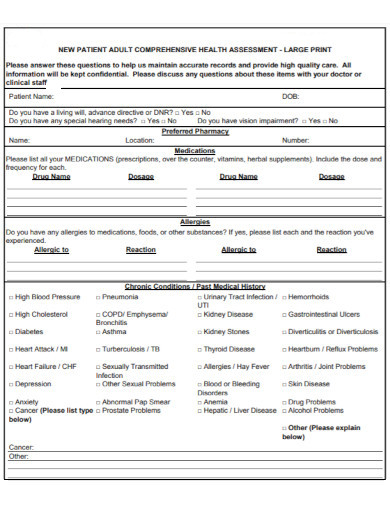
The standard components are familiar territory for anyone in clinical practice. You've got the chief complaint and history of present illness, which most people handle reasonably well. Then the past medical history, surgical history, medication list with dosages and adherence notes, allergy documentation, family history with actual disease states rather than vague labels like "heart problems," and social history that goes beyond smoking and drinking to cover occupation, living situation, care supports, health literacy, and access barriers. The review of systems should be targeted based on the presenting complaint rather than a rote head-to-toe read-through. Physical examination findings need to be documented with specificity. Laboratory and diagnostic results get pulled together. Functional assessment using tools like the Katz index or Barthel index when relevant. Cognitive screening with something like the MoCA or MMSE in appropriate populations. Nutritional status evaluation. Pain assessment. Mental health screening. And then the synthesis, which is where most assessments fall apart. Here's something most beginners miss: the synthesis step is not the same thing as listing every abnormal finding and hoping the treatment plan writes itself. I watched a colleague once compile a 12-page assessment for a geriatric patient with diabetes, hypertension, mild cognitive impairment, osteoarthritis, and depression, and then the plan section was literally two sentences recommending "continue current medications and follow up in three months." That's not a comprehensive assessment. That's a data dump. The synthesis needs to prioritize. You identify which problems are driving the patient's current state, which are stable and just need monitoring, and which are iatrogenic—caused or worsened by the treatment of other conditions. In that same patient's case, the polypharmacy was likely the biggest issue. The antihypertensive regimen was causing orthostatic symptoms that were being misattributed to "aging," which was then feeding into the fall risk and limiting her functional status. Fixing the medication order would have addressed multiple problems at once instead of treating each one separately. Another counter-intuitive point that people don't always grasp: a comprehensive assessment is not inherently better than a focused one when the clinical question is narrow. If you're following a stable type 2 diabetic at a six-month recall visit, running a full comprehensive assessment with the same depth as an initial visit is often wasteful and can actually introduce noise. You're more likely to pick up incidental findings that lead to unnecessary follow-up testing, which is the whole cascade that drives up costs without improving outcomes. The guideline-recommended approach for routine follow-up of stable chronic conditions is a targeted assessment that checks whether the management plan is working, whether new problems have emerged, and whether the patient's status has changed in any meaningful way. Comprehensive assessments have their place, usually at intake or when there's a significant change in clinical status, but they shouldn't be the default for every encounter.
There are also structural limitations worth being honest about. The assessment takes time. A properly done comprehensive assessment in a primary care setting runs 45 to 90 minutes depending on complexity and the clinician's familiarity with the process. Most reimbursement structures don't adequately compensate for that time, which creates a perverse incentive to rush through it or delegate meaningful portions to support staff who may not have the clinical training to recognize what's actually significant. There's also the documentation burden. Electronic health records weren't designed with comprehensive assessments in mind, and the template-driven approach that most systems force you into tends to produce checkbox medicine rather than thoughtful clinical evaluation. You'll see this everywhere: structured fields that look comprehensive on the surface but collapse nuanced clinical reasoning into dropdown menus and predefined categories. If you're looking to actually implement this rather than just understand the concept, the best starting point is a standardized framework rather than building your own from scratch. The USPSTF and various specialty societies have published guidance on what components to include for different patient populations. The geriatric comprehensive assessment is probably the most well-developed model, with established tools and validation data. For general adult populations, the WHO's Integrated Health Assessment tool is a reasonable starting framework. You can find downloadable versions and adaptation guides through their respective organizational websites. The key is to adapt the template to your specific clinical context rather than using it wholesale. A rural clinic serving an agricultural population needs different emphasis than an urban cardiovascular practice, and the assessment tools should reflect that. The hardest part is consistently doing good synthesis. I've found that writing a brief problem list with a one-sentence summary for each active issue before moving to the plan section forces you to actually think through what matters. It's an extra three to five minutes that makes a real difference in the quality of the resulting care plan. Most people skip straight from findings to orders, which is why so many comprehensive assessments end up looking like shopping lists rather than clinical reasoning documents.
Get the Full Details