How I Actually Document a Focused Abdominal Pain Exam
Most EHR templates for abdominal pain documentation are built for chief complaint tracking, not clinical reasoning. You fill in the preset fields, attach a photo if required, and call it done. But the quality of your documentation isn't measured by whether the template is complete. It's measured by whether another clinician can read your note and immediately understand the clinical picture without having been in the room.
Health Focused Exam Abdominal Pain Documentation requires a different approach than general abdominal assessment notes. I've spent years refining this, and the methods below come from dealing with chart reviews, quality audits, and the occasional medico-legal question.
The Method I Use Before Writing Anything Down
I don't start with the template. I start with a mental framework. The focused abdominal pain exam has a standard structure, but the documentation should reflect the actual clinical decision-making process. Here's the sequence:
Chief complaint with time parameters. Not just "abdominal pain." I document when it started, whether it was sudden or gradual, and what the patient was doing when it began. A 58-year-old female with epigastric pain that started 3 hours after a heavy meal and radiates to her back reads very differently from a 22-year-old male with crampy periumbilical pain that migrated to the RLQ over 12 hours. The history drives everything that follows.
Then I move to the relevant past medical, surgical, and social history. For abdominal pain specifically, I document prior abdominal surgeries (adhesions change everything), anticoagulant use (spontaneous retroperitoneal hemorrhage is a thing), recent trauma, alcohol intake, and pregnancy possibility in women of childbearing age. These four items alone can redirect an entire workup.
Review of systems gets trimmed to the relevant domains. GI: nausea, vomiting, bowel habit changes, hematochezia or melena. GU: dysuria, hematuria, frequency. Constitutional: fever, chills, weight loss. Cardiovascular: chest pain or palpitations. Pulmonary: cough or shortness of breath. I don't document the full ROS. I document the parts that are relevant to abdominal pain and their results. Positive findings get more space. Negative findings relevant to the differential get mentioned.
Now the physical exam. I follow the standard sequence: inspect, auscultate, percuss, palpate. I never skip auscultation before palpation. I've seen too many students and residents press on the abdomen first, then auscultate, and wonder why bowel sounds sounded off. The pressure changes motility. It's a basic but frequently violated principle.
Inspection covers distension, visible peristalsis, scars, masses, skin changes, and hernia sites. I document what I see in each quadrant, not just "abdomen normocontoured and non-distended." That phrase means nothing unless I specify what I actually looked for and didn't find.
Auscultation covers bowel sounds (present, absent, hyperactive, hypoactive), vascular sounds (bruits over the aorta, renal arteries), and any friction rubs. Again, I'm specific. "Bowel sounds present and normoactive in all four quadrants" is better than "bowel sounds present." "Systolic bruit heard over the left upper quadrant near the epigastrium" is worth far more than "vascular bruit noted."
Percussion covers tympany versus dullness, liver span, spleen size, and any areas of hypersonic resonance. It's an older skill that fewer clinicians use thoroughly anymore, but it adds information that palpation alone can't provide. A diffusely tympanic abdomen points toward obstruction or ileus. Localized dullness might indicate a mass or fluid collection.
Palpation is where most documentation falls short. I document light palpation findings first—superficial tenderness, muscle guarding, involuntary rigidity. Then deep palpation—organomegaly, masses, deeper tenderness. I specifically assess for rebound tenderness (Blumberg sign), the psoas sign, the obturator sign, and Murphy's sign when clinically indicated. Each positive finding needs its location and character documented.
For Health Focused Exam Abdominal Pain Documentation, I also include the pain characterization: location, radiation, quality, severity on a 0-10 scale, aggravating and alleviating factors, and temporal pattern. This goes in the history section but is critical for the exam interpretation.
A Specific Problem I Ran Into and How I Fixed It
Last year, I was covering a shift when a patient presented with intermittent mid-abdominal pain. My initial exam showed mild diffuse tenderness without peritoneal signs. Bowel sounds were present but somewhat hypoactive in the left lower quadrant. I documented accordingly and recommended observation with return precautions. The patient left against medical advice, returned 18 hours later with a rigid abdomen, and was taken for emergency surgery for a perforated viscus.
The chart review focused heavily on my initial documentation. The question wasn't whether I missed the diagnosis—I can't diagnose a perforation before the signs appear—but whether my documentation adequately conveyed the uncertainty and the plan. It didn't. I had written "abdomen soft with mild tenderness, no peritoneal signs" but hadn't documented the fluctuating nature of the pain or my explicit concern about early peritonitis that couldn't yet be demonstrated on exam.
After that case, I changed my approach. Now I document the dynamic nature of abdominal pain exams explicitly. If the exam is equivocal or evolving, I write something like: "Abdomen currently demonstrates mild diffuse tenderness without frank peritoneal signs. However, given the episodic severity and patient's risk factors, early peritonitis cannot be excluded. Plan includes serial abdominal exams every 4 hours with immediate escalation if peritoneal signs develop." This creates a clear timeline and shows that I recognized the limitation of a single exam point.
The workaround is simple but requires intention. I now document the exam as a snapshot in time, not an absolute truth. I note the limitations explicitly: what I couldn't assess due to pain or body habitus, what findings were equivocal, and what the plan is for re-evaluation. This protects the patient and the provider because it communicates clinical thinking, not just checklist completion.
Counter-Intuitive Insights Beginners Miss
First, the absence of bowel sounds does not equal a benign abdomen. A patient with a complete bowel obstruction may have hypoactive or absent sounds in certain segments while having hyperactive, high-pitched sounds in others. Documenting "absent bowel sounds" when you only heard them in two quadrants is inaccurate. I document the specific findings by quadrant: "hyperactive in RLQ, hypoactive in LUQ, absent in RUQ and LLQ." That tells a story.
Second, guarding versus rigidity is a distinction that matters legally and clinically. Voluntary guarding is a pain response to palpation. Involuntary rigidity indicates peritoneal inflammation. Many clinicians document both as "guarding" or "rigidity" interchangeably. They're not the same. I explicitly distinguish them in my notes because the management pathway diverges significantly. Voluntary guarding might respond to analgesia and reassessment. Involuntary rigidity warrants immediate surgical consultation.
Third, the pain score is almost useless in isolation. A "10 out of 10" pain score means different things depending on context. I document the pain score alongside the response to positioning, movement, and palpation. Does the pain worsen with coughing or jumping? That suggests peritoneal irritation. Does it improve with flexion of the hips? That might point to psoas pathology. The number matters less than the behavioral and positional context.
Fourth, hernia examination is routinely omitted from focused abdominal exams but is a common source of missed pathology. I check the inguinal canals, femoral regions, umbilicus, and any prior incision sites for bulging or tenderness. A small incarcerated inguinal hernia can present with vague abdominal pain and normal-appearing bowel sounds. If I don't look, I won't find it.
Where This Approach Falls Short
The focused exam documentation I described takes longer than filling in a template. A thorough neurovascular and abdominal assessment with proper quadrant-by-quadrant documentation can add 5 to 10 minutes to an encounter. In a busy clinic setting with 15-minute slots, that's significant.
The documentation also depends on the examiner's skill. A careful hand is necessary to distinguish voluntary from involuntary guarding, to detect subtle organomegaly, to appreciate the difference between tympany and dullness on percussion. These are learned skills, not template skills. Two clinicians examining the same patient can legitimately document different findings. That's a limitation of the entire physical exam enterprise, not just the documentation.
Electronic health record systems often don't support the granularity I find necessary. Drop-down menus force binary choices. Free text fields are either too small or skipped entirely. I've worked around this by creating custom smart phrases or abbreviations in my EMR that expand to the detailed language I want in the permanent record. It's a workflow adjustment, but it makes the documentation actually useful.
When the exam is truly limited—obese patient, uncooperative patient, acute surgical abdomen where detailed palpation causes unacceptable pain—the focused documentation should explicitly state those limitations. "Examination limited by patient body habitus and pain avoidance. Superficial tenderness noted in all quadrants. Deeper assessment deferred. Recommend CT abdomen and pelvis with contrast for further evaluation." This is honest documentation and it guides the next step appropriately.
For patients where the focused exam doesn't reach a conclusion, additional imaging or laboratory studies become the documentation priority. I make sure to link the exam findings to the order rationale. If I ordered a CT because of localized tenderness in the right lower quadrant with hypoactive bowel sounds in that area, I state that connection in the note. It shows clinical reasoning, not shotgun testing.
The most important thing I've learned is that documentation isn't about protecting against malpractice. It's about communicating with the next clinician who sees this patient. Whether that's the resident covering night float, the surgeon in the ER, or the specialist you're referring to. Good Health Focused Exam Abdominal Pain Documentation makes that handoff seamless. Bad documentation creates gaps that the next provider has to fill in, and gaps are where errors happen.
Gallery Health Focused Exam Abdominal Pain Documentation
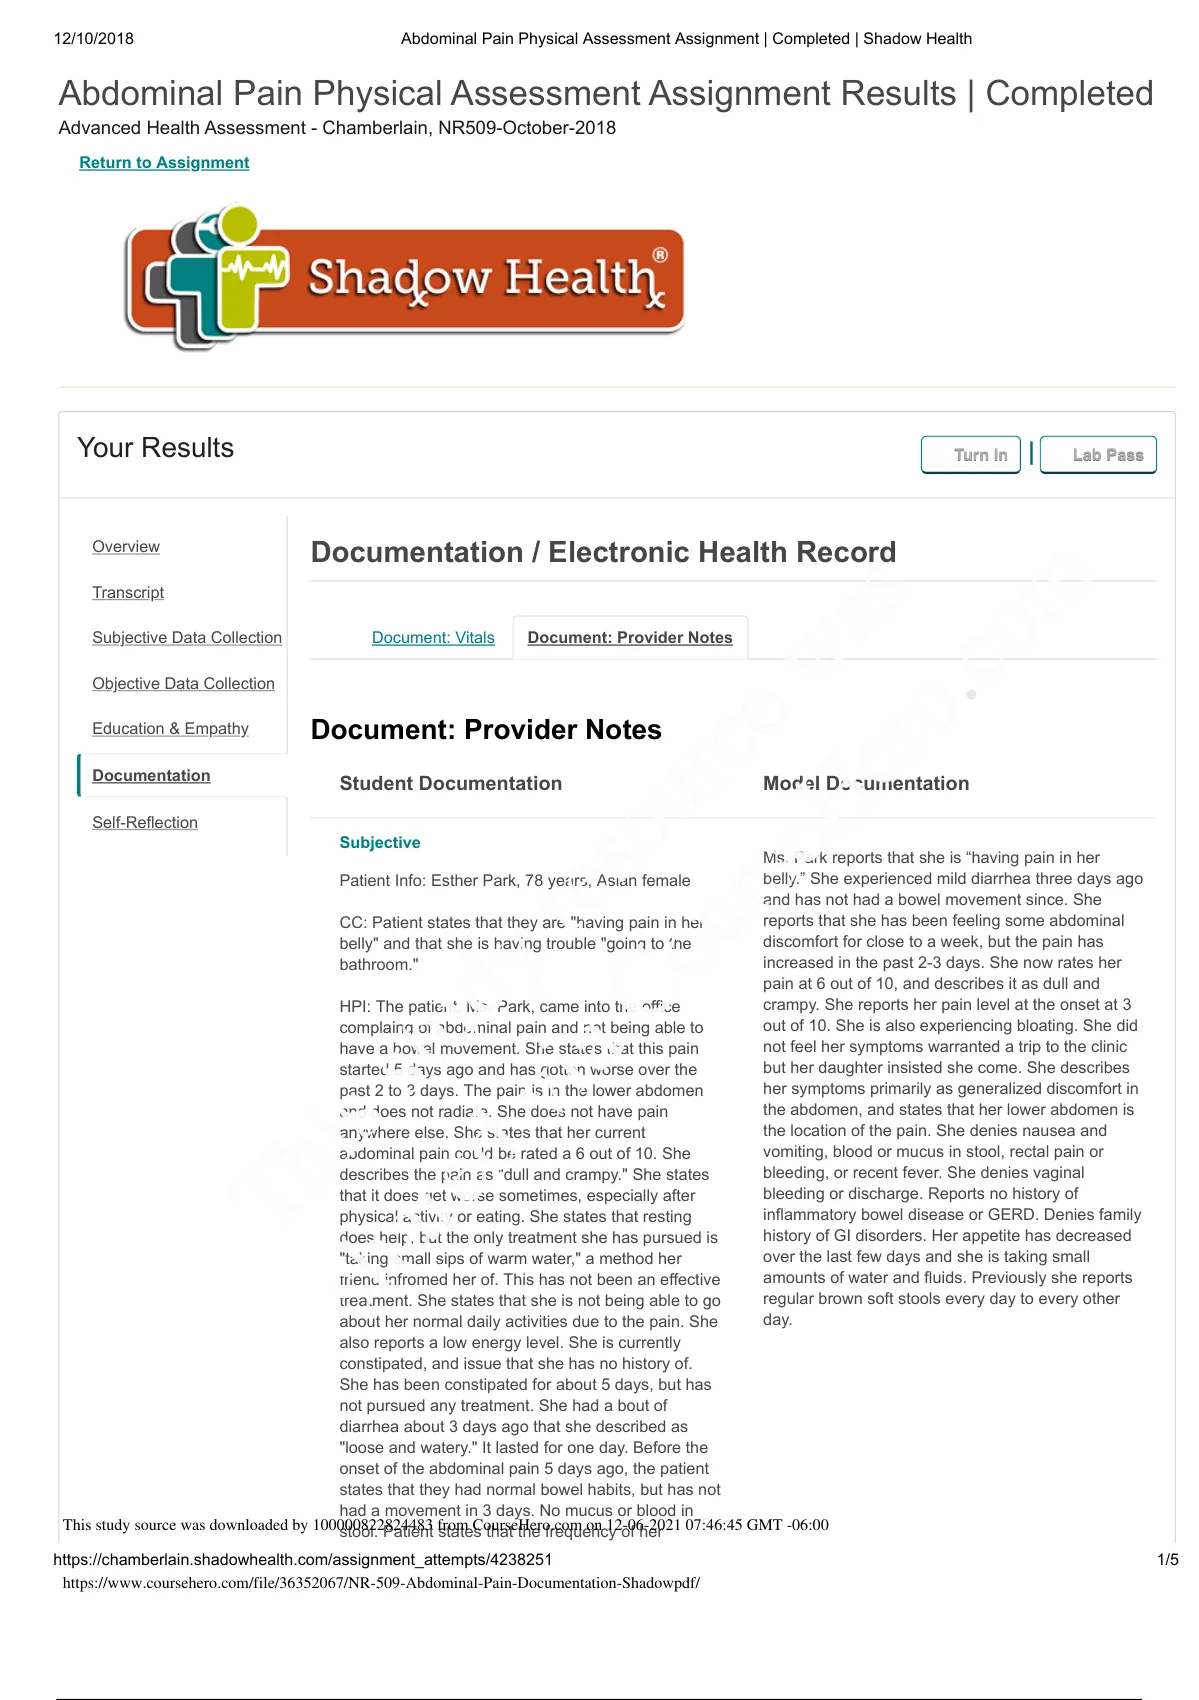
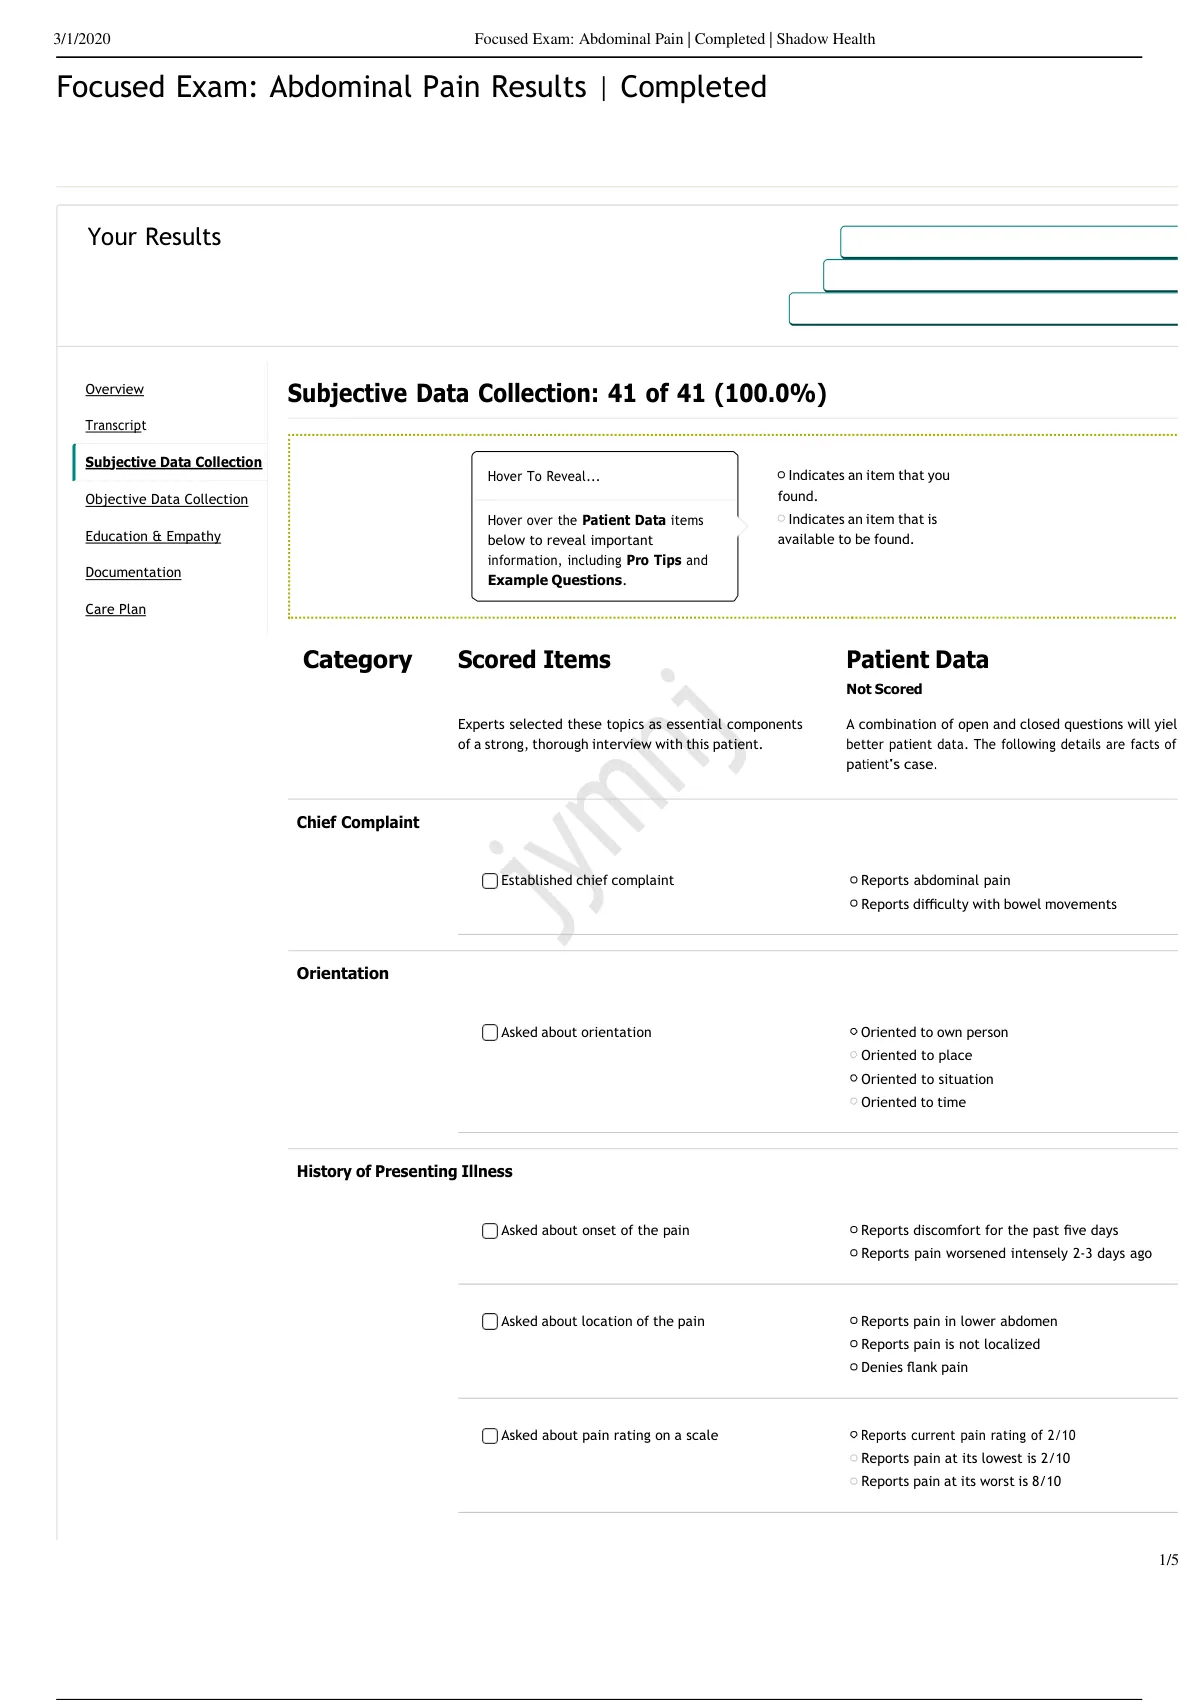
Focused Exam Abdominal Pain | Subjective Data| Esther Park (2022/2023) - Shadow health - Stuvia US
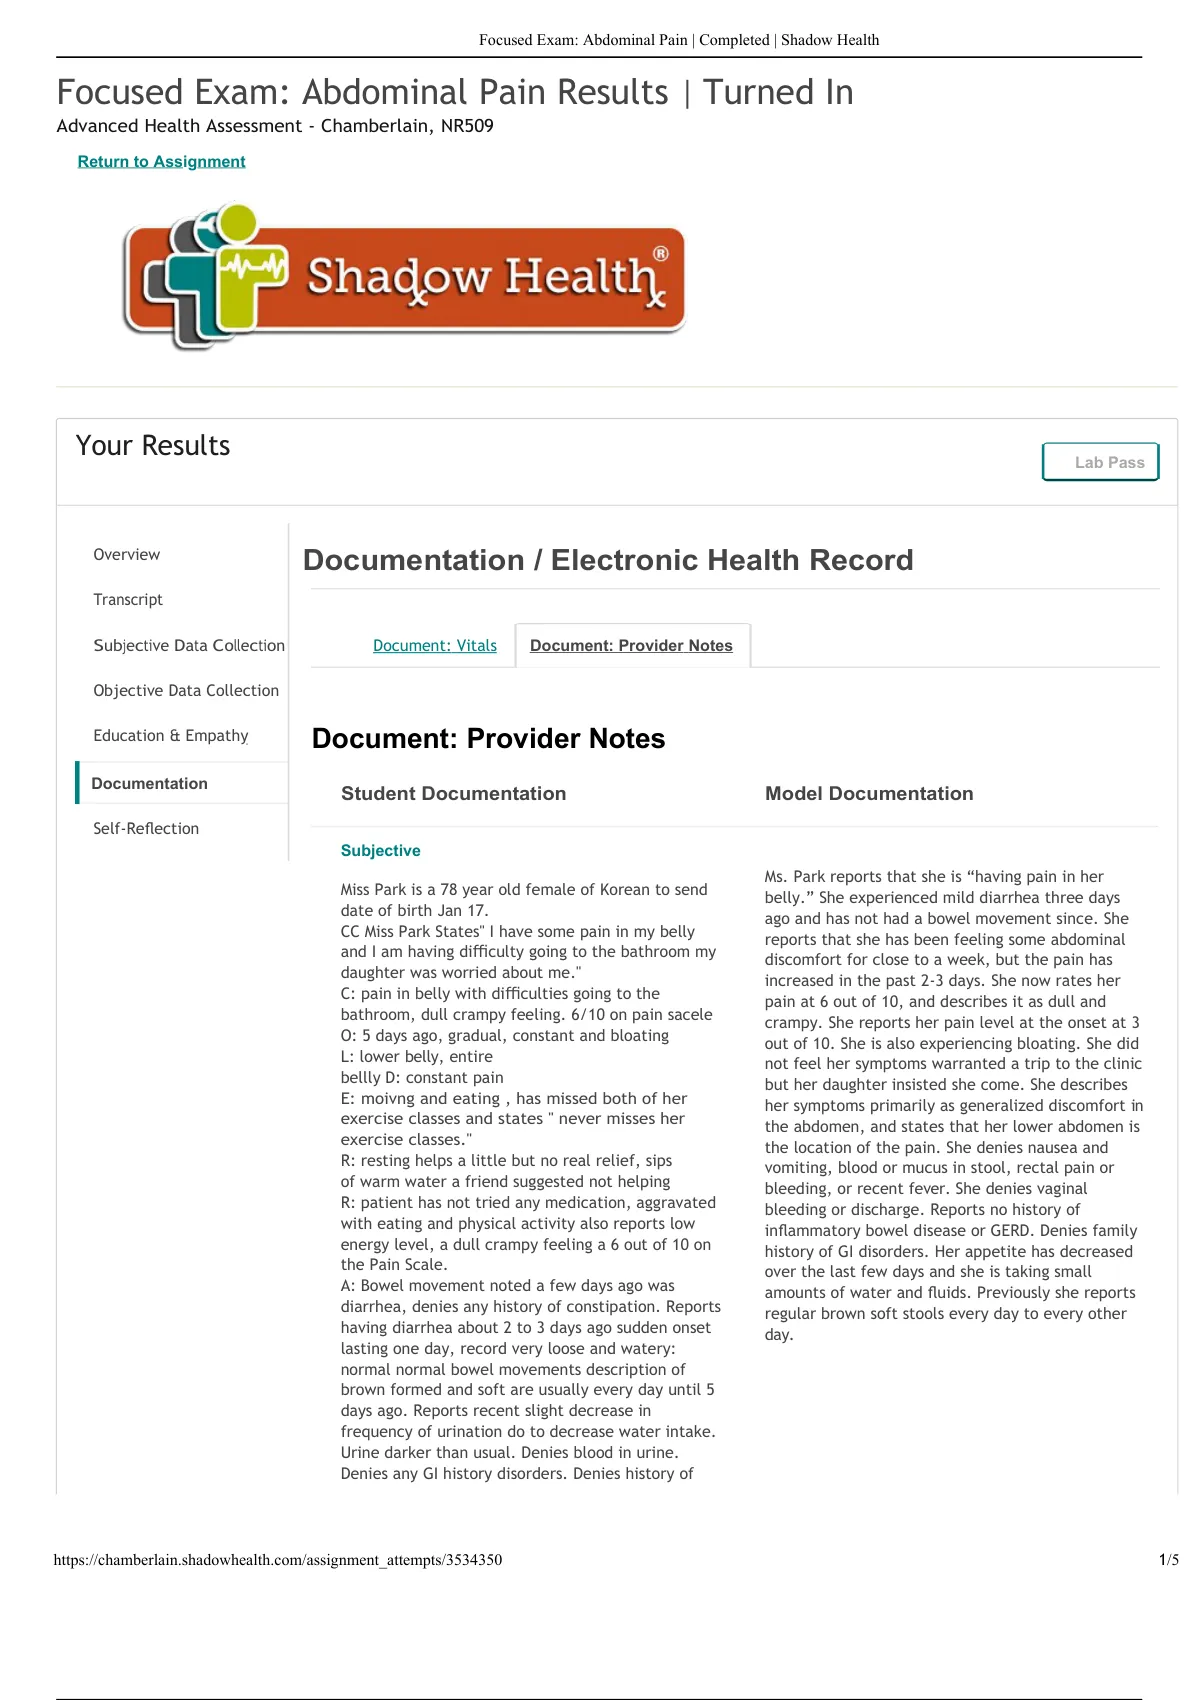
Focused Exam- Abdominal Pain | documentation - Focused Exam- Abdominal Pain | documentation ...
Shadow Health Abdominal Pain Esther Park (Focused Exam: Abdominal Pain) - Shadow Health ...
Esther Park Subjective - Focused Exam: Abdominal Pain Completed I Shadow Health Focused Exam ...
Shadow Health-Focused Exam; Abdominal Pain - Shadow Health-Focused :Abdominal Pain - Stuvia US