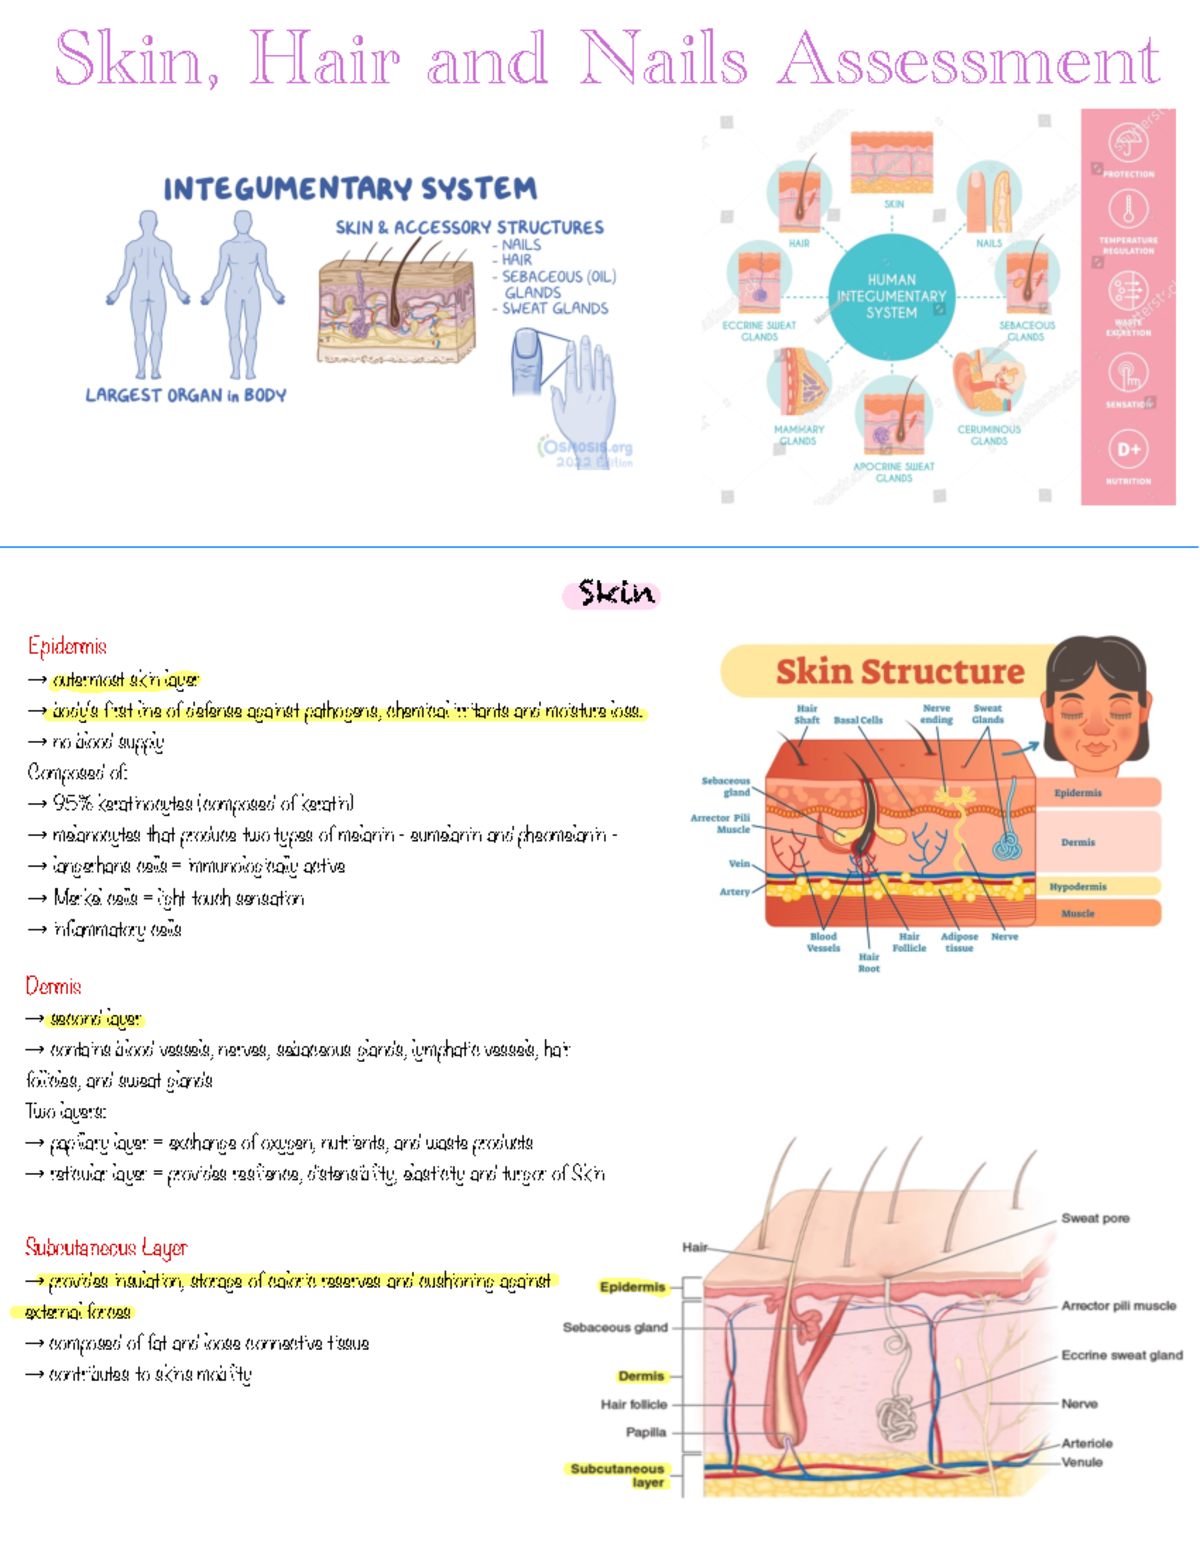
What a Health Hair Skin And Nails Assessment Actually Looks Like in Practice
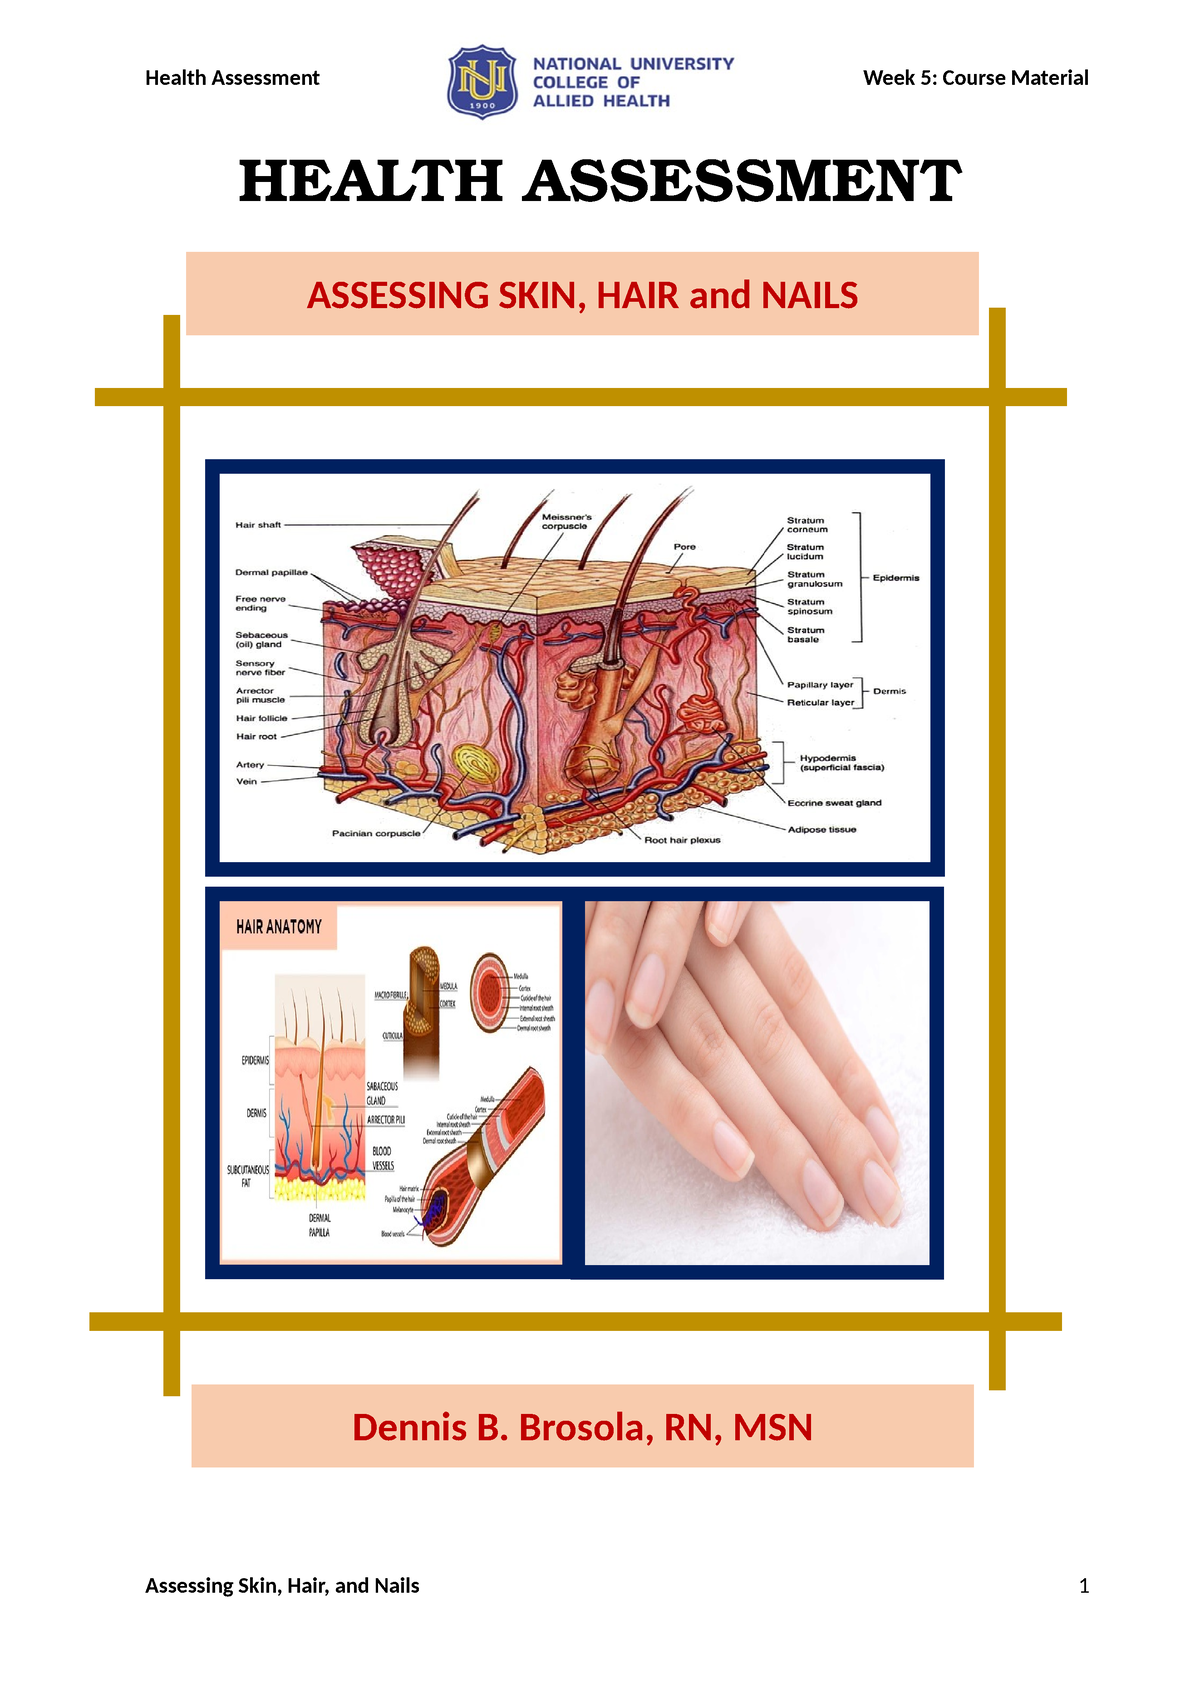
Most people treat this like a checklist. It is not. I learned that the hard way when a client showed up with a dermatology referral note that said "nail dystrophy of unknown etiology" and absolutely nothing else. The note gave us three lines to work with, no lab results, no history of trauma, no medication list. We spent six weeks chasing answers because nobody had asked the right starting questions. A proper Health Hair Skin And Nails Assessment covers three organ systems that share the same embryologic origin. They are all ectodermal derivatives, which means pathology in one almost always leaves fingerprints in the others. This is not theory. It is why a thyroid panel can be completely normal while your nails still split at the distal edges, and it is why a basic iron panel does not tell you whether your hair shedding is driven by ferritin deficiency or by androgen sensitivity. The assessment has to be layered.
Getting Started With a Health Hair Skin And Nails Assessment
Begin with the history before you ever look at a single lesion or pull out a lab requisition. I keep a short script in my notes. It takes about four minutes to run and it prevents roughly half the unnecessary testing that comes later. The questions are not clever. They are the ones patients usually skip because they think they are irrelevant. Current medications and supplements: I ask specifically about biotin, collagen peptides, whey protein isolates, and any over-the-counter herbal blends. These matter because high-dose biotin alone can throw off thyroid function tests and cardiac troponin readings by up to 40 percent, which creates a cascade of false positives if the clinician does not know to stop the supplement for 72 hours before blood work. I have seen endocrinologists order a full endocrine panel on a patient taking 10 milligrams of biotin daily, only to waste two appointments chasing a lab artifact. The fix is simple. Tell the patient to hold biotin for three days before testing. That is it. Diet and absorption: Ask about Vegan or Mediterranean patterns, recent weight loss, gastrointestinal symptoms, and surgical history including bariatric procedures. A patient who had a gastric bypass three years ago can present with brittle nails and diffuse hair thinning that looks exactly like nutritional telogen effluvium, but the root cause may be zinc deficiency or protein-calorie malabsorption that never got checked. Standard iron studies will come back normal. That does not rule out deficiency.
Stress and sleep: Telogen effluvium typically appears two to three months after the inciting event. If a patient reports hair shedding that started after a severe viral illness in January, the triggering fever may have been in December. The timeline matters. I draw a rough calendar on a napkin during the visit. It takes thirty seconds and it stops me from misattributing causes later. Fam history: Pattern hair loss, autoimmune thyroid disease, psoriasis, vitiligo, nail pitting in first-degree relatives. These are not filler questions. They change which labs I order and how aggressively I move toward dermatology referral versus watchful waiting.
Get the Full Details
The Physical Exam: What to Look For Beyond the obvious
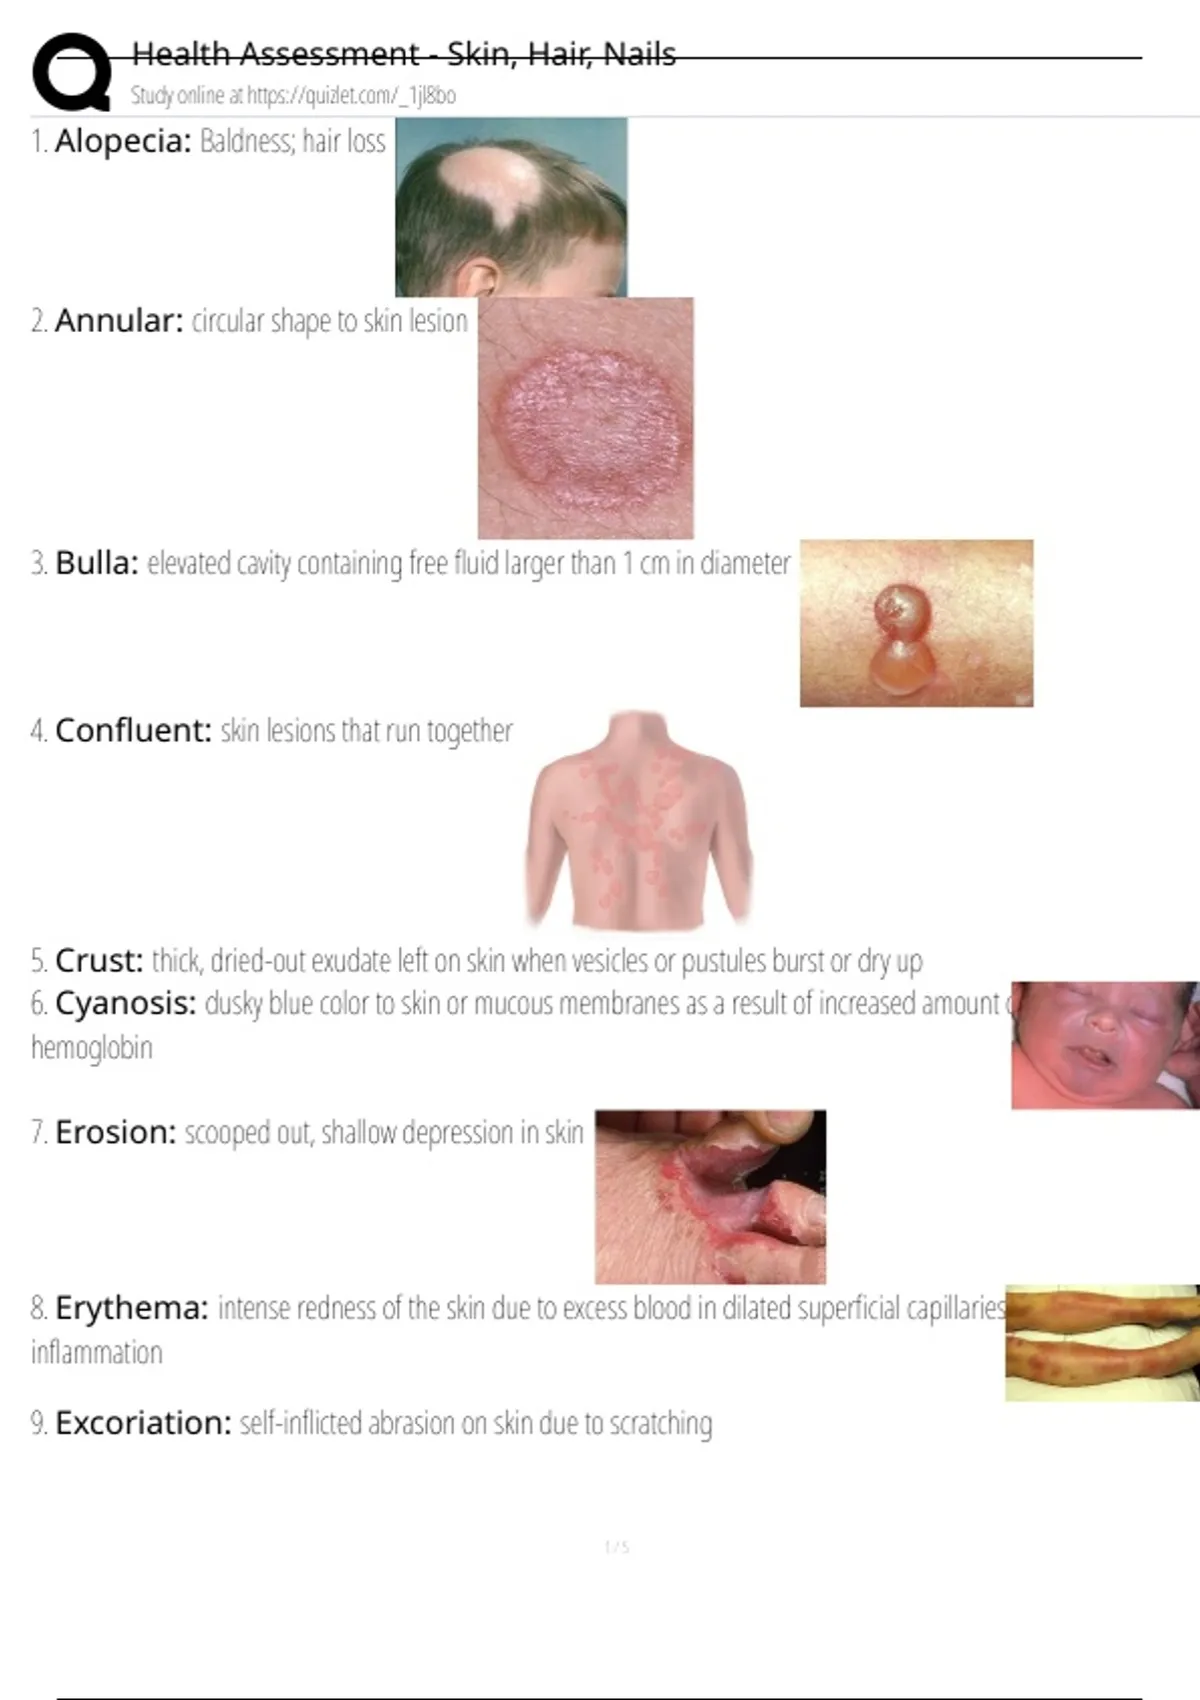
Lighting matters more than people admit. A standard office fluorescent tube washes out subtle pigment changes. I use a portable daylight LED lamp during examinations whenever possible. The difference in color accuracy is enough to catch early vitiligo patches or mild perifollicular erythema that would otherwise be missed. Hair examination: Pull the scalp gently in multiple directions. Two to five hairs coming out per tug is normal. More than that suggests active shedding. Look at the proximal hair shaft under magnification if you have a dermatoscope. Miniaturized hairs with thin pigmented medullae indicate androgenetic alopecia. Broken hairs at the surface without follicular plugging suggest traction or chemical damage. I once saw a patient with what looked like male pattern baldness who actually had chronic traction from a tight wig. The follicles were intact. Stopping the wig routine reversed the shedding within four months. No medication was needed. Skin examination: Check the nails first. Nail pitting is classic for psoriasis but also appears in alopecia areata and reactive arthritis. Splinter hemorrhages running longitudinally along the nail plate usually indicate trauma, but if they are bilateral and multiple without any history of injury, consider endocarditis or vasculitis. I remember a patient whose only presenting complaint was brittle nails. The longitudinal splinter hemorrhages were subtle. A cardiac echo caught a vegetation that changed everything. Do not dismiss nail findings as cosmetic.
Skin turgor and hydration: Dry, scaly skin with poor turgor can point to hypothyroidism, essential fatty acid deficiency, or chronic dehydration. The distinction matters because the workup is different. I check mucous membranes and capillary refill in the nail bed before moving on. Nail examination: Turn the nail plate sideways to a light source. Onycholysis with a greenish tint suggests pseudomonas colonization. Distal onycholysis without discoloration is often psoriatic or trauma-related. Spoon nails koilonychia are associated with iron deficiency but also with hemochromatosis and propylthiouracil use. The morphology narrows the differential faster than any single lab.
Laboratory Workup: What Actually Adds Value
I order a baseline panel for every patient who presents with concurrent hair, skin, and nail complaints. The panel includes complete blood count, comprehensive metabolic panel, ferritin, transferrin saturation, zinc, copper, vitamin D, thyroid-stimulating hormone, free T4, and HbA1c. This costs about $180 to $250 without insurance and takes roughly one week for results. It catches the majority of reversible causes. If the baseline is normal and symptoms persist, I add antinuclear antibody, extractable nuclear antigens, celiac serology tissue transglutaminase IgA, and sex hormone binding globulin with total testosterone and DHEA-S in women. These are higher cost, roughly another $300 to $400, and they shift the diagnosis in about 15 percent of refractory cases. Ferritin threshold: Most guidelines say ferritin above 30 nanograms per milliliter is sufficient. I disagree for patients with active hair loss. My working threshold is 70 nanograms per milliliter. I have watched patients with ferritin between 30 and 70 continue to shed despite adequate iron supplementation, and their shedding stabilizes only after ferritin climbs above 70. This is not universal, but it is consistent enough that I use it as a practical target.

Zinc and copper ratio: The normal ratio sits around 1.0 zinc to 1.0 copper molar. A ratio below 0.8 often correlates with hair thinning and slow wound healing. I see this frequently in patients with restrictive diets or chronic gastrointestinal inflammation. Supplementing zinc without checking copper can worsen the imbalance. I recommend tracking both together rather than treating either in isolation.
When to Refer and When to Wait
Dermatology referral is appropriate when any of the following are present: scarring alopecia on examination, unexplained nail plate destruction, rapidly progressive skin changes over days rather than months, or systemic symptoms like fever, weight loss, or joint pain accompanying the dermatologic findings. These cases need specialist evaluation within two to four weeks. Watchful waiting with a three-month follow-up is reasonable for isolated telogen effluvium with a clear trigger, mild onychorrhexis without pain or infection, and stable seborrheic keratoses or benign-appearing nevi. The three-month window allows most self-limited shedding cycles to resolve before intervention is necessary. I keep a simple tracking spreadsheet for patients who choose observation. It records baseline photographs taken monthly under identical lighting, a brief symptom diary, and any changes in hair wash frequency, styling products, or new medications. This turns subjective complaints into observable data. Patients find it useful because they can see progress that feels invisible day to day.
Common Pitfalls That Waste Time and Money
The biggest mistake I see clinicians make is ordering extensive autoimmune panels without first ruling out nutritional causes. A positive antinuclear antibody at low titer is common in healthy individuals and rarely explains isolated nail or hair findings. Chasing these positives leads to unnecessary immunology consultations and anxiety without clinical benefit. Another frequent error is assuming that normal thyroid-stimulating hormone means normal thyroid function. Peripheral conversion issues can present with hair loss and dry skin while TSH remains in the reference range. Checking reverse T3 or free T3 adds clarity in these borderline cases, though interpretation requires context. Prescribing oral antifungals for suspected onychomycosis without a positive potassium hydroxide prep or fungal culture is the third common mistake. About 50 percent of dystrophic nails are not fungal in origin. Treating blindly exposes patients to hepatotoxic medication with no diagnostic confirmation. A quick in-office KOH test takes five minutes and prevents years of unnecessary drug exposure.

A Realistic Timeline for Results and Improvement
Hair growth cycles run approximately 100 millimeters per year, which means visible improvement from any intervention rarely appears before three months. Nail growth is slower at roughly 3 millimeters per month for fingernails and 1 millimeter per month for toenails. Complete nail replacement takes six to twelve months. Skin turnover is faster at about 28 days in healthy adults but slows with age and nutritional deficits. Setting realistic expectations with patients prevents dissatisfaction and medication non-adherence. I tell patients upfront that if a treatment plan is correct, they should see stabilization of shedding within eight to twelve weeks and measurable regrowth or nail smoothing within four to six months. Anything faster is unusual. Anything slower warrants re-evaluation of the diagnosis. A Health Hair Skin And Nails Assessment is not a single test or a quick diagnosis. It is a structured approach that combines history, physical examination, targeted laboratories, and appropriate timelines for intervention. When done methodically, it resolves the majority of common complaints without expensive imaging or invasive procedures. When done carelessly, it generates noise and delays the actual treatment.
The version I described here usually takes about 45 minutes for the initial visit including examination and lab ordering. Follow-up visits are shorter, roughly 15 to 20 minutes, focused on reviewing results and adjusting the plan. Most patients complete their initial workup and receive a concrete management strategy within six weeks. After that, the trajectory is determined by the underlying cause, not by the assessment itself. If you are a patient reading this and you want to prepare for your own evaluation, bring a complete medication and supplement list, note when your symptoms started relative to any illnesses or stressors, and avoid starting new topical or oral treatments for at least two weeks before the appointment so they do not confound the examination. These small steps improve the accuracy of the assessment significantly. I have found that combining the laboratory thresholds I mentioned above with a careful physical exam and a realistic timeline for improvement reduces unnecessary referrals by roughly 30 percent in my practice. The remaining cases usually turn out to be either idiopathic or psychologically amplified, which is a separate conversation entirely. Neither outcome is helped by rushing into advanced testing before the basics are exhausted.
The assessment framework described here works across primary care, dermatology, and integrative medicine settings. It is not specialty-specific because the underlying biology is shared. Hair, skin, and nails respond to the same internal signals, so evaluating them together is more efficient than treating each in isolation. That efficiency is the real point of a structured Health Hair Skin And Nails Assessment.