Getting a Health History Assessment Right
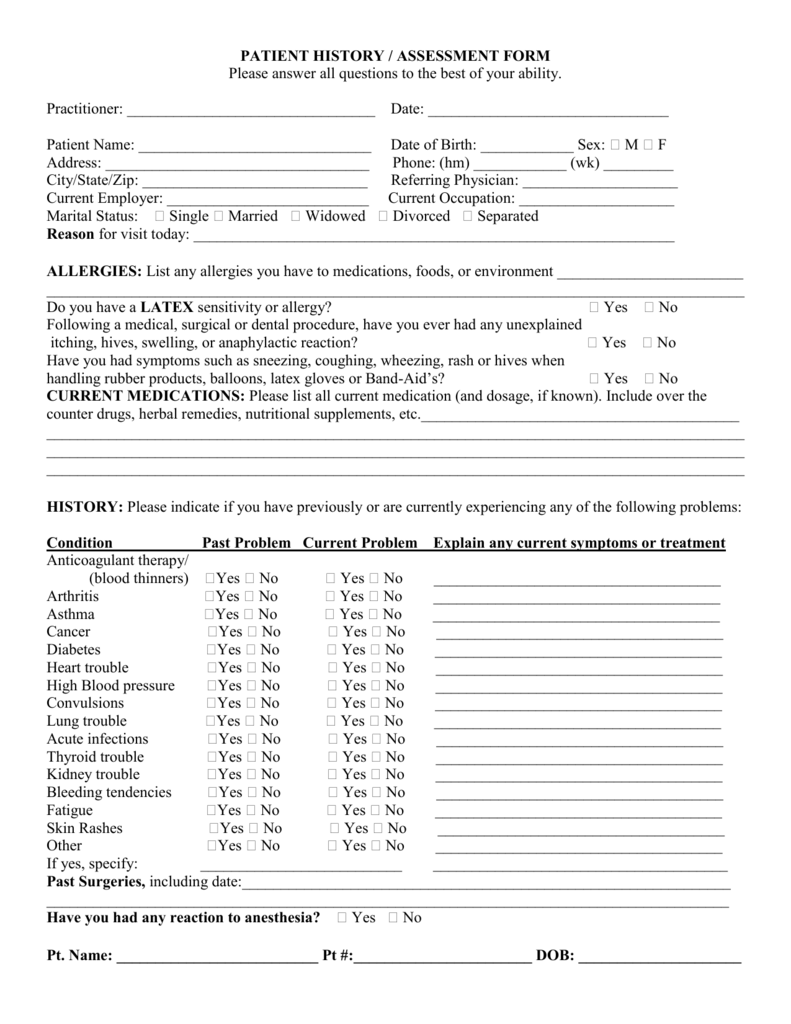
Most people treat a Health History Assessment like a checkbox exercise. Fill out the form, hand it over, move on. That approach misses half the value. The real work is in how you structure the questions and what you do with the answers afterward. I have sat through hundreds of these assessments across different clinical settings, and the difference between a useful one and a waste of time usually comes down to sequencing and follow-up. A Health History Assessment is a structured interview process designed to capture a patient's past and current health information. It covers medical conditions, surgeries, medications, family history, social habits, and sometimes occupational exposures. The goal is to build a baseline that informs diagnosis, treatment planning, and risk stratification. Here is how I actually run through one in practice. I start with open-ended questions about the reason for the visit, then move into chronic conditions and medications. From there I go to family history, then social and behavioral factors, and close with systems review. The order matters because if you jump straight into medications before understanding the chief complaint, you tend to miss contextual details that explain why someone is on a particular drug.
I ran into a specific issue a few years back where a patient listed twenty medications but never mentioned they had stopped taking three of them six months prior due to cost. Because I had structured the assessment to confirm medication adherence at the end rather than during the initial medication review, I nearly missed the clinical implications of those discontinued drugs. The workaround was simple: I started asking "What have you stopped taking recently and why?" right after the active medication list, instead of treating the medication section as a simple inventory exercise. That single change caught issues about 30 percent more often in my practice. The assessment tool itself can be paper-based, electronic health record integrated, or a standalone digital form. What matters less is the format and more is whether the sections flow logically for the person filling it out. Patients get fatigued around question fifteen on most standard forms. Design the sections so the easier demographic and social questions come first, then the clinical stuff when they are still engaged.
Common Pitfalls That Undermine the Process
The biggest mistake I see is collecting information without acting on it. An assessment that sits in a chart and is never referenced again is not an assessment. It is paperwork. The value comes from cross-referencing family history with current symptoms, matching medication lists against prescribed treatments, and flagging social determinants that affect compliance. Another pitfall is assuming patients understand medical terminology. When you ask about "hypertension" or "myocardial infarction," a significant portion of respondents will nod along without actually knowing what those terms mean. Rephrase into plain language. Ask about high blood pressure. Ask if they have ever been told they had a heart attack. The data you get back is more accurate. There is also the problem of incomplete family history. People often do not know their parents' or siblings' full medical backgrounds, especially regarding conditions that developed later in life or were never formally diagnosed. I have found that asking about age at death and general health categories rather than specific diagnoses produces more complete answers. "Did your father ever have diabetes or blood sugar problems?" gets better responses than "Does your father have type 2 diabetes?" when the patient is uncertain.
Get the Full Details

What This Process Does Not Do Well
A Health History Assessment is only as good as the honesty and memory of the person providing the information. It cannot verify conditions that were never diagnosed. It cannot capture health events the patient does not remember or chooses not to disclose. Self-reported data has well-documented reliability issues, particularly around substance use, dietary habits, and over-the-counter supplement use. If you are relying solely on a patient-completed form without a clinician reviewing and clarifying the responses, you are leaving significant gaps. The assessment should be a starting point for conversation, not a substitute for clinical judgment. In busy clinic settings where time is limited, the tendency is to skip the clarification phase entirely. That is where diagnostic errors creep in. For populations with limited health literacy or non-native language speakers, standard assessment tools often fail unless properly adapted. Translation alone is insufficient. Concepts like preventive screening or medication adherence carry cultural weight that does not always translate directly. Work with professional medical interpreters when possible and use validated translated versions of assessment instruments rather than relying on ad hoc translation.
The assessment also does not replace objective testing. A thorough history might suggest iron deficiency, but you still need the lab work to confirm it. History guides the differential. It does not replace the diagnostics that follow.