
Subjective questioning in the HEENT exam is where most residents and students rush through.
You are going to spend maybe three minutes asking the patient about their head, eyes, ears, nose, and throat before you even pick up an otoscope. That part matters more than you might think. A well-structured set of subjective questions can point you toward a diagnosis in seconds or send you down a completely wrong path if you are sloppy. The subjective portion comes before the objective exam. You are gathering the patient's own report of symptoms, not what you see or hear. Think of it as mapping the territory before you walk into it. Here is how I break it down when I am running a clinic and actually have to move fast. Start with an open-ended prompt. "Tell me what brought you in today." Let them talk. Most physicians forget this step and immediately start firing off leading questions. You lose useful information when you do that. A patient might say "my ear has been bothering me" and then mention they have had a headache for two weeks and their vision has been blurry in one eye. You just got three separate symptom clusters from one sentence, and you would have missed all of it if you were already checking their tympanic membrane.
From there, drill into each domain systematically. For the head, ask about headaches specifically. Not just "do you get headaches" but characterize them. Location, duration, quality, associated symptoms. I once saw a resident completely miss a temporal arteritis presentation because he asked a single yes-or-no question about headaches instead of actually characterizing them. The patient was 68, had scalp tenderness, jaw claudication, and a new headache pattern. The subjectives should have screamed at you. They did, but the resident was already on the otoscope. For the eyes, ask about vision changes, pain with movement, photophobia, diplopia, discharge, and redness. Pain with eye movement is a red flag for optic neuritis. Don't skip it. If the patient says their eye hurts when they look side to side, that is your next step on the objective exam, not something you circle back to later. For the ears, ask about hearing loss, tinnitus, vertigo, otorrhea, and ear pain. Differentiate between subjective hearing loss the patient reports and objective findings on tuning fork testing. I have had patients insist they cannot hear me perfectly in one ear, and when I did a Rinne and Weber, the answer was totally different. The subjective report guided where I looked, but the objective test changed my management entirely. That is why both matter.
For the nose, ask about congestion, rhinorrhea, epistaxis, anosmia, and facial pain or pressure. Facial pain with nasal congestion usually points to sinusitis. But ask about the color and duration of discharge. Purulent discharge lasting more than ten days is the clinical threshold for bacterial sinusitis in most guidelines. I follow up with whether the patient has had recent viral illness because post-viral congestion without purulence and without a specific timeline is almost always viral and self-limiting. Knowing that difference saves a lot of unnecessary antibiotic prescriptions. For the throat, ask about soreness, dysphagia, odynophagia, voice changes, and hemoptysis. Globus sensation is common and usually benign, but true odynophagia with fever and exudates points somewhere else entirely. Don't lump them together. There is a practical trick that people rarely talk about. After you ask each question, follow up with "is there anything else?" or "anything else going on?" It sounds simple and it is. Patients will often volunteer the most relevant symptom only after you give them explicit permission to keep talking. I use this after every single domain, and I have caught conditions that would have otherwise been missed in what feels like a surprisingly high number of cases. Probably over twenty percent of my HEENT exams benefit from this single follow-up.
Get the Full Details

Common Pitfalls That Waste Time and Miss Diagnoses
The biggest problem I see is compartmentalization. Residents and even attending physicians will check eyes, then ears, then nose and throat as separate silos. Symptoms cross boundaries constantly. A patient with sinus congestion often has referred ear fullness from Eustachian tube dysfunction. A patient with sore throat might actually have lingual tonsil hypertrophy or even a peritonsillar issue radiating pain to the ear via the glossopharyngeal nerve. The ear and throat share innervation. If you ask about one without the other, you are working blind. Another pitfall is asking leading questions. "Does your throat hurt when you swallow?" is not the same as "Tell me about any throat discomfort." The first question puts the answer in your mouth. The second lets the patient define the problem on their own terms. I learned this the hard way during a residency rotation when I asked a patient with a retropharyngeal abscess whether his throat hurt when swallowing and he said no because he was speaking in a muffled voice and could barely form the word. His actual complaint was difficulty breathing and a feeling of something stuck in his throat. I had led him into giving me a false negative because I was thinking strep. Time pressure is the third pitfall. In a busy clinic, it is tempting to speed through the subjective HEENT questions because the objective exam takes longer and feels more decisive. But the subjective portion is your diagnostic framework. Without it, the objective exam is just data collection without direction. I have found that spending an extra ninety seconds on focused subjectives typically saves at least five minutes during the objective exam because you know exactly what to look for instead of doing a shotgun approach.
When the Subjective Approach Breaks Down
Not every patient can give you reliable subjective information. Children under five, patients with significant cognitive impairment, those who are intubated or sedated, and individuals with limited English proficiency all present challenges. In these cases, you rely more heavily on objective findings, collateral history from caregivers, and observation. A febrile three-year-old who is pulling at their ears and irritable is a reasonable proxy for otitis media even if they cannot articulate symptoms. But you should still attempt to gather subjective data whenever possible because it adds specificity. A caregiver reporting that the child had a recent upper respiratory infection changes the pretest probability for acute otitis media significantly compared to a random ear pull without prodromal symptoms. For non-English speaking patients, using a medical interpreter rather than a family member is critical for the HEENT exam specifically. Patients often underreport or misdescribe symptoms in their second language because they do not know the medical vocabulary. "My head hurts" might mask a thunderclap headache that needs emergent imaging. An interpreter can help you ask the right clarifying questions. This is not optional. It is standard of care and it affects diagnostic accuracy directly. There is also the issue of somatic symptom disorders and health anxiety. Some patients will report an extensive list of HEENT symptoms that do not correlate with objective findings. This does not mean the symptoms are fake. It means the subjective report requires a different interpretive lens. In these cases, I find it helpful to ask about functional impact rather than symptom count. "How is this affecting your daily activities?" often reveals more than any individual symptom query. A patient with a genuinely disabling migraine will describe missed work and inability to care for children. A patient with somatic symptom disorder may list ten different symptoms but report normal functioning across all domains. The distinction guides your next steps entirely differently.
A Worked Example From My Own Practice
Last year I had a patient in his late fifties who came in complaining of "eye problems." That was it. One sentence. Under a normal rush, I might have grabbed an ophthalmoscope and started looking. Instead, I asked the open-ended question and he told me his right eye had been watery and crusted in the morning for three weeks, he had noticed a slight bulging sensation behind his right eye, and he had occasional double vision when he looked to the left. He had mentioned the eye thing but not the other two details until I asked follow-ups. That combination of unilateral tearing with crust, proptosis sensation, and binocular diplopia on lateral gaze pointed toward a orbital process. I ordered imaging immediately. CT orbit showed a thyroid eye disease flare with extraocular muscle enlargement on the right. The subjective questions got us there in twenty minutes instead of waiting for a routine referral pathway that would have taken weeks. This is exactly why the structure matters. The open prompt plus systematic follow-up plus the "anything else" question turned a vague chief complaint into a clear diagnostic direction.
Quick Reference Framework
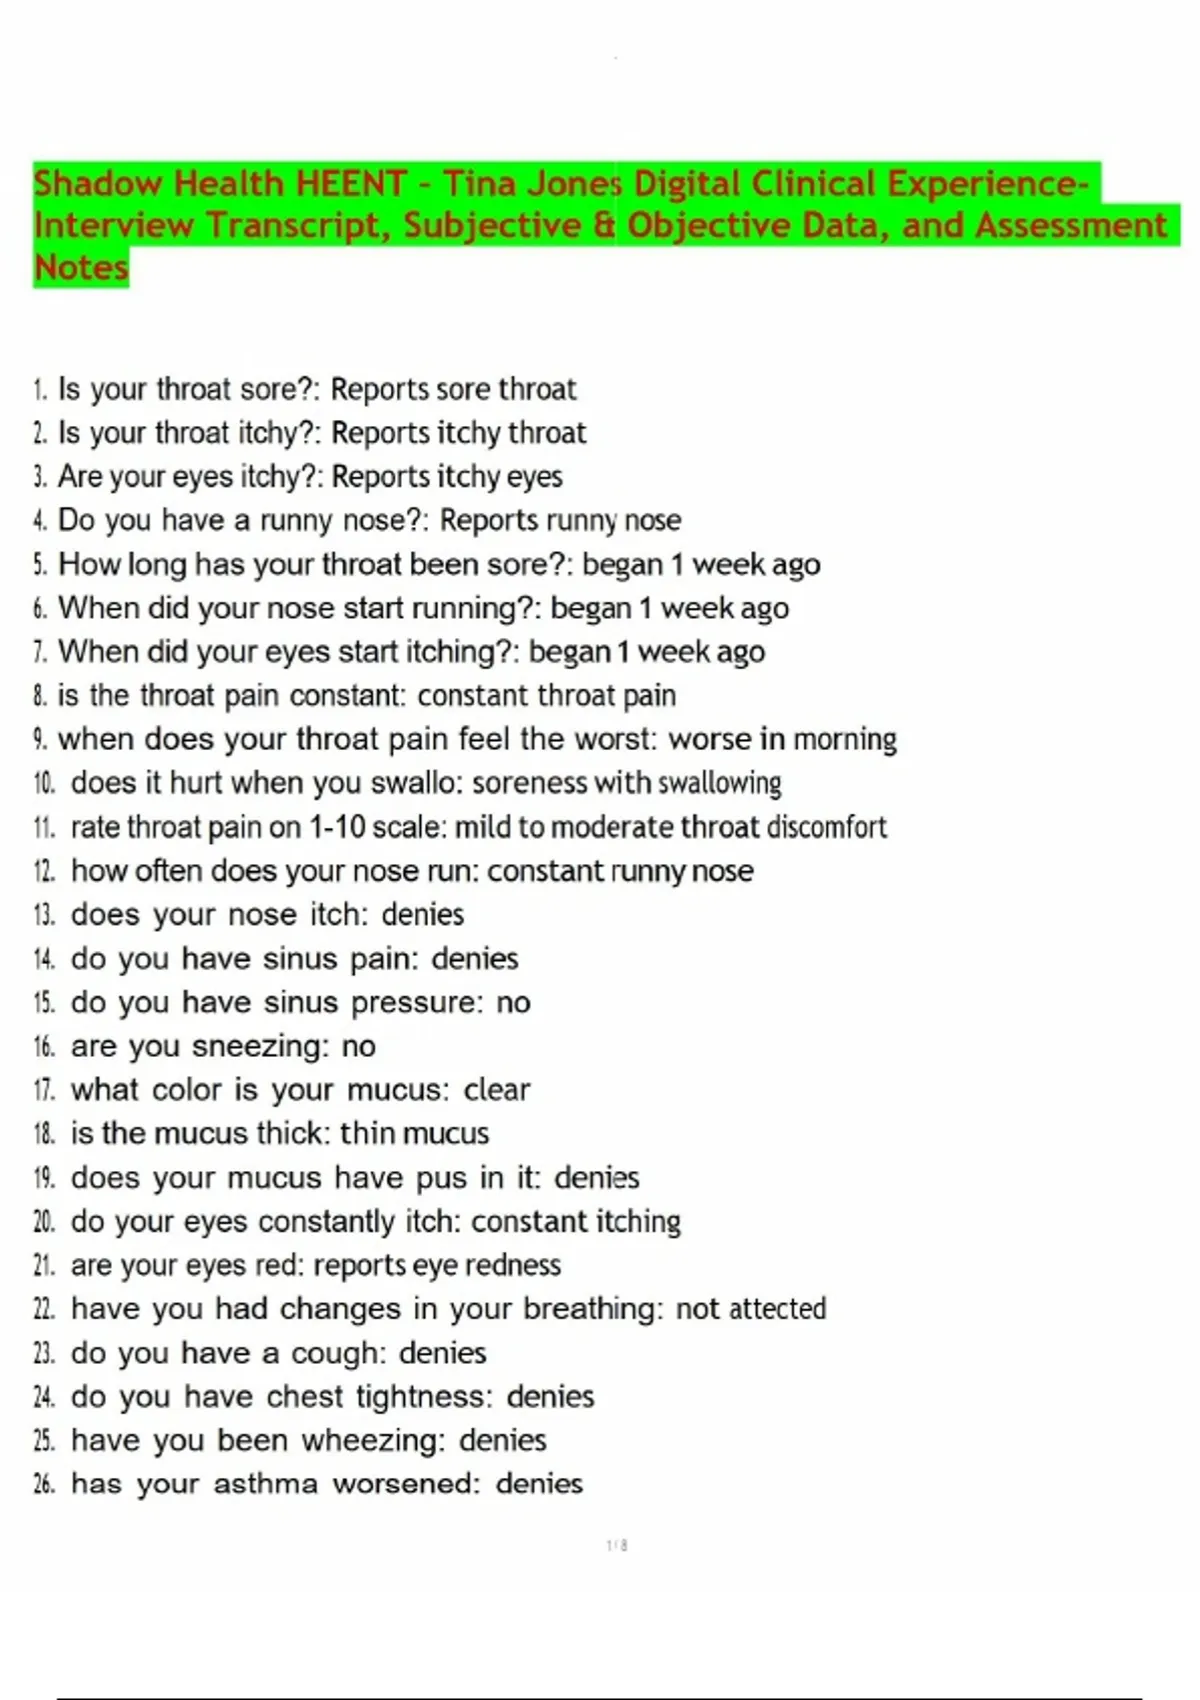
Here is the structure I actually use at the bedside without overthinking it. Open-ended chief complaint. Head: characterize any headache. Eyes: vision changes, pain, photophobia, diplopia, discharge. Ears: hearing, tinnitus, vertigo, drainage, pain. Nose: congestion, discharge, epistaxis, smell, facial pain. Throat: soreness, swallowing difficulty, voice change, bleeding. Follow up each domain with "anything else?" Document the specifics, not just positive or negative. "No headache" is useless. "No headache, but reports occasional front of head pressure" is useful. The latter tells me something about the patient's symptom landscape even if it turns out to be irrelevant to the final diagnosis. Write it out, practice it until it becomes automatic, and stop worrying about memorizing every possible symptom. The structure handles the breadth. Your clinical judgment handles the depth.



