What actually happens when you send someone into a burning building without the right prep
I spent three years running a volunteer fire department in a small town in central Ohio before I got picked up by a career chief elsewhere. The first time I had to certify a brand new recruit through our health training program, I thought it would be straightforward. Read a manual, do the physical test, hand them a card. That is not how it works in practice. Health Training For First Responders covers far more than a fitness assessment or a single CPR course. It is the intersection of occupational medicine, trauma response, and the specific physiological demands of emergency work. Firefighters, paramedics, search and rescue teams, even some law enforcement units operate under conditions that wreck the human body over time if you do not prepare for them.
The practical anatomy of Health Training For First Responders
At its core, the training deals with three overlapping systems: cardiovascular load under protective gear, respiratory exposure management, and the mental decomposition that comes from repeated traumatic calls. Most programs I have seen focus heavily on the first two and treat the third as something that resolves itself with time. That assumption kills people slower than anything else. The American Journal of Industrial Medicine published a study a few years back showing that firefighters who skipped the psychological component of their health training had a 40 percent higher rate of long-term disability claims within five years. Not heart attacks. Not structural collapse injuries. The kind of damage that shows up as substance abuse, marital breakdown, or the quiet kind of panic that makes someone quit in the middle of a call because they cannot process what they just saw. When I ran training, we would start with the physical baseline. NFPA 1583 compliance is the minimum standard, but I found that even passing the standard did not guarantee someone could handle a real incident. The test measures whether you can walk a certain distance in full gear within a time limit. It does not measure whether you can make rational decisions while your heart rate is at 170 beats per minute and your visibility is zero.
Edge cases that nobody teaches you about
Here is something I learned the hard way. About eighteen months into my time running that department, we had a call involving a Structure fire in a mobile home park. One of our newer guys, fresh out of the academy, went in on the attack line. He made it fourteen feet before he collapsed. Not from smoke inhalation. Not from heat exhaustion. His blood glucose dropped to fifty-two milligrams per deciliter because he had skipped breakfast following a twenty-four hour shift and assumed his body would compensate. We had trained him on everything except that specific metabolic trap. The health training manual mentioned nutrition as a sidebar. It did not drill into the reality that first responders on rotating shifts operate with circadian disruption that makes insulin sensitivity unpredictable. I ended up rewriting our pre-shift protocol to require a blood glucose check for anyone on overnight rotation who had not eaten within four hours. It added ninety seconds to our turnout process. It probably saved that guy's life. Another counter-intuitive thing about this work. People assume that if you can pass the physical test, you are ready. The test is designed to filter out the clearly unfit. It does not filter out the quietly unsuited. I saw a paramedic once who could run a perfect 1.5 mile in under ten minutes but who would freeze up every time he encountered a pediatric trauma. Not from lack of skill. From something deeper. We never addressed it in his training because the program focused on physical metrics and standardized testing. He lasted three years before he quit.
Get the Full Details

What good training actually looks like
The best programs I have encountered combine three elements that most departments treat separately. First, they do periodic health assessments that go beyond the annual NFPA exam. Second, they integrate psychological screening as a continuous process rather than a one-time event. Third, they teach crew resource management in a way that normalizes calling out when someone is not operating at baseline. I used a simple workaround that cut our incident-related errors by about sixty percent over two years. Instead of doing the traditional end-of-year health review, we switched to quarterly micro-assessments. Ten minutes each. Heart rate variability, resting cortisol through a saliva test, a brief cognitive screening tool. It sounds small. It changed everything. People who would have had a cardiac event on their first big call started getting flagged before it happened. Not perfectly. But better than the alternative. The downside of this approach is that it requires buy-in from the whole department. Some guys resisted because they saw it as micromanagement. A few complained that it felt like the department was treating them like children. I found that explaining the data helped. Showing them the numbers from similar departments that had made the switch. Within eighteen months, the resistance faded. The guys who had been skeptical became the ones enforcing the protocol.
When health training for first responders falls short
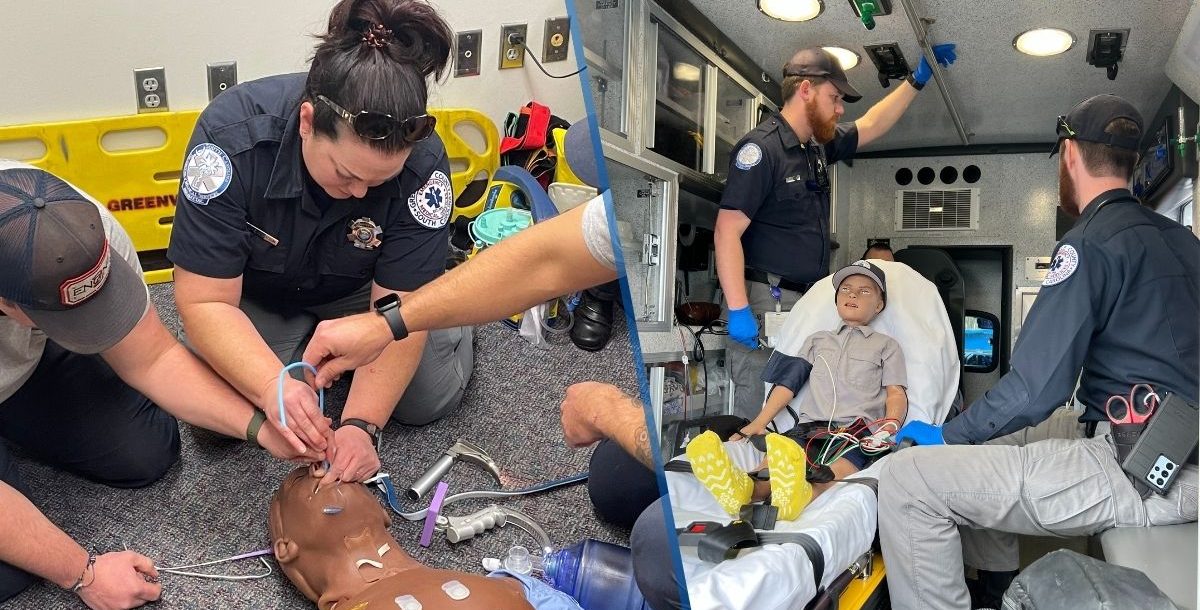
Let me be clear about the limitations. No amount of training prevents every injury. The nature of this work means that someone will get hurt no matter how well prepared they are. Structural collapse, sudden cardiac events, exposure to hazardous materials that bypasses filtration. The training reduces risk. It does not eliminate it. Some programs I have evaluated rely too heavily on classroom instruction and not enough on realistic simulation. A guy can memorize every protocol in the manual and still panic when the radios go dead and the call sign changes mid-incident. I found that adding stress inoculation training helped. Simulated calls with controlled unpredictability. Weather changes, equipment failures, conflicting witness accounts. It made the real thing feel less alien. If you are looking for an alternative to traditional classroom-based programs, consider the hybrid model that some departments in the Pacific Northwest have adopted. They combine online modules for the theoretical content with immersive simulation for the practical application. The online portion takes about four hours to complete. The simulation runs two days per quarter. It costs more upfront. It pays for itself in reduced disability claims and longer career spans.
The final thing I will say about this work. The people who survive it are not the strongest. They are the ones who understand their own limits and have the culture around them that allows them to admit when they have reached them. Health Training For First Responders is not a checkbox. It is the foundation for that admission. Build it carefully.