Mapping Where Care Actually Moves (and Where Money Gets Stuck)
Value chain analysis in healthcare sounds like an academic exercise until you try to apply it to a real health system. The framework itself is straightforward — trace every activity from referral to post-treatment follow-up and ask which ones create patient value and which ones just consume resources. The problem is that healthcare doesn't organize itself neatly along those lines. I worked on a value chain mapping project for a regional hospital network a few years back. We needed to identify where the most cost leakage was happening across the oncology pathway. The textbook approach would be to map the linear flow: diagnosis, staging, treatment planning, administration, monitoring, survivorship. We drew that up in about two days. The reality showed up three weeks later when we realized that staging decisions were being made in three different departments with no standardized protocol, and each department was using different coding systems that didn't reconcile with billing.
Healthcare Value Chain Analysis
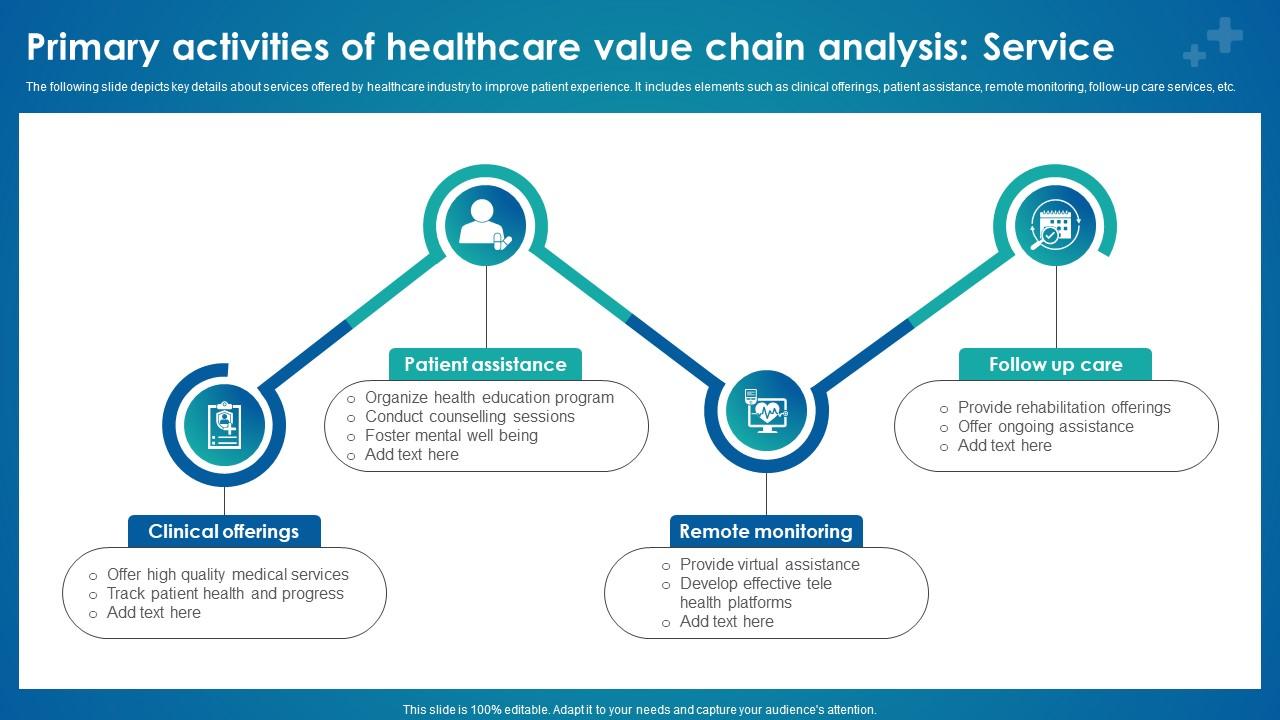
The foundation comes from Porter's value chain model, adapted for healthcare. You split activities into primary and support categories, but the categories look different than in manufacturing. Primary activities in healthcare are typically: patient identification and access, diagnosis and treatment delivery, support services (imaging, pharmacy, lab), patient discharge and transitions, and post-acute follow-up. Support activities cover procurement of pharmaceuticals and equipment, health information systems, clinical staff development, and quality/safety infrastructure. What most people miss on the first pass is that value chains in healthcare are not linear. They branch, loop, and intersect constantly. A patient with diabetes might cycle through primary care, endocrinology, ophthalmology, podiatry, and nutrition services over a year. The value chain for that patient isn't a single line — it's a web. Your analysis needs to account for branching paths and return loops, or you'll systematically undercount the cost of coordination. Here is how the actual work goes. Step one is scoping. You pick a specific patient population or clinical pathway. Not the entire hospital. Not "all patients." Pick one. A coronary artery bypass graft (CABG) pathway or a maternal care pathway works well because they have clear entry and exit points. If you try to map the entire value chain of a multi-site health system in one go, you will produce something useless within six weeks and burn out everyone involved.
Step two is activity mapping. You sit with clinicians and unit managers and walk through the pathway hour by hour. You document every decision point, every handoff, every test ordered, every communication that happens between departments. This is where the work gets tedious. You will learn that the surgical consent process alone involves four different forms, two different sign-off authorities, and approximately seventeen minutes of patient waiting time between when consent is obtained and when the patient is moved to the pre-op holding area. That seventeen minutes doesn't show up in any aggregate cost report. Step three is cost attribution. You take the activity map and overlay it with cost data. This is the step where most analyses break down. Hospital cost accounting systems are built around revenue centers and departments, not clinical pathways. A single CT scan might pull resources from radiology, cardiology, emergency medicine, and IT support depending on what the scan is looking for. Your costing method has to decide how to allocate those shared costs, and the decision you make will change your results significantly. Activity-based costing gives more accurate results but requires granular data that most hospitals simply do not have. Standard cost allocation formulas are easier to apply but tend to distort the picture, especially for complex or low-volume procedures. Step four is value assessment. You compare each activity against clinical outcomes and patient experience metrics. An activity that adds cost but no measurable improvement in outcomes or experience is a candidate for elimination or redesign. This step is where the analysis becomes genuinely useful rather than just descriptive. You start identifying which activities are value-adding and which are purely administrative overhead. In the oncology project I mentioned, we found that the staging review process — the meetings where oncologists, surgeons, and radiologists discussed each case — was consuming about 4.2 hours per patient on average. Clinical outcomes for patients who had the review were measurably better. But we also found that 60 percent of the discussion time was spent on cases where the treatment path was already obvious and the review added nothing. The workaround was a tiered review system: standard cases got a 15-minute checkbox review, and only complex or borderline cases got the full multidisciplinary discussion. That cut average review time to about 28 minutes per patient without any measurable decline in outcomes.
Get the Full Details
There is a specific edge case I want to flag here. When you are analyzing value chains across multiple facilities or health systems, you run into the problem of variant care pathways. The same condition might be treated differently at Hospital A versus Hospital B because of local physician preferences, equipment availability, or payer contracts. If you pool the data and average the pathways, you lose the signal. You end up with a pathway that doesn't exist at either facility. The fix is to analyze each site separately first, identify the source of variation, and then decide whether the variation represents legitimate clinical judgment or inefficiency. This takes more time upfront but prevents your final recommendations from being nonsensical at every site. The second common mistake is treating the value chain as a static model. Healthcare pathways change constantly — new drugs get approved, guidelines get updated, payer policies shift. A value chain analysis that was valid six months ago may already be outdated. I've seen organizations treat the deliverable as a report to file rather than a living framework. The analysis should be designed to be revisited and updated, ideally on an annual basis or whenever a significant clinical or regulatory change occurs. Another counter-intuitive point: the highest-cost activities are not always the biggest targets for improvement. In acute care settings, the most expensive activities tend to be surgery, intensive care, and advanced imaging. Those are hard to reduce without affecting outcomes. The lower-hanging fruit is usually in the coordination activities — the communication, scheduling, documentation, and handoffs between departments. These activities rarely show up as line items in a budget report. They are embedded in staff time and waiting periods. But they can account for a substantial portion of total pathway cost, and they are exactly the kind of thing that can be streamlined without clinical risk.
You will also encounter resistance from clinicians who see value chain analysis as cost-cutting dressed up in academic language. This is a fair concern if your organization's leadership hasn't been honest about the intent. The framing matters. When you present this as a way to understand where resources are going and where patient care can be improved, you get different reactions than when it's presented as a cost reduction exercise. The data should speak for itself, but the initial conversation determines whether people cooperate or obstruct. Software tools can help, but don't assume any off-the-shelf product will solve the problem. Most healthcare analytics platforms are built for financial reporting or clinical quality dashboards, not for pathway-level value chain mapping. You will likely need a combination of data extraction from your EHR and cost accounting systems, some kind of process mapping tool, and probably a spreadsheet or two for the costing work. The technical barrier is less about the tools and more about the data quality. If your EHR doesn't capture encounter-level timestamps or your cost system doesn't allocate overhead by service line, you will spend more time cleaning data than doing analysis. One more practical note on scale. A single pathway analysis for a mid-size hospital typically takes three to five weeks of focused work from a small team. Two to three clinicians, one data analyst, and one operations person. If you are doing this for an entire health system across multiple pathways, plan in quarters, not weeks. And start with one pathway, prove the method, then replicate. The learning curve is steep on the first attempt and flattens considerably after that.
The output should be a set of prioritized recommendations, not a comprehensive report. Decision-makers don't read 80-page value chain analyses. They read one-page summaries with the top three or four changes that would move the needle. The full mapping and costing data should be available as supporting material, but the primary deliverable needs to be actionable and concise. I learned this the hard way on my second project, where I produced a beautifully detailed 60-page document that sat in an inbox for three months before someone asked me to summarize it in five bullet points. By then, the funding cycle had moved on. What this analysis is not: a substitute for clinical governance, a replacement for operational budgeting, or a comprehensive quality improvement program. It is a diagnostic tool. It tells you where the system is and where it isn't efficient. It doesn't tell you how to fix everything. The fixes require separate initiatives, different expertise, and often organizational changes that this framework alone cannot drive.


