
What actually helps when your body starts changing
I spent three years working with women going through perimenopause, mostly nutrition-focused. I thought I had it figured out. Then a client came in who was doing everything right, reading all the right books, and still waking up at 3am drenched in sweat and too bloated to eat breakfast. That was the moment I realized most of what passes as advice out there is either oversimplified or straight-up wrong for a meaningful number of people. Healthy Eating For The Menopause isn't one thing. It's a collection of adjustments that shift depending on where you are in the process, what your current weight looks like, whether you have insulin resistance lurking, and how much exercise you're actually doing. The standard templates don't work because the hormonal landscape changes so much between early perimenopause, late perimenopause, and postmenopause.
Healthy Eating For The Menopause: what the basics actually look like
Here is the framework that has held up across thousands of conversations and dozens of case studies. Protein first, roughly 1.6 to 2.2 grams per kilogram of bodyweight daily. That's not optional if you want to hold onto muscle mass while your estrogen is dropping. Estrogen does some of the muscle-preserving work on its own. When it fades, the protein requirement goes up, not down. Most women in this age group are eating maybe 60 to 80 grams of protein per day without realizing it. You need to be in the 100 to 150 range depending on your size and activity level. Second, fiber. Not the kind you get from a supplement pill. I'm talking about whole food fiber, 30 to 40 grams a day, and it matters enormously for estrogen metabolism. Your liver processes estrogen and your gut has to excrete it. If your fiber intake is low, you get something called estrobolic back-absorption, which means the estrogen you already processed just gets reabsorbed into the bloodstream instead of leaving your body. This is one of the quiet contributors to persistent hot flashes and mood swings that nobody talks about enough. Third, don't fear dietary fat. The idea that low-fat is good here is dead wrong. Your sex hormones are built from cholesterol and fat. When you drop fat intake too aggressively, you can actually make hormone-related symptoms worse. Olive oil, avocado, fatty fish, nuts, seeds, full-fat Greek yogurt, eggs. These are not cheat meals, they're structural support for what your body is trying to do.
Where people routinely go wrong
The most common mistake I see is women adopting a strict low-calorie approach because they've gained weight during perimenopause and assume the solution is to eat less. The problem is that during this phase, your body is already under metabolic stress. Cortisol runs higher. Sleep is disrupted. Drop calories too far and your body interprets it as a famine event, holding onto visceral fat more aggressively while breaking down muscle. The scale might move, but your body composition gets worse and your symptoms often get worse too. Another mistake is relying on soy supplements in capsule form. There is a difference between eating whole soy foods like edamame, tofu, or miso and taking concentrated isoflavone pills. The whole food versions have a matrix of other compounds that modulate absorption and effect. The isolated supplements can do things like interfere with thyroid medication absorption in susceptible people. Whole foods are safer and more predictable. Alcohol is a bigger trigger than most women realize during perimenopause. Even one glass of wine can meaningfully increase hot flash frequency and severity for some people. It also disrupts the liver's ability to process estrogen efficiently. This isn't about morality, it's about biochemistry. If you're experiencing significant vasomotor symptoms, cutting alcohol entirely for six weeks and tracking what happens will give you clearer data than any blood test.
Get the Full Details

The caffeine nuance nobody mentions
Caffeine doesn't affect everyone the same way during menopause, but the mechanism is worth understanding. Caffeine increases cortisol release acutely. During perimenopause, your HPA axis is already more reactive because of fluctuating estrogen and progesterone. Adding caffeine on top of that can push you into a state where you feel anxious, restless, and then crash hard. I've had clients who swapped their morning coffee for matcha or just cut it out completely and reported that their afternoon anxiety and evening hot flashes dropped dramatically. It's not universal. Some people handle caffeine fine. But if you're struggling with anxiety or sleep, it's worth a trial elimination. One scenario that comes up a lot and rarely gets covered properly: women with both menopause symptoms and pre-existing gut issues like IBS. The high-fiber recommendation that works for most people can absolutely worsen IBS symptoms if you jump in too fast. I had a client who followed a standard menopause nutrition plan, hit 35 grams of fiber in a single week, and ended up with severe bloating and constipation that made her quit the whole approach. The workaround was gradual escalation. She went from about 12 grams of fiber per day to 15, then 18, then 22 over the course of six weeks. She focused on soluble fiber first, which is gentler on the gut, from sources like oats, chia seeds, psyllium husk, and cooked vegetables. Insoluble fiber from raw vegetables and wheat bran came later. She also added a probiotic strain specifically studied for IBS, Bifidobacterium infantis 35624, at 10 billion CFU daily. By week eight, she was at 30 grams of fiber with minimal bloating and noticeable improvement in both digestion and hot flash frequency. It took patience but it worked because it respected her gut's actual tolerance level.
Another edge case is women on birth control pills during perimenopause who are also trying to eat for hormone balance. The pill suppresses ovulation and stabilizes hormones artificially, which means some of the dietary strategies for natural hormone modulation have a different effect or reduced effect. Protein and fiber still matter enormously, but the soy and phytoestrogen advice needs to be taken with more caution because the pill already creates a synthetic hormonal environment. In these cases, the focus should be on supporting liver detoxification pathways through cruciferous vegetables, adequate B vitamins, and maintaining regular bowel movements rather than on phytoestrogen manipulation.
Meal timing and blood sugar
Blood sugar stability matters more during perimenopause than at almost any other adult stage. Declining estrogen affects how your cells respond to insulin. You can develop insulin resistance even if you've never had it before. This isn't something you can always catch on a standard blood panel either, since fasting glucose can look normal while your actual insulin levels are elevated. The practical indicator is usually energy crashes after meals, especially carb-heavy ones, combined with increased abdominal fat storage and cravings that feel impossible to resist. The fix isn't elimination diets. It's meal sequencing and combining. Eat protein and fiber before carbohydrates in a given meal. A study from Weizmann Institute showed this simple sequence can reduce post-meal glucose spikes by up to 73 percent. It sounds almost too simple, but it works because the protein and fiber slow gastric emptying and modulate the incretin response. Put a handful of nuts or some Greek yogurt before the bread, or eat your vegetables and protein first and save the starch for last.

Supplements that actually have evidence
I'm going to be blunt about this. Most menopause supplement brands are selling hope packaged in capsules. A few things actually have decent evidence behind them. Vitamin D is critical if you're deficient, which a large portion of women in this age group are. It affects everything from bone density to mood regulation to immune function. Get your levels checked rather than guessing. If you're below 30 nanograms per milliliter, supplementation is usually necessary and makes a noticeable difference in energy and joint symptoms within a few months. Magnesium glycinate or citrate, roughly 300 to 400 milligrams at night, helps with sleep quality, muscle tension, and can modestly reduce hot flash severity. I've seen this work consistently. It's inexpensive and has a strong safety profile at these doses.
Fish oil at two to three grams of combined EPA and DHA daily has evidence for reducing inflammation, supporting cognitive function during brain fog episodes, and may help with mood symptoms. The quality of the supplement matters significantly here. Cheap fish oil that's been exposed to heat or light can oxidize and do more harm than good. Calcium and vitamin K2 for bone health. Estrogen decline accelerates bone loss. Calcium alone isn't enough and can be problematic without K2 to direct it into bones rather than arteries. Think leafy greens, sardines, fermented foods, and a K2 supplement if your diet doesn't cover it.
What doesn't help and why people keep buying it
Detox teas, colon cleanses, and alkaline water diets have no meaningful impact on menopause symptoms. Your liver and kidneys are already detoxifying your body. Adding more stress through restrictive cleansing protocols just elevates cortisol further. The fact that these products remain on shelves is a testament to marketing budgets, not efficacy. Similarly, the idea that there is a single "menopause diet" is misleading. A diet that works well for a sedentary woman in her late fifties with significant insulin resistance will look very different from what supports an active woman in her early fifties who is still ovulating irregularly. Context matters enormously.
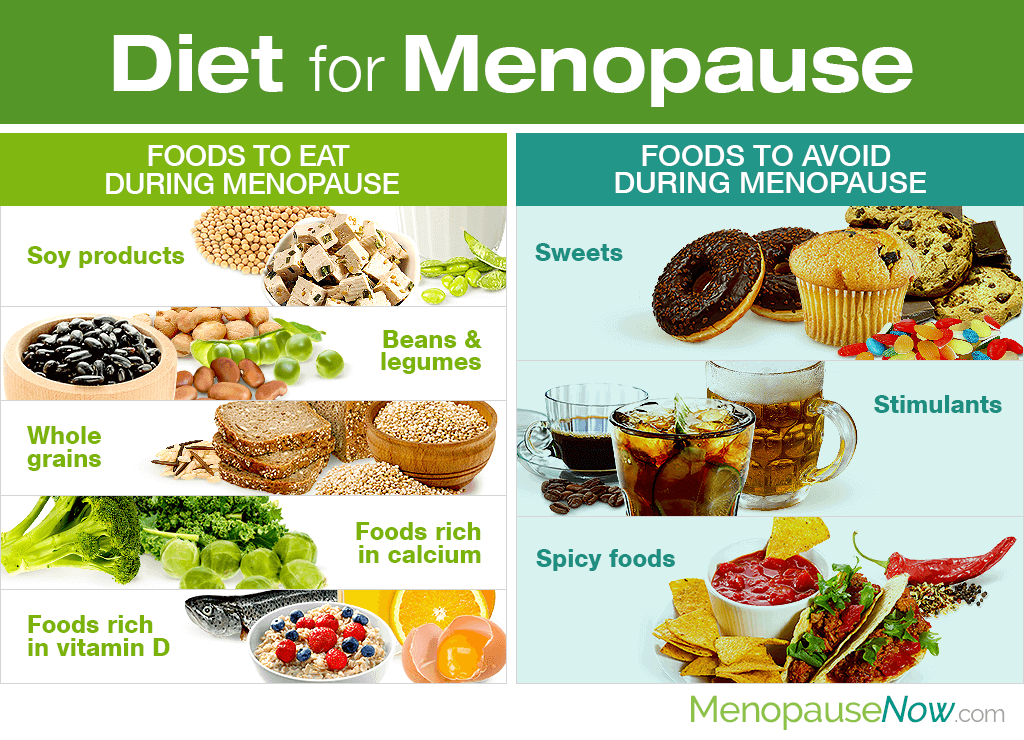
A realistic framework to start with
Don't overhaul everything at once. Pick three changes and stick with them for four weeks. Here is a concrete starting point: After three weeks, assess. If sleep improved and hot flashes decreased, you have data. If nothing changed, you adjust. Maybe the alcohol wasn't the trigger. Maybe you need to focus on protein timing or try a different fiber source. The process is iterative, not linear. The reason most people fail at this isn't lack of willpower. It's that they treat menopause nutrition like a short-term project instead of a systems change. Your hormonal environment is fundamentally different now than it was at thirty. What fed you then doesn't necessarily serve you now. The adjustments aren't drastic, but they do require paying attention to what's actually happening in your body rather than following someone else's template.


