Why You Should Skip the Labeled Version
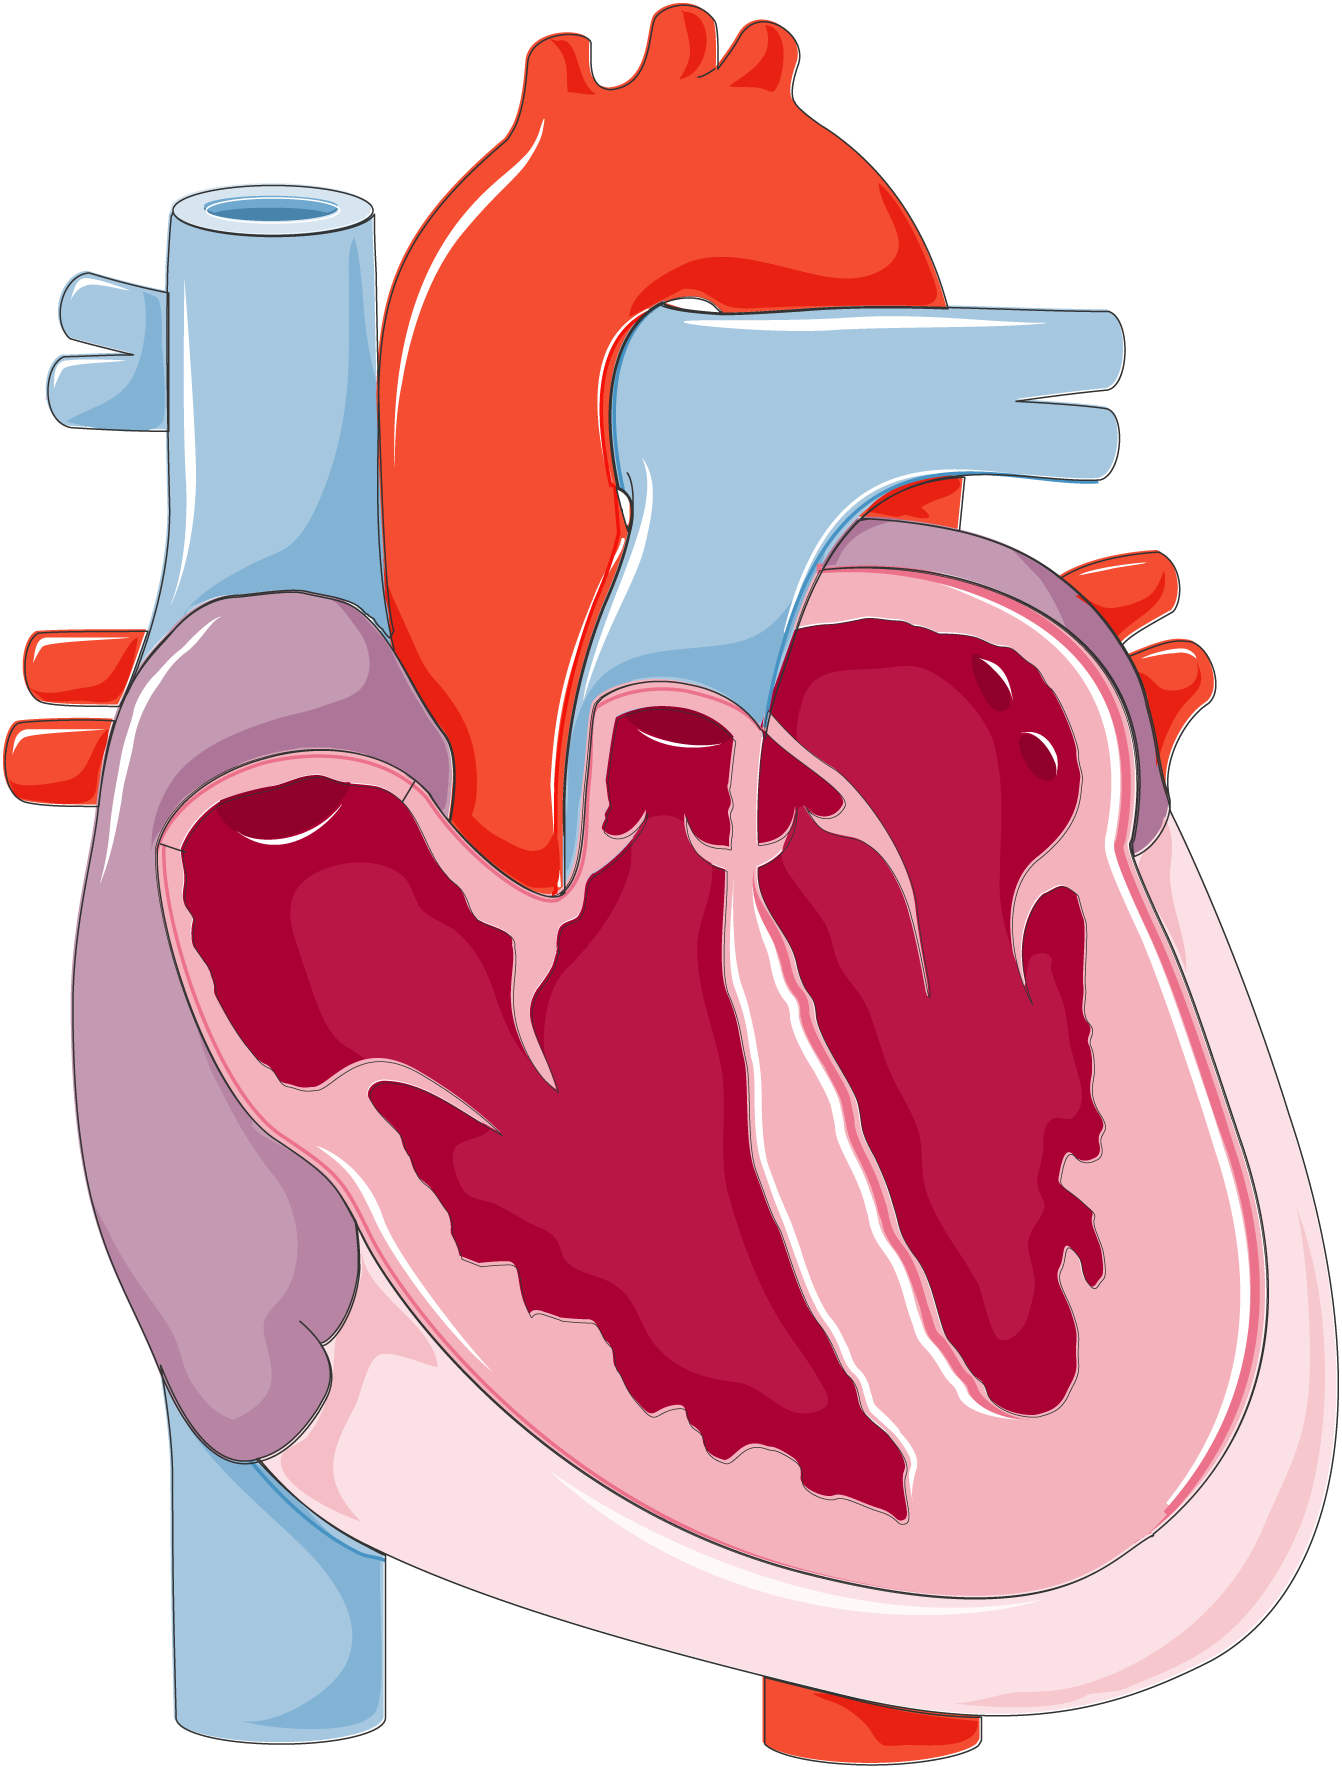
I've been teaching anatomy to pre-meds and nursing students for roughly twelve years, and honestly, the labeled diagrams are the single biggest waste of study time you can do. Everyone hands out those glossy textbook plates with every vessel and chamber clearly titled, and students just stare at it, read the labels, and feel like they understand. They don't. The moment you remove the text, you realize you barely know anything. A Heart Anatomy Diagram Unlabeled forces actual recall instead of pattern recognition. Reading "superior vena cava" underneath the drawing doesn't teach you anatomy. Memorizing the spatial relationship between the right atrium, the sulcus terminalis, and the crista terminalis without a single word on the page does. That's the difference between passing a practical exam and actually understanding cardiovascular structure for the rest of your career.
How to Use a Heart Anatomy Diagram Unlabeled Effectively
The standard mistake people make is grabbing a blank diagram and immediately trying to fill it from memory without first studying a labeled reference. It looks efficient, but it reinforces wrong information. The correct workflow takes longer upfront and saves you hours of relearning. Here's what I tell every student who comes to me struggling: Step one: Open a labeled diagram and study it for fifteen minutes. Don't memorize. Just orient yourself. Learn which vessels attach to which chamber. Note the difference between the coronary sinus sitting in the posterior atrioventricular groove and the anterior interventricular artery on the front of the heart. Step two: Close the labeled diagram completely. Pull up a blank Heart Anatomy Diagram Unlabeled version and fill it in from scratch. When you get stuck, don't peek immediately. Struggle with it for at least thirty seconds. That retrieval friction is where the actual learning happens. Neuroscience has known this for decades; the struggle is the signal that your brain is building connections.
Step three: Check your work against the labeled reference. Make corrections in a different colored pen so the errors are visually obvious. The red corrections matter more than the original answers. Step four: Repeat the blank version from memory one more time the next day, then again three days later. Spaced repetition beats marathon cram sessions by a wide margin. The interval matters more than the total hours you spend looking at the diagram.
Get the Full Details
What You Actually Need to Identify
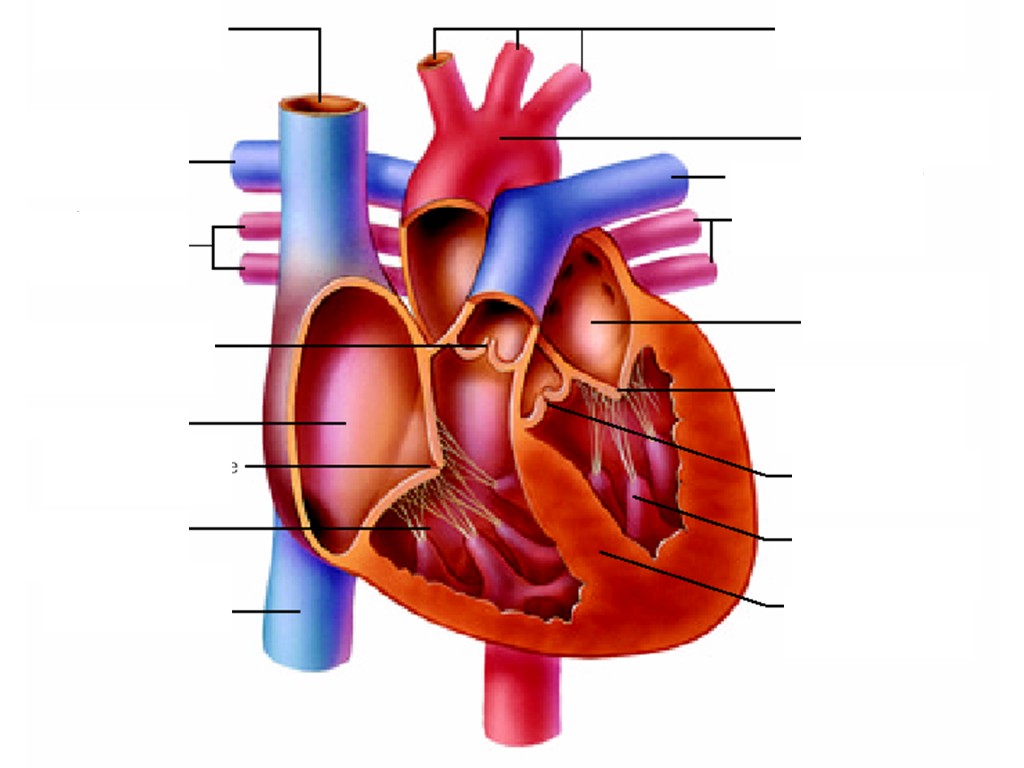
Not every unlabeled diagram test covers the same level of detail, but the core structures that appear consistently in medical programs are the following. If you can label these from memory, you're already above where most first-year students land. The four chambers form the foundation: right atrium, right ventricle, left atrium, left ventricle. Get these right in position. The left ventricle wall should be noticeably thicker than the right. Anyone labeling them equally is guessing. The major vessels are where people lose points. Superior vena cava enters the right atrium from above. Inferior vena cava enters from below. The pulmonary trunk exits the right ventricle and bifurcates into the left and right pulmonary arteries. The four pulmonary veins enter the left atrium. This one trips people up constantly because the veins aren't symmetric like the arteries. Two from each lung, entering the posterior wall of the left atrium.
The aorta is non-negotiable. Ascending aorta, aortic arch, descending thoracic aorta. The arch passes over the left pulmonary artery. That relationship is tested repeatedly. Most unlabeled diagrams you'll encounter in exams include the three branches off the arch: brachiocephalic trunk, left common carotid artery, and left subclavian artery. Draw them carefully. The valves deserve attention too. Tricuspid valve between right atrium and right ventricle. Pulmonary valve at the base of the pulmonary trunk. Mitral valve between left atrium and left ventricle. Aortic valve at the base of the aorta. The coronary sinus sits in the posterior atrioventricular groove. The thebesian veins are too small for most diagrams but showing up on that one tells the professor you've actually studied the text, not just the pictures.
Where I Got Stuck and What Worked
About five years ago, I was putting together exam questions for a cardiac anatomy practical. I pulled a standard unlabeled diagram from a free online source and used it for the first time. Half the students scored in the upper nineties. The other half were clustered around forty percent. I looked at the answer sheets and saw the same pattern of mistakes repeated across dozens of papers. Everyone kept labeling the ligamentum arteriosus as a vessel that still carries blood. They were drawing it as part of the pulmonary circulation pathway rather than understanding it as a fibrous remnant of the fetal ductus arteriosus. I had assumed that because the diagram showed it connected the aortic arch to the pulmonary trunk, students would infer its function. They didn't. The workaround was brutal but effective. I added a second unlabeled diagram that isolated just the arterial ligament region and forced students to label the structures without the surrounding context. Stripping away the distraction made the anatomical reality clearer. It took about twenty extra minutes per section but cut my exam score variance in half the next time around. Another recurring issue I noticed involves the coronary circulation. Students routinely confuse the left anterior descending artery with the posterior interventricular artery because both run near the interventricular septum. In most adults, the PIA comes from the right coronary artery and runs in the posterior interventricular groove. The LAD runs in the anterior interventricular groove. Draw those grooves correctly on your diagram and the artery names sort themselves out. If the grooves aren't visible, label the artery names based on which side of the heart you're viewing.

Where to Find Reliable Blank Diagrams
Most free resources online are low quality. The images are blurry, the proportions are wrong, or the diagrams leave out structures that every legitimate exam will include. I've compiled what actually works from practical use over several years. The OpenStax Anatomy and Physiology textbook includes downloadable unlabeled diagrams in the cardiovascular chapter. They're accurate enough for introductory courses and completely free. Download the PDF and use the figure exports rather than screen-capturing web pages. The resolution holds up when you print them. Kenhub offers free unlabeled heart diagrams if you create an account. Their images are clinically accurate and show the heart from multiple views: anterior, posterior, and inferior. The inferior view is where most students fail because it's the least practiced orientation. Do yourself a favor and drill that one.
AnatomyZone has a YouTube series with corresponding unlabeled worksheets on their website. The video walk-throughs are useful when you're stuck on a particular structure. I've used these when students insist on watching something before attempting the blank diagram, which is fine as long as the watching converts into actual labeling practice afterward. If you have access to Complete Anatomy or Visible Body software, both include exportable unlabeled images. The interactive 3D models help you rotate the heart and see relationships that flat diagrams flatten out. Printing a rotated view you can't quite understand is worse than not having it at all.
Pitfalls That Actually Cost Students Points
The first trap is perspective confusion. Anterior view diagrams show the right ventricle as the most anterior chamber. Posterior view diagrams completely rearrange the visual hierarchy. Students who only memorize the anterior view freeze when the exam switches to posterior. Practice both views with unlabeled diagrams until you can draw each one from memory. The second trap is asymmetry. The heart isn't symmetrical. The left ventricle is larger and forms the apex. The right atrium forms the right heart border. The superior vena cava is wider than the inferior. If your unlabeled diagram draws everything symmetrically, it's teaching you the wrong anatomy. Good unlabeled diagrams preserve these proportional differences because they matter for identification. The third trap is ignoring surface landmarks. The atrioventricular groove and the interventricular grooves are surface features that separate chambers externally. Many unlabeled diagrams either omit these grooves or draw them inconsistently. Including them correctly on your own redrawn versions improves accuracy dramatically. You start recognizing structures by their grooves rather than by guessing based on position alone.

The Hard Truth About Using These Diagrams
Unlabeled heart diagrams work well when you already have a baseline understanding of cardiac anatomy. They are not a primary learning tool for absolute beginners. If you open a blank diagram with zero prior study, you'll guess, reinforce incorrect information, and waste time correcting it later. Use labeled references first. Then switch to unlabeled for testing and retention. The diagrams also have a hard ceiling. They cannot teach you pathological variations. A congenital anomaly like transposition of the great arteries won't appear on any standard unlabeled diagram you'll find online. For advanced courses, you need pathology atlases alongside the standard anatomical ones. Using only normal anatomy diagrams in a course that tests congenital variations is a reliable way to fail. My recommendation for anyone serious about this material is to pair the unlabeled diagram practice with cadaver lab observation if available. No flat image captures the texture, the variability, or the actual three-dimensional relationships that exist in real tissue. I've had students who aced the diagram labeling portion fail the practical exam because the actual heart they were handed looked nothing like the textbook version. The coronary arteries branching patterns vary significantly between individuals. The diagrams are guides, not guarantees.
The process of repeatedly filling in a Heart Anatomy Diagram Unlabeled is tedious and. You will make the same mistakes multiple times. That's normal. The improvement is incremental and almost invisible day to day. But after three or four weeks of consistent practice, the structures become automatic. You stop translating labels into images and start recognizing anatomy directly. That's the point where the effort finally pays off.