Getting Started With Labeled Heart Anatomy Models
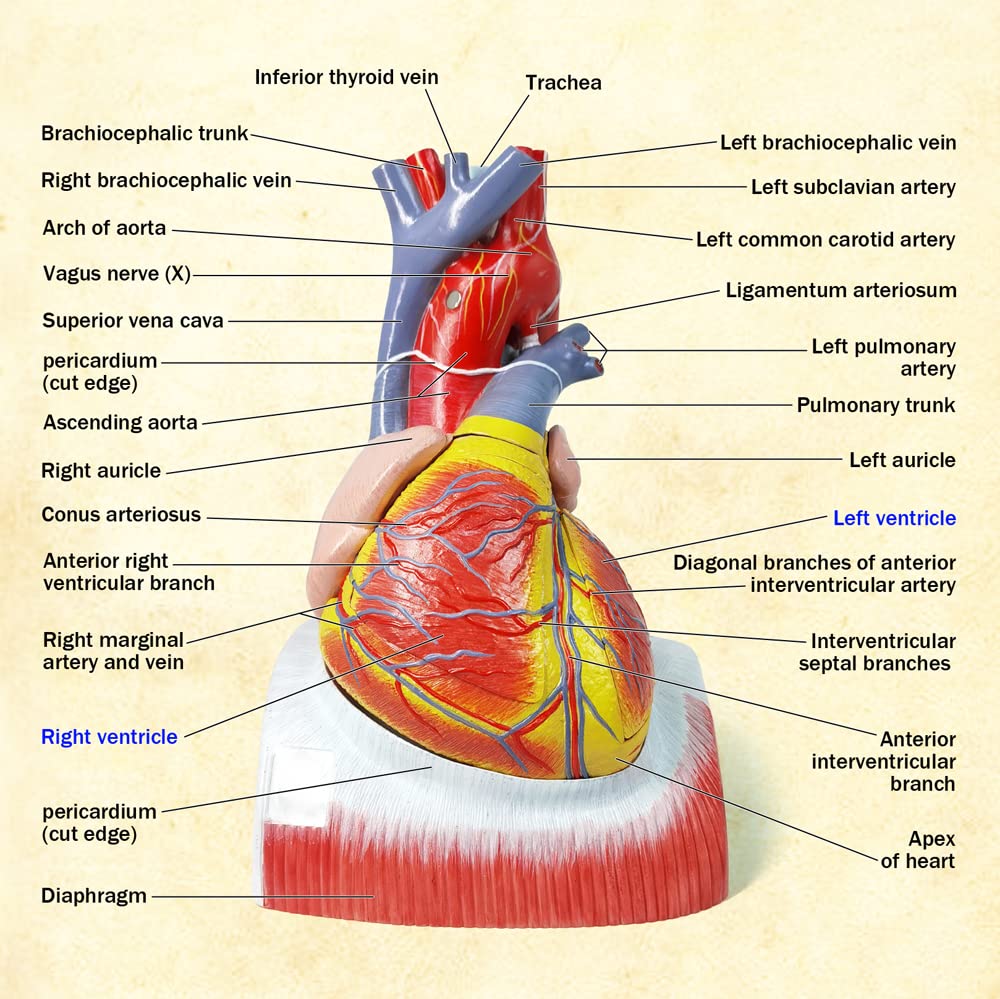
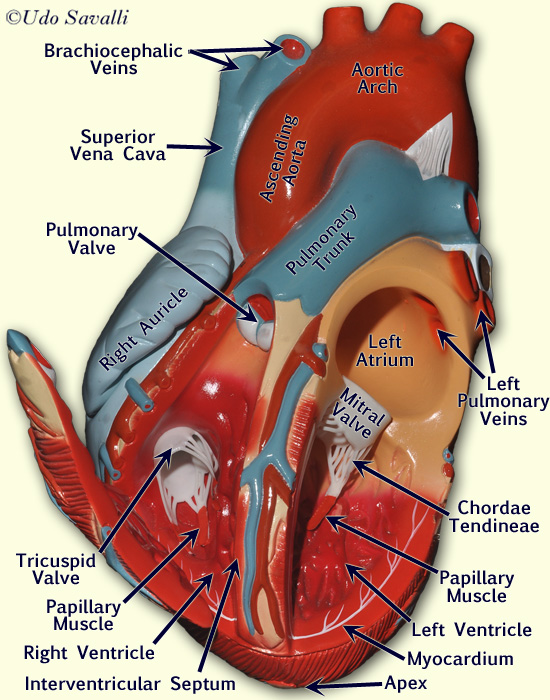
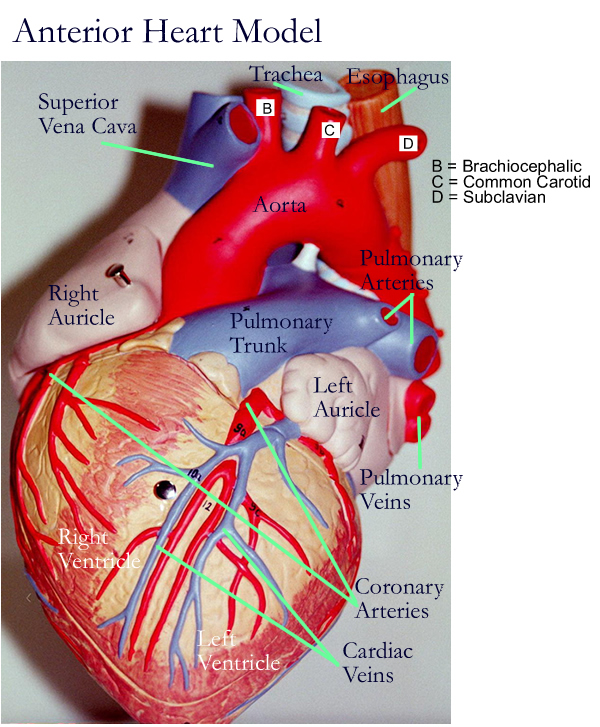
I keep running into people who need a labeled heart model for class presentations, study groups, or patient education and don't know where to actually find one that isn't just some clip art from 2003. The market is cluttered with low-quality renders that miss basic labeling conventions. Here's what actually works and where to look. The two main formats you'll encounter are physical anatomical models and digital 3D files. Physical models from companies like 3B Scientific or Anatomical Trading Company tend to hold up better over time, but they cost between 40 and 150 dollars depending on the detail level. Digital models are free or cheap, but the labeling quality varies wildly. If you're doing medical school level work, you need something more precise than a generic free download. For digital work, Sketchfab and Thirteenth Floor have decent options. The Thingiverse section has some printable models too, though many are outdated. I usually check the NCBI's PubChem or the Visible Human Project for publicly available datasets when I need accurate labeling. The Visible Human Project specifically has cross-sectional data with proper anatomical terminology that most free downloads don't bother including.
Practical Labeling Standards You Should Know
Most beginners don't realize that "labeled" means different things in different contexts. A nursing student needs chamber names, valve positions, and major vessel connections. A surgery resident needs coronary artery territories, conduction system pathways, and fascicular anatomy. The model you pick should match the detail level your audience actually requires. Over-labeling is just as bad as under-labeling, especially when you're trying to teach someone something specific. The standard labeling convention follows Terminologia Anatomica, which is the international standard for anatomical nomenclature. If a model uses Latin terms without English equivalents, it's probably aimed at a professional audience rather than students. Check the legend. If it lists "aorta" but also "arteria pulmonalis" without clarifying which is which, that's a red flag. The model might be translated from another language or just copied from an older textbook without updates. I had a specific problem last year where a client ordered a labeled heart model for a cardiac surgery workshop. The vendor sent a model where the coronary arteries were labeled correctly but the veins were completely misidentified. The great cardiac vein was labeled as the small cardiac vein, and the posterior interventular vein was missing entirely. For a surgery workshop, that level of error is a real liability because residents are going to study from that model. I ended up annotating my own overlay using Blender and exporting corrected labels, which took about three hours but saved the workshop from going forward with bad reference material.
How to Evaluate and Use These Models
When you're reviewing a Heart Model Anatomy Labeled product, check a few things quickly. Look at the valve cusps first. A correct model shows the left coronary cusp, right coronary cusp, and non-coronary cusp of the aortic valve with proper orientation. If the cusps look wrong or are labeled generically as "aortic valves," move on. Next, verify the interatrial septum has the fossa ovalis labeled. Most cheap models skip that entirely. Then check the pulmonary veins. There should be four of them clearly labeled, not just a generic "pulmonary vein" tag on the side. For physical models, run your finger along the coronary sulcus. It should be clearly defined as a groove between the atria and ventricles. In cheaper models, this groove is either missing or painted on inconsistently, which makes it harder for students to understand the spatial relationship between chambers. The model should also show the difference between the trabeculae carneae in the ventricles versus the smooth walls of the atria. That's a basic anatomical distinction that gets glossed over in most commercial products. If you're using digital models in software like Blender, Maya, or Unity, the labeling is usually just text overlays or vertex markers. You'll need to import the file, apply your own labels, and make sure the annotations don't obscure critical structures. I typically use Blender's geometry nodes system for this because it lets me attach text labels to specific vertices and rotate them based on camera angle. That way the labels stay readable from multiple viewing angles without floating in weird positions. It's a bit of a learning curve if you've never used geometry nodes, but it pays off when you need to present the model from different perspectives.
Get the Full Details

Heart Model Anatomy Labeled Common Pitfalls and Workarounds
One thing nobody warns you about is scale. Many labeled models are built to a standard size that doesn't match real anatomical proportions. The ventricles might look appropriately sized, but the atria could be disproportionately small or large depending on the artist's interpretation. This matters if you're using the model for measurement or surgical planning. I've seen people try to estimate chamber volumes from a model that's off by 20 percent, which is enough to throw off calculations entirely. Another issue is the labeling of the cardiac conduction system. Most commercial models don't include the sinoatrial node, atrioventricular node, Bundle of His, or Purkinje fibers at all. If your work requires that level of detail, you're going to need a specialized model or you're going to add the labels yourself. I keep a reference set of conduction system measurements from Gray's Anatomy and cross-check whatever model I'm using against those values. It takes maybe ten minutes and prevents you from teaching or presenting incorrect information. The biggest limitation of most labeled heart models is that they show a single static view. Real cardiac anatomy is dynamic. The heart changes shape during systole and diastole. A labeled model that only shows the heart in one position can give students a false sense of how the chambers relate to each other spatially. I usually supplement any static model with a short video or animation showing the cardiac cycle. Free options exist on YouTube channels like the NMBR or Osmosis, but I prefer embedding my own recordings when I'm doing presentations so I can control the timing and narration.
There's also the question of pathology versions. A standard labeled heart model is useful, but knowing which structures change during common diseases is where the real educational value comes in. If you're studying for exams or preparing teaching materials, having access to models that show hypertrophy, valve stenosis, or septal defects alongside the normal anatomy makes a significant difference. Some vendors like 3B Scientific sell separate pathology models, but they're expensive. A more practical approach is to find a high-quality normal model and then use a 3D editor to create your own pathological variations. I've done this for several courses and it took about twenty minutes per variant once I had the workflow figured out. If you need a quick starting point for downloading, the Smithsonian's National Museum of Natural History has a public domain collection of anatomical illustrations that can be adapted into labels. The Wellcome Collection also has historical anatomical prints that are freely available, though they're not 3D models. For actual 3D files, the NIH's National Library of Medicine has some datasets through their NCBI bookshelf resources. These aren't always ready-to-use with labels, but they're anatomically accurate and you can add your own annotations. The bottom line is that finding a good labeled heart model usually means spending more time vetting options than the purchase price suggests. Cheap models look fine at a glance but fall apart under scrutiny. Take the extra twenty minutes to verify the labels against a standard reference like Netter's Atlas of Human Anatomy before you commit to using anything in a teaching or clinical setting. It saves you from having to redo the work later when someone points out an error.