Understanding HRV Measurement Methods
The most reliable way to measure heart rate variability is using a chest strap or FDA-cleared device that records R-R intervals, then calculating RMSSD from at least 5 minutes of resting data taken in the morning before you get out of bed. I stopped relying on phone-camera PPG sensors years ago after noticing they gave wildly different readings depending on room temperature and how firmly I pressed the phone against my finger. The chest strap approach takes about 90 seconds to set up, and once you have the raw data you can run it through Kubios HRV or a similar tool that spits out RMSSD in milliseconds. RMSSD is the gold standard for tracking parasympathetic nervous system activity, and it is the metric you will see in nearly every peer-reviewed study on HRV and aging. SDNN is also useful but more sensitive to short-term trends and breathing patterns, which makes it harder to interpret consistently from day to day.
Heart Rate Variability Chart By Age
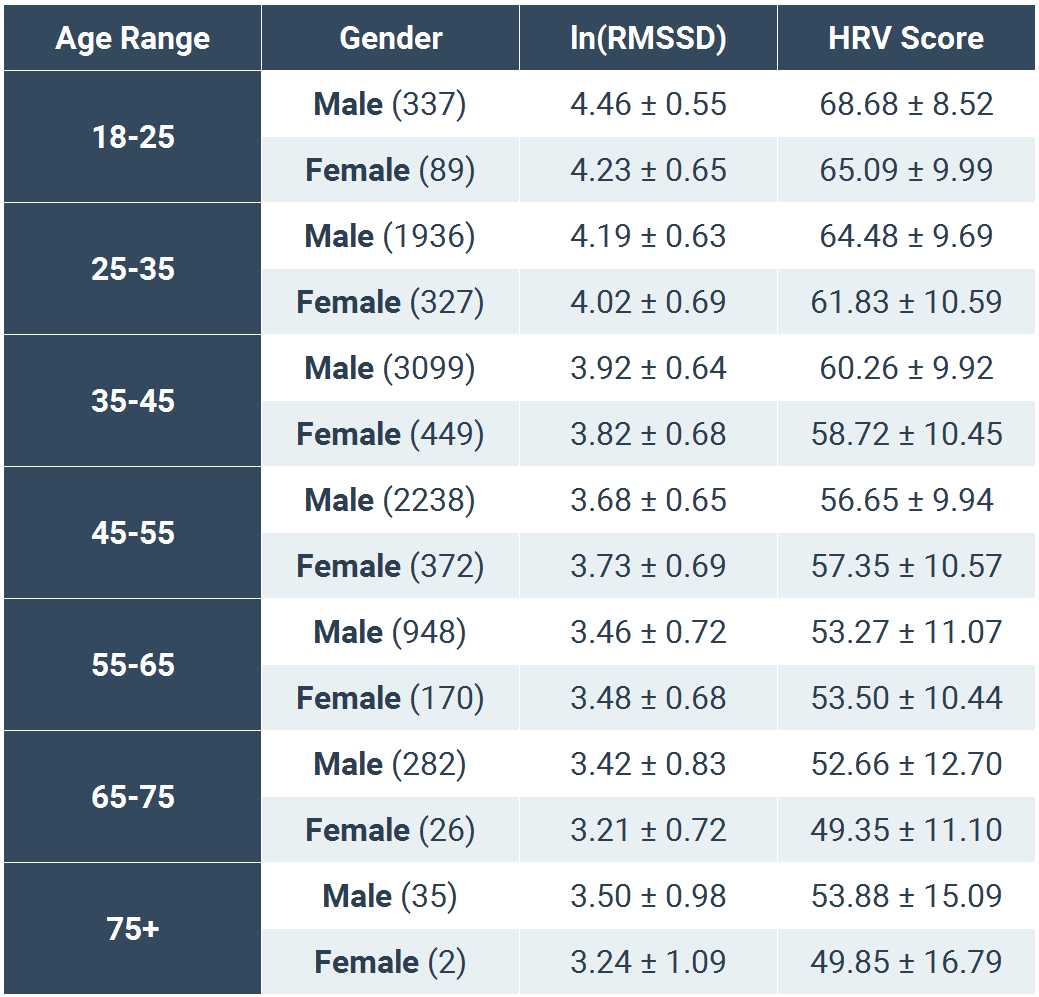
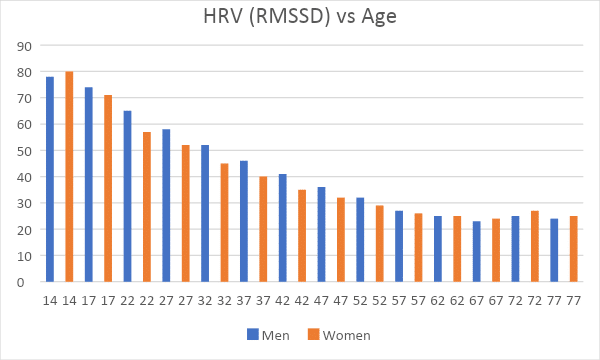
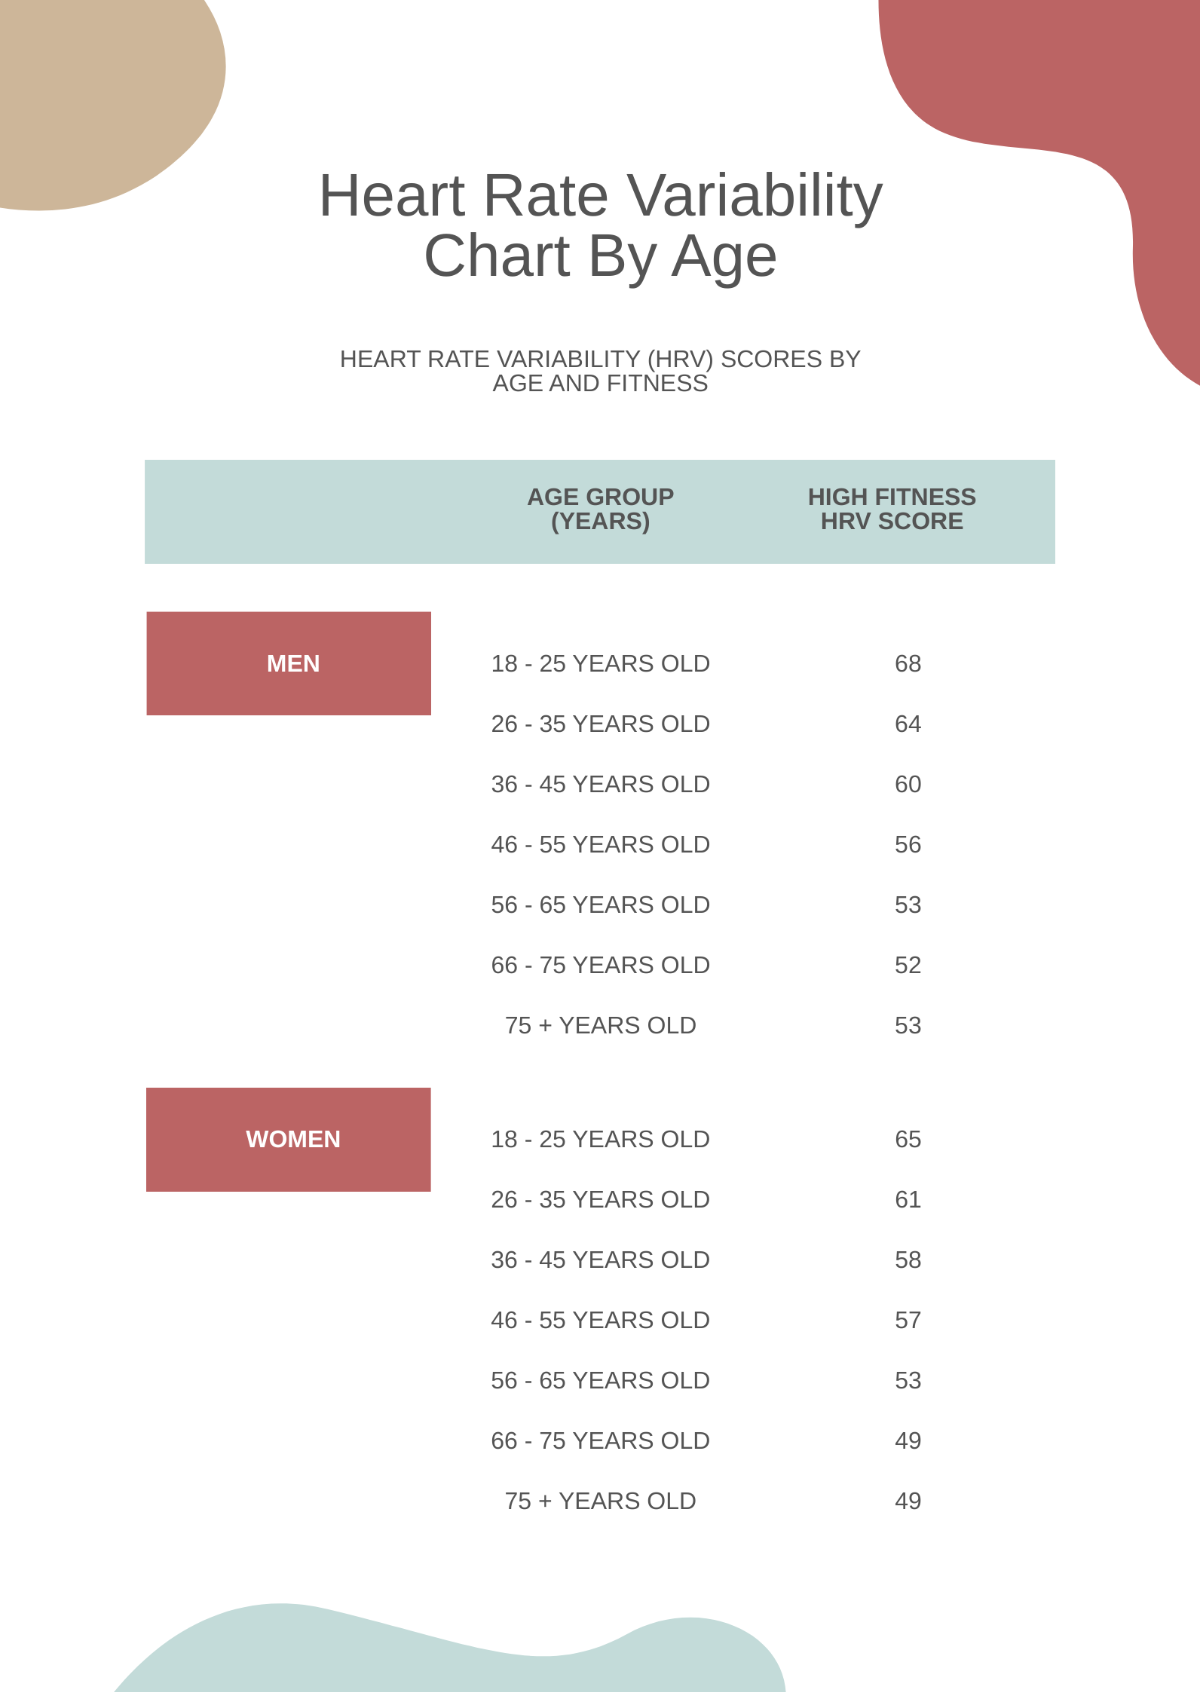
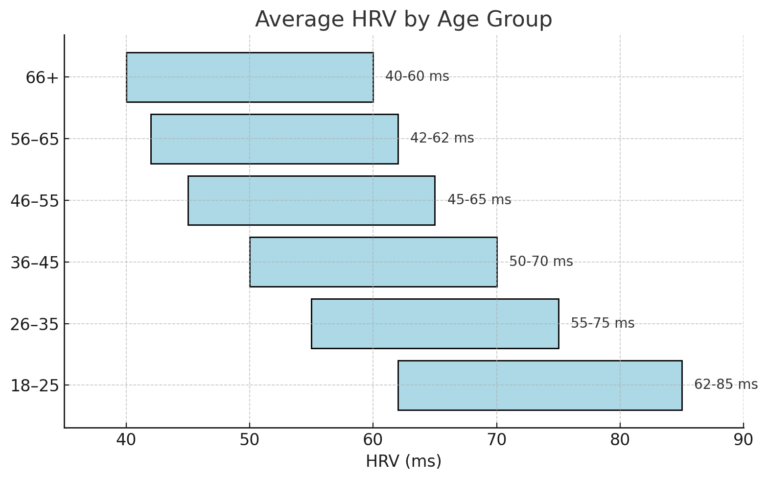
When you look at a Heart Rate Variability Chart By Age, you are usually seeing something like this: adults in their early twenties often average 55-75 ms RMSSD, people in their thirties and forties drop to roughly 40-60 ms, and by age sixty the typical range falls somewhere between 25-45 ms. These are broad population averages though, and they do not account for training status, chronic stress, sleep quality, or medications. A well-trained endurance athlete in their fifties might still sit comfortably in the 60-80 ms range, while a sedentary forty-year-old with high work stress could regularly register below 30 ms. The chart gives you a starting reference point, but it is not a diagnostic tool. I hit a wall with generic HRV charts about three years ago when my own readings started looking terrible by age standards even though I felt fine and was sleeping well. I was forty-two, logging consistent morning RMSSD values in the low forties, and the app I was using flagged everything as "poor recovery." It turned out the app was comparing me against a dataset that skewed heavily toward younger athletes, so my perfectly normal values were being mislabeled. I switched to tracking my own baseline instead, establishing a rolling 30-day average and only flagging deviations that exceeded two standard deviations from that personal norm. That fixed the false alarms immediately, and it also made the data actually useful for adjusting training load. Age explains maybe thirty to forty percent of the variation in resting HRV. The rest comes from a messy pile of lifestyle and physiological factors that interact with each other in ways that are hard to untangle. Alcohol is one of the biggest disruptors. A single heavy drinking session can suppress RMSSD for up to seventy-two hours, and the suppression often outlasts the hangover symptoms. I learned this the hard way during a week-long conference where I kept wondering why my recovery scores looked garbage despite sleeping seven hours and taking it easy. One session of drinks at dinner wiped out my HRV for three days straight, and the chart did not warn me about that.
Heat exposure changes things too. Sauna use, hot baths, or training in warm environments can initially raise HRV for a day or two, then depress it if you push too hard without adequate recovery. Conversely, cold exposure from ice baths or cold showers tends to suppress HRV for twenty-four to forty-eight hours afterward, which is counterintuitive for people who assume cold is purely restorative. Morning sunlight and time spent outdoors also matters more than most trackers account for. I noticed my readings improved by roughly 8-12% RMSSD during months when I got at least thirty minutes of morning sun before breakfast compared to winter months when I worked indoors starting at seven in the morning.
Get the Full Details
Common Mistakes People Make When Reading HRV Data
The biggest mistake is treating a single reading as meaningful. One bad night, a late meal, or even just sleeping on your right side instead of your back can knock your RMSSD down by ten to twenty percent on any given morning. You need at least seven to fourteen days of consistent measurement before you can establish a reliable personal baseline, and even then daily fluctuations are normal. Another mistake is trying to compare your numbers to someone else's without knowing how they collected the data. Phone apps use different sensors, different calculation windows, and different filtering methods, so their numbers are not interchangeable with chest strap measurements. People also misinterpret the direction of change. A rising HRV trend usually means your nervous system is adapting well to training stress, but it can also signal that you are becoming ill. I had one stretch where my RMSSD climbed from 45 ms to 62 ms over four days, and I felt great. Turns out I was coming down with a mild respiratory infection, and the spike represented sympathetic overdrive rather than true recovery. The trick is watching the trend alongside subjective markers like resting heart rate, sleep quality, and how you actually feel, rather than letting the number drive every decision.
How to Build a Personal Reference System
Instead of relying on generic charts, set up a personal tracking system that accounts for your own age, fitness level, and lifestyle. Measure every morning within five minutes of waking, before caffeine, before food, and ideally while still lying down. Use the same device every single time. Calculate your rolling 30-day average and your rolling 7-day average, then track the ratio between them. When the 7-day average drops below eighty percent of your 30-day baseline, that is usually a signal to reduce training intensity or add an extra rest day. Also track contextual factors alongside your HRV numbers: alcohol intake, sleep duration, life stress events, training load, illness symptoms, and weather changes. A spreadsheet or a simple note app entry works fine. Within three months you will start seeing patterns that no generic chart can show you, because those patterns are specific to your body and your schedule. The generic Heart Rate Variability Chart By Age is useful as a rough sanity check, but it should never override your own longitudinal data.
When HRV Data Stops Being Useful
There are scenarios where HRV measurements become essentially noise. People on beta-blockers, calcium channel blockers, or certain antidepressants have blunted autonomic responses, which means their HRV readings do not reflect stress or recovery the way they would in someone without those medications. Atrial fibrillation makes standard HRV analysis invalid since the underlying rhythm is irregular by definition. Post-surgical patients and people managing acute illness should not rely on HRV trends for decision-making without medical supervision, because the autonomic nervous system is in a state of flux that has nothing to do with training load. Even for healthy individuals, HRV should not be the sole metric for judging readiness. If your HRV says you should train hard but your resting heart rate is elevated by five beats per minute and you feel sluggish, the combined signal usually points to incomplete recovery regardless of what the variability number shows. The practical takeaway is to use HRV as one input among several, not as a standalone oracle. The most useful approach is combining morning HRV, resting heart rate, and subjective wellness scores into a simple three-number dashboard, then making decisions based on the convergence of all three signals rather than any single data point.