Heat Therapy For Depression: What Actually Happens When You Sit in a Sauna
The basic mechanism is straightforward enough. Exposing your body to sustained high temperatures triggers a cascade of physiological responses. Your core temperature rises. Blood vessels dilate. Heart rate increases to something between 100 and 130 beats per minute, which is roughly the same cardiovascular load as a moderate walk. The body then activates its cooling systems—sweating, increased circulation to the skin surface. But the part that matters for mood regulation is the downstream effect on neurochemistry and the stress-response system. Research from the University of Kuopio in Finland followed over a thousand participants and found that regular dry sauna bathing—four to seven sessions per week—was associated with a significantly lower risk of developing depressive symptoms compared to once-weekly sauna use. The protective effect was dose-dependent. More frequent exposure correlated with better outcomes. A 2019 study in the Journal of Affective Disorders found that a single whole-body hyperthermia session produced measurable improvements in mood and fatigue scores that lasted roughly 30 to 45 minutes post-session, and regular practitioners reported more sustained baseline improvements over several weeks. The proposed biological mechanisms involve several overlapping systems. Heat shock proteins are upregulated during thermal stress. These proteins help repair misfolded proteins and reduce cellular inflammation, which is increasingly implicated in depressive pathology. Brain-derived neurotrophic factor, or BDNF, tends to increase after repeated heat exposure. BDNF supports neuronal survival and plasticity, and depressed patients consistently show lower BDNF levels. There's also evidence that sustained heat exposure modulates the hypothalamic-pituitary-adrenal axis, which controls cortisol release. Chronic depression often involves HPA-axis dysregulation, and thermal stress may help recalibrate it over time through repeated, controlled exposure.
Implementing Heat Therapy For Depression: Protocol and Practical Constraints
Here is the straightforward protocol most of the published studies use. Dry sauna at 70 to 90 degrees Celsius, or a infrared sauna at 50 to 60 degrees Celsius. Session duration of 15 to 20 minutes. Target heart rate should be elevated but not to the point of distress. Cool down gradually. Rest for 10 to 15 minutes after. Repeat three to four times per week minimum. The Finnish studies suggested that four or more sessions per week was where the statistically significant depression-protective effects emerged, so doing it once a week is probably not going to move the needle much. I need to be blunt about the limitations because this is not a treatment you can just add to a existing regimen and expect immediate results. The evidence base is still relatively small. Most studies are observational rather than randomized controlled trials. The effect sizes are modest. Heat therapy is not going to replace SSRIs or psychotherapy for anyone with moderate to severe depression. What it does is provide a adjunctive tool that some people find useful, particularly for the fatigue, psychomotor retardation, and low-grade inflammation components of depression. It is not a magic bullet. There are specific edge cases that trip people up. One thing I encountered when researching protocols for clients: the cooling-down phase is where most of the benefit actually happens, not the heating phase. After a sauna session, your body enters a post-exercise hypotension window that can last 30 to 60 minutes. During this time, there is increased parasympathetic activity, which is the relaxation state. If you get up immediately and rush back to your day, you cut off the window where the nervous system is actually transitioning out of sympathetic dominance. The recommendation in the literature is to sit or lie down for at least 10 minutes after exiting, preferably in a cool but not cold environment. Do not jump into an ice bath right after unless you are specifically doing contrast therapy, and even then, the cooling should be gradual.
Another practical issue is hydration. A single sauna session can cause a fluid loss of 1 to 2 liters through sweating. Dehydration itself worsens depressive symptoms—cognitive fog, fatigue, irritability. So you need to replace fluids aggressively. Water alone is not sufficient because you are losing sodium and potassium. Electrolyte supplementation is necessary if you are doing this regularly. Without it, you will feel worse the day after, not better, and you will blame the sauna instead of the electrolyte deficit. Contraindications are important. Cardiovascular disease is the primary concern. The combination of vasodilation, increased heart rate, and blood pressure changes during and after a session can be dangerous for people with uncontrolled hypertension, recent myocardial infarction, or severe valvular disease. Pregnant women should avoid sauna use. Lithium users should be extremely cautious because dehydration concentrates lithium in the blood and can lead to toxicity. Some psychiatric medications, particularly those affecting thermoregulation like tricyclic antidepressants and antipsychotics, can impair your ability to sweat and cool down safely. If you are on any of these, consult a physician before starting. A counter-intuitive point that most people miss: the temperature does not need to be uncomfortably high for the therapeutic effect to occur. Infrared saunas operate at lower temperatures but still raise core body temperature effectively because they heat the body directly rather than heating the air around you. For someone who finds traditional saunas intolerable due to heat anxiety or claustrophobia, an infrared unit at 50 to 60 degrees Celsius for 20 minutes may produce the same physiological stress response without the psychological aversion. The depression benefit comes from the core temperature elevation and the resulting biological cascade, not from suffering through extreme heat.
Get the Full Details
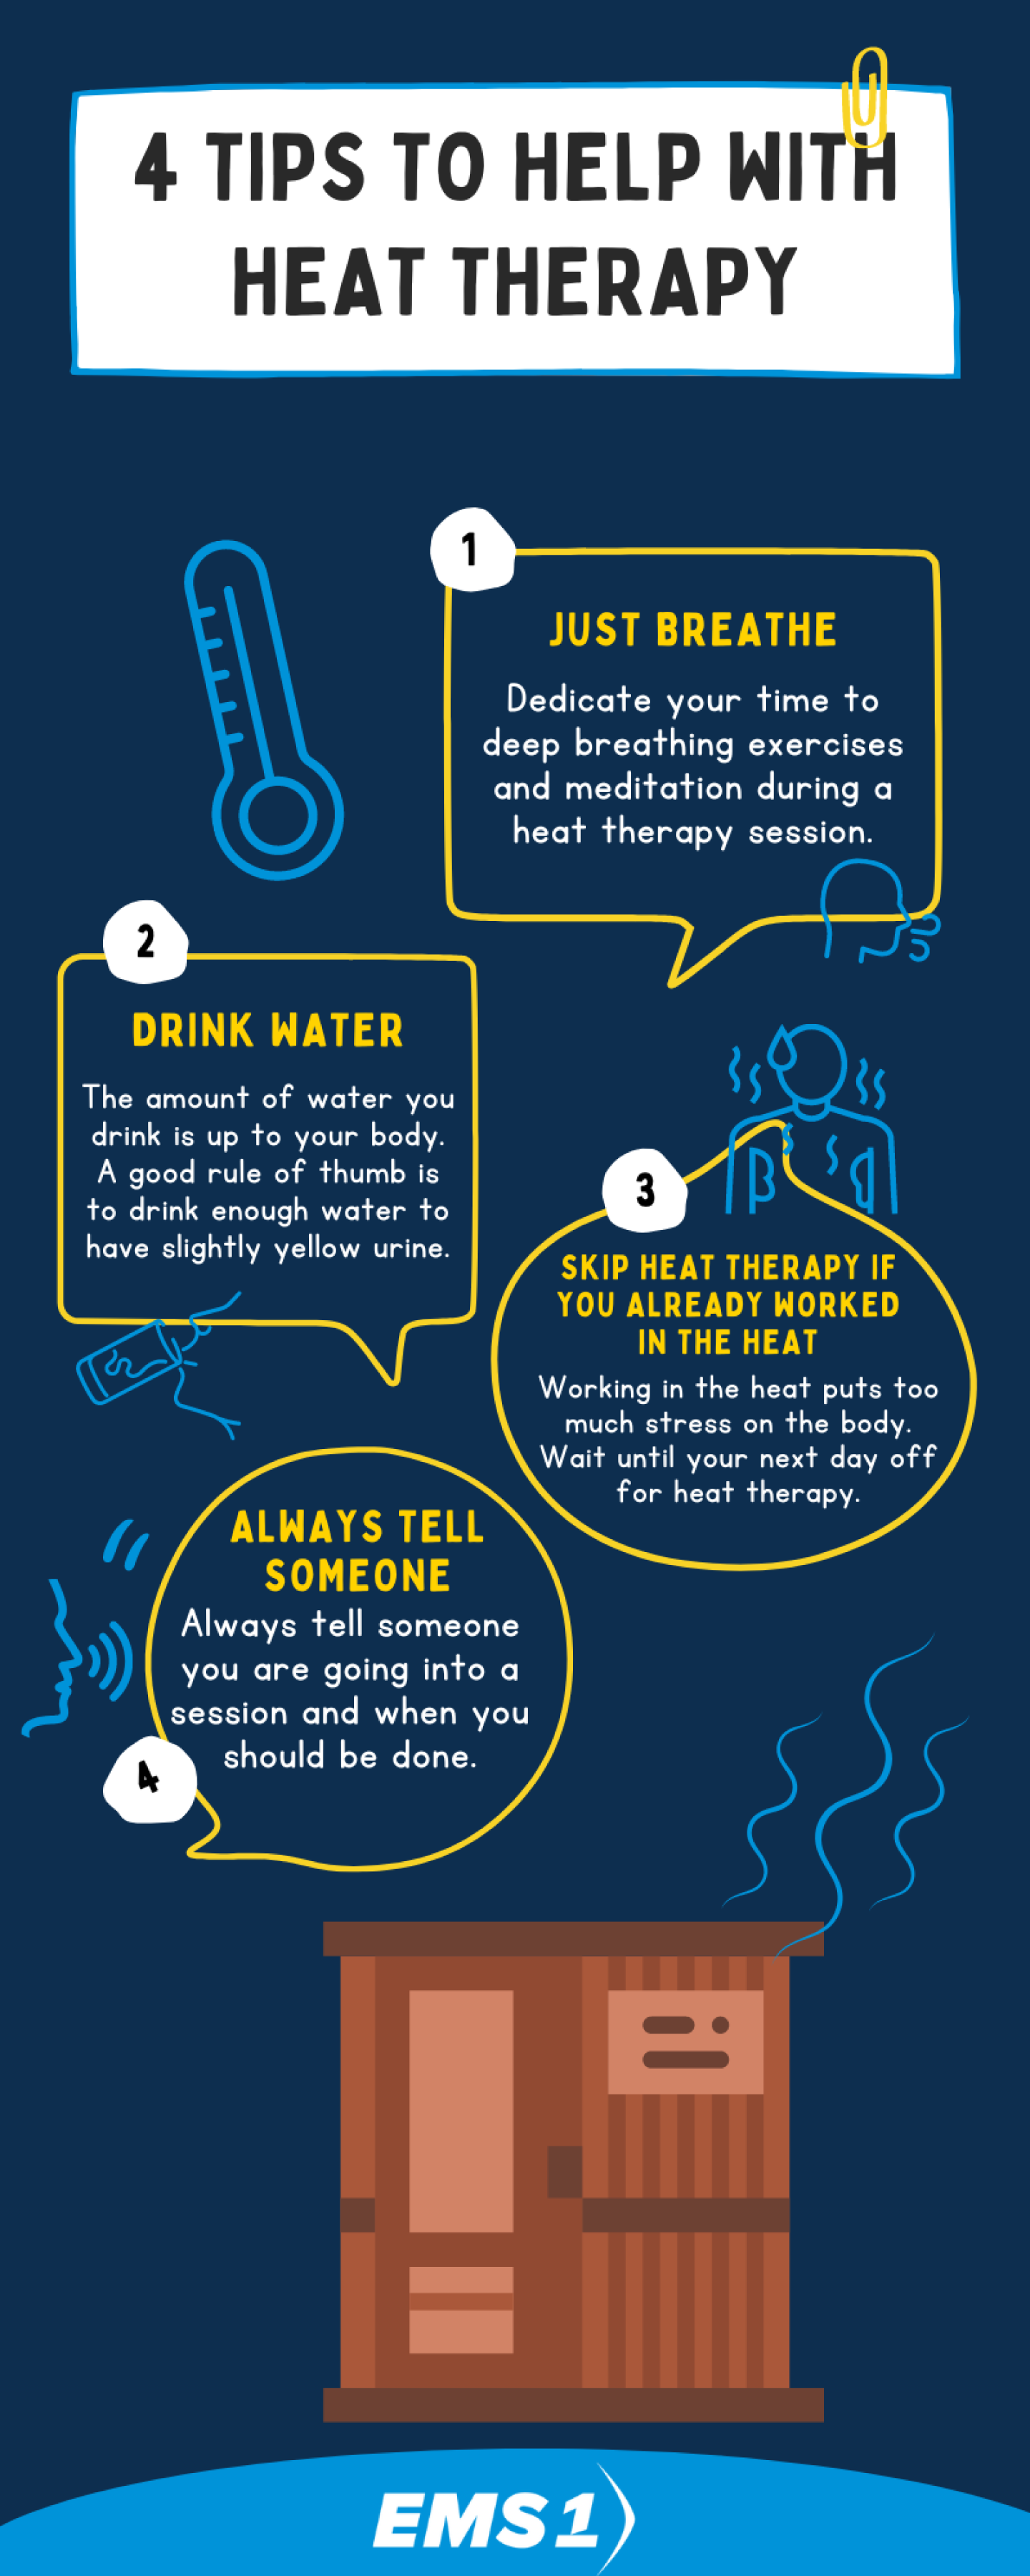
The other counter-intuitive finding is that consistency matters far more than intensity. A single 45-minute session at 100 degrees Celsius will not produce lasting benefits. Three 15-minute sessions per week at 75 degrees Celsius will. The repeated, moderate stress of thermal exposure appears to be what drives the adaptive responses—increased BDNF, improved HPA-axis regulation, reduced inflammatory markers. One extreme session just causes acute stress without giving the body time to adapt. If you want to track whether this is actually helping, do not rely on subjective mood ratings alone. They are too variable. Track sleep quality, resting heart rate, and morning fatigue levels. These are more objective measures that correlate with the physiological changes heat therapy produces. If your resting heart rate drops over three to four weeks and your sleep deepens, the therapy is likely working even if your mood feels unchanged in the short term. Mood improvements tend to lag behind physiological changes by one to two weeks. A final practical note: the equipment choice matters. Cheap infrared panels with inconsistent temperature regulation will not deliver a stable core temperature rise. Look for units that maintain temperature within 2 degrees Celsius of the set point. Cheaper models often overshoot and undershoot, which means your body is cycling between heat stress and cooling off repeatedly instead of maintaining a steady thermal load. That cycling reduces the effectiveness and can make the sessions feel jarring rather than relaxing.