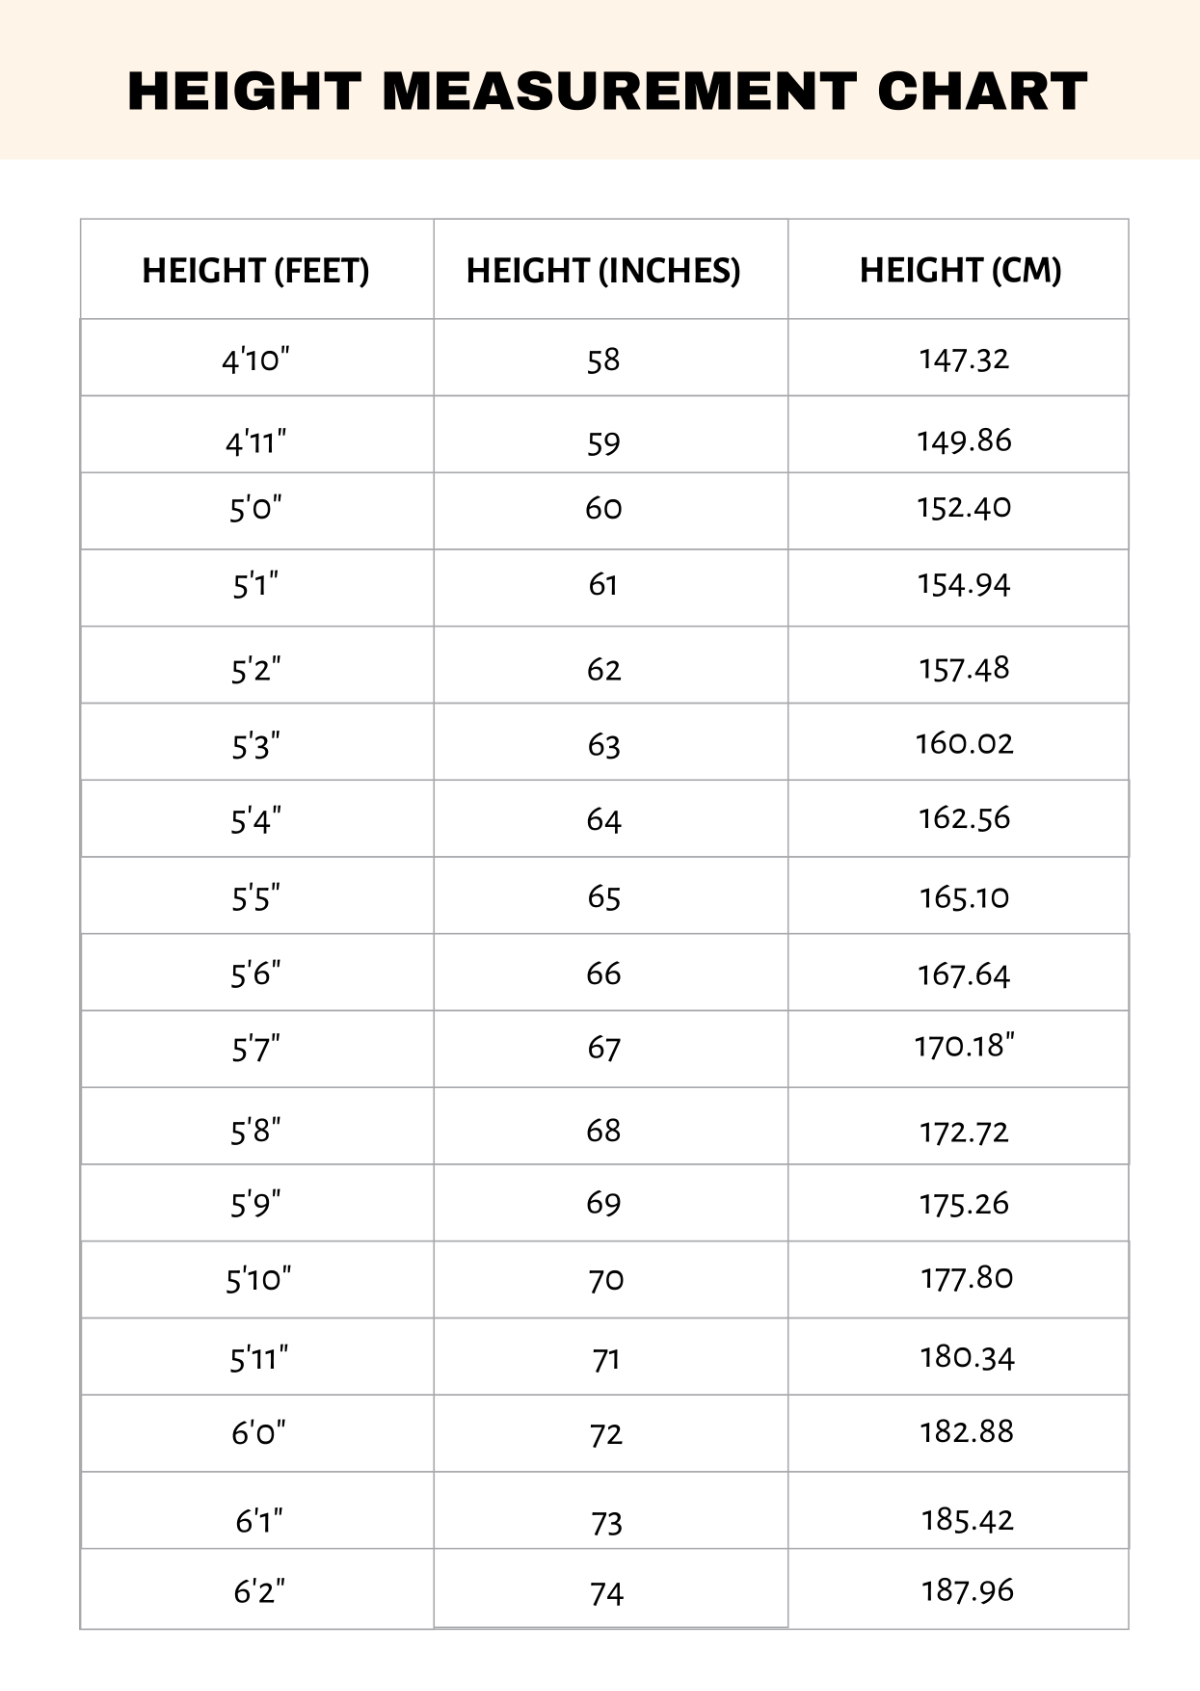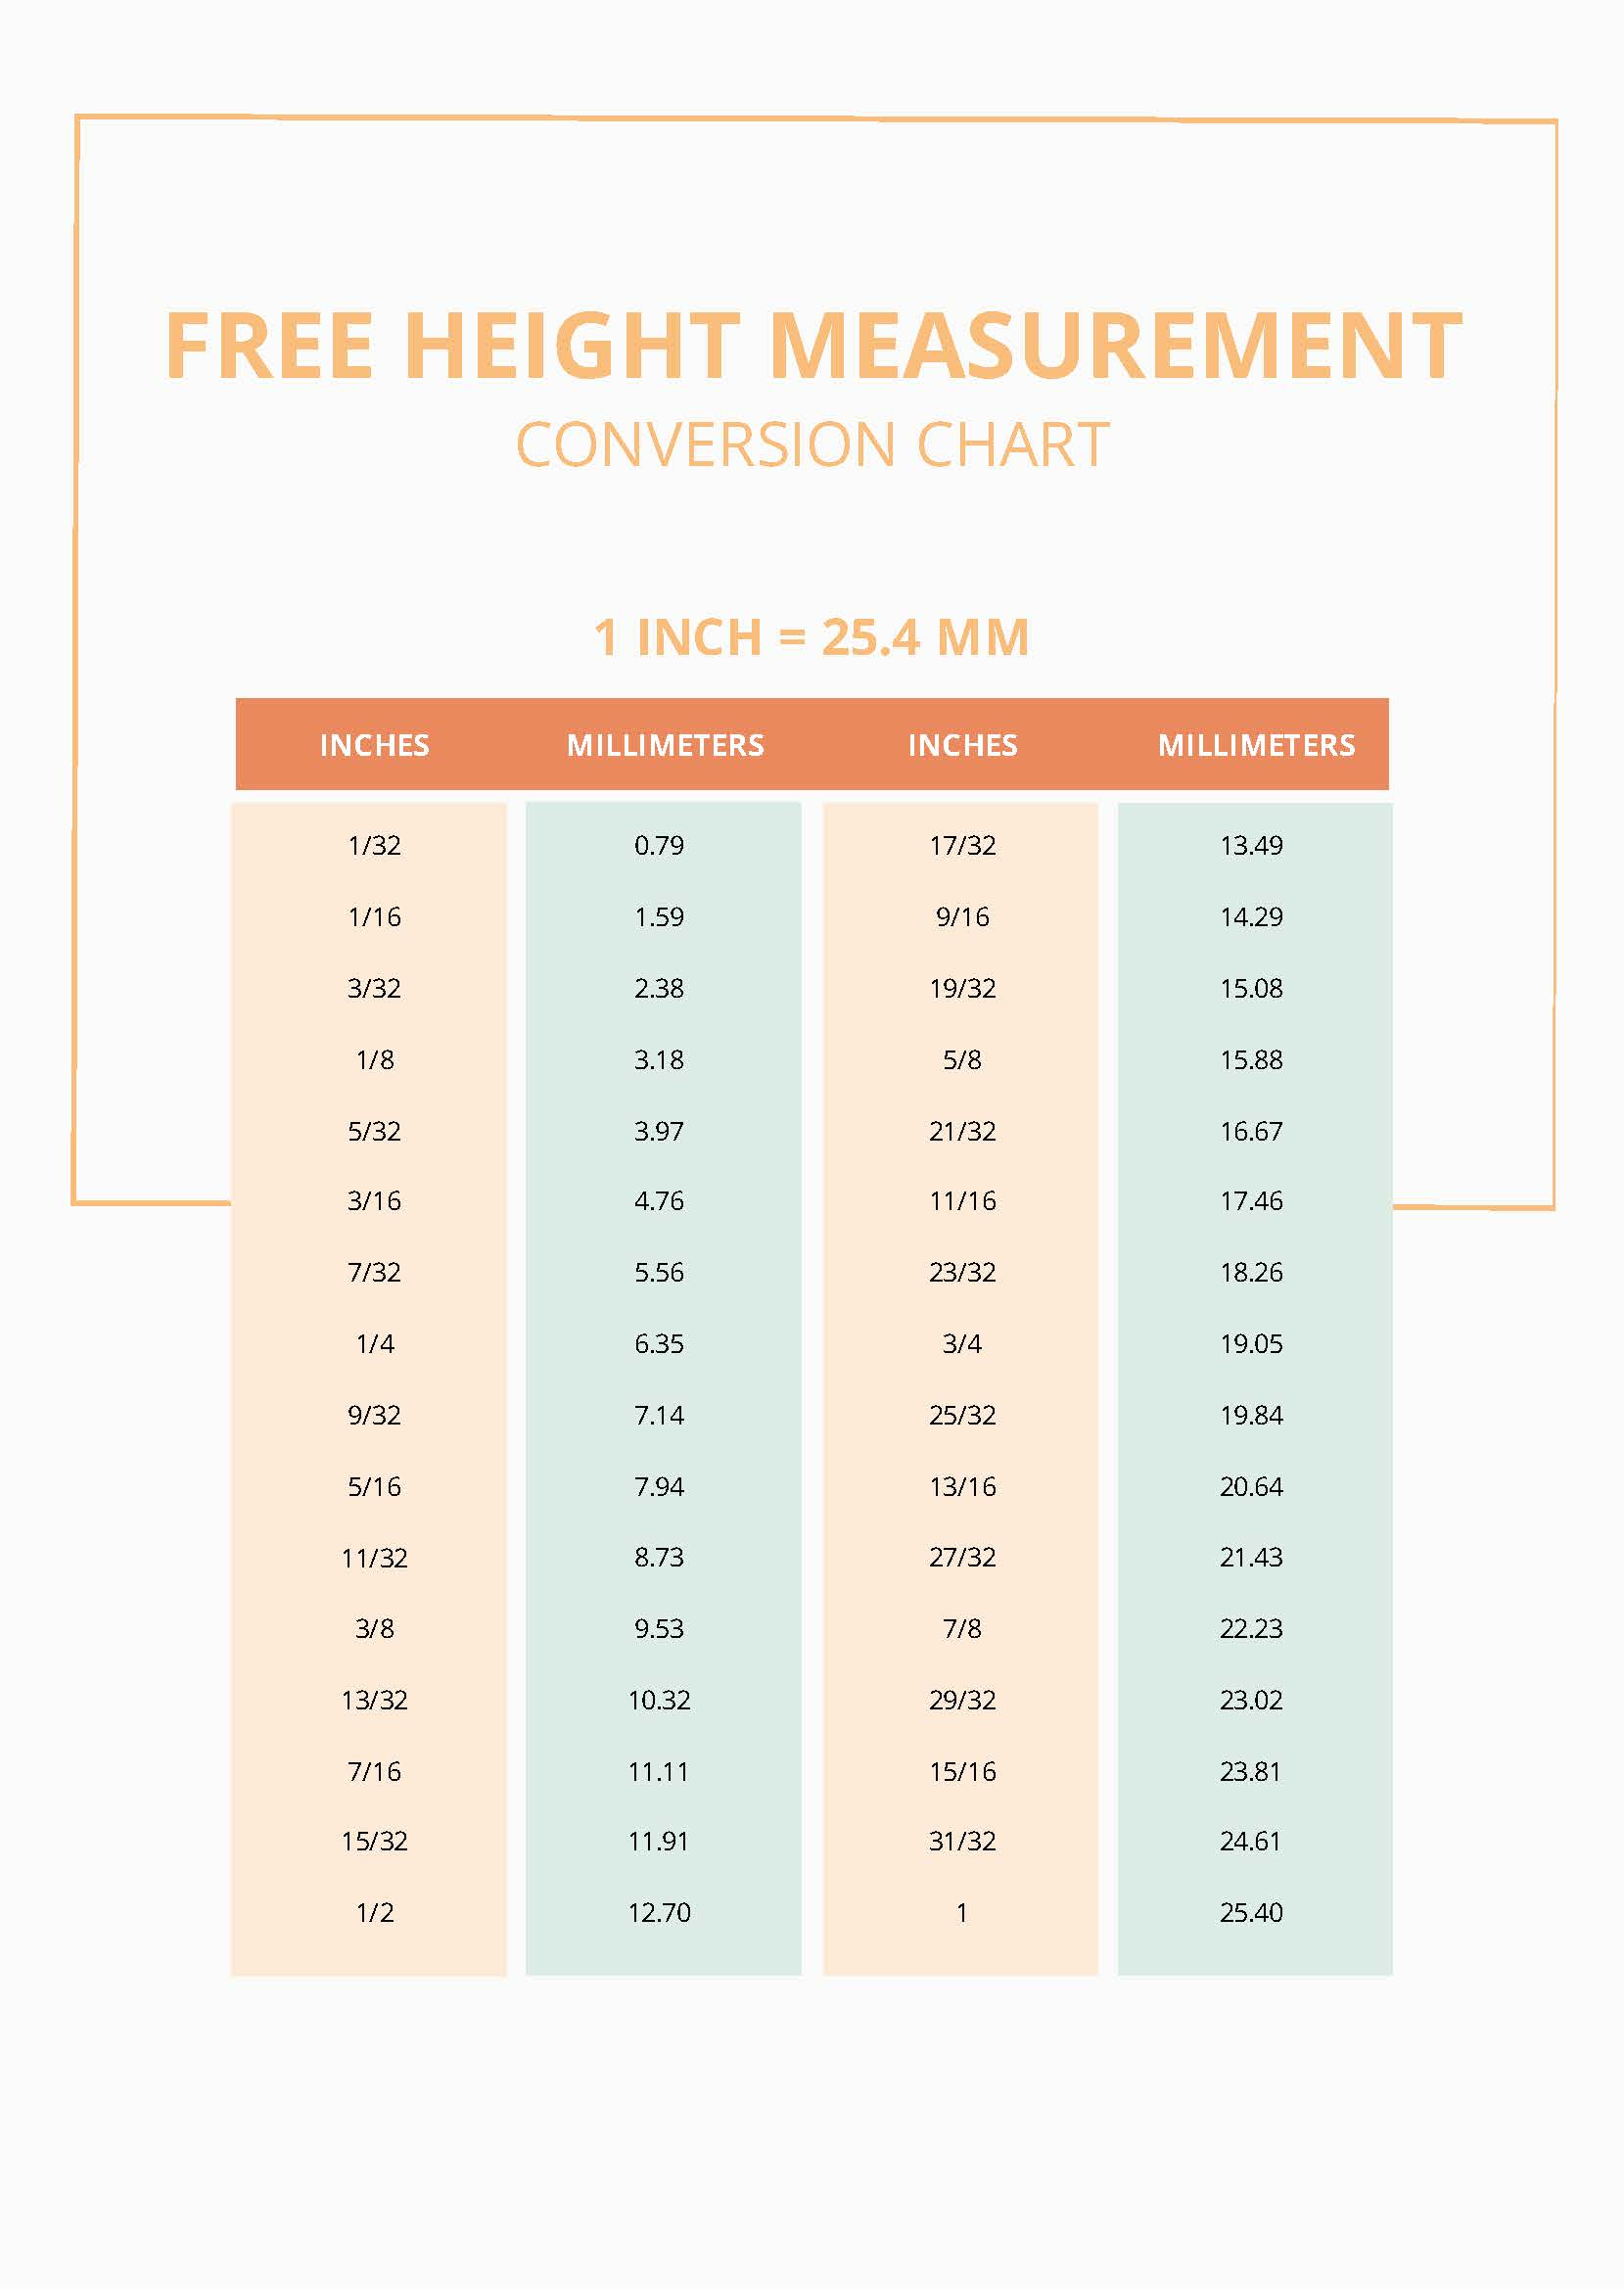
Understanding Height Chart Inches
A Height Chart Inches is simply a growth reference tool that plots a person's height in inches against standardized percentiles by age. It's been around since the 1970s when the CDC first published growth charts based on large-scale surveys. You see them in pediatric offices, sports clinics, and even some gym contexts. The basic idea is straightforward: you measure someone, find where they fall on the curve for their age and sex, and use that to track trends over time. But the devil is always in the details. Start by measuring accurately. A wall-mounted stadiometer is the standard tool. Have the person stand barefoot, heels together, back against the wall, looking straight ahead. Lower the headboard until it contacts the top of the head. Record the measurement to the nearest 1/8 inch or better. Then grab the right chart — WHO charts for children under 2, CDC charts from 2 to 20, and adult height references for people over 20. Find the person's exact age in months for young children. Age matters more than you'd think. A kid who is 5 years and 11 months is essentially different from one who is 5 years and 0 months on these charts. The percentile lines on the chart show the distribution. The 50th percentile is the median. That's what most people call "average," though average can mean different things statistically. The 3rd and 97th percentiles are generally considered the clinical boundaries. Falling below the 3rd percentile or above the 97th usually triggers further evaluation, but it doesn't automatically mean something is wrong. I've seen perfectly healthy kids sit at the 2nd percentile because both parents are short. The percentile tracks where they are relative to the reference population, not whether they're healthy.
One thing most people miss is that these charts are cross-sectional, not longitudinal. They show where most kids stand at each age on a single day, not how individual kids grow over time. Two kids can both be at the 50th percentile today but grow at completely different rates. That's why tracking your own child or patient along a single percentile line over years is more useful than obsessing over where they sit at any given moment.
Common Mistakes and What Actually Happens
I once had a case that stuck with me for a while. A family brought in their 8-year-old boy who was measuring around 4 feet 6 inches. On the chart he was hovering near the 15th percentile, which looked fine on the surface. But when I pulled up his previous measurements from the past three years, I noticed something odd. He'd been tracking steadily along the 40th percentile since age 4, and somewhere around age 6 he'd dropped two full percentile lines. Not dramatically, just enough to slip from 40th down to around 15th. The parents had never noticed because he still looked like a normal-sized kid compared to his friends. His bone age X-ray came back delayed by about 18 months, and the endocrinologist ended up running a full workup. Turns out it was a manageable growth hormone issue caught early. If they'd only looked at one data point, we might have dismissed it. That experience reinforced something I try to remember constantly: a single measurement is almost useless. The trend is everything. Plotting at least three measurements spanning a year or more gives you a real picture. Anything less is just a snapshot that could be noise. Another practical problem: measuring infants and toddlers in inches is annoying. You can't stand them up. You need a recumbent length board, and even then, getting an accurate reading is harder than it looks. A 2-inch error on a 30-inch toddler is a 6.7% mistake. On a 60-inch 10-year-old, it's only 3.3%. So the younger the child, the more precision matters, and the harder it is to get. I usually take two measurements and average them. If they don't agree within a quarter inch, I take a third.
Get the Full Details
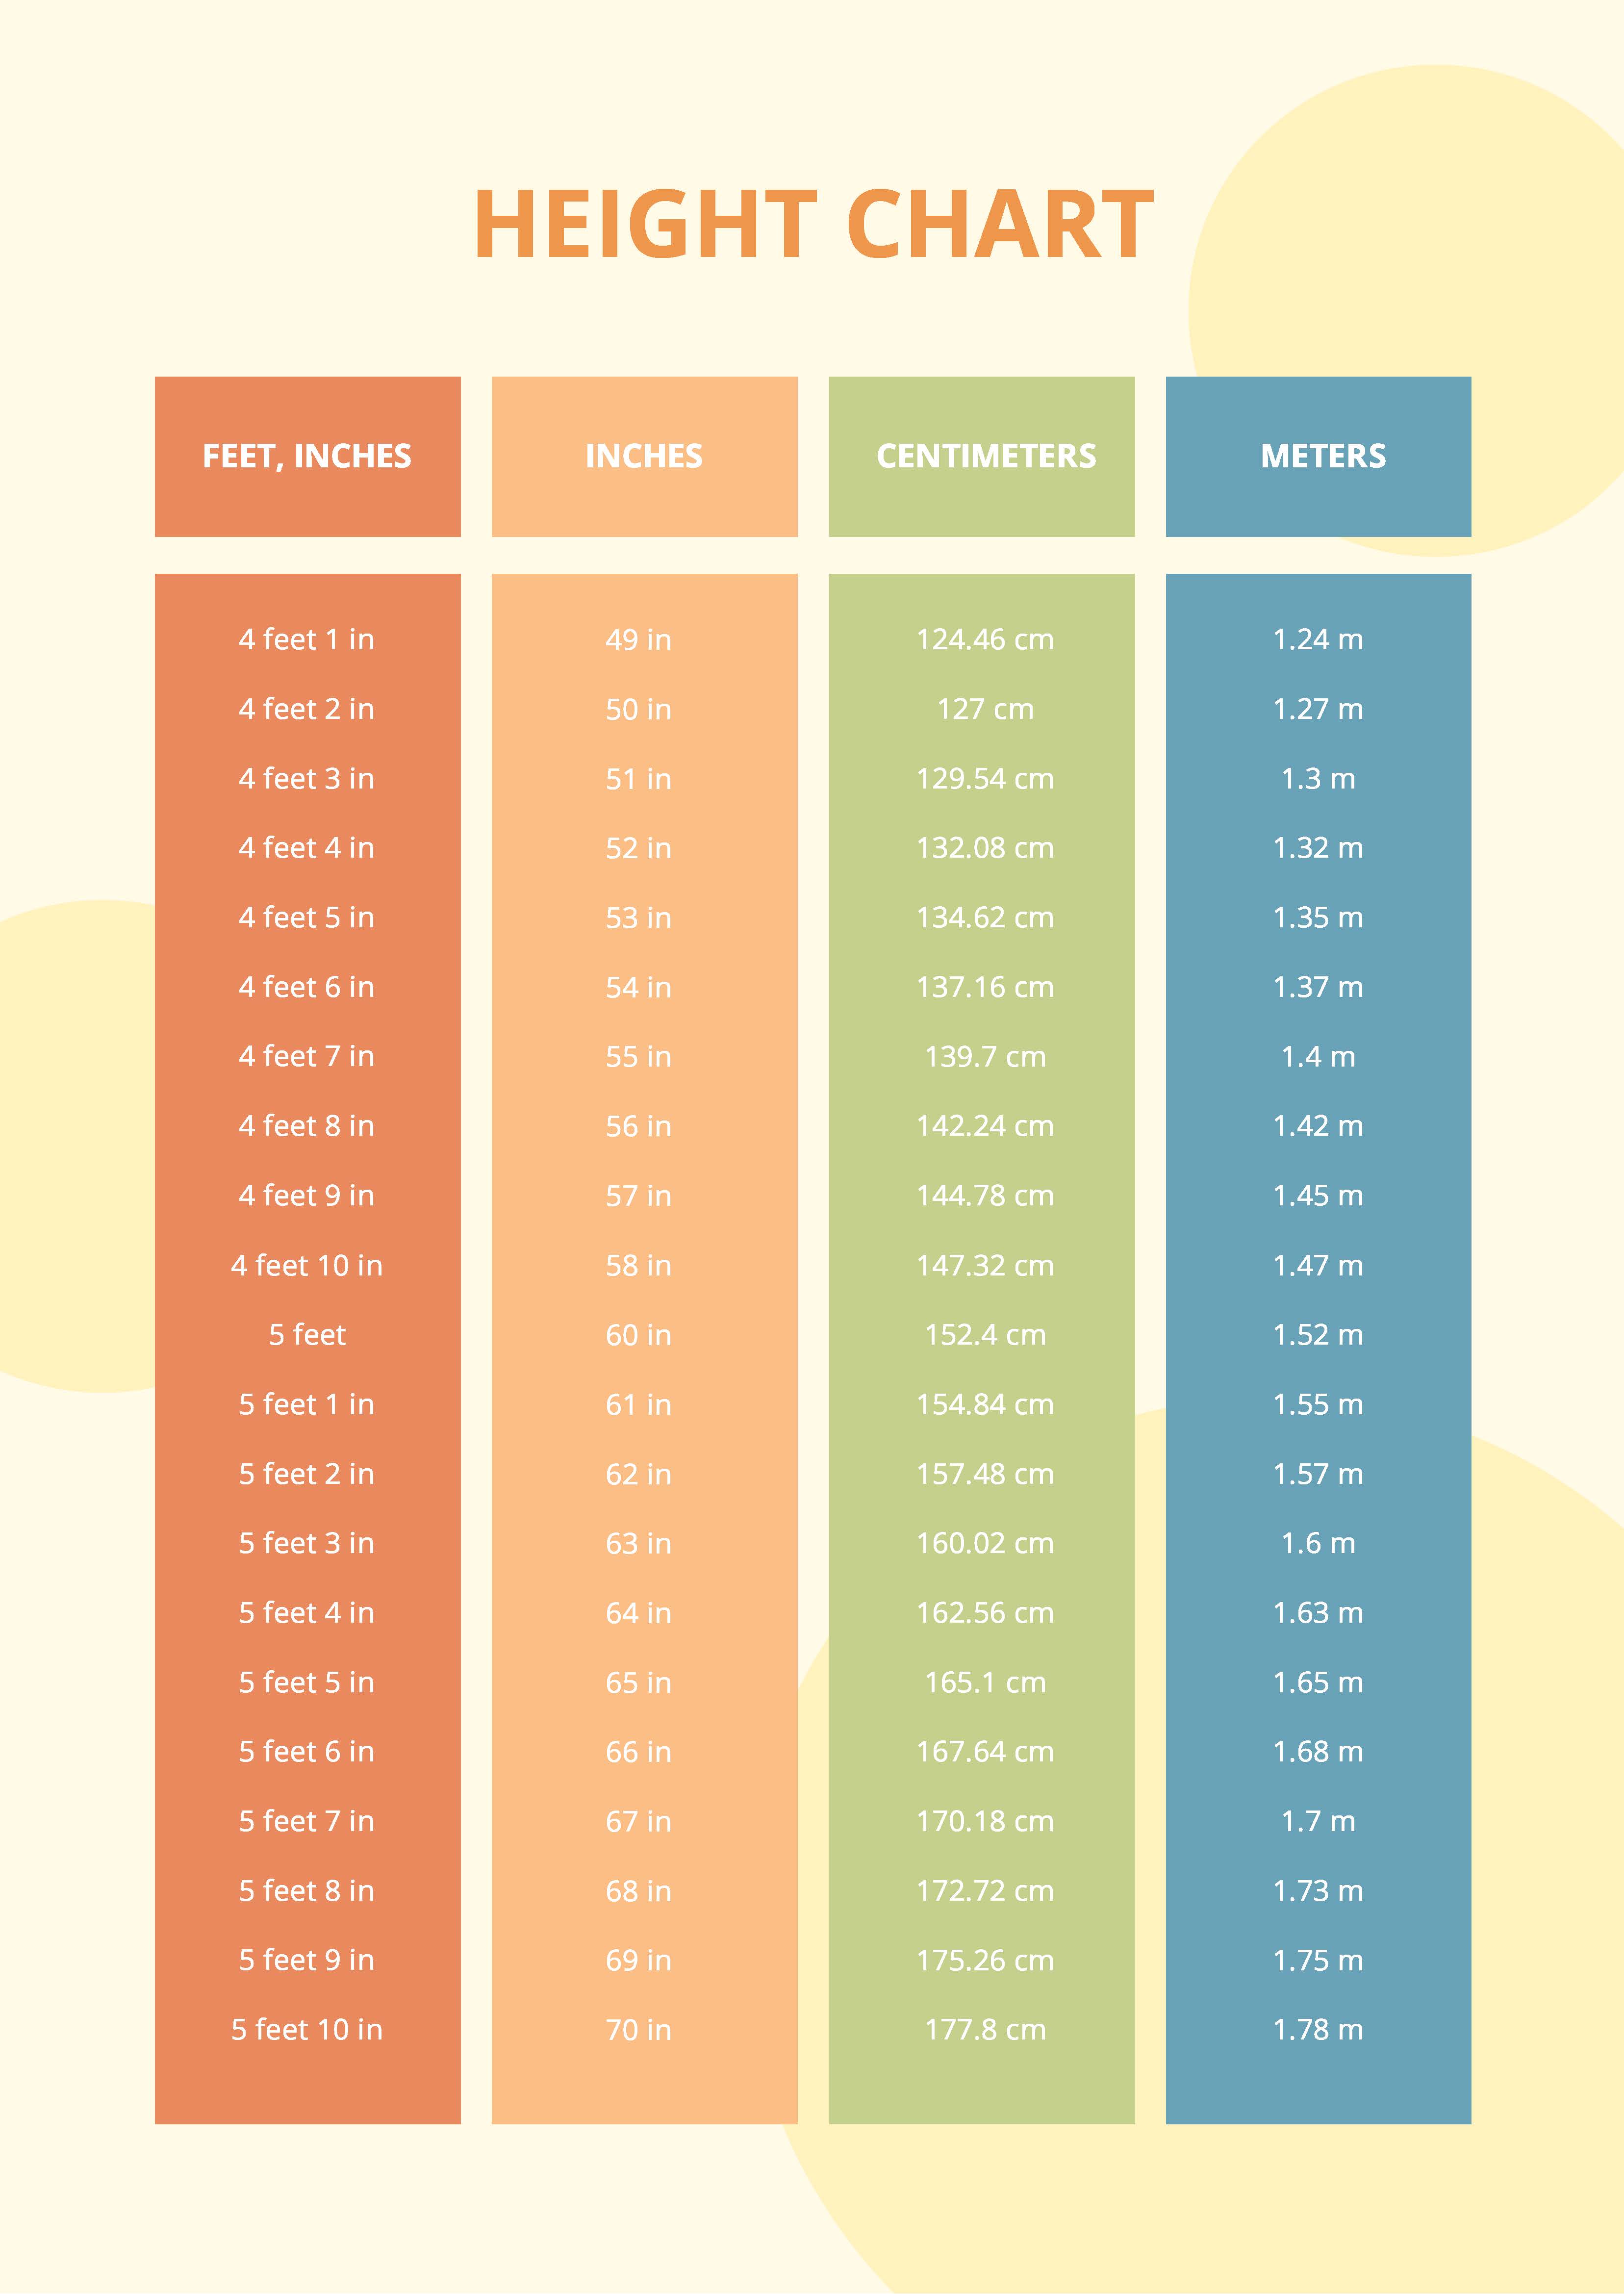
There's also the issue of shoe insoles and posture. I've seen people add half an inch because they stood with their shoulders rolled back and spine artificially straightened. Others slouched. The difference between good posture and relaxed posture on a growth chart can shift a percentile by one or two lines. That's not clinically significant on its own, but combined with measurement error it can create a false trend. Standardize the conditions and stick to them.
Where These Charts Fall Short
Height Chart Inches charts are based on reference populations that don't represent everyone. The CDC growth charts were built mostly from white, middle-class American children sampled before nutritional interventions became widespread. The WHO charts are better for global representation but still have gaps. Kids from certain ethnic backgrounds, adopted children from different geographic regions, and kids with chronic conditions may not fit neatly into these curves. A child who consistently plots at the 10th percentile might be perfectly healthy for their genetic background but flagged for concern because the reference doesn't account for it. Puberty timing is another blind spot. These charts don't distinguish between a kid who hit puberty early and one who hit it late. A girl who starts puberty at 10 and a girl who starts at 13 will diverge significantly on the chart during early adolescence, and both can be completely normal. The chart shows height but not maturity, which is why bone age assessments exist alongside them. For adults over 25, these charts stop being useful. Height naturally decreases with age due to spinal compression and disc degeneration. An adult who was 5'10" at 25 might measure 5'8.5" at 70. That's not a growth problem. It's just aging. Some commercial apps claim to track adult height on percentile charts, but that's misleading because the reference data isn't designed for adult aging patterns.
Practical Tips That Actually Matter
If you're tracking a child's growth at home, do it at the same time of day. People are about half an inch taller in the morning than in the evening due to spinal disc hydration. Measuring at different times of day will make the data look jittery even when growth is perfectly steady. Use the same tool if possible, or calibrate between tools. A tape measure on a wall and a proper stadiometer can differ by a quarter to half an inch. Document everything. Date, time, tool used, who took the measurement. When you're looking back at data from six months ago, you'll forget whether you measured before or after school, whether the kid wore socks, whether the wall surface was carpet or hardwood. Those details matter when you're trying to interpret a small change. Don't fixate on percentiles. What matters is velocity — how many inches per year a child is growing. A healthy school-age child grows about 2 to 2.5 inches per year. If a kid who was growing 3 inches a year suddenly drops to 1.5 inches a year, that's a signal worth investigating regardless of which percentile they sit at. Velocity changes are more informative than absolute position on the chart.
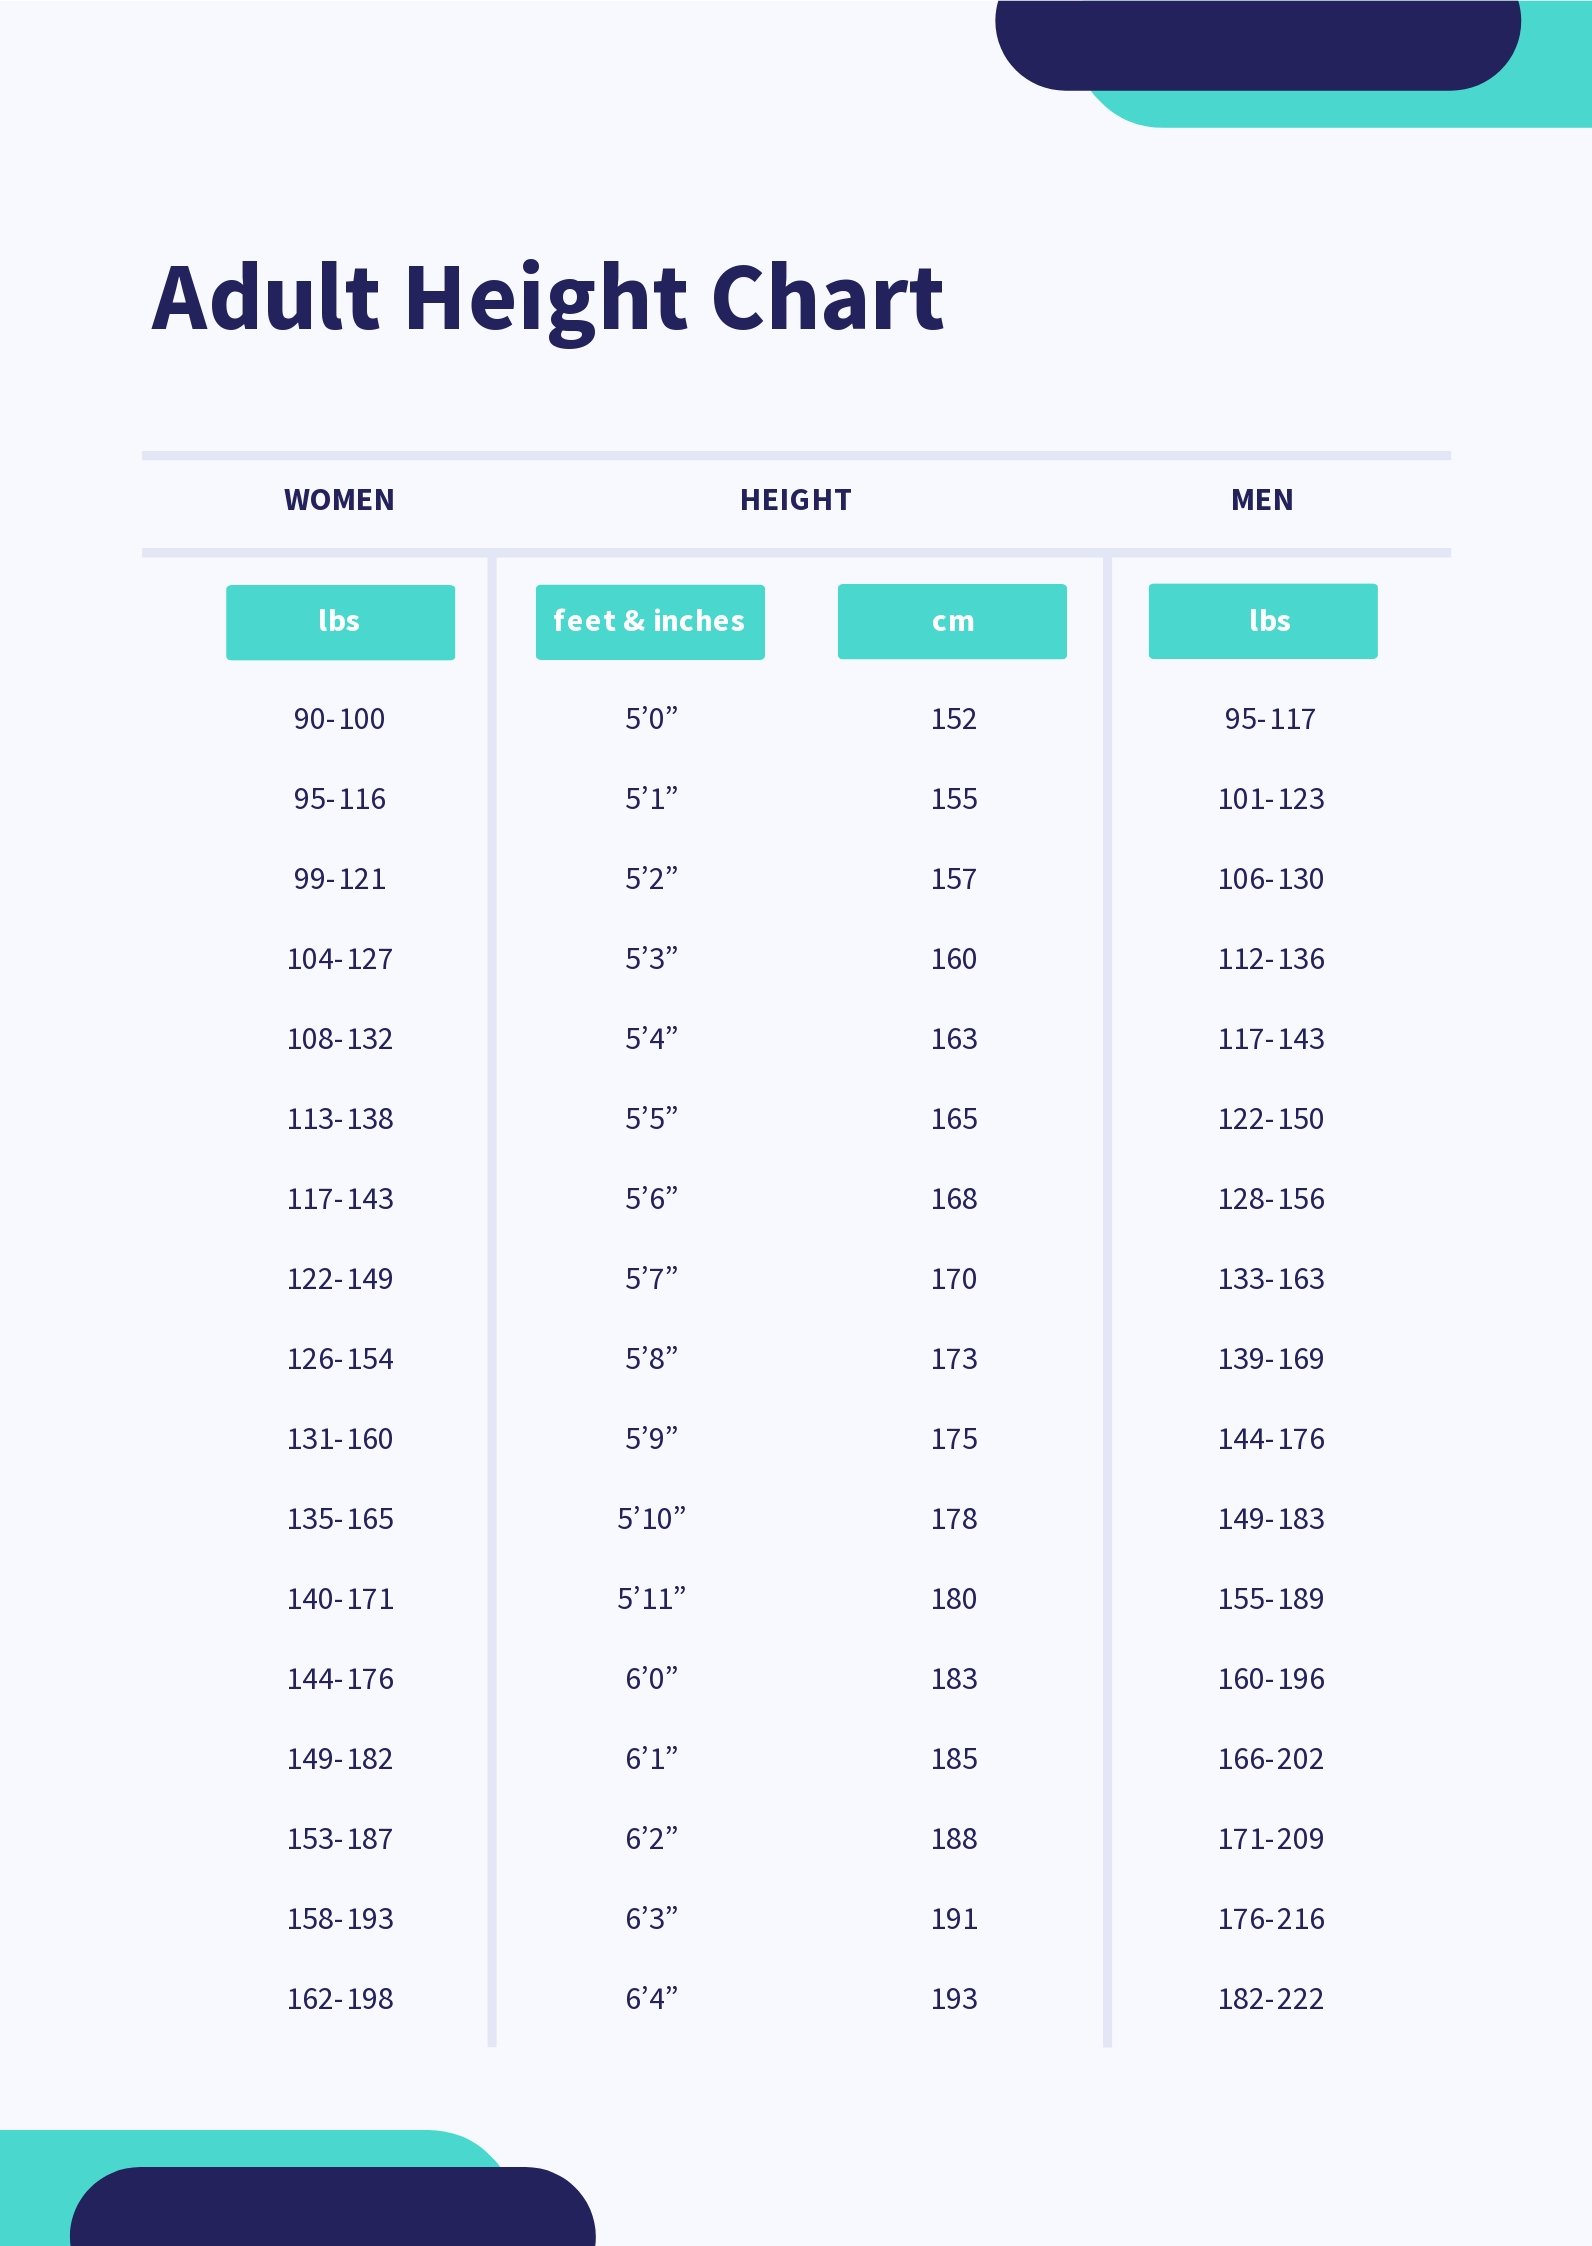
For downloadable resources, the CDC and WHO both offer free printable growth charts on their websites. The CDC page has separate charts for boys and girls from 0 to 20 years. The WHO has similar charts for 0 to 5 years with international standards. Avoid third-party apps that claim to replace these — many don't use the official percentiles or update them properly. I've seen a few that calculated percentiles incorrectly by using the wrong reference population for the child's sex. The bottom line is that a Height Chart Inches is a screening tool, not a diagnosis. It flags patterns that might need attention. Most kids who dip below the 3rd percentile or cross multiple percentile lines are fine. But catching the ones who aren't requires paying attention to the full picture — multiple measurements, posture consistency, family height patterns, and overall health. Anything less is just guessing with extra steps.