
Writing nursing diagnoses is one of those skills that seems simple until your instructor marks it down three times and you have no idea why.
I learned this the hard way during my second semester of nursing school. I wrote what I thought was a perfectly reasonable nursing diagnosis on paper, submitted it, and got it back covered in red ink. The problem wasn't that my assessment was wrong. It was that I'd written a medical diagnosis disguised as a nursing diagnosis. "Impaired gas exchange related to COPD" — you learn pretty quickly that COPD is the physician's diagnosis, not the related factor you're supposed to cite. The related factor needs to be something you can actually intervene on as a nurse. This is the core issue behind Help Writing Nursing Diagnosis requests I see constantly on forums and study groups. Students understand the pathophysiology. They can assess a patient. They struggle with the format and the language of nursing diagnoses specifically.
Help Writing Nursing Diagnosis: Understanding the PES Structure
A proper nursing diagnosis follows the PES format — Problem, Etiology, and Signs/Symptoms. The problem is the NANDA-I approved label. The etiology is the "related to" factor, which must be a nursing-sensitive issue. The signs and symptoms are the "as evidenced by" data that supports your diagnosis. Here is what a correct formulation actually looks like in practice. "Impaired gas exchange related to altered oxygen-carbon dioxide diffusion as evidenced by SpO2 of 88% on room air, tachypnea at 26 breaths per minute, and client report of shortness of breath." Every single piece in that statement is defensible. The etiology is something you address through positioning, oxygen therapy, and monitoring. The evidence includes objective and subjective data. That is the standard your faculty is looking for. The mistake most students make is skipping the evidence portion entirely or making it vague. "As evidenced by difficulty breathing" is not acceptable. You need specific assessment findings — vital signs, lab values, behavioral indicators. This is what separates a diagnosis that passes review from one that gets sent back.
Common NANDA-I Labels That Cause Problems
Some nursing diagnoses are more troublesome than others, and this tends to trip people up repeatedly. Risk diagnoses are a particular pain point. A risk diagnosis does not include signs and symptoms because the problem has not yet occurred. So "Risk for Falls related to gait instability and history of falls" is structured differently than an actual diagnosis. You will lose points if you try to add evidentiary data to a risk diagnosis the same way you would for an actual problem. Another category that causes confusion involves syndrome diagnoses. NANDA-I includes things like "Trauma" as a syndrome diagnosis, which combines multiple related problems into one. Students often do not know when to use a syndrome diagnosis versus individual component diagnoses. The general rule is straightforward enough but easy to mess up under time pressure. If a cluster of issues presents together consistently and has a recognized NANDA-I label, use the syndrome. Otherwise, write individual diagnoses. I recall a clinical rotation where I was caring for a post-operative abdominal surgery patient. The obvious choice was Acute Pain. But writing just "Acute Pain related to surgical incision as evidenced by facial grimacing, guarding behavior, and pain rating of 7 out of 10" was incomplete for this patient. She also had impaired mobility due to pain and fear of movement, along with potential risk for infection from the surgical site. The instructor wanted to see whether I could prioritize and connect multiple diagnoses. I missed that on my first attempt and wrote only one diagnosis. She pointed out that nursing care is rarely about a single problem per patient, and that I was treating the symptoms while ignoring the cascade of related issues.
Get the Full Details

Prioritization Is Where Most Students Struggle
You cannot always list every possible nursing diagnosis for a patient. You need to prioritize. The standard approach uses Maslow's hierarchy and airway-breathing-circulation frameworks, but the application is not always clean. A patient with pneumonia has an actual Impaired Gas Exchange diagnosis that takes priority over Risk for Infection. But a post-surgical patient who is immunocompromised might flip that order. These edge cases are what make nursing diagnosis writing harder than simply matching symptoms to NANDA-I labels from a textbook. Another practical problem is documentation overlap. When you write a diagnosis for one patient, similar wording keeps appearing across different cases. Instructors can tell when you are copy-pasting generic diagnoses without customizing them to the specific patient data. "Imbalanced nutrition less than body requirements related to inadequate intake as evidenced by weight loss" is fine as a template, but if three patients in your assignment all have that exact wording with no individualized supporting data, you are going to get flagged. The workaround I eventually adopted was keeping a personal reference sheet organized by body system. For each major system, I listed the top five NANDA-I diagnoses, common related factors that were appropriate for nursing intervention, and the types of evidence that typically supported each one. This took about twenty minutes to compile but saved me significant time during care plan assignments. It also forced me to actually read through the NANDA-I definitions instead of guessing at labels.
Tools and Resources That Actually Help
There are websites and study guides that advertise Help Writing Nursing Diagnosis assistance, and some of them are genuinely useful while others will get you in trouble. The safest approach is to use official NANDA-I resources and your course textbook as primary references. Some platforms offer diagnosis constructors that guide you through building PES statements, which can be helpful when you are unsure about structure. The downside is that over-reliance on these tools can prevent you from learning the actual skill, which is what you need for clinical and board exams. Quizlet and similar flashcard platforms have NANDA-I label collections, but they are only as good as the user-generated content. I found several sets with incorrect related factors listed. Always cross-reference with your textbook or a licensed nursing resource before accepting a flashcard as accurate. For students who need direct assistance, university writing centers and nursing labs often have tutoring available. These are typically free and run by faculty or graduate students who understand exactly what your program requires. Private tutoring services exist as well, but the quality varies significantly and the cost adds up quickly. If cost is a factor, look into peer study groups where students work through care plan examples together. This is often more effective than solo study because explaining your reasoning to someone else reveals gaps in your understanding immediately.
What Gets Diagnoses Marked Wrong Most Often
From what I have seen across multiple semesters of grading and reviewing student work, the top reasons nursing diagnoses get rejected are straightforward. Using medical diagnoses as related factors is number one. Writing vague evidence like "patient appears uncomfortable" without specific behavioral or physiological data is number two. Choosing NANDA-I labels that do not match the actual patient presentation is number three. These are all fixable with practice and careful review before submission. The hardest issue to overcome is the habit of thinking in medical terms rather than nursing terms. Medical diagnoses describe disease processes. Nursing diagnoses describe human responses to those processes that nurses can independently address. This distinction matters on exams and it matters in clinical practice. When you are writing a care plan for a diabetic patient, "Uncontrolled Blood Glucose related to ineffective medication regimen" is a nursing diagnosis because medication adherence and education are within the nursing scope. "Type 2 Diabetes Mellitus" is not a nursing diagnosis. It never was. Writing good nursing diagnoses takes repetition. Your first ten attempts will probably contain errors. Your next twenty will be mostly correct with minor issues. By the time you have written about fifty across different patient scenarios, the format starts becoming automatic. The PES structure stops feeling like a constraint and starts feeling like a useful framework for organizing your clinical thinking.
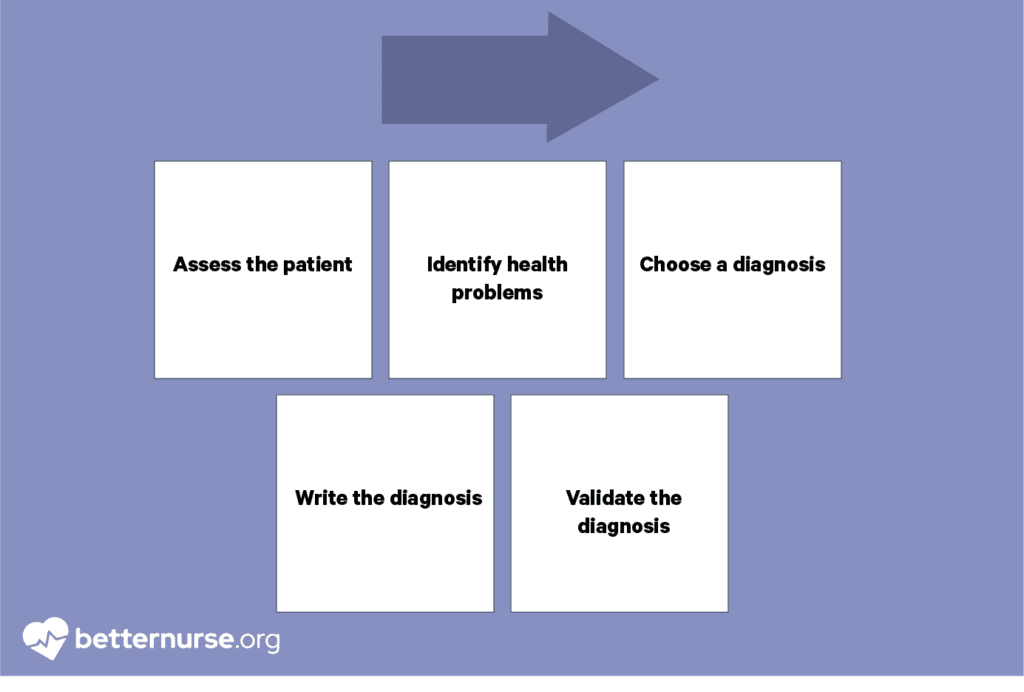
If you are currently stuck on a specific diagnosis and need help working through it, the most effective approach is to break down your patient assessment data into objective findings and subjective findings, match each finding to a NANDA-I label, verify that your related factor is something you can independently intervene on, and then confirm that your evidence is specific and measurable. Running through that checklist before you write your final statement catches the majority of common errors.



