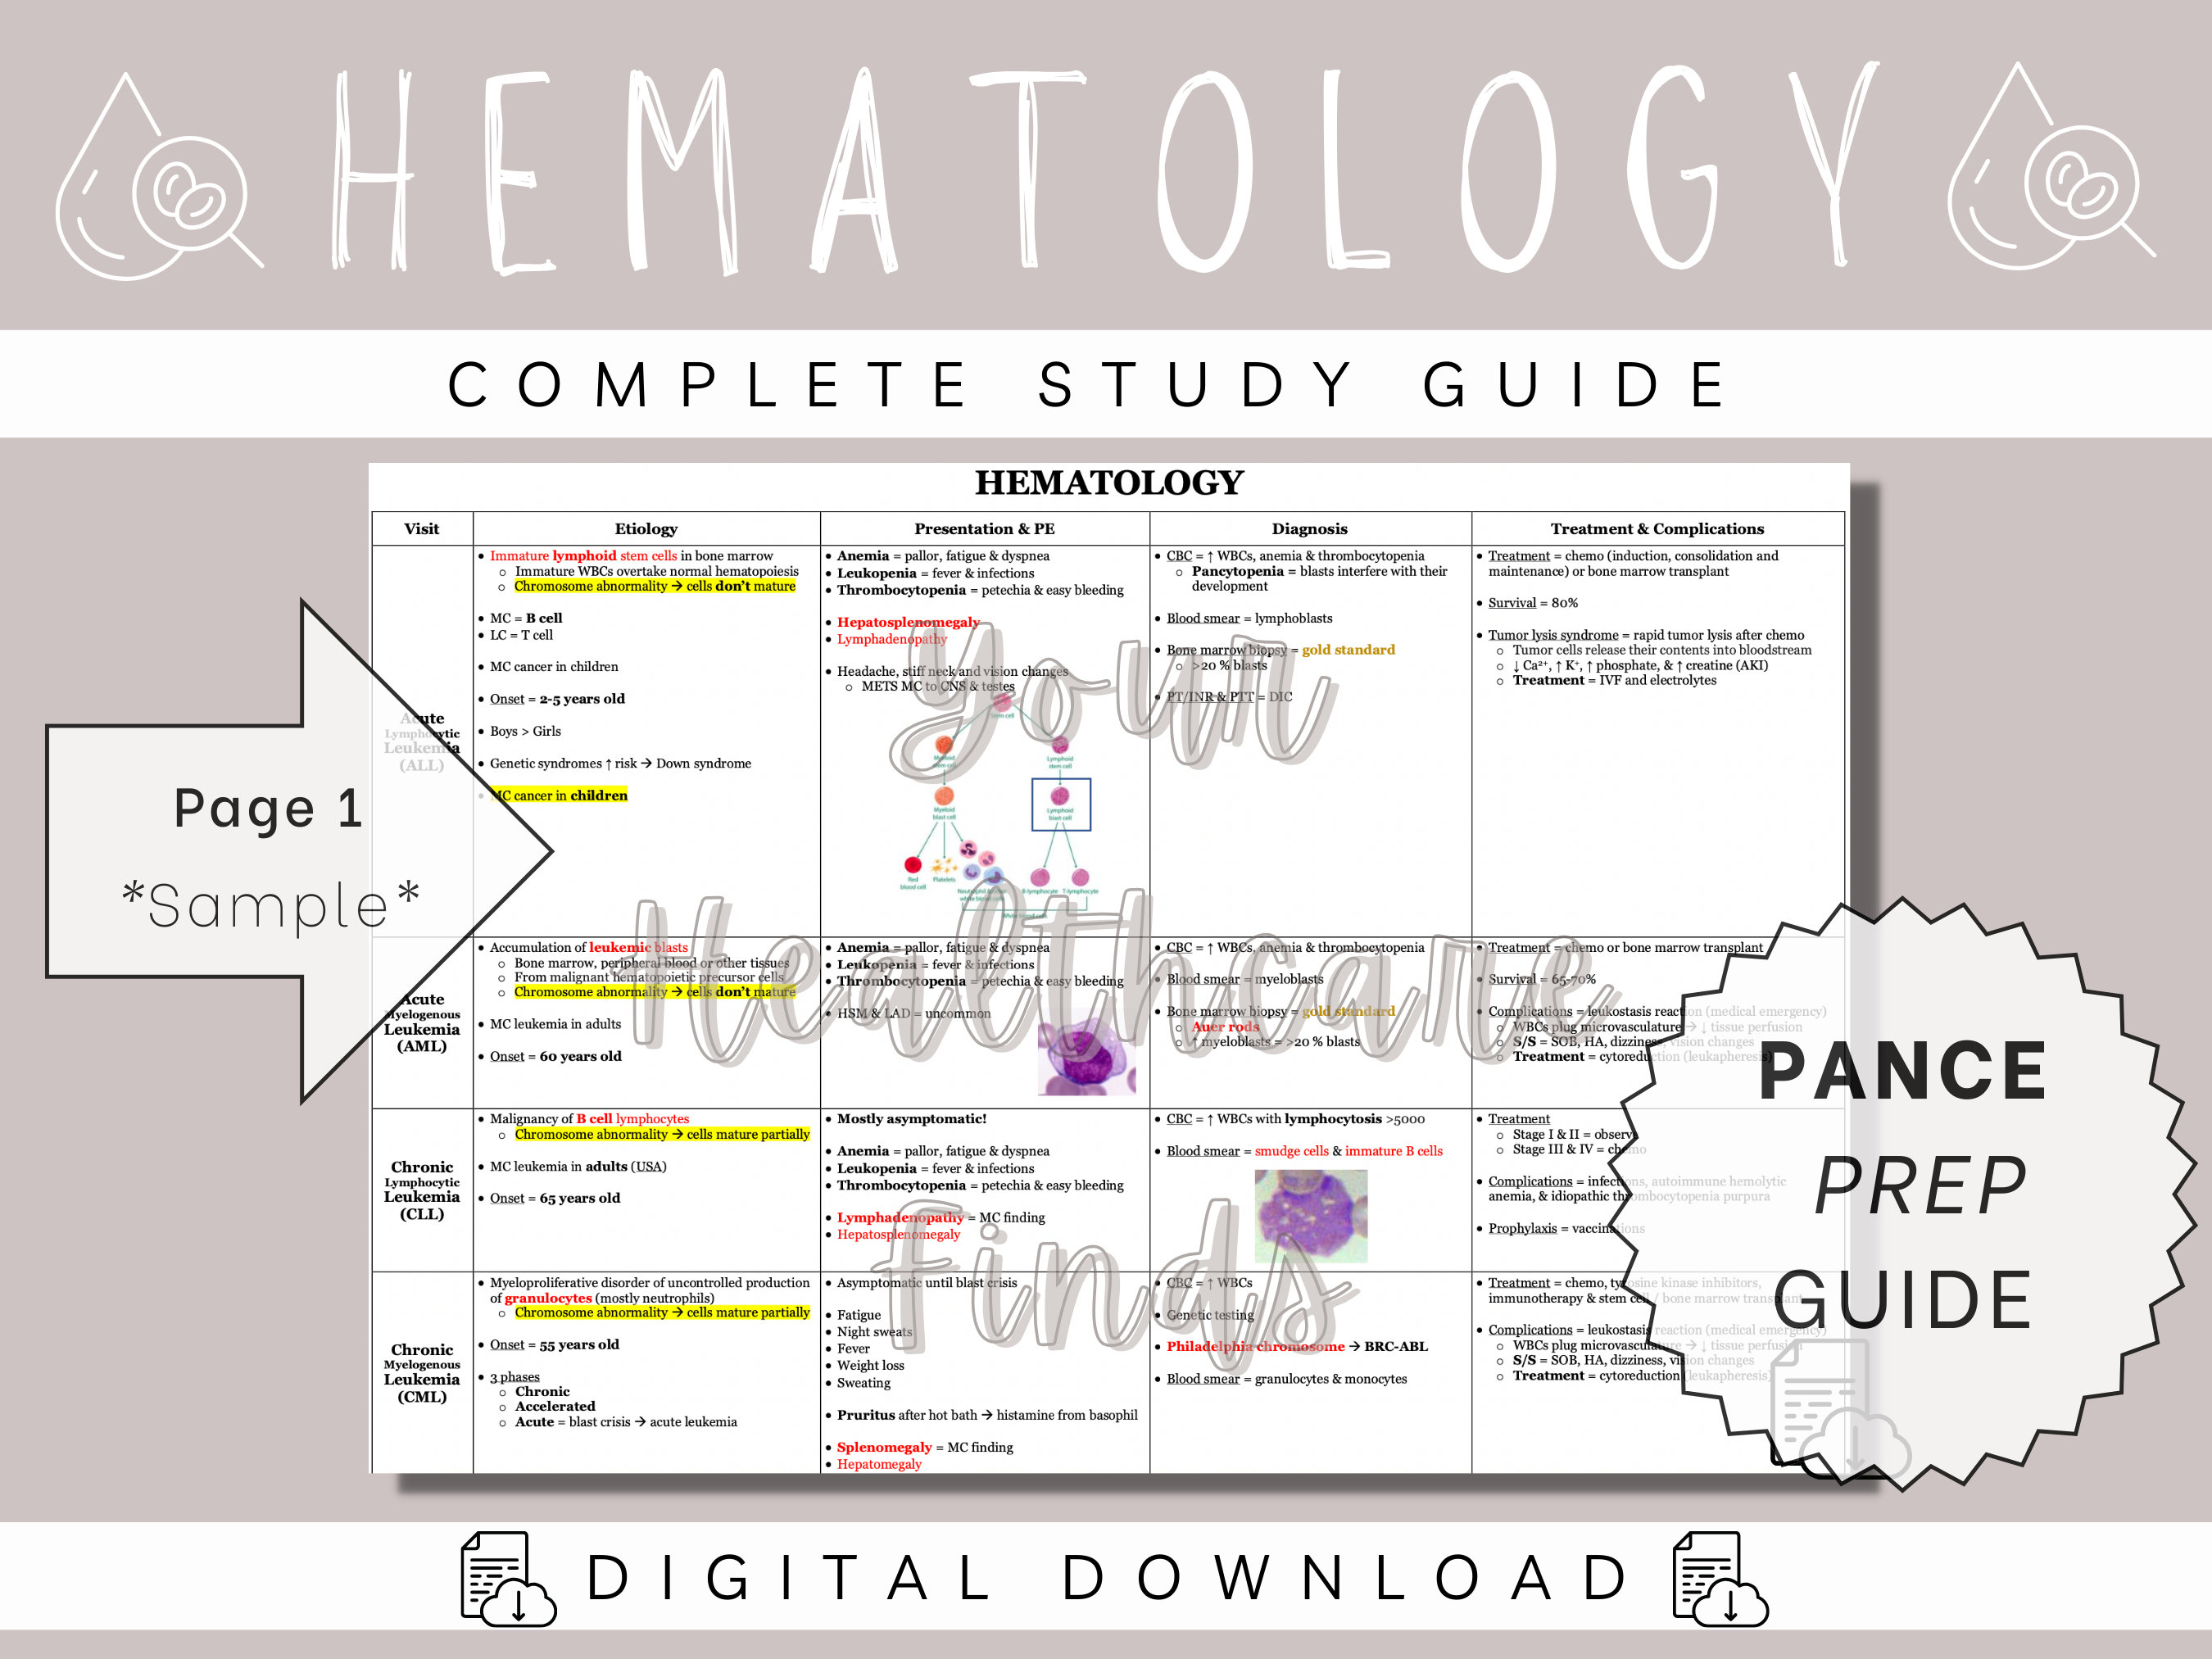
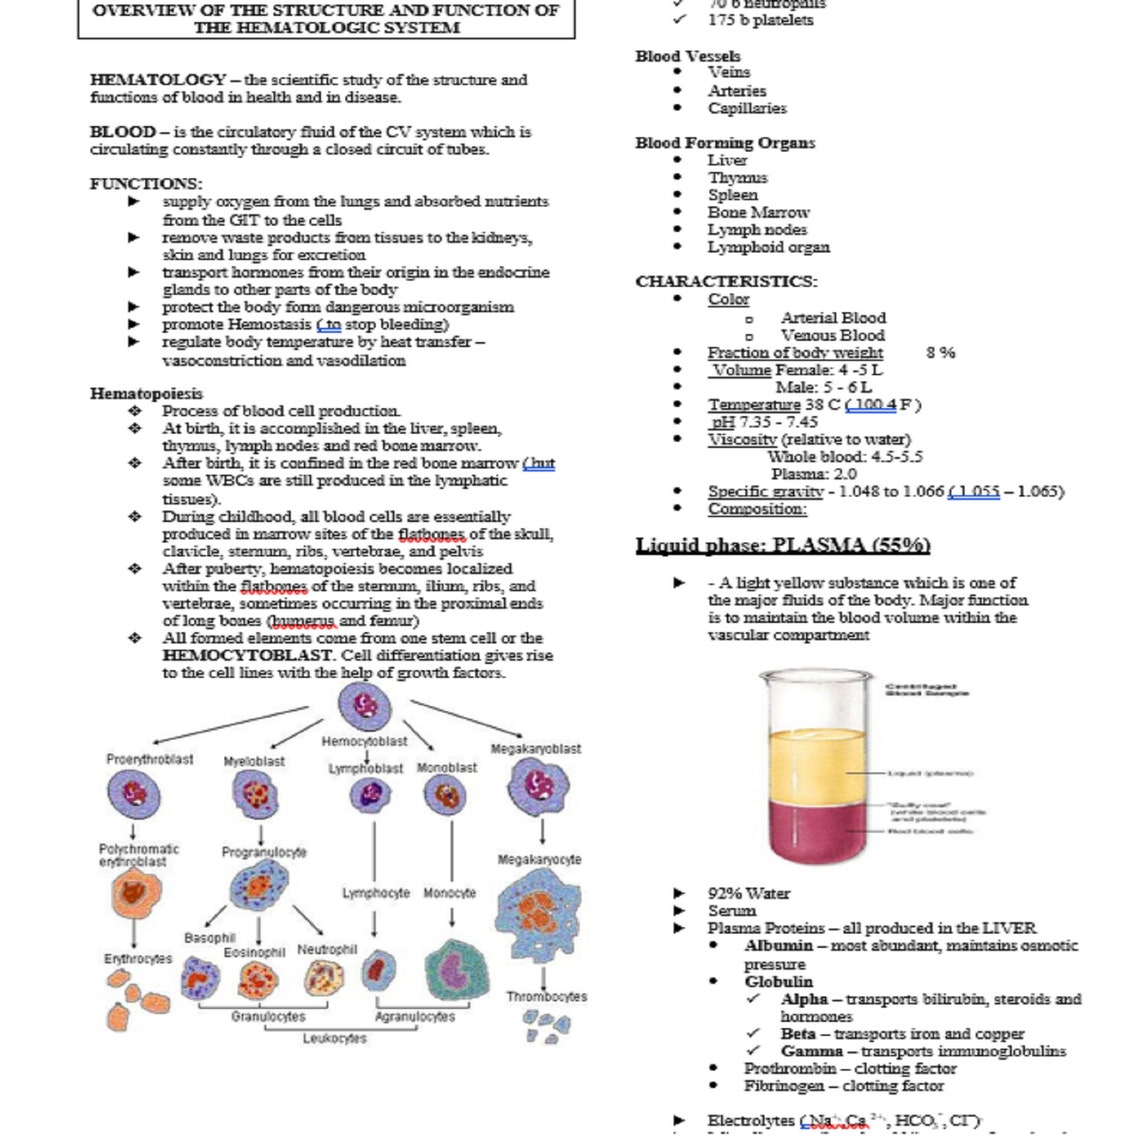
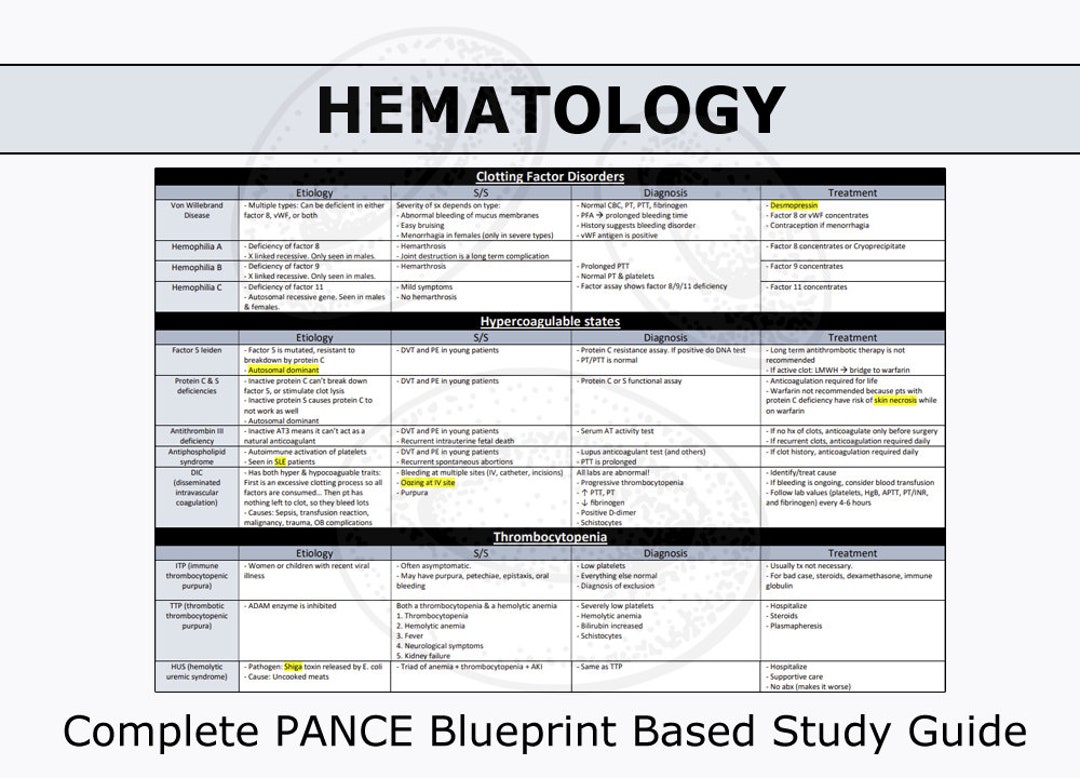
What You Actually Need to Know Before Sitting the Hematology Specialty Exam
The hematology specialty test isn't hard because the material is obscure. It's hard because it forces you to differentiate between conditions that look nearly identical on paper but require completely different management pathways. I spent three years working in a reference lab before I felt comfortable walking into this exam, and even then, I failed the first attempt. The second time around, I used a structured study guide approach instead of re-reading textbooks cover to cover, and that made the difference. Here's the breakdown of what actually matters, based on my experience preparing for and taking these specialty assessments.
Hematology Study Guide For Specialty Test: Where Most People Go Wrong
The biggest mistake I see candidates make is treating hematology like a memorization subject. It isn't. It's a pattern-recognition discipline. You need to be able to look at a peripheral blood smear description or an automated differential result and immediately start ruling conditions in or out based on morphological clues, not recall facts in isolation. A study guide for the hematology specialty test should organize content around clinical scenarios, not chapters on isolated cell lines. Look for resources that present a case — say, a patient with pancytopenia and macrocytic anemia — and walk through the differential diagnosis process step by step. That's how the exam tests you, and that's how you should prepare. I can't recommend a single specific download link here because legitimate resources vary depending on which credentialing body you're pursuing — ASCP, ABMGG, or a hospital-specific competency exam. What I can tell you is what to look for and what to avoid when you're shopping around for study materials.
The Core Content Areas That Actually Get Tested
Peripheral blood cell morphology carries the highest weight. This means you need to be able to identify nucleated red blood cells, schistocytes, hypersegmented neutrophils, and the full range of blast morphologies at a moment's notice. The tricky part isn't recognizing the common findings — it's catching the subtle ones that change the entire diagnostic direction. A single schistocyte on a smear can be the difference between diagnosing TTP versus ITP, and the exam will absolutely include questions where missing that one detail flips the answer. Hemostasis and coagulation is the second major area, and it's where most people lose points. Not because they don't understand the coagulation cascade — everyone knows that from med school — but because they can't interpret mixed results. I remember one practice question where the PT was prolonged, the aPTT was normal, and the platelet count was low. The obvious trap answer was disseminated intravascular coagulation, but the correct reasoning led toward vitamin K deficiency with concurrent heparin contamination. The platelet drop was artifactual. These kinds of questions require you to think about pre-analytical variables, not just pathophysiology. Bone marrow morphology and cytochemistry form the third pillar. You need to know what Auer rods look like, how to distinguish reactive from leukemoid granulopoiesis, and what the iron stain reveals in different anemias. The exam doesn't ask you to diagnose a disease from a marrow biopsy alone — it asks you to integrate smear findings, marrow findings, flow cytometry data, and cytogenetics into a single coherent picture.
Get the Full Details
How to Actually Use a Study Guide Effectively
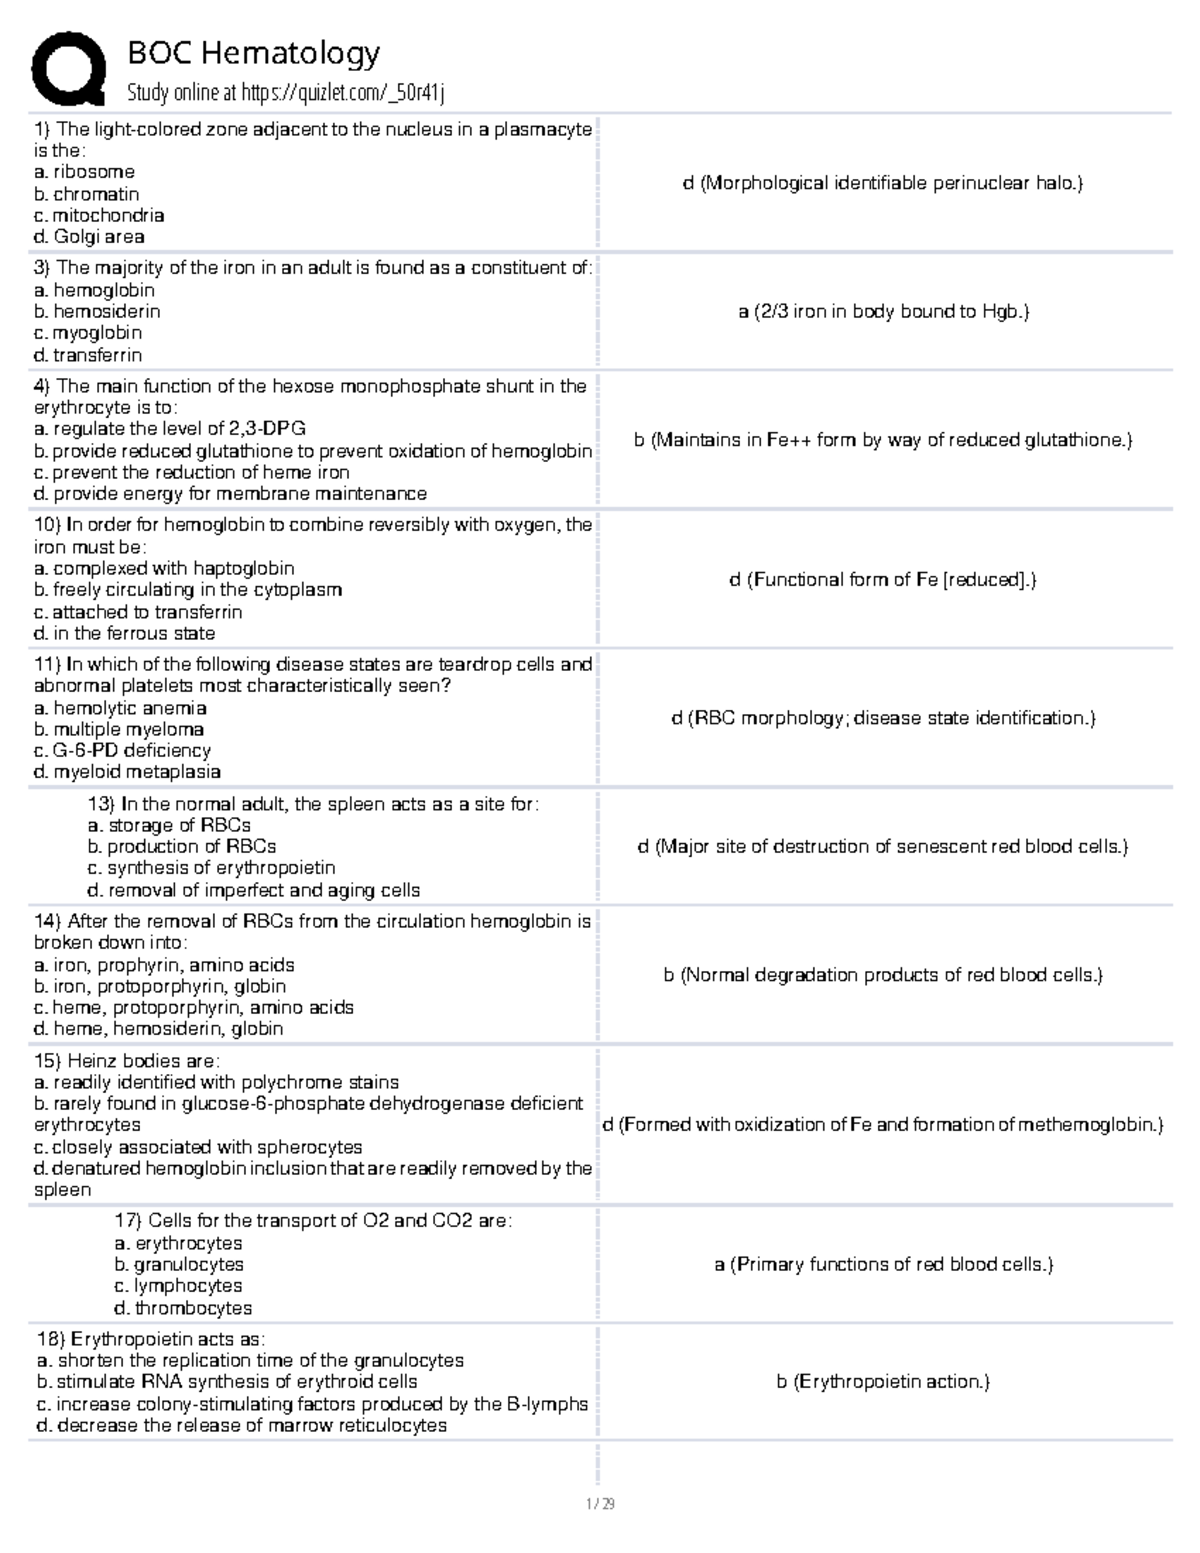
Don't read through it once. That's the most common waste of time I see. A study guide for hematology specialty exam prep works like this: read a section, then immediately do the practice questions attached to that section without looking at the answers first. When you get something wrong, don't just note the right answer — write down why your reasoning was wrong. Was it a knowledge gap? A misread of the question? An assumption you made that wasn't supported by the data? I used a method where I'd take a stack of index cards, write the question on one side and my initial answer on the other, then flip it over to check. If I got it wrong, I'd write the correct reasoning in my own words below the question. This forced me to reconstruct the logic rather than just recognize the right answer when I saw it. It took longer upfront but cut my review time in half going into the exam week. Focus heavily on questions that combine multiple organ systems or diagnostic modalities. The real specialty test doesn't give you a clean, textbook case. It gives you a messy clinical picture with conflicting data points, and it wants to see if you can prioritize. I spent about 60 percent of my study time on integrated case questions and only 40 percent on content review. That ratio held up well on test day.
Edge Cases and the Stuff Books Don't Cover
There's a phenomenon called platelet clumping that shows up on automated counters and creates a falsely low platelet reading. On the exam, they might give you a case where the platelet count is 25,000 but the smear shows normal platelet numbers with visible clumps. The correct answer is almost never "transfuse platelets" — it's "recollect in a citrate tube and repeat." I encountered this exact scenario in a practice test and initially went with the transfusion pathway because my brain fixated on the number. After that mistake, I started scanning every platelet value for the word "clumped" or "decoyed" before committing to any management answer. Another area that catches people off guard is cold agglutinin disease. The smear will show RBC agglutination, the MCV will be artificially elevated, and the RDW will be wide. If you don't warm the sample before running it on the counter, your indices are garbage. Questions involving spurious results from sample handling issues appear regularly, and they're designed to filter out people who only studied the pathology and ignored the pre-analytical phase.
Limitations of This Approach
A study guide alone won't get you through this exam if you have zero clinical lab experience. The questions assume you've handled actual specimens, seen actual smears, and dealt with actual instrument flagging. If you're coming from a purely academic background, you need to supplement your study guide with as much practical exposure as possible — even watching recorded smear reviews or virtual microscopy sessions helps build the pattern recognition that the exam demands. Additionally, no single study guide covers every credentialing body's exact blueprint. The ASCP board exam emphasizes different weightings than the AABB hematology section or institutional competency assessments. Check the official exam content outline for your specific test before you buy anything. Some guides are thorough on morphology but light on quality control and laboratory management, which can be a significant portion of the score depending on which exam you're taking. If you're short on time — say, less than six weeks to prepare — I'd recommend pairing a comprehensive study guide with an question-bank-only cram period for the last two weeks. Reading and answering simultaneously is better than finishing a book and then facing questions cold. The integration is where the learning actually happens.