Why the Hemodialysis Flow Sheet Template Exists
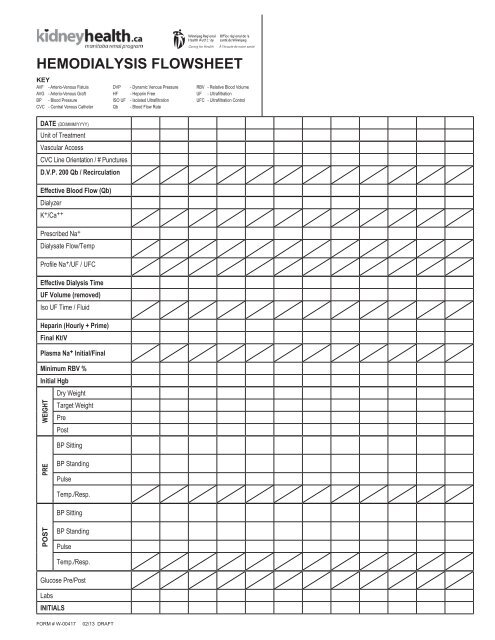
Most dialysis units still track patient sessions on paper or scattered spreadsheets. A Hemodialysis Flow Sheet Template is a structured form that consolidates pre-treatment vitals, intra-treatment parameters, and post-treatment summary into one continuous record per session. It's not fancy. It exists because regulators and clinical leads want a single document you can pull during a chart audit without chasing three different nursing notes. A standard template has three sections. Pre-treatment block: patient ID, date, session number, weight before treatment, blood pressure, pulse, temperature, access type, access flow (if available), ultrafiltration goal, prescribed Kt/V or Booker equation inputs, anticoagulant plan, and baseline labs if they're relevant to the session.
Intra-treatment block: time-stamped entries every 30 minutes during the first two hours and hourly after that, or whatever the clinic protocol says. Fields for BP, cramp score, needle site issues, dialysate temperature, blood pump speed, dialysate flow rate, venous pressure, arterial pressure, transmembranous pressure, heparin dosing, saline bolus events, and any extra fluids or medications given. Post-treatment block: end weight, total ultrafiltration removed, total blood volume processed, session duration, actual Kt/V if your machine calculates it, dialysate conductivity at start and end, and clinician signature. The exact layout depends on whether you're doing standard triweekly hemodialysis, nocturnal home HD, or pediatric treatments. The template should have a dropdown or checkbox for treatment type so you aren't filling out fields that don't apply.
How to Build One Without Overcomplicating It
I've seen people try to make these in Excel with conditional formatting and data validation until the file takes ten seconds to open. Don't do that. Use a clean grid layout with fixed column widths. Merge cells only where it actually matters, like headers that span multiple rows. Start with the bare minimum fields. If a field isn't used by your nursing staff within two weeks, remove it. I spent three months tracking dialysate sodium drift manually on a custom template before realizing nobody was checking it consistently. The field stayed for six more months because someone thought it looked thorough. It didn't improve anything. I removed it and went back to focusing on BP trends and ultrafiltration profiling. Here's the structure I recommend:
Get the Full Details
- Row 1: Header with clinic name, form title, revision date
- Row 2-4: Patient demographics and treatment prescription
- Row 5-8: Pre-treatment vitals and access details
- Row 9: Intra-treatment table with time columns and parameter rows
- Row 10: Post-treatment summary
- Row 11: Signatures and notes
Keep the intra-treatment section wide enough for six to eight time points. Most four-hour sessions need at least six entries. More than that and the form gets ridiculous on a single page. Last year, my unit switched to a new EMR and the lab wanted the flow sheet exported as a PDF at the end of each shift. The problem was that our nurses entered blood pressures in different formats. Some wrote "120/80", others wrote "120 over 80", and one guy just wrote "118". The export script broke because it expected a specific regex pattern. I couldn't change the EMR validation rules quickly enough, so I built a preprocessing step in a simple Python script that parsed the common formats and standardized them before the PDF generation ran. The script took about twenty minutes to write and saved me from getting called at 6 PM every evening to fix broken exports. It also flagged entries that were clearly outside clinical ranges so I could catch transcription errors. That might sound like overkill for a flow sheet, but when you're dealing with audit readiness, even small data quality issues add up fast.
Fields You Should Never Skip
Some templates leave out the anticoagulant details because they assume the medication administration record covers it. It doesn't. The flow sheet needs to show heparin bolus dose, heparin infusion rate if used, citrate settings for regional anticoagulation, and any protamine reversal. Auditors look at this section first when they're assessing bleeding risk management. Also never skip the access type field. Arteriovenous graft versus fistula versus catheter matters enormously for infection tracking and access revision planning. I've seen three separate clinics use different terminology for the same access type on their forms. Standardize it to SNOMED or just pick three clear labels and stick with them.
Common Pitfalls
Over-engineering is the biggest one. People add fields for things that might be useful someday. The result is a form that nurses partially complete because it takes too long. An 80% complete flow sheet is worse than a 100% complete one with fewer fields. Keep it tight. Another mistake is putting the post-treatment block at the top. Nurses fill forms top to bottom. If the post-treatment section is first, they either skip it or fill it out prematurely with guesses. Always put treatment outcomes last. Kt/V documentation is another area where people cut corners. Some templates just have a box for "Kt/V prescribed" and leave the calculated value blank. That's insufficient. If your machine generates a session Kt/V or uKt/V, capture it. If not, include a simple field for the Booker estimate inputs so someone can retroactively calculate it if needed.

When a Template Won't Help
A paper-based or even a well-designed digital template doesn't solve the problem of inconsistent nursing documentation. If your staff is rushing between patients and skipping vital sign entries, a prettier form won't fix that. In those cases, you need workflow changes, not a new template. Consider placing reminder stickers at nurse stations or integrating mandatory field checks into your EMR if you have the budget for it. The template is only as good as the people filling it out. Make it simple enough that completing it quickly doesn't require thinking too hard about which box goes where.
Distribution and Versions
If you want a ready-made Hemodialysis Flow Sheet Template, you can pull a basic version from most hospital supply portals or modify one from a dialysis equipment vendor's documentation page. The ones from vendors like Fresenius or B. Braun tend to align well with their machine outputs, which reduces manual data entry. If you use a different machine brand, you'll spend more time transcribing numbers anyway, so a generic template might be faster to work with. Whatever format you choose, put a version number and a revision date on the first page. Your accreditation surveyor will ask for it. I once had a surveyor pull a form from 2019 because the revision date was missing and we had to spend an hour proving it wasn't an outdated version still in circulation.
Integration With Electronic Systems
Most modern clinics use something like Epic, Cerner, or a dedicated dialysis-specific EHR. The template should be compatible with your system's export format. If your EMR auto-populates machine data, leave those fields read-only so nurses don't accidentally overwrite correct values. I've seen that happen twice in one month and it made the audit trail look suspiciously clean. If you're running a paper-based system, scan the completed sheets within 24 hours of treatment. Paper gets lost. It sounds obvious but I've found missing flow sheets in cabinets that were supposed to be digitized and never were. A simple daily checklist for the charge nurse helps prevent that.
What to Check Before Rolling It Out
Test the template with two nurses for a week before full deployment. Ask them to fill it out during actual treatments, not in a training session where they have time to think about it. The friction points will show up immediately. If someone asks what a field means three times in an hour, redesign that section. Simple as that. Also check whether your quality improvement committee has specific data points they want tracked. They usually do. If your template doesn't include their required metrics, they'll complain later and you'll have to redo it anyway. Get buy-in upfront instead of revising it mid-cycle. The Hemodialysis Flow Sheet Template is one of those things that seems minor until an audit requires it. Spend an afternoon getting it right and you save yourself months of patchwork corrections.