Understanding The Vagus Nerve In Relation To Hernias
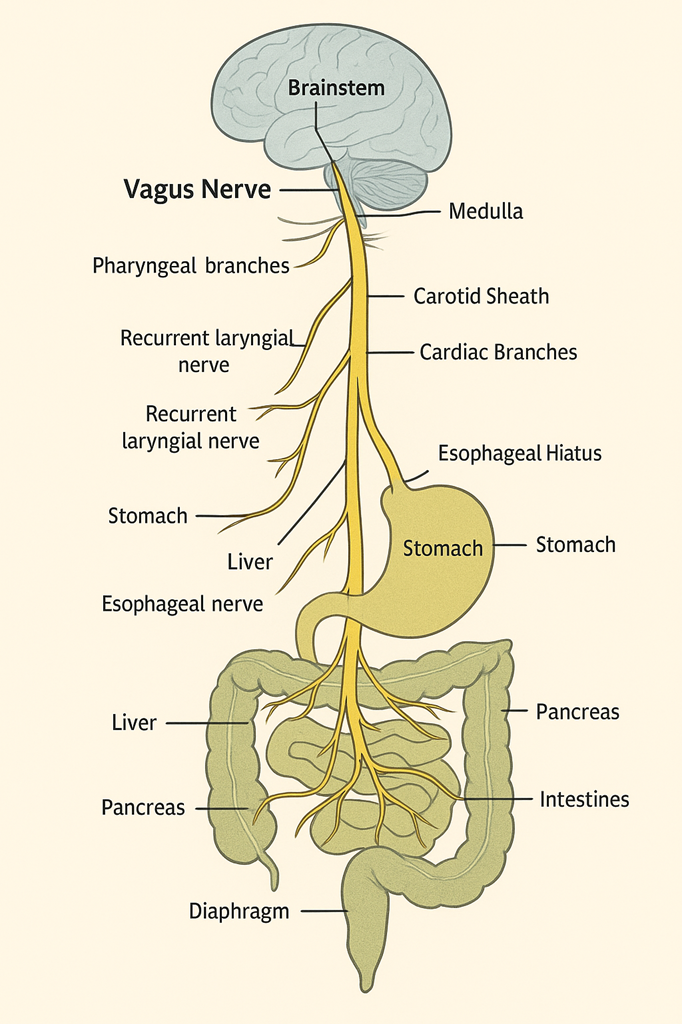
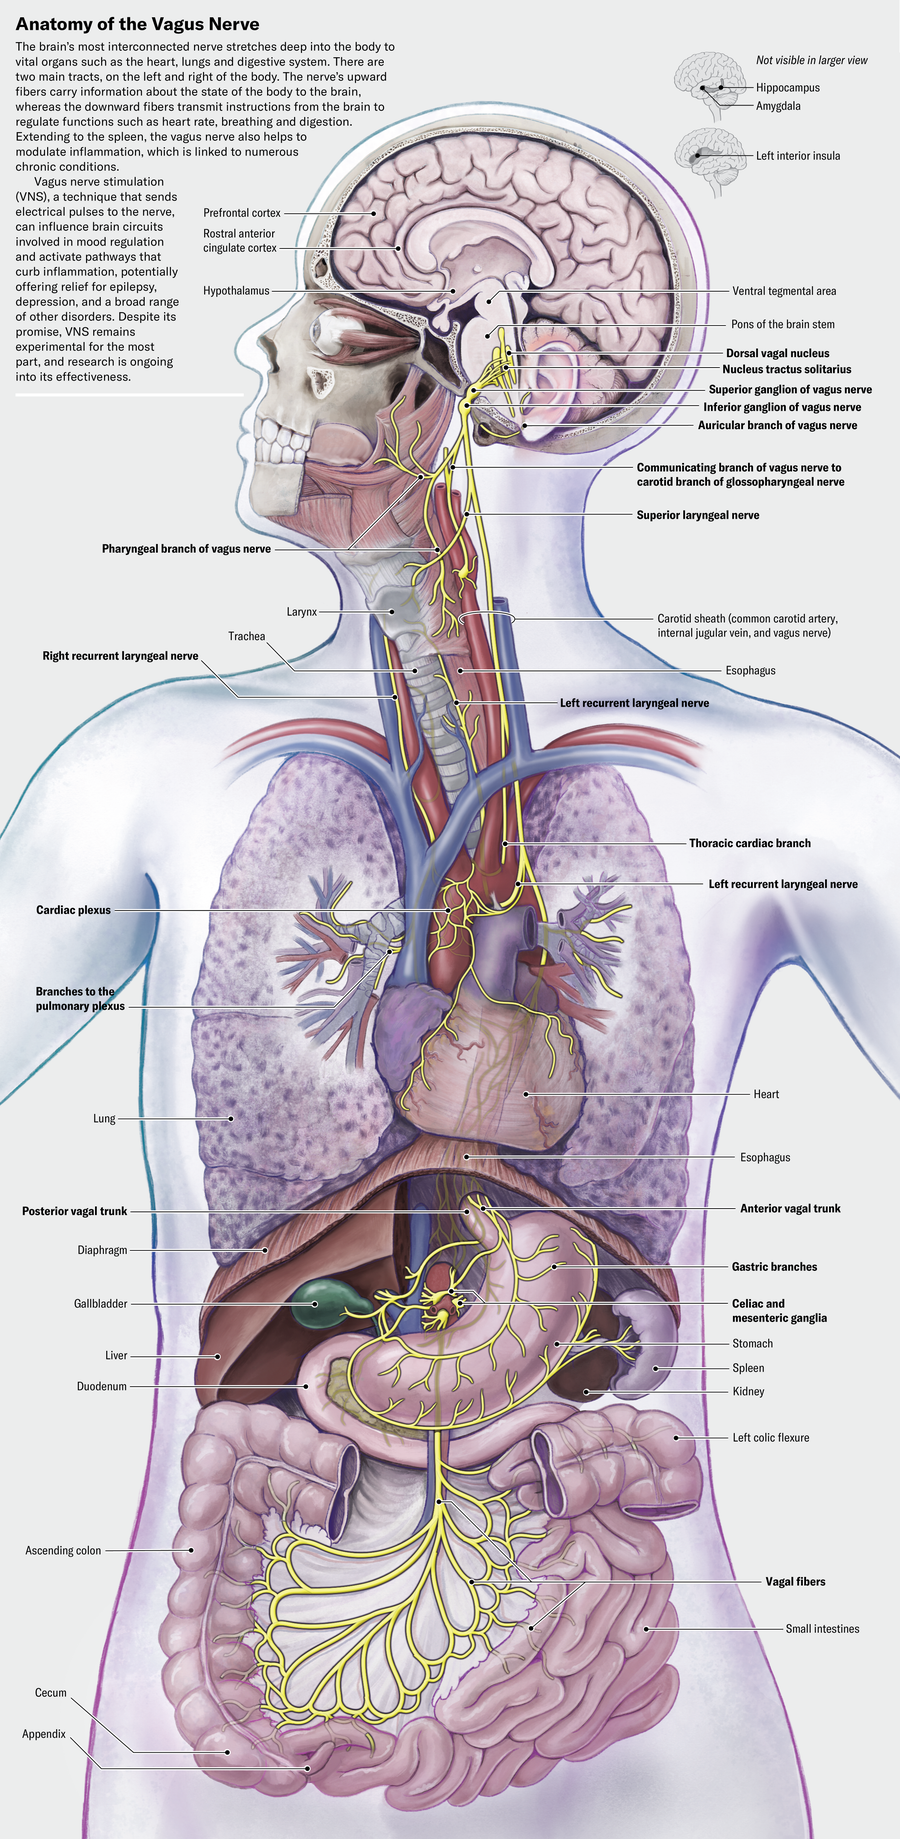
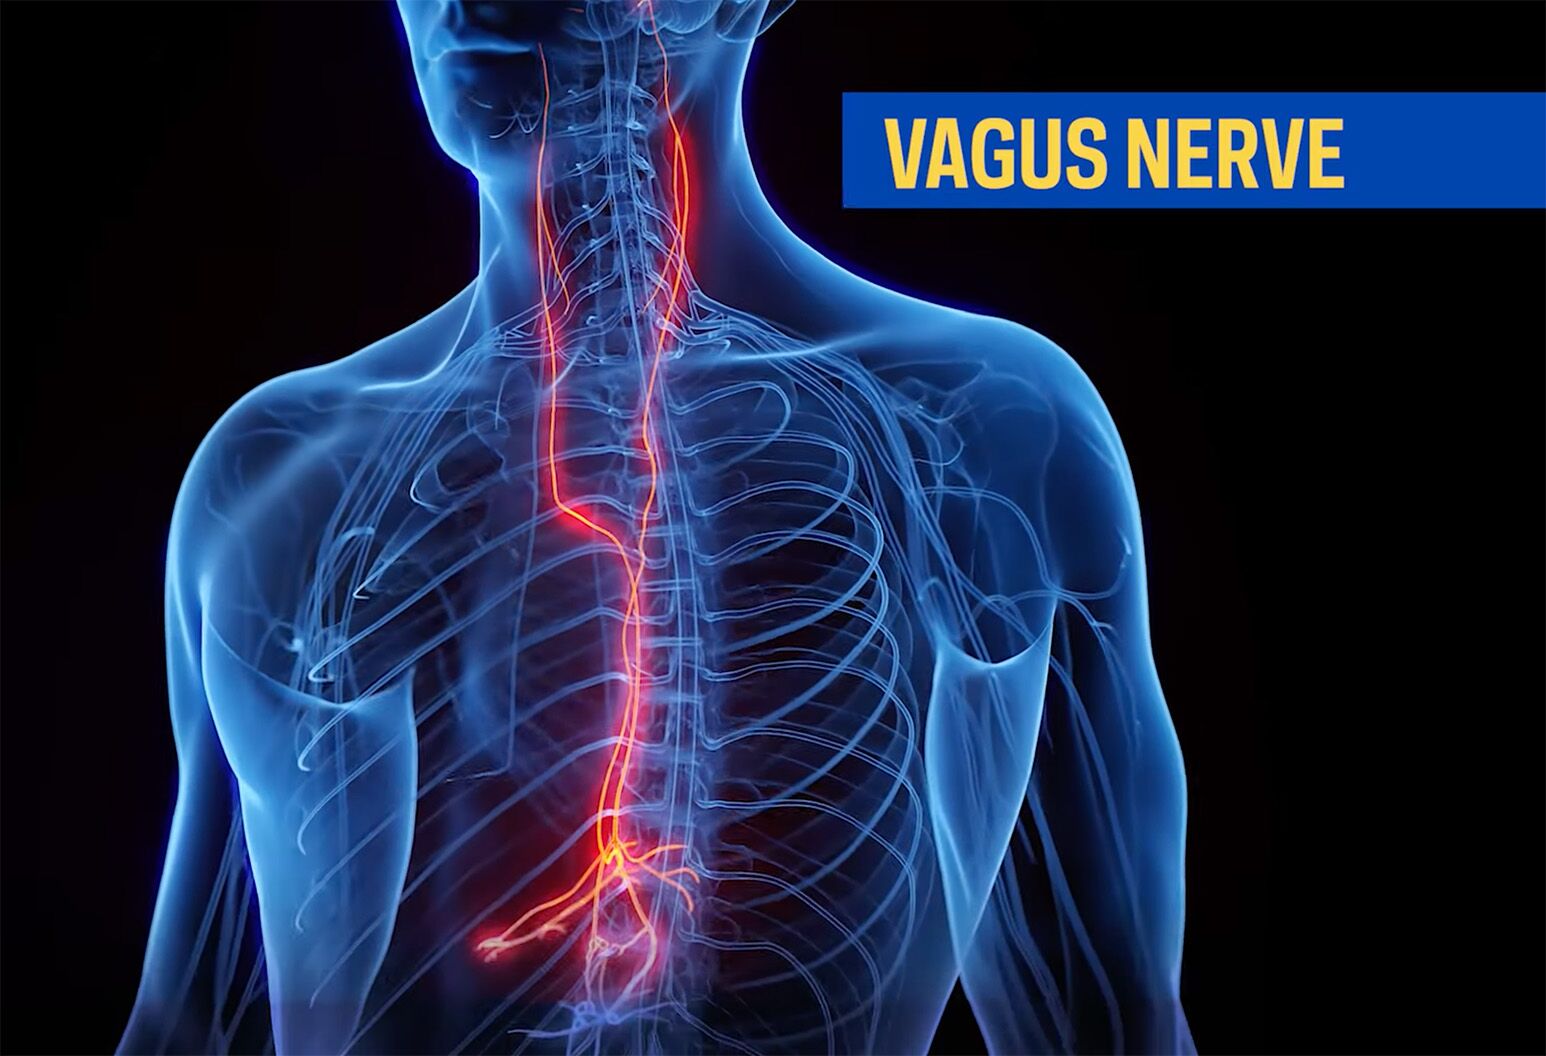
The vagus nerve runs from your brainstem down through your neck, chest, and abdomen. It's the longest cranial nerve in your body, innervating structures including the heart, lungs, and digestive tract. When it comes to hernias, the connection matters mostly in two contexts: hiatal hernias affecting vagal function, and surgical considerations during hernia repair. I've seen patients who developed vagal symptoms after hernia surgery without anyone explaining why. It happens more often than most surgeons want to admit. Let me walk through what actually goes wrong and how to deal with it.
What You Need To Know About Hernia And Vagus Nerve Connection
A hiatal hernia occurs when part of your stomach pushes up through the diaphragm into your chest cavity. The esophageal hiatus is the opening in the diaphragm where the esophagus passes through, and the vagus nerve travels alongside the esophagus at this point. When a hiatal hernia develops, it can stretch, compress, or irritate the vagal branches passing through that area. This is the primary anatomical link between hernias and vagus nerve dysfunction. The problem with hiatal hernias is that they don't always cause obvious symptoms. I had a patient last year who presented with unexplained bradycardia and occasional syncope. We ruled out cardiac causes first, which took about three weeks of testing. The real culprit turned out to be a paraesophageal hernia compressing the posterior vagal trunk. Once we repaired the hernia laparoscopically, his heart rate stabilized within 48 hours. The vagal compression was causing intermittent vasovagal episodes. There's also the reverse situation to consider. During open hernia repairs, especially large ventral or incisional hernias, the dissection near the diaphragmatic attachments can inadvertently damage vagal branches. Surgeons are taught to be careful here, but the anatomical relationships are tricky. I've reviewed operative reports where the surgeon explicitly noted "dissection near the esophageal hiatus" and subsequent post-op records showed signs of vagal irritation - gastroparesis, prolonged gastric emptying, nausea that wouldn't resolve.
Surgical Considerations Involving The Vagus Nerve
If you're scheduled for hernia repair and you're worried about vagal complications, there are things you can do before and after surgery to minimize risk and catch problems early. Before surgery, ask your surgeon about their approach to the diaphragmatic crura, especially for hiatal or large upper abdominal hernias. A laparoscopic approach generally carries less risk of vagal injury than open surgery because there's less blunt dissection and better visualization. However, laparoscopic repair has its own tradeoffs. The pneumoperitoneum required for laparoscopy increases intra-abdominal pressure, which can theoretically affect vagal tone during the procedure itself. Some patients report feeling unusually bradycardic during surgery - this is usually transient and monitored closely by anesthesia, but it's worth noting in your pre-op discussion. After surgery, pay attention to certain symptoms. Vagal dysfunction after hernia repair typically presents as one or more of the following: persistent nausea or vomiting, early satiety, bloating after small meals, unexplained heart rate changes, dizziness or fainting episodes, and in rare cases, hoarseness or swallowing difficulties. The last one suggests the recurrent laryngeal branch of the vagus may be involved.
Get the Full Details

Here's something most patients don't know: vagal symptoms after hernia surgery can appear immediately or be delayed by several weeks. I've seen cases where patients felt fine post-op and then developed significant gastroparesis three weeks later as post-surgical inflammation settled around the vagal branches. If symptoms develop progressively rather than immediately, don't assume it's just normal recovery. Get it checked. For managing post-surgical vagal symptoms, the usual approach starts conservative. Prokinetic medications like metoclopramide or erythromycin can help with gastric emptying issues. Low-dose beta-blockers may help with heart rate dysregulation. Most cases resolve on their own within six to eight weeks as inflammation subsides and the nerve recovers. If symptoms persist beyond that window, you should be referred to a gastroenterologist for gastric emptying studies and possibly vagal function testing. In the rare cases where vagal injury is confirmed and doesn't resolve conservatively, surgical exploration may be necessary to decompress or repair damaged vagal branches. This is uncommon but worth knowing about if your symptoms aren't improving. I'd also recommend keeping a symptom diary documenting when issues occur, their severity, and any triggers you notice. It sounds like a small thing but it's genuinely useful for your doctors to see patterns over time rather than relying on your memory during a rushed appointment.