What Actually Helps When You Have a Herniated Disc
Most people I see online are either dangerously aggressive with their rehab or completely immobilized because they're scared of re-injury. Both extremes make things worse. The reality sits somewhere in the middle, and it's not very glamorous. Let me be straightforward about what Herniated Disc Exercises actually do and don't do. They don't "fix" the herniation in the way people hope. The body resorbs disc material on its own timeline, usually 6 to 12 months for significant improvement. What exercise does is manage symptoms, improve mechanical function, and prevent recurrence. That's it. Anything promising faster or more dramatic results is selling something.
Getting Started With Herniated Disc Exercises Safely
The McKenzie method is where most people should begin, but not everyone responds the same way. About 70% of lumbar disc herniations are posterior or posterolateral, which means extension-based movements tend to help. The other 30% or so — and this is critical — won't respond to extension at all. Some will get worse. I've had patients who spent weeks doing prone press-ups and then came back with worse sciatica because their herniation had a different anatomical orientation than assumed. Here's the sequence I recommend starting with. Begin with prone lying for two to three minutes. Just lie on your stomach, arms at your sides, palms down. If that doesn't aggravate symptoms after 90 seconds, progress to prone on elbows, holding for 30 seconds to a minute. Then move to press-ups: hands under shoulders, lower body still on the floor, gently push your upper body up while keeping hips contact. Do 10 repetitions, resting 30 seconds between each. If leg pain centralizes — moves from the calf or thigh back toward the lower spine — that's a good sign. If it peripherals or intensifies, stop and reassess. Neural gliding is another cornerstone that most people skip entirely. Sit on a firm chair, extend the affected leg with the heel on the floor, and gently nod your head forward and back while point-and-flexing the ankle. Five sets of 10 repetitions. The goal isn't stretching — it's gentle movement of the nerve through its sheath to prevent adhesion formation. Static stretching of the sciatic nerve actually makes things worse in the acute phase. There's a difference between mobilizing neural tissue and irritating it, and people routinely confuse the two.
The Things Nobody Tells You
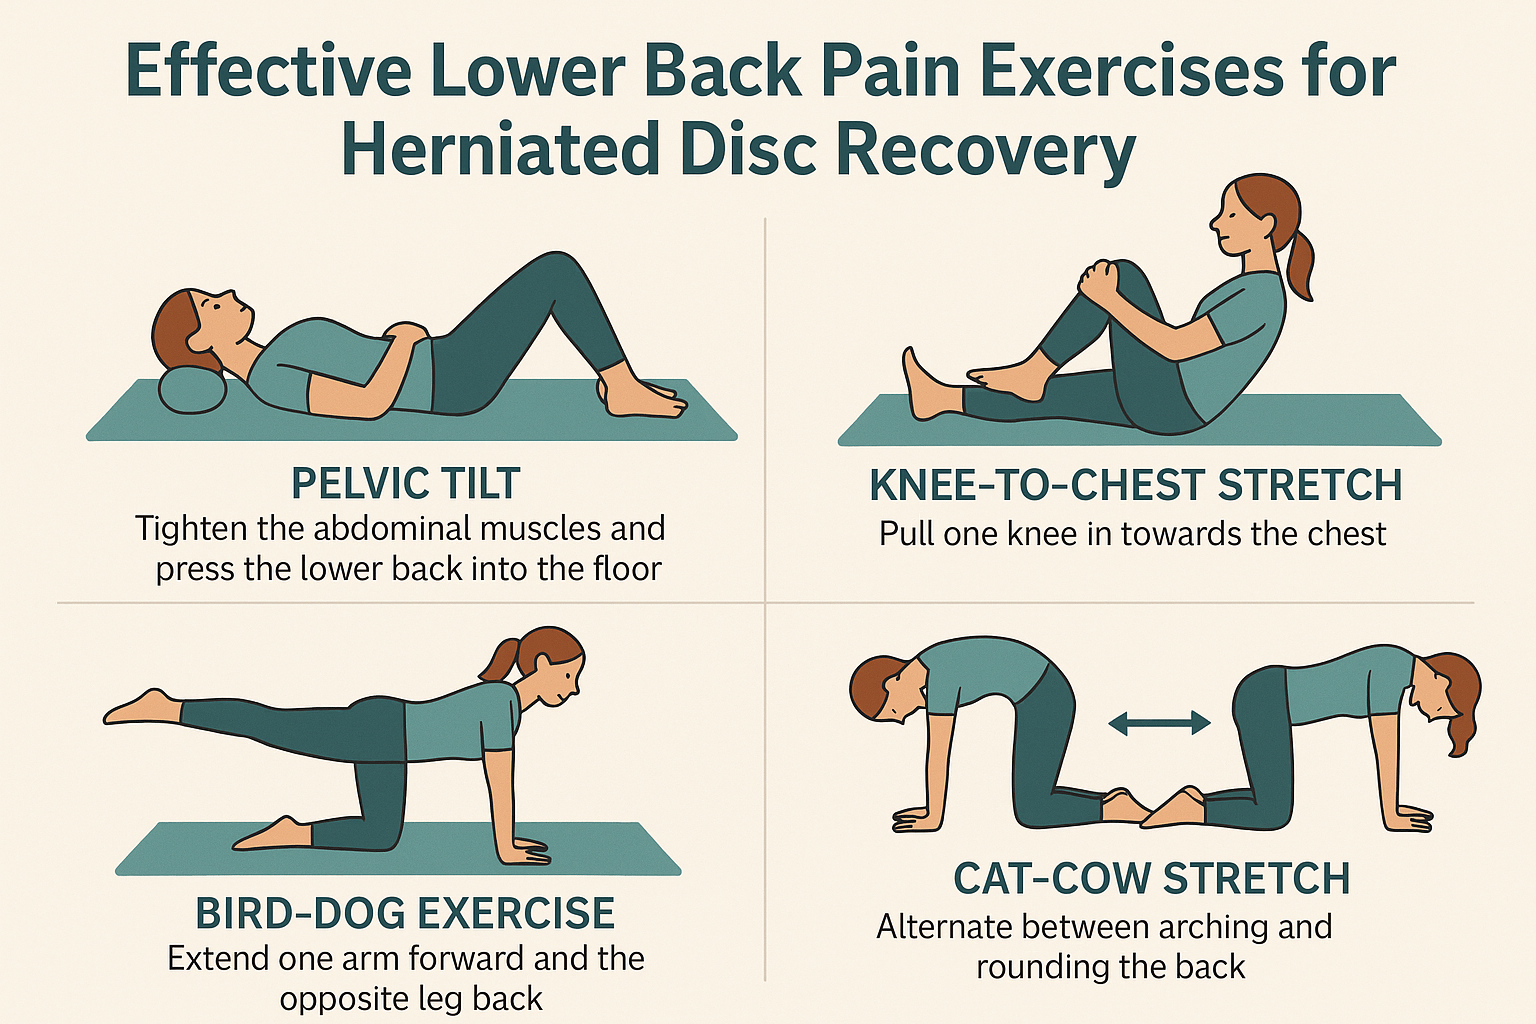
Core stability work matters, but the timing is everything. Planks and bird-dogs are fine once the acute inflammatory phase subsides, which typically takes 5 to 7 days for most people. Doing them during the first week when nerve root inflammation is at its peak will just add mechanical load to an already irritated structure. I learned this the hard way with a patient who was doing dead bugs on day three of an acute episode because a fitness influencer said it was "gentle core work." He ended up back on disability for another six weeks. Hip flexor tightness is a silent amplifier of lumbar disc problems. The psoas connects directly to the lumbar vertebrae, and when it's chronically shortened from sitting, it pulls the lumbar spine into increased lordosis. That increases posterior disc pressure by roughly 40% compared to a neutral position. Hip flexor stretches done supine, holding for 60 seconds per side, three times daily, are more impactful for disc loading than most people realize. The stretch should be felt in the front of the hip, not the lower back. If you feel it in your back, you're arching instead of tilting the pelvis. Nerve flossing frequency is another area where people go too far. More is not better. Three to five sessions per day, spaced out, is the effective range. Beyond that, you're just re-aggravating the same tissue without giving it recovery time. I've seen patients do nerve flossing every hour "to be safe." It didn't help. It made their symptoms fluctuate more and delayed actual improvement by weeks.
Get the Full Details

What Doesn't Work and Why
Hamstring stretching in the acute phase is counterproductive. Tight hamstrings are often a protective splinting response from the nervous system, not the primary problem. Aggressive stretching during this phase triggers a stretch reflex that increases muscle guarding and can worsen nerve root irritation. Address hamstrings later, during the remodeling phase, not during the initial inflammatory window. Twisting motions should be avoided entirely for at least the first three weeks. The lumbar discs bear the highest torsional load during combined flexion and rotation. Even gentle rotational stretches like the supine knee drop can reload a healing disc if done too early. I had a client who was three weeks post-herniation and doing gentle yoga twists because her instructor said rotation was "good for mobility." She went from walking 20 minutes without pain to needing pain medication within a day. The disc hadn't healed enough to handle that load yet. Sitting is the enemy during recovery. Sitting increases intradiscal pressure by approximately 40% compared to standing and 140% compared to lying down. If you have a desk job, you need a standing arrangement or frequent position changes every 20 to 30 minutes. No exceptions. The 20-minute rule isn't arbitrary — it's based on how long disc hydration equilibrium holds before pressure builds back up to problematic levels.
Progression Timeline and Red Flags
Week one is rest and gentle McKenzie extensions only. Walk short distances, maybe 5 to 10 minutes at a time, two or three times per day. Walking is underrated for disc recovery because the rhythmic compression and decompression promotes fluid exchange in the disc without significant load. After week one, introduce nerve glides and begin core stabilization work if pain permits. Weeks three through six are where most people see the most meaningful improvement, assuming they haven't been doing things that aggravate the condition. Red flags that mean you need imaging and possibly a specialist referral: bowel or bladder dysfunction, saddle anesthesia, progressive motor weakness (foot drop, inability to stand on your toes or heels), or pain that doesn't improve at all after four to six weeks of conservative management. Cauda equina syndrome from a massive central disc herniation is rare but requires immediate surgical intervention. Don't wait and see with those symptoms. For the vast majority of people, Herniated Disc Exercises performed consistently and with proper progression will resolve symptoms within eight to twelve weeks. The ones who struggle are usually the ones who either push too hard too early or stop too soon because they think they're fine once the worst pain subsides. The inflammatory cascade doesn't stop the day the sharp pain disappears. The disc is still structurally compromised for months after acute symptoms ease. Continue the exercises through the full progression, even when you feel good.