
The Heska Allergy Manual Guide: What It Actually Is and How It Gets Used in Practice
If you have never touched a Heska Allergy Manual Guide before, the first thing you notice is that it is not a single booklet. It is a working set of materials — the manual itself, the vial labels, the dosing tables, the sample-handling notes, and the interpretation charts — that gets printed, reprinted, and annotated over years of practice. The system is built around Allercept hypersensitivity testing and immunotherapy preparation. It has been around long enough that most people who work with it have strong opinions about which steps matter and which can be glossed over, and honestly, most of those opinions are wrong in predictable ways. The manual guide covers a fairly narrow loop: skin or blood sample collection, antigen selection, allergy extract preparation, intradermal or serological testing, and then immunotherapy formulation when results indicate it is needed. The actual step most people rush through is sample handling, because the pre-analytical variables eat up test accuracy faster than anything else in the reagent chain. Here is what that looks like on a typical Tuesday. You draw a venipuncture or do an intradermal skin test, then you label the tubes, log the patient, and you are already thinking about the next case. That is where the manual guide earns its keep. The dosing tables and the sample stability notes are not decoration. They are the reason the allergen extracts do not degrade between collection and processing. The guide tells you how long a sample stays viable at room temperature, what the centrifugation parameters should be, and how to record the antigen panel so it maps cleanly onto the extract catalog.
What the Manual Actually Covers in Detail
Inside the Heska Allergy Manual Guide you will find section after section on test methodology, reconstitution ratios, storage temperatures, quality-control checkpoints, and result interpretation. It also covers the transition from positive test findings to custom immunotherapy formulation, because that is where the system does most of its work. The immunotherapy part is not optional. It is the whole point of running the allergy testing in the first place. The manual includes dosing protocols for the allergen extracts themselves, which are species-specific. Canine protocols differ from feline ones, and the guide makes that separation explicit. It also includes the antigen panel layout — the common inhalant allergens, the food-related markers when applicable, and the regional organism lists that change depending on where the clinic is located. If you are working in a area with high mold spore counts or a particular tree pollen season, the manual guide helps you choose the right panel instead of throwing a generic extract at the patient and hoping for the best.
Where People Go Wrong With the Heska Allergy Manual Guide
I ran into this repeatedly when I was first learning the workflow. The most common mistake is treating the sample stability guidance as approximate. It is not. A serum sample left at room temperature past the recommended window will show degraded antibody binding, and the interpretive charts in the manual do not warn you loudly enough about that. You end up with false positives or weak positives that look clinically significant but are actually artifacts of delayed processing. Another problem is antigen panel selection. The manual guide gives you a base panel, but every region has different allergen exposure patterns. If you are in a humid climate with heavy dust mite pressure, the standard panel might underrepresent what the patient is actually reacting to. I learned to cross-reference the local epidemiology data with the manual's regional notes rather than relying on the default list alone. That usually means adding or swapping a few antigens based on what local vets report, not just running the off-the-shelf panel every time. Storage is the third failure point. The allergen extracts have specific temperature ranges, and when people leave them at inconsistent fridge temperatures or expose them to light between uses, the potency drifts. The manual guide has storage tables, but they are easy to skim past. I started logging extract receipt dates, opening dates, and current storage temperatures in a simple spreadsheet. It takes about thirty seconds per vial, and it catches problems before they show up as inconsistent test results weeks later.
Get the Full Details

How Dosing and Administration Actually Work
The Heska Allergy Manual Guide includes detailed dosing schedules for immunotherapy. These are not one-size-fits-all. The induction phase, the maintenance phase, and the adjustment factors based on patient weight, response, and adverse reactions are all spelled out. The guide also covers when to modify doses — for example, if a patient has a pronounced local reaction at a particular antigen concentration, the manual tells you how to back off and rechallenge at a lower level. Administration routes matter too. The manual distinguishes between subcutaneous and intradermal approaches, and it gives guidance on which to use depending on the clinical question. For ongoing immunotherapy management, subcutaneous is far more common because it is easier to administer and monitor over time. The intradermal route is mostly reserved for diagnostic testing or special cases where you need finer-grained response data. One practical detail the manual emphasizes but people often miss is the documentation loop. Every dose needs a record: date, time, route, antigen concentrations, volume, patient weight, and any immediate reactions. This is not bureaucracy. It is the only way you can compare responses across visits and adjust the protocol intelligently. Without that paper trail, you are guessing, and guessing in allergy management leads to inconsistent outcomes.
Interpretation and Result Handling
When the test comes back, the manual guide gives you interpretive criteria. Positive, borderline, negative — each has thresholds based on the assay method and the patient's clinical context. The tricky part is that a positive lab result does not automatically mean clinical allergy. The manual stresses correlating test findings with history, physical exam, and sometimes elimination trials or response to treatment. There is also the question of which antigens to include in the final immunotherapy mix. The manual provides guidance on selecting antigens based on reactivity levels, clinical relevance, and regional exposure. It is not simply a matter of picking the top five positive reactions. Sometimes a moderate positive with strong clinical correlation is more useful than a high positive that does not match the patient's actual exposure pattern.
Quality Control and Troubleshooting
Good laboratory practice applies here. The manual includes quality-control recommendations: reagent verification, equipment calibration, operator training checkpoints, and result repeatability checks. These are not optional extras. They are the difference between a system that produces reliable data over months and one that drifts into inconsistency. When things go wrong — and they do — the manual guide offers troubleshooting paths. Common issues include weak positive controls, unexpected negative results in symptomatic patients, or extract potency degradation. The manual helps you determine whether the problem is pre-analytical, analytical, or interpretive, which is important because the fix is different in each case.
Storage, Shelf Life, and Stability Notes
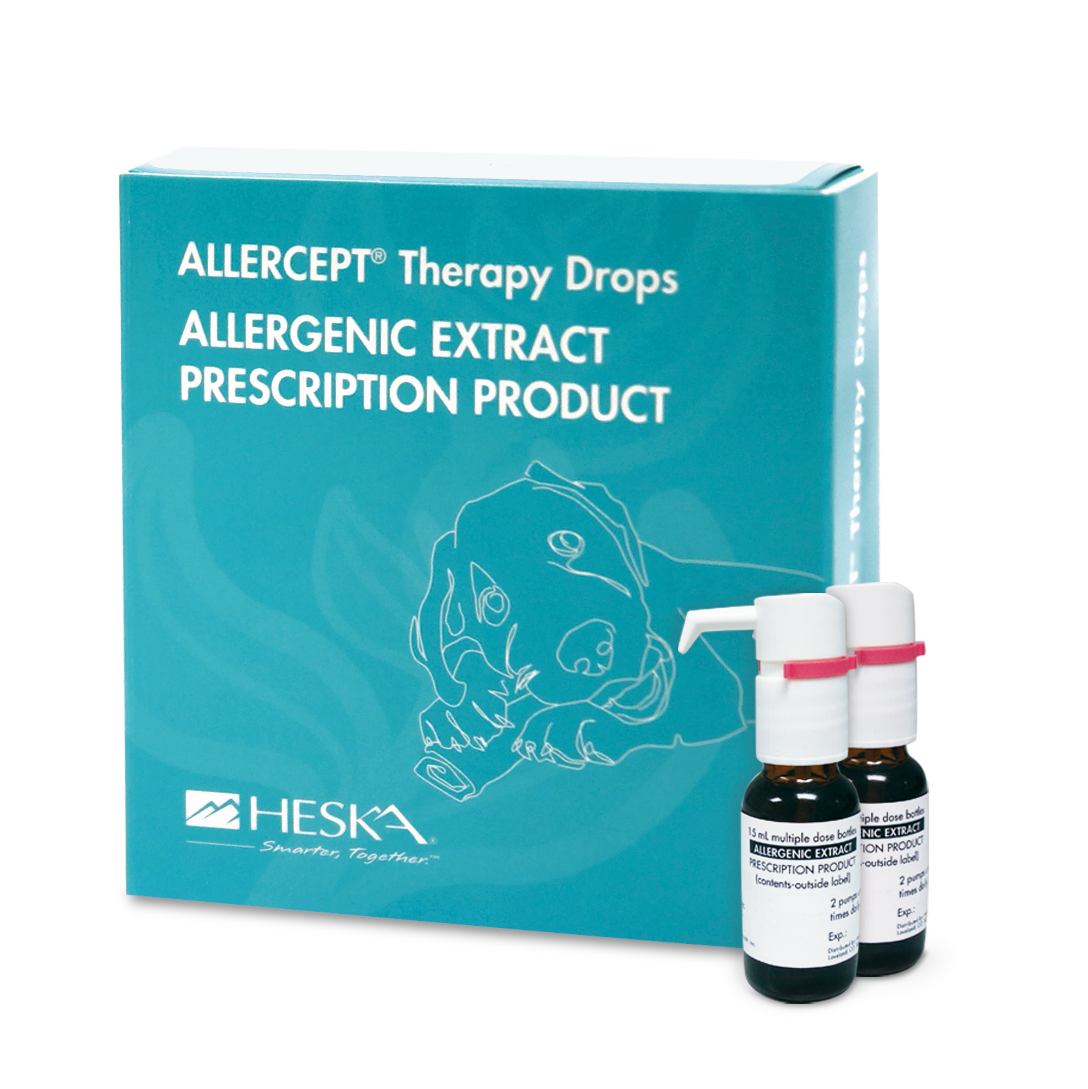
The manual provides shelf-life information for the allergen extracts and the reagents used in testing. These numbers matter. Using an expired or improperly stored extract skews results, and the guide explains how to recognize and avoid that problem. Refrigeration temperature monitoring, light protection, and proper labeling are all covered in detail. One thing the manual makes clear is that once a vial is opened, the stability clock changes. The guidance on post-opening use timelines is specific, and ignoring it leads to subtle potency loss that is hard to detect without careful record-keeping.
Practical Tips for Working With the Heska Allergy Manual Guide
Start by reading the sections on sample handling before you ever draw a sample. The pre-analytical guidance is where most errors originate, and knowing it ahead of time prevents costly mistakes. Keep the manual nearby during testing sessions. The dosing tables and interpretation charts are reference material, not something you memorize. Having it accessible during the procedure reduces the chance of transcription errors or skipped steps. Document everything. Patient records, test dates, extract lot numbers, storage conditions, dose adjustments, and adverse reactions. This creates a searchable history that becomes invaluable when you are managing chronic allergy cases over months or years.
Train your team on the workflow. The manual is only as good as the people using it. Consistent technique, clear communication, and shared understanding of the protocols make a measurable difference in result reliability.

Limitations and When the Manual Guide Is Not Enough
No manual replaces clinical judgment. The Heska Allergy Manual Guide provides structured guidance, but it cannot account for every patient variation, every regional allergen difference, or every unexpected reaction. It is a framework, not a complete solution. Additionally, the manual is specific to the Heska system and its reagents. If you switch to a different testing platform or supplier, the protocols and dosing may differ. The principles remain similar, but the specifics change, and you need to adapt accordingly. Finally, allergy testing and immunotherapy are evolving fields. New research, updated guidelines, and improved reagents may alter best practices over time. The manual provides current guidance, but staying informed beyond the manual is important for optimal patient care.
Bottom Line
The Heska Allergy Manual Guide is a practical, detailed resource for veterinary allergy testing and immunotherapy management. It covers everything from sample collection to dose adjustment, with an emphasis on consistency, documentation, and clinical correlation. Used correctly, it improves test reliability and treatment outcomes. Used carelessly, it is just paper. The difference is in how carefully you follow the guidance, how thoroughly you document, and how willing you are to adapt the manual's recommendations to the realities of your practice and your patients.


